Treatment Strategies for the Edentulous Jaw: Fixed Prosthesis Maxilla1
Treatment Options2
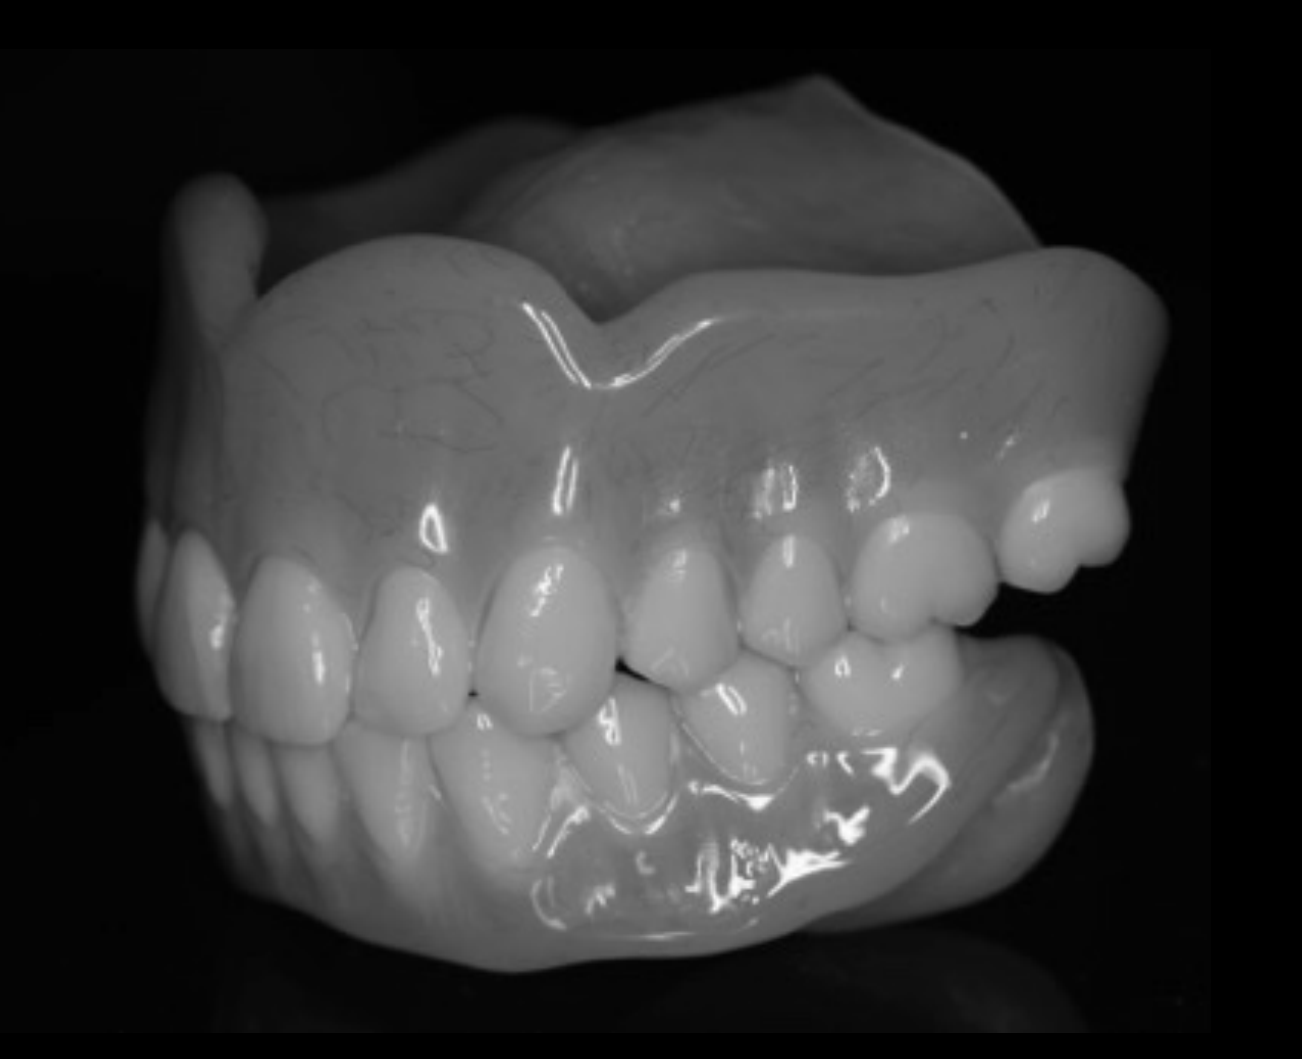
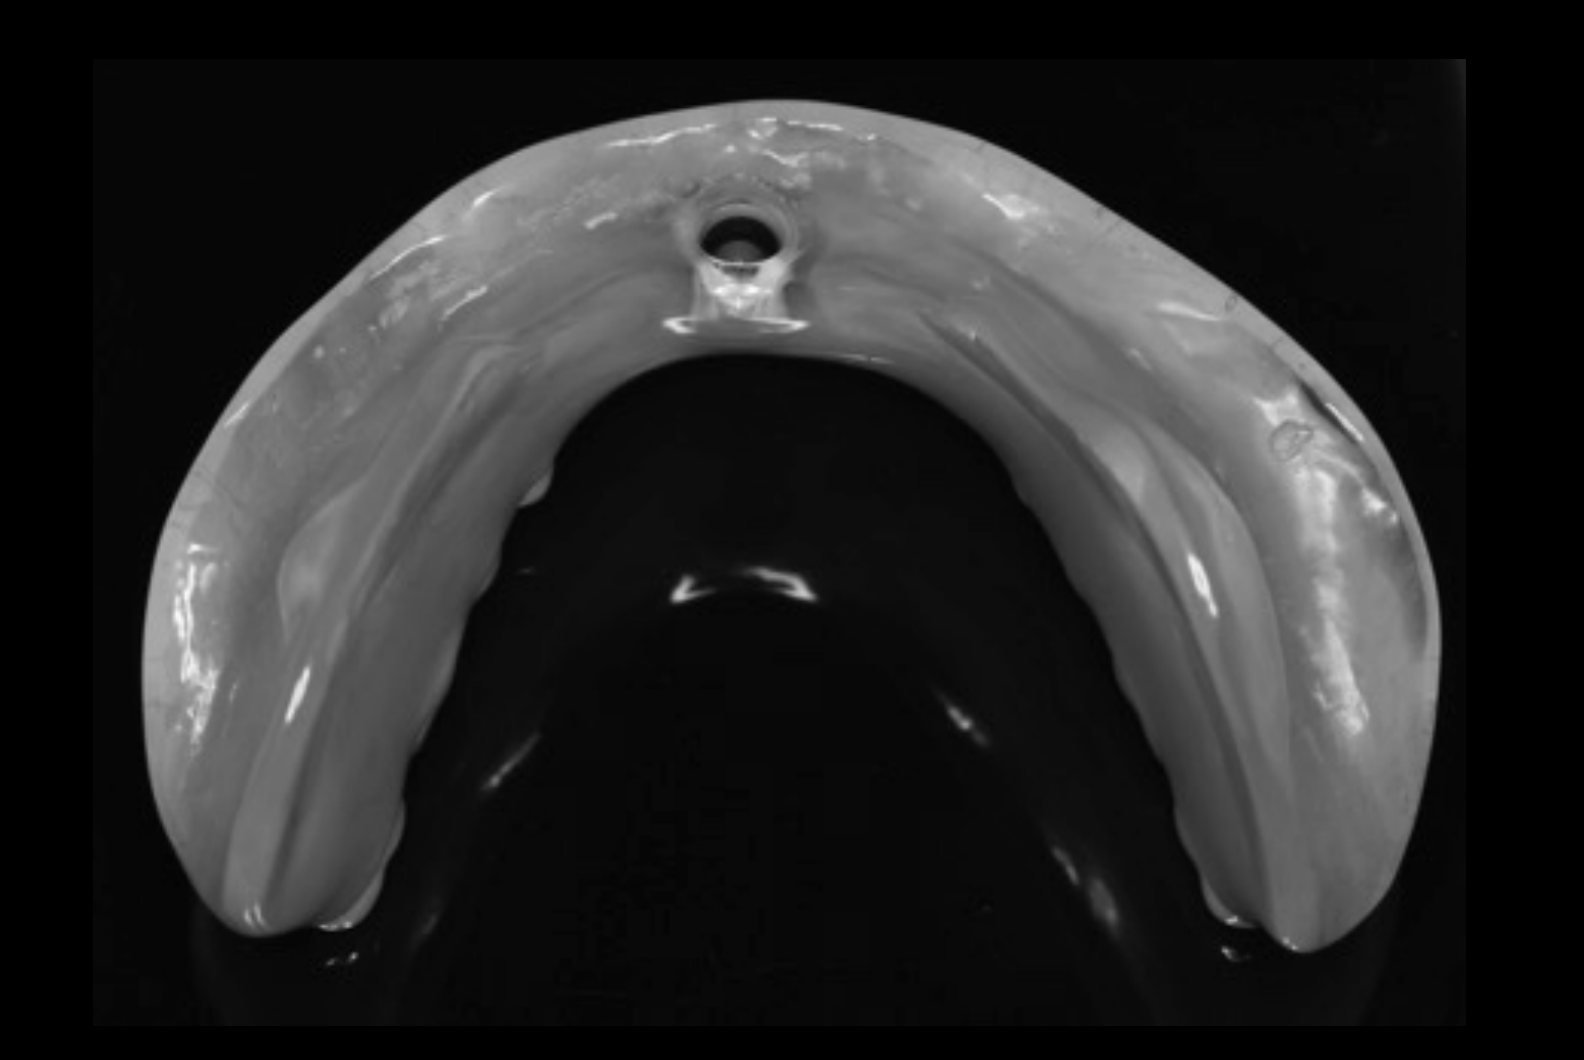
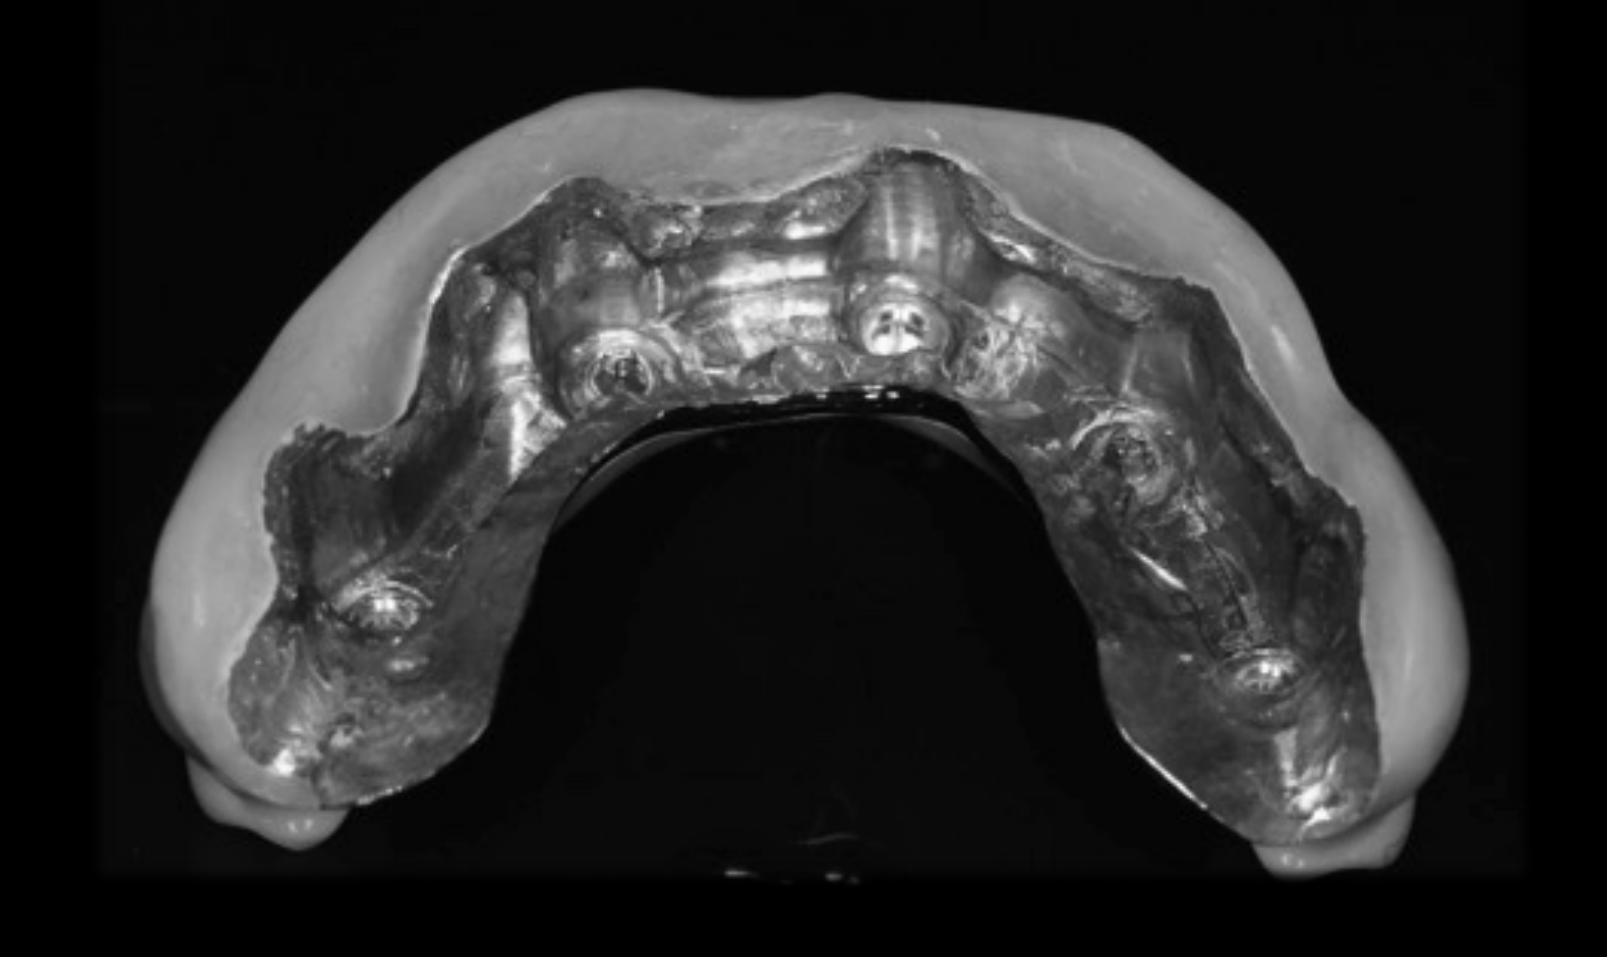
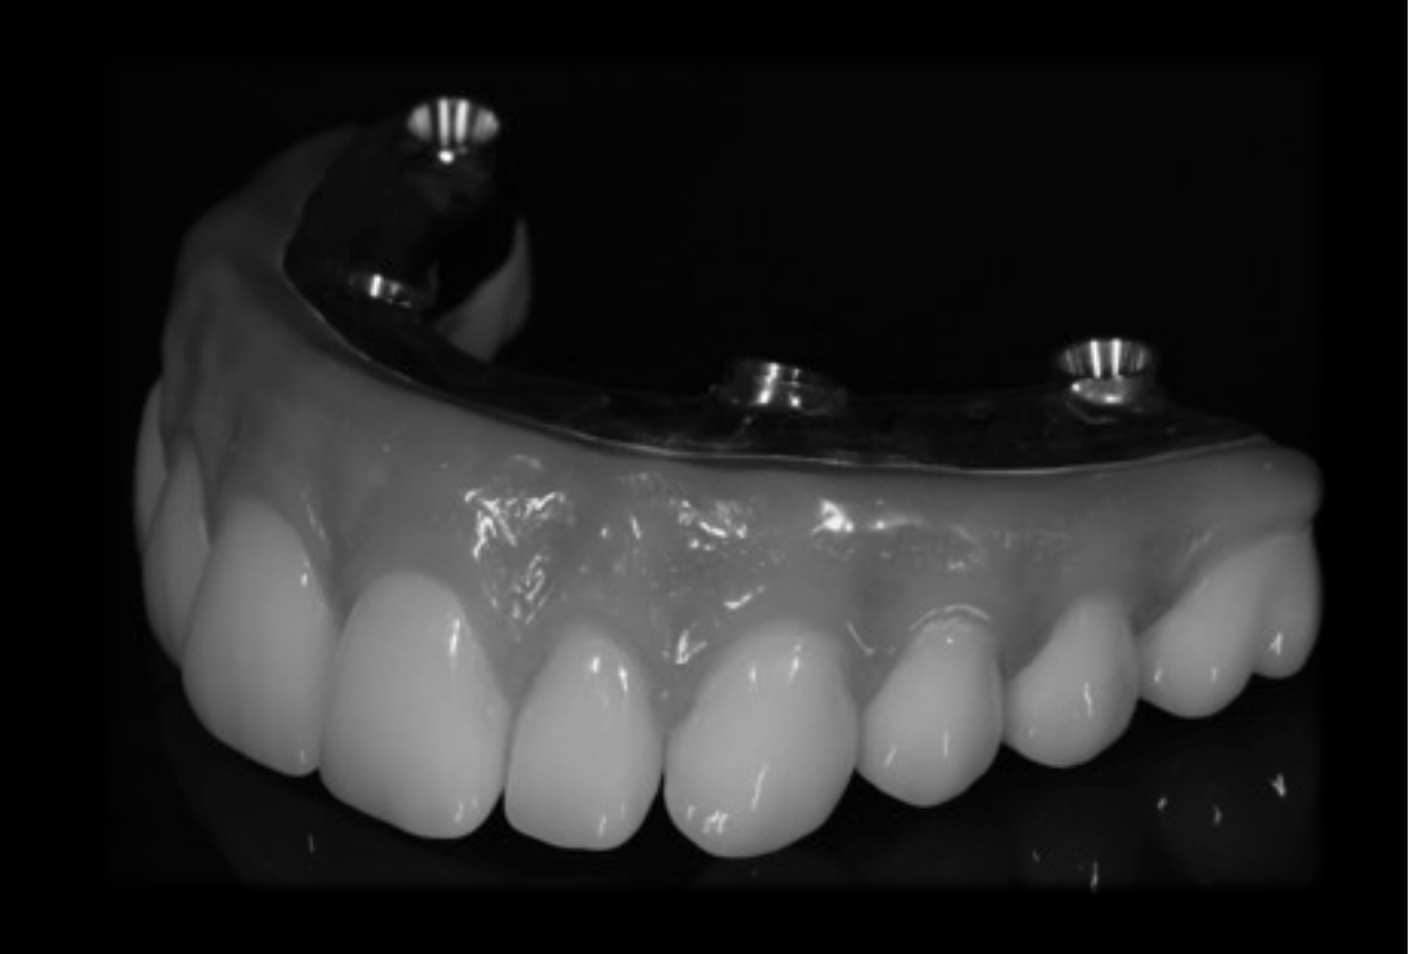
- Complete Denture
- Implant Overdenture
- Implant Detachable Prosthesis
- Fixed Prosthesis
 |  |
 |  |
Lecture Introduction34
Lecture 35
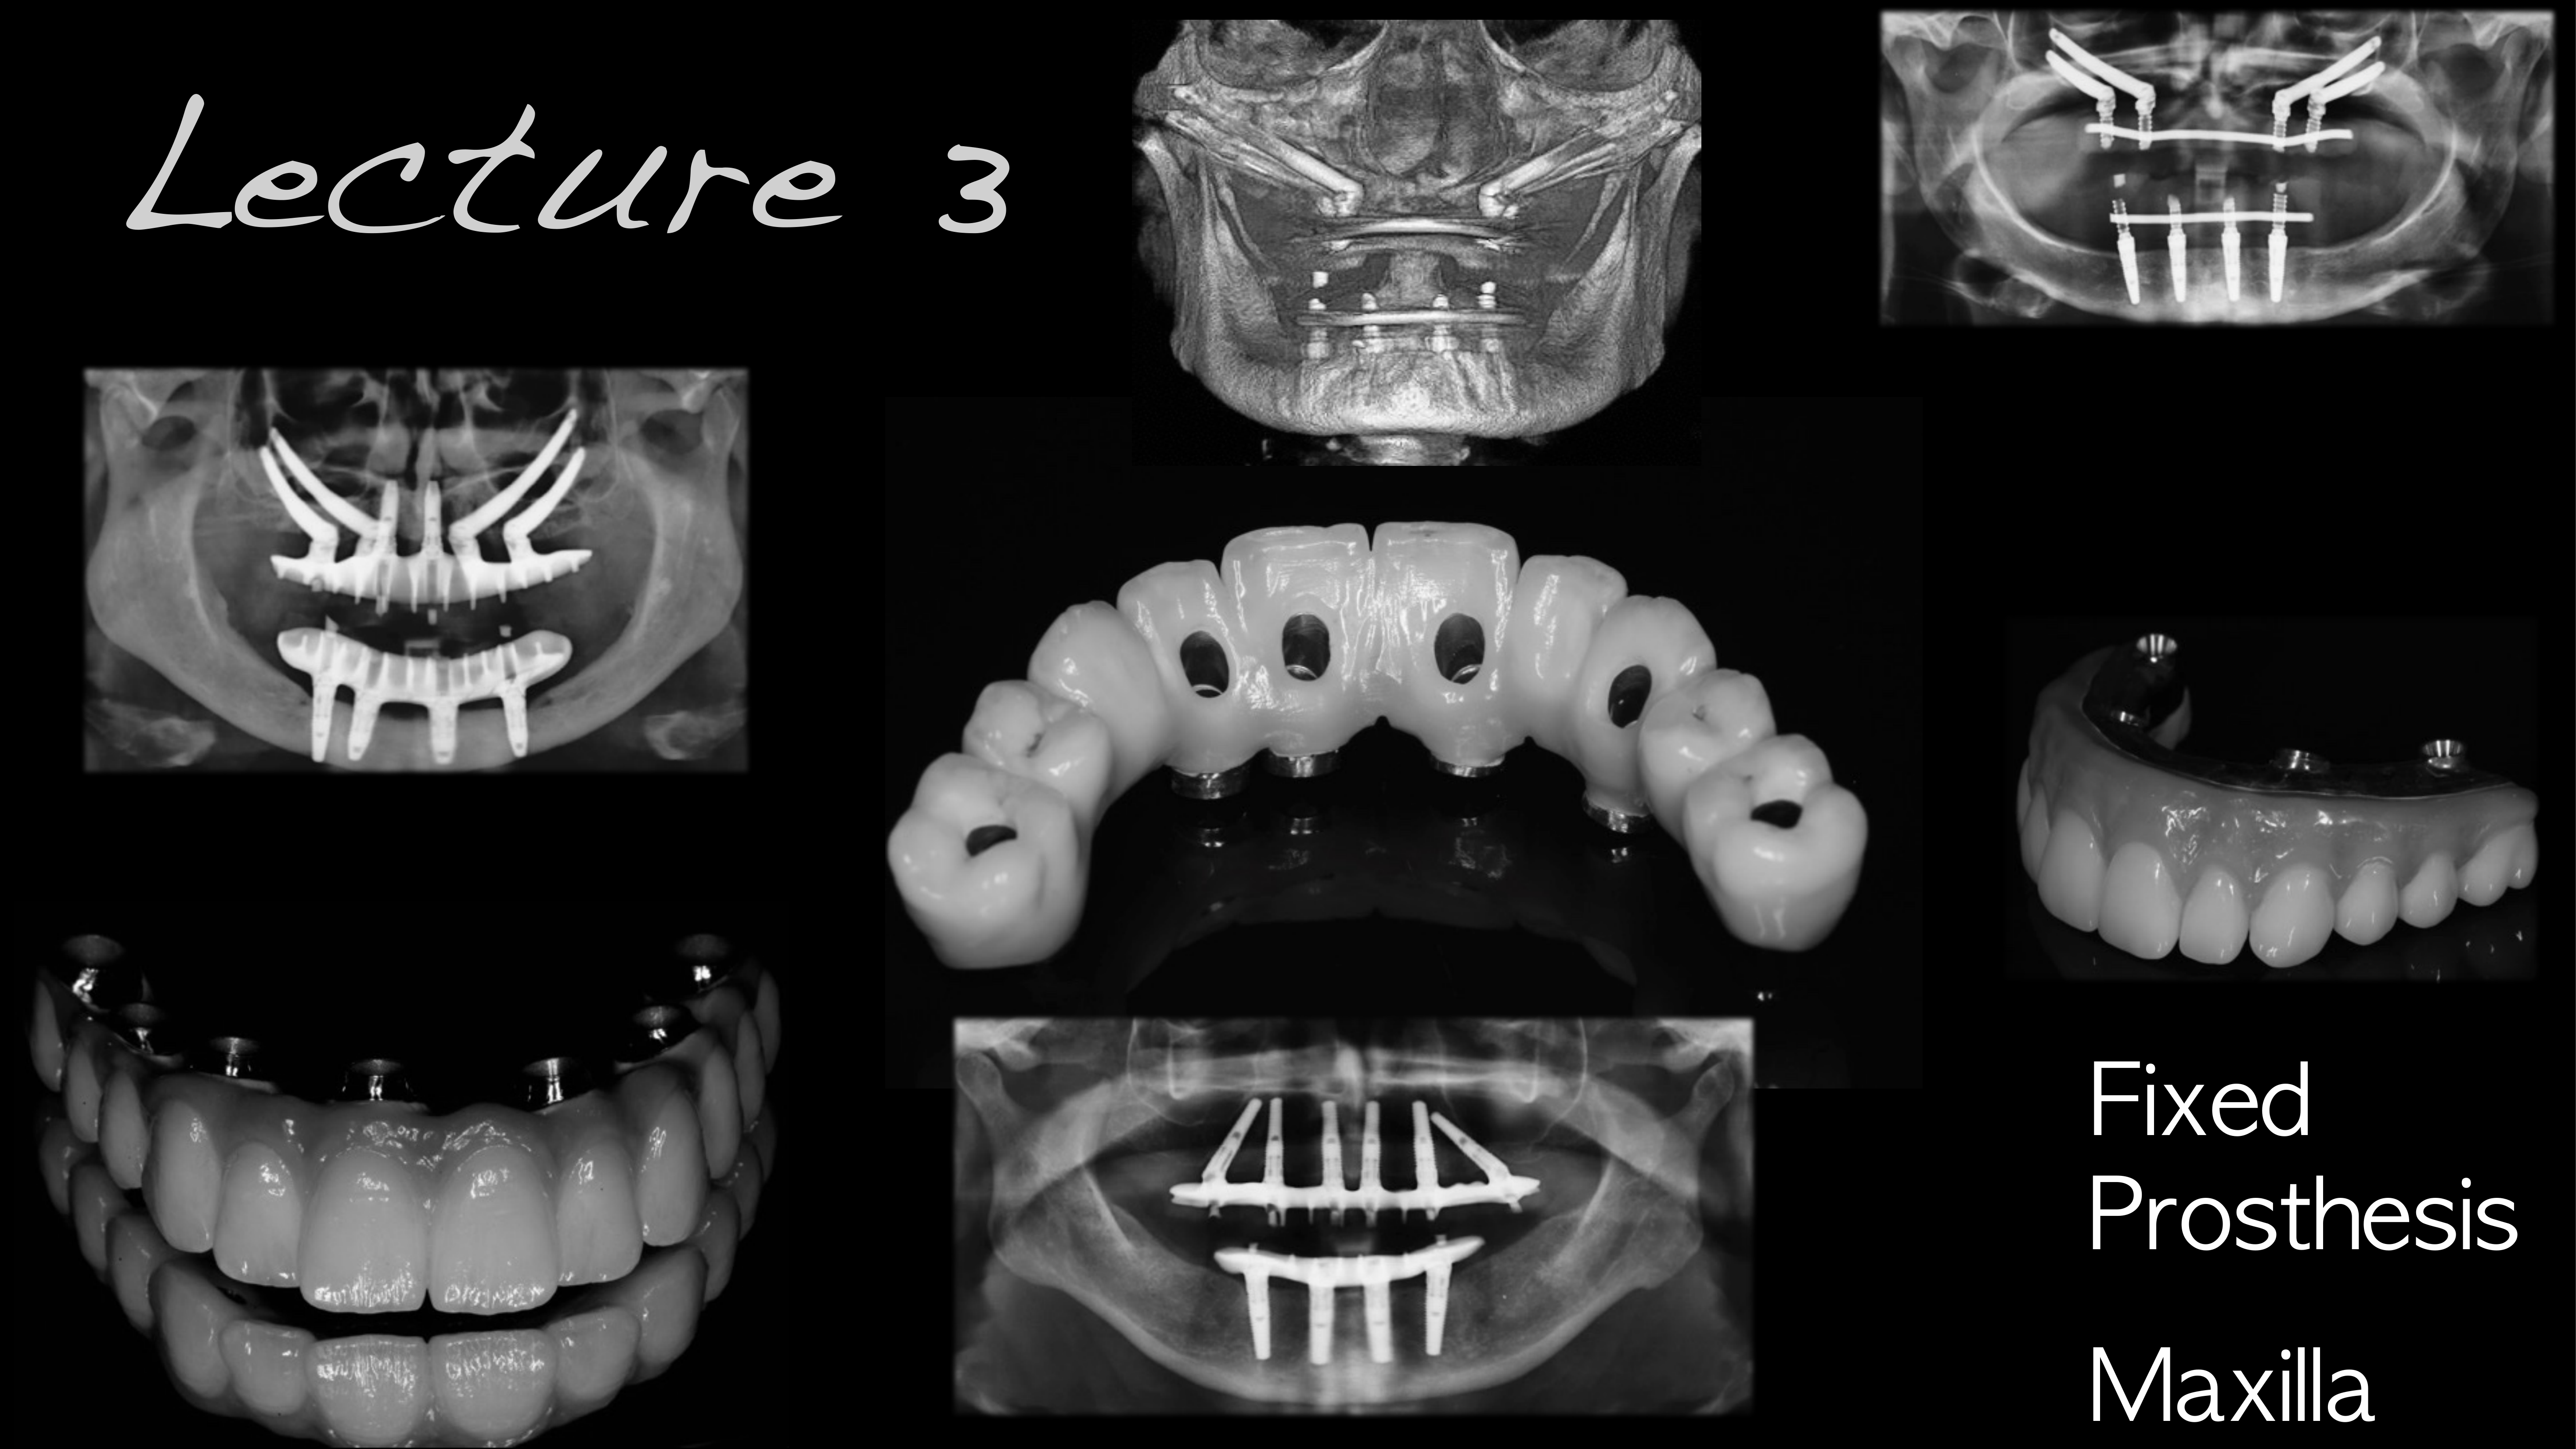
Fixed Prosthesis: Maxilla
Treatment strategies for the edentulous jaw
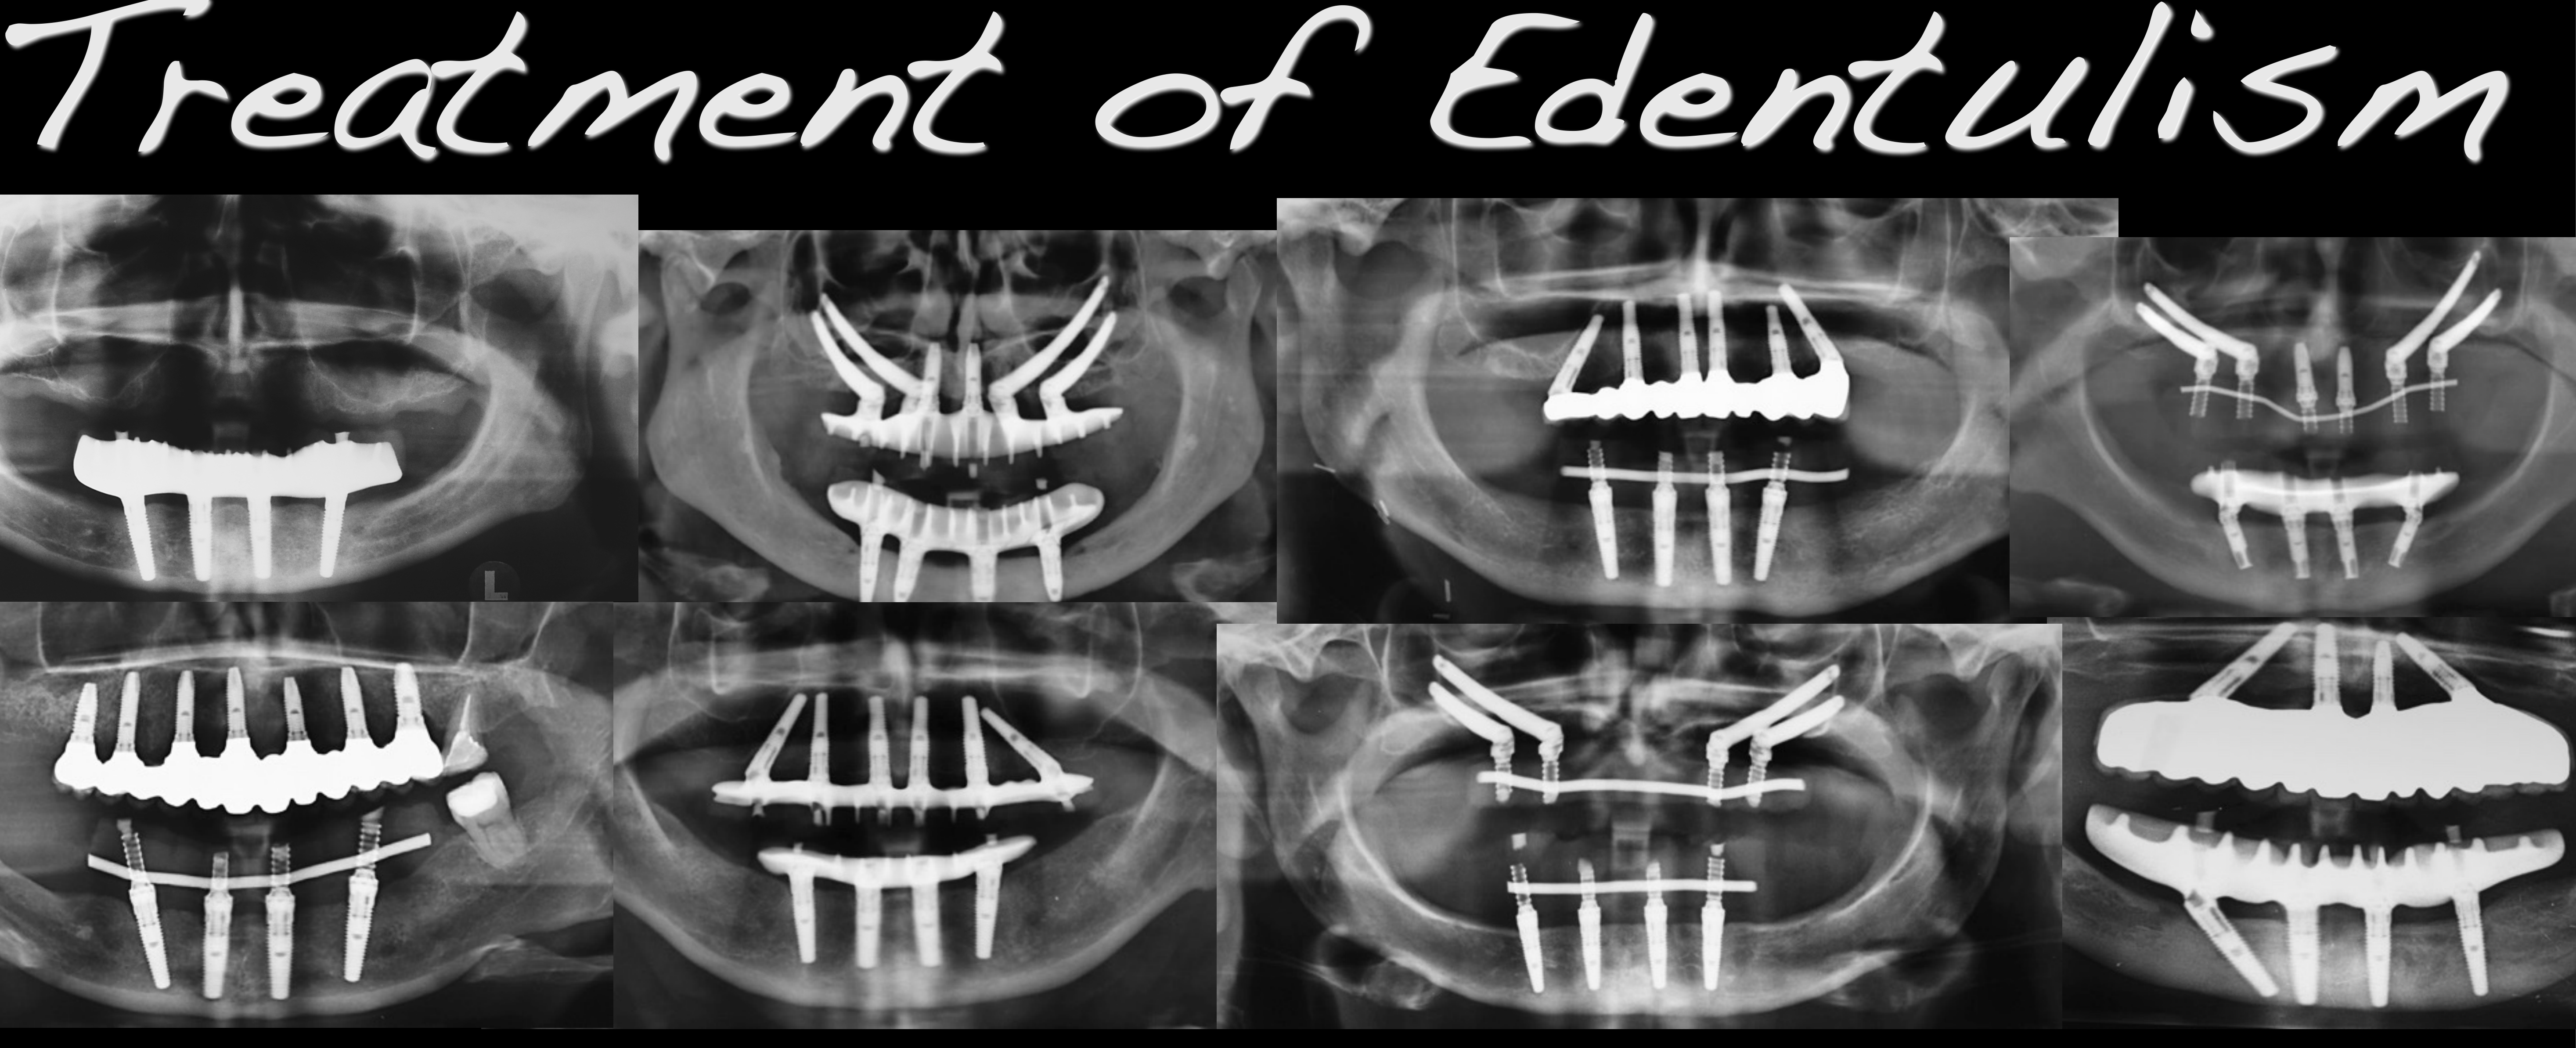
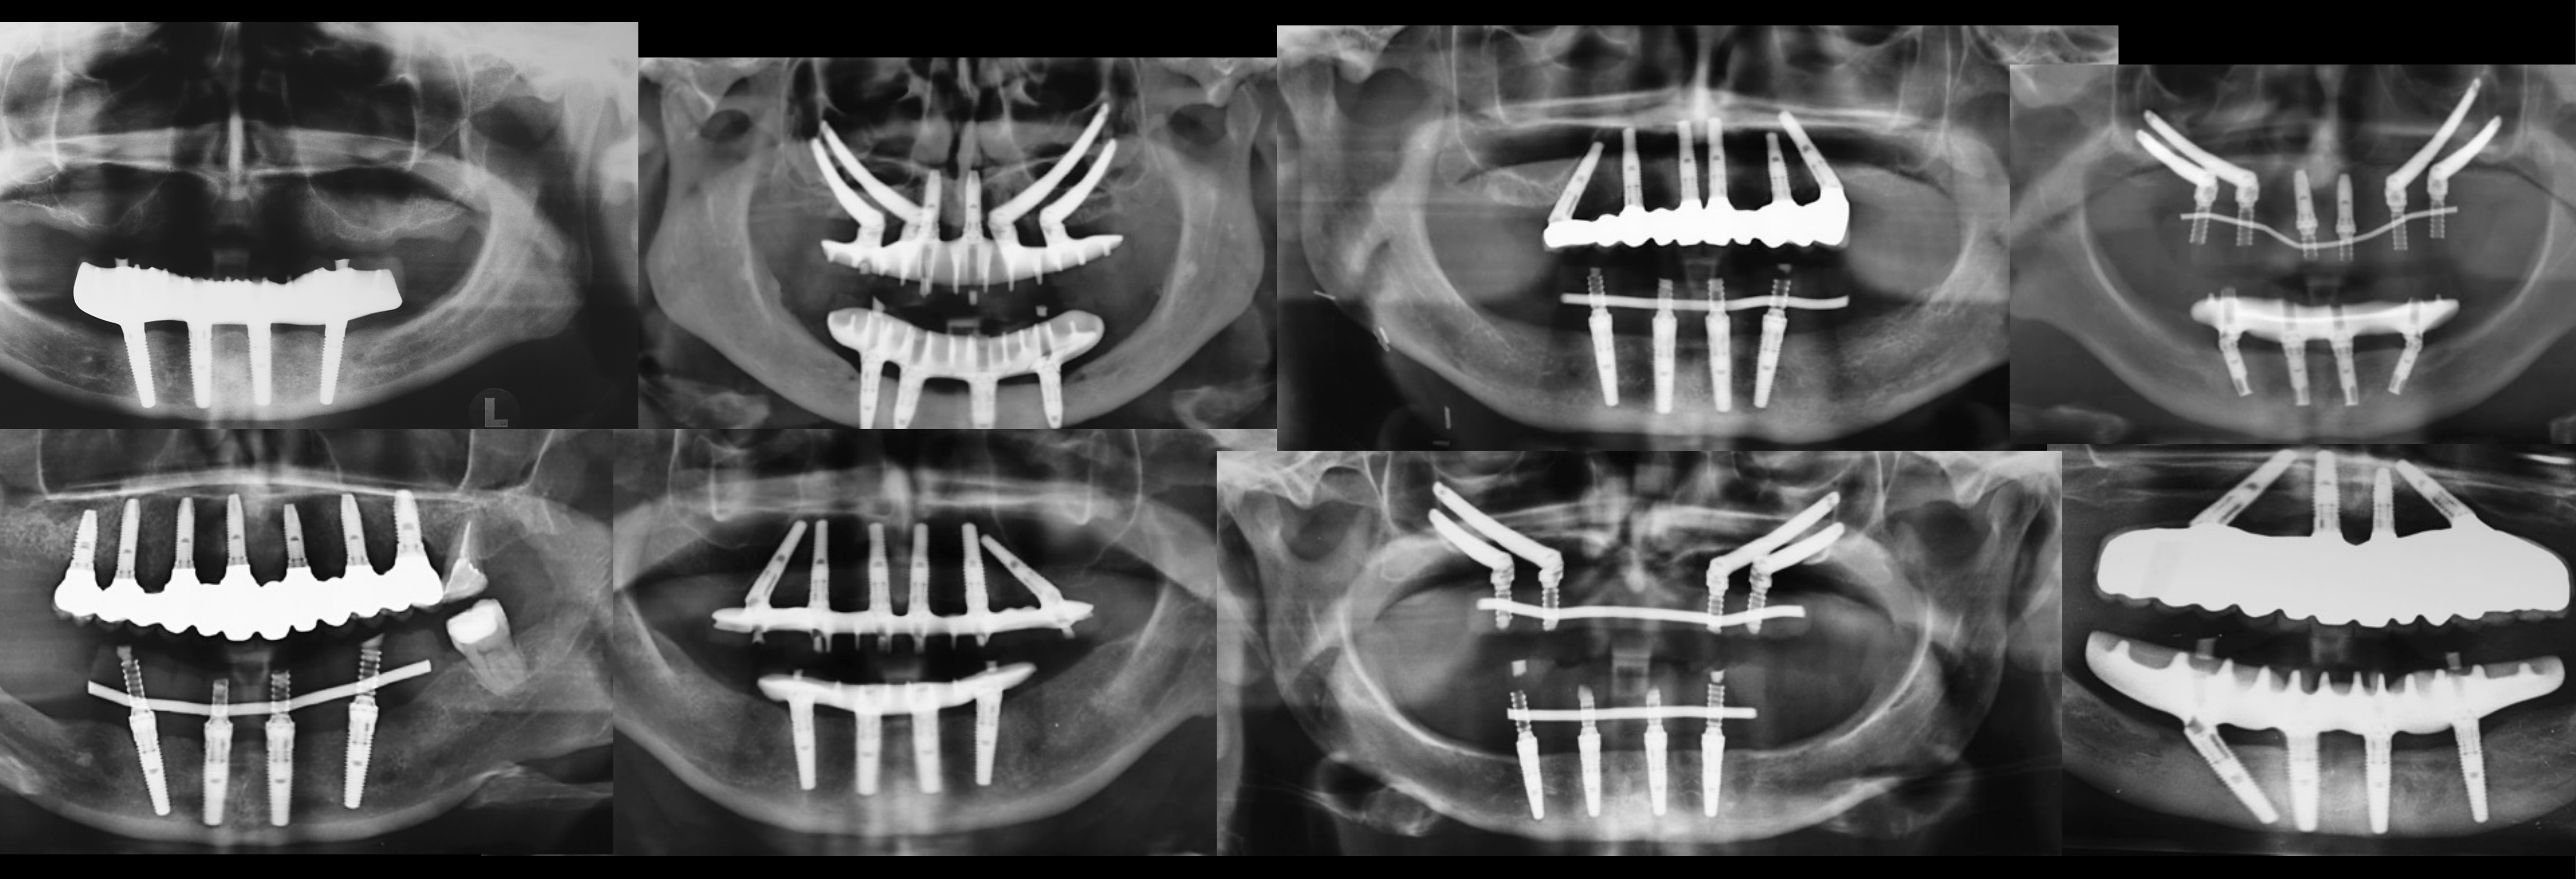
Treatment of Edentulism6
Friberg B, Jemt T. Rehabilitation of edentulous mandibles by means of four TiUnite implants after one-stage surgery: a 1-year retrospective study of 75 patients. Clin Implant Dent Relat Res. 2010;12 Suppl 1:56-62.
Friberg B, Jemt T. Rehabilitation of edentulous mandibles by means of five TiUnite implants after one-stage surgery: a 1-year retrospective study of 90 patients. Clin Implant Dent Relat Res. 2008;10(1):47-54.
 |  |
Immediate Loading of Edentulous Jaws
Timeline and Clinical Milestones7
- 1991: Single stage surgery and immediate loading (T-033C)
- 1994: Routine lower jaw on 4 implants, immediate loading
- 1998: Brånemark Novum (T-086)
- 2000: Immediate loading maxilla
- 2003: Teeth in an hour (NobelGuide)
- 2008: Immediate loading of Zygoma implants
Sequelae of Tooth Loss8
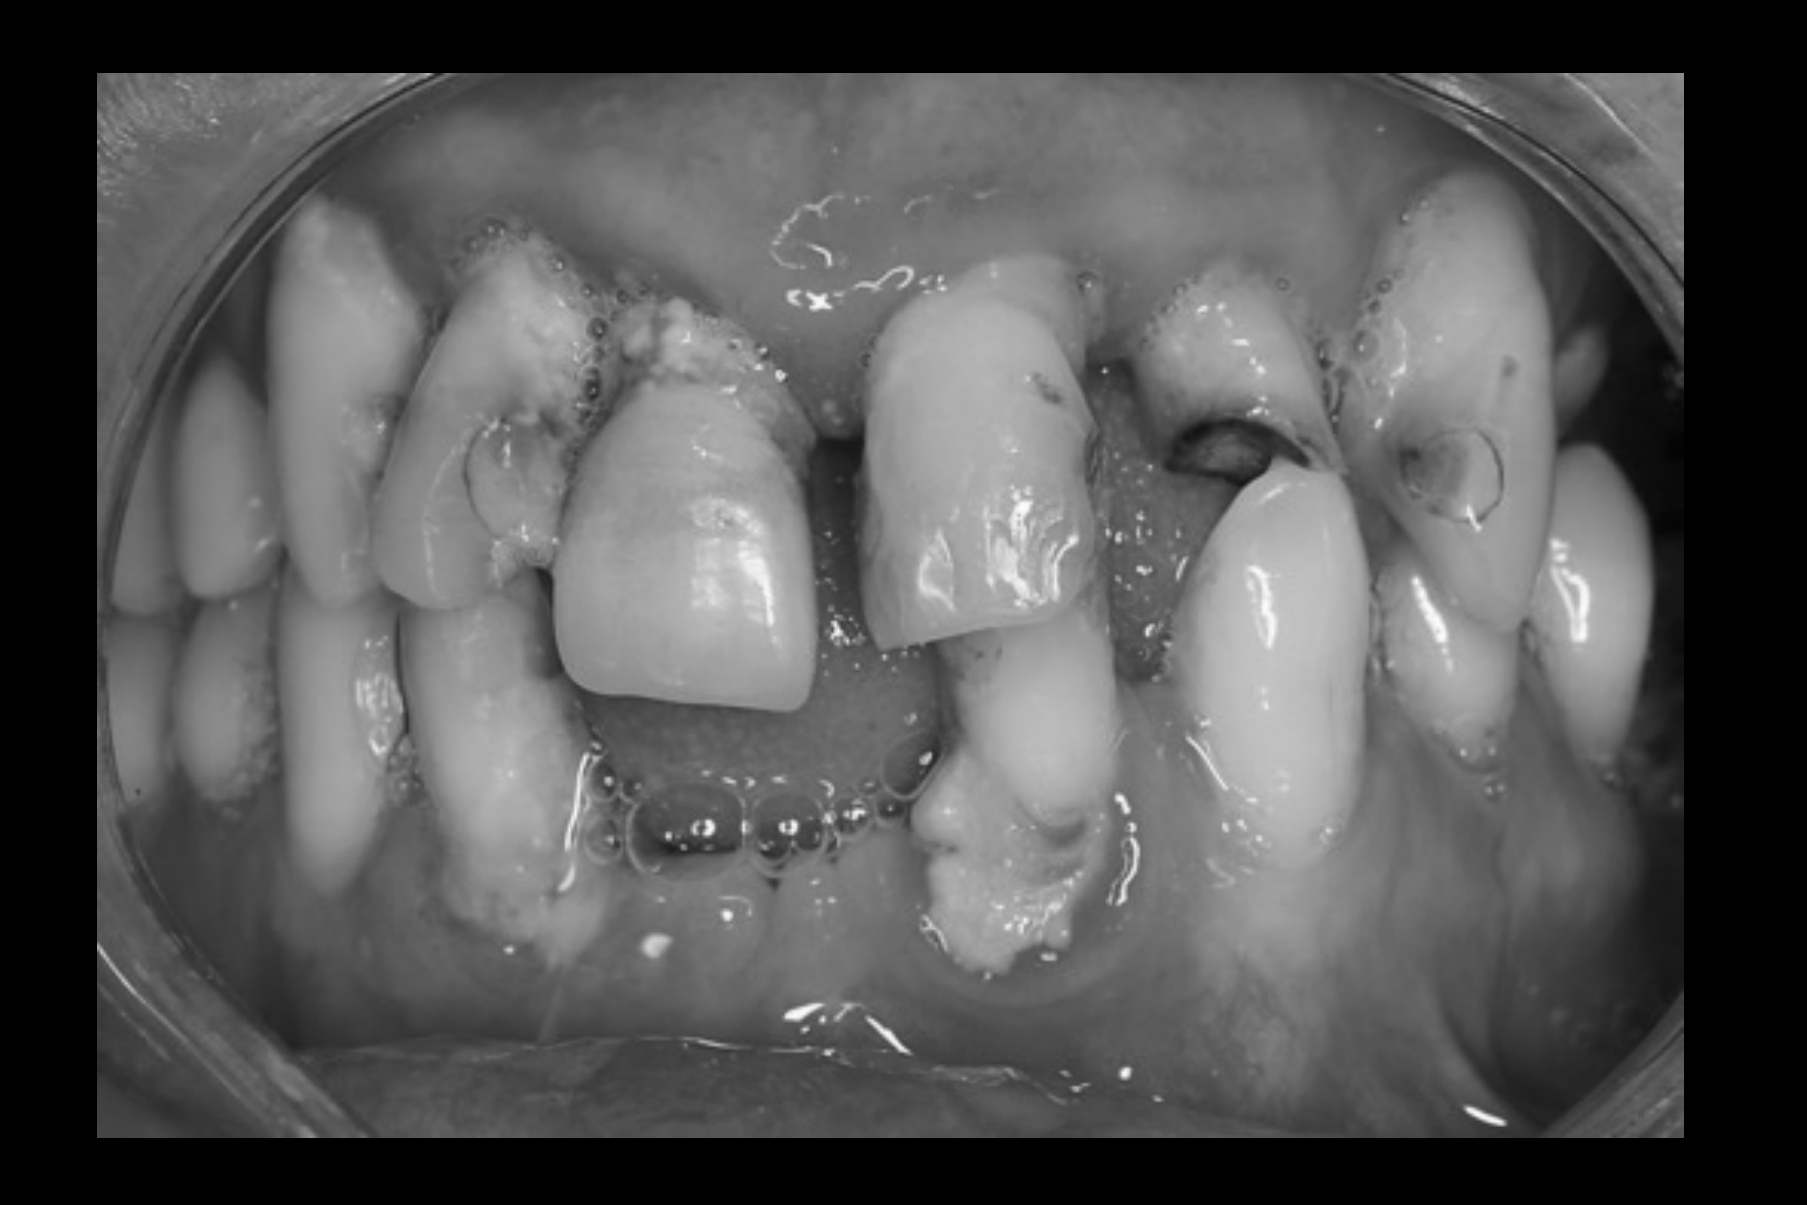
Factors to Consider9
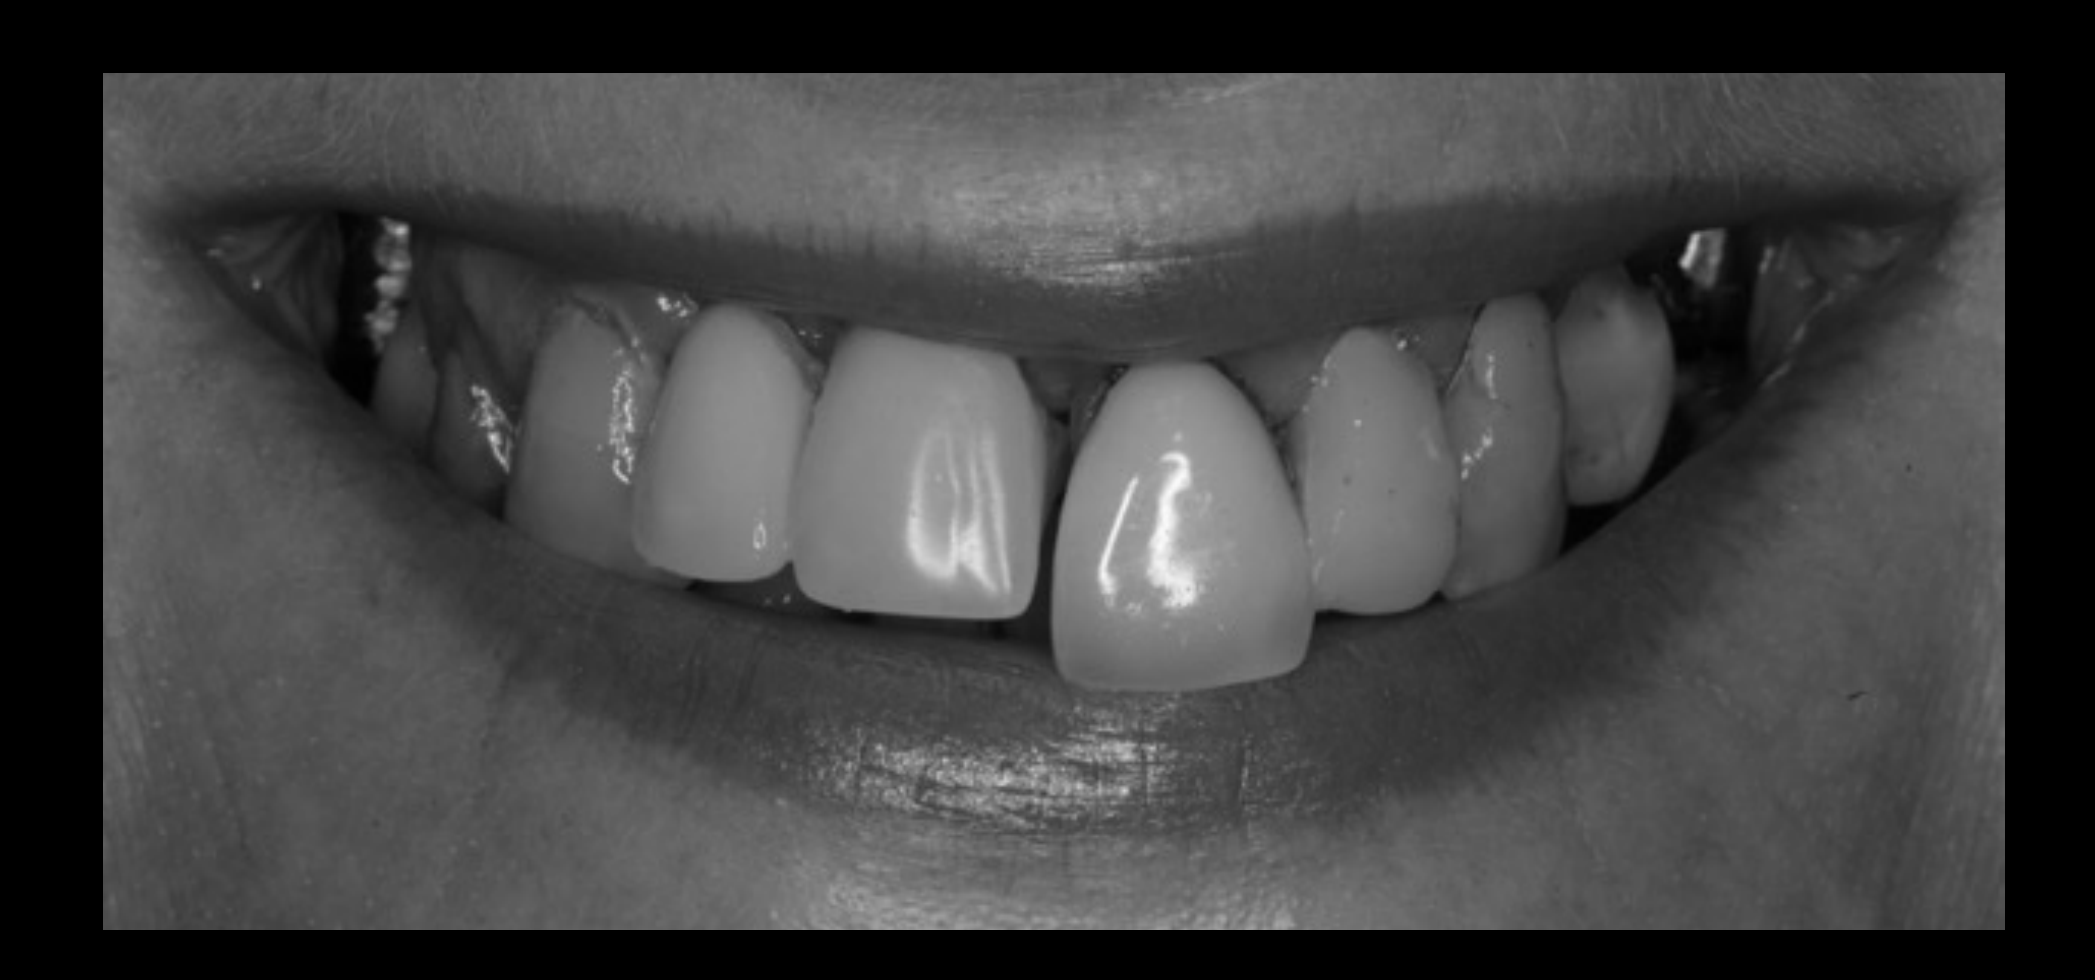
- Initial aesthetic expectation
- Current dentition, prostheses
 |  |
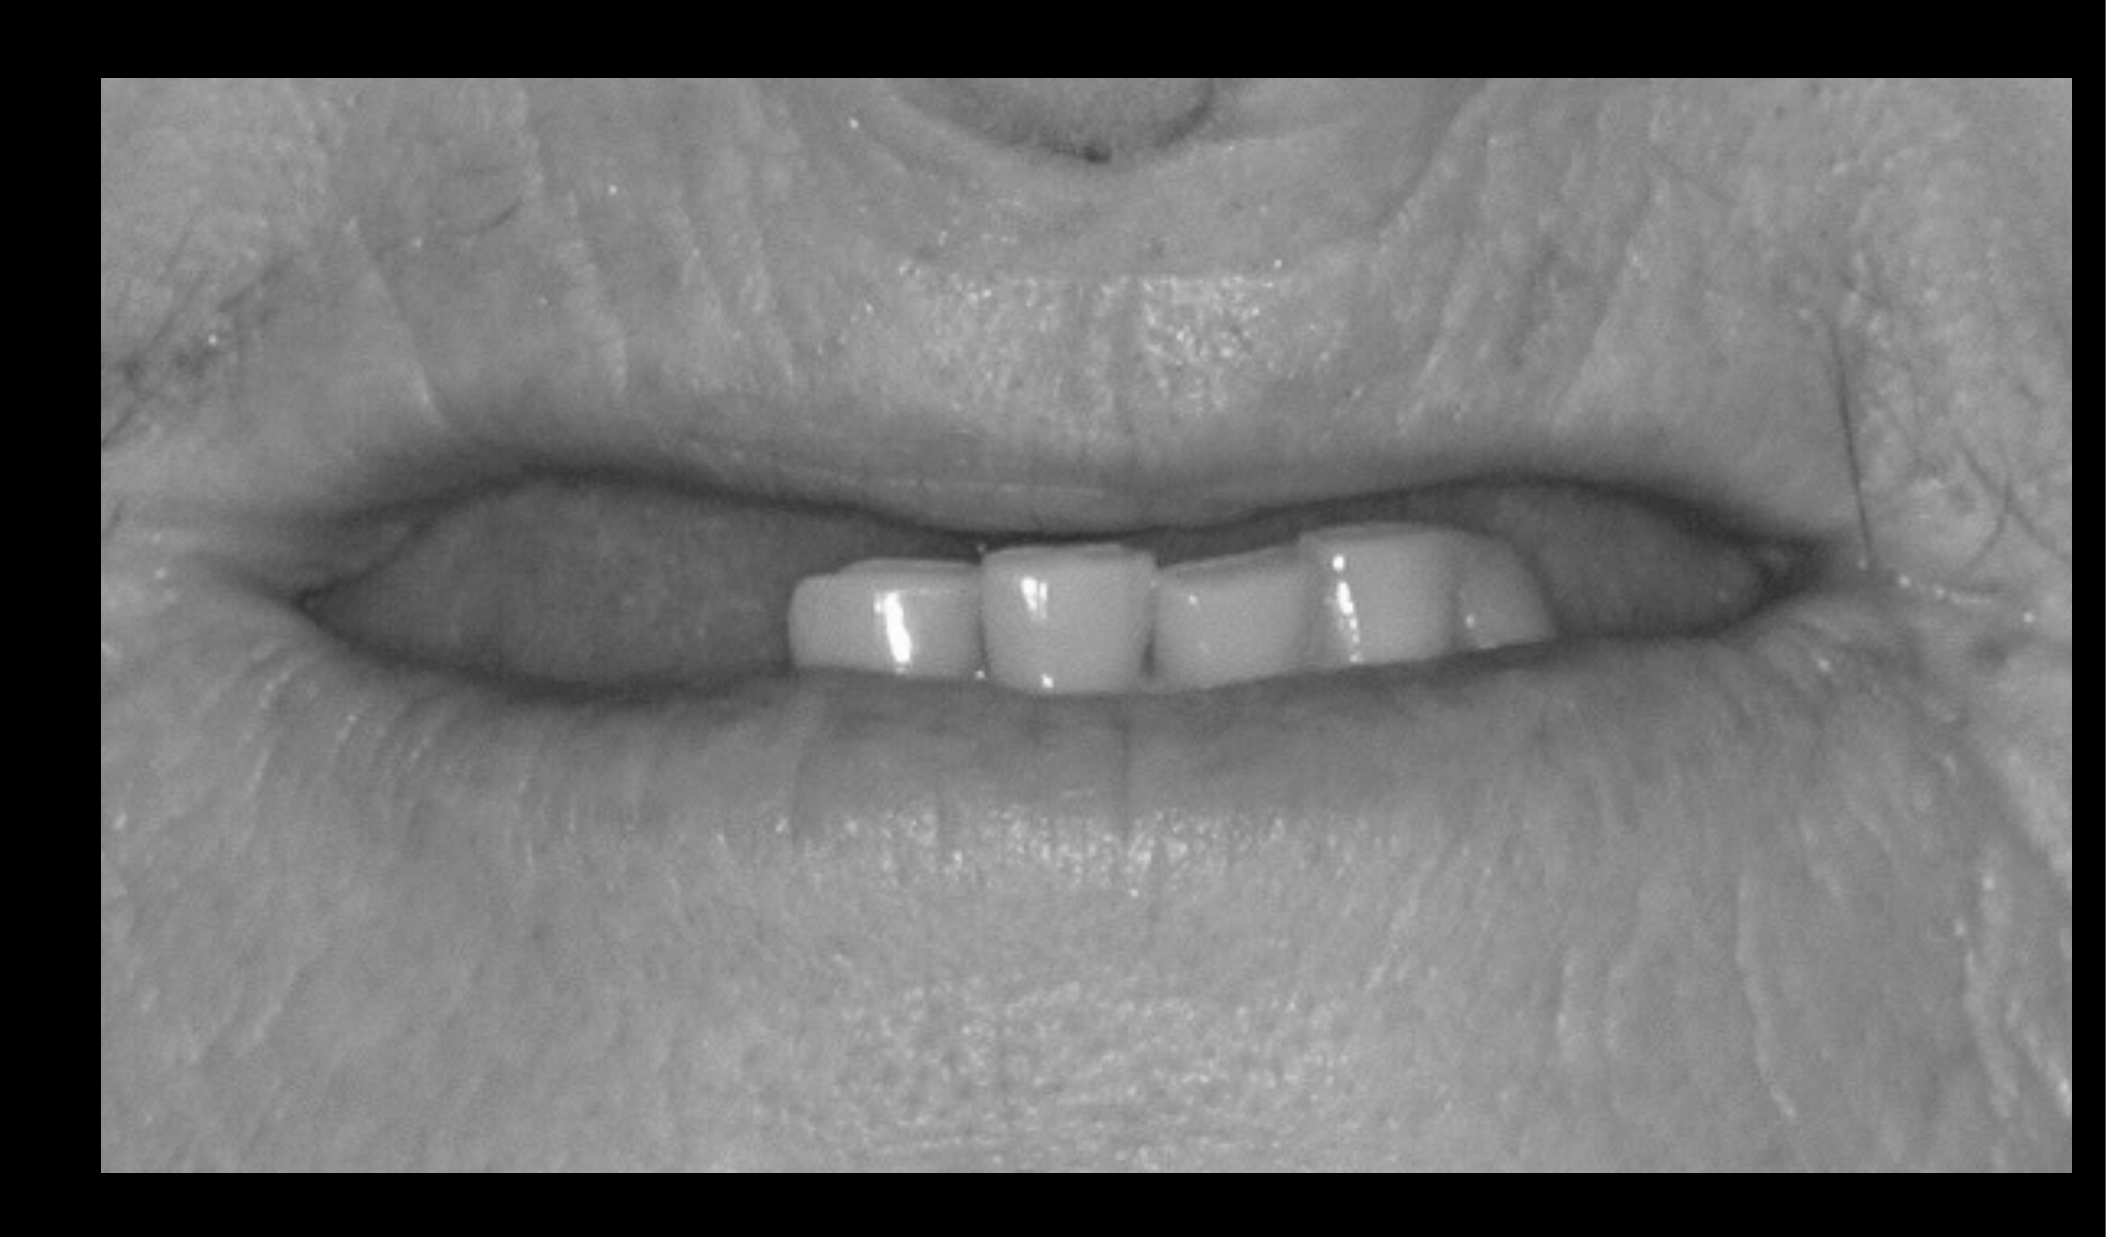 |
Facial Aesthetics and Lip Support10
Clinical Evaluation11
- Left: Before photo—darker teeth, more visible wrinkles, and uneven smile line.
- Right: After photo—brighter, whiter teeth, smoother skin, and a more defined smile.
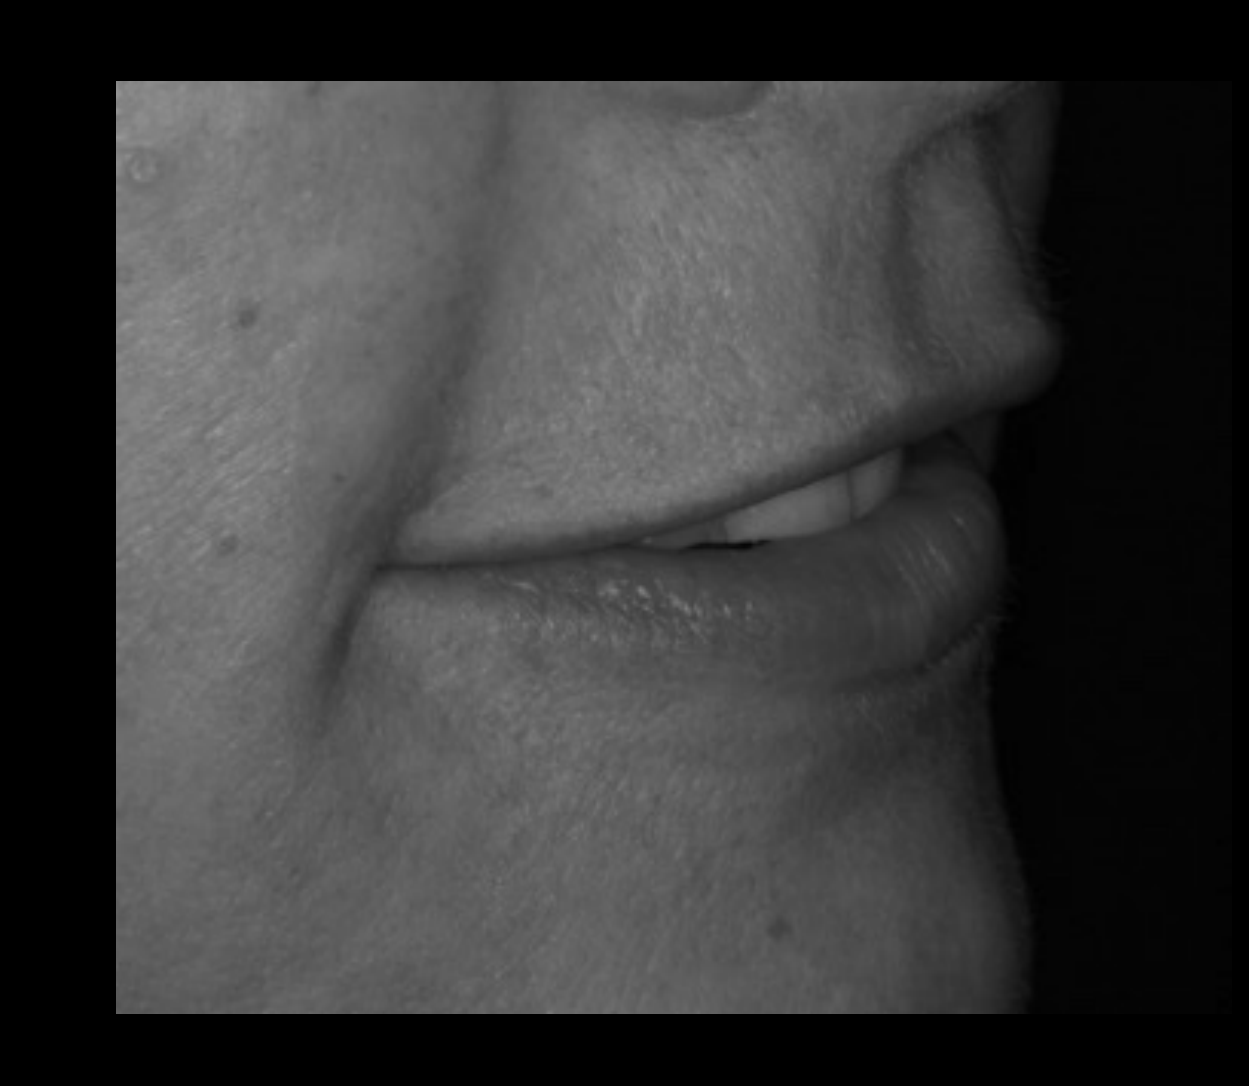
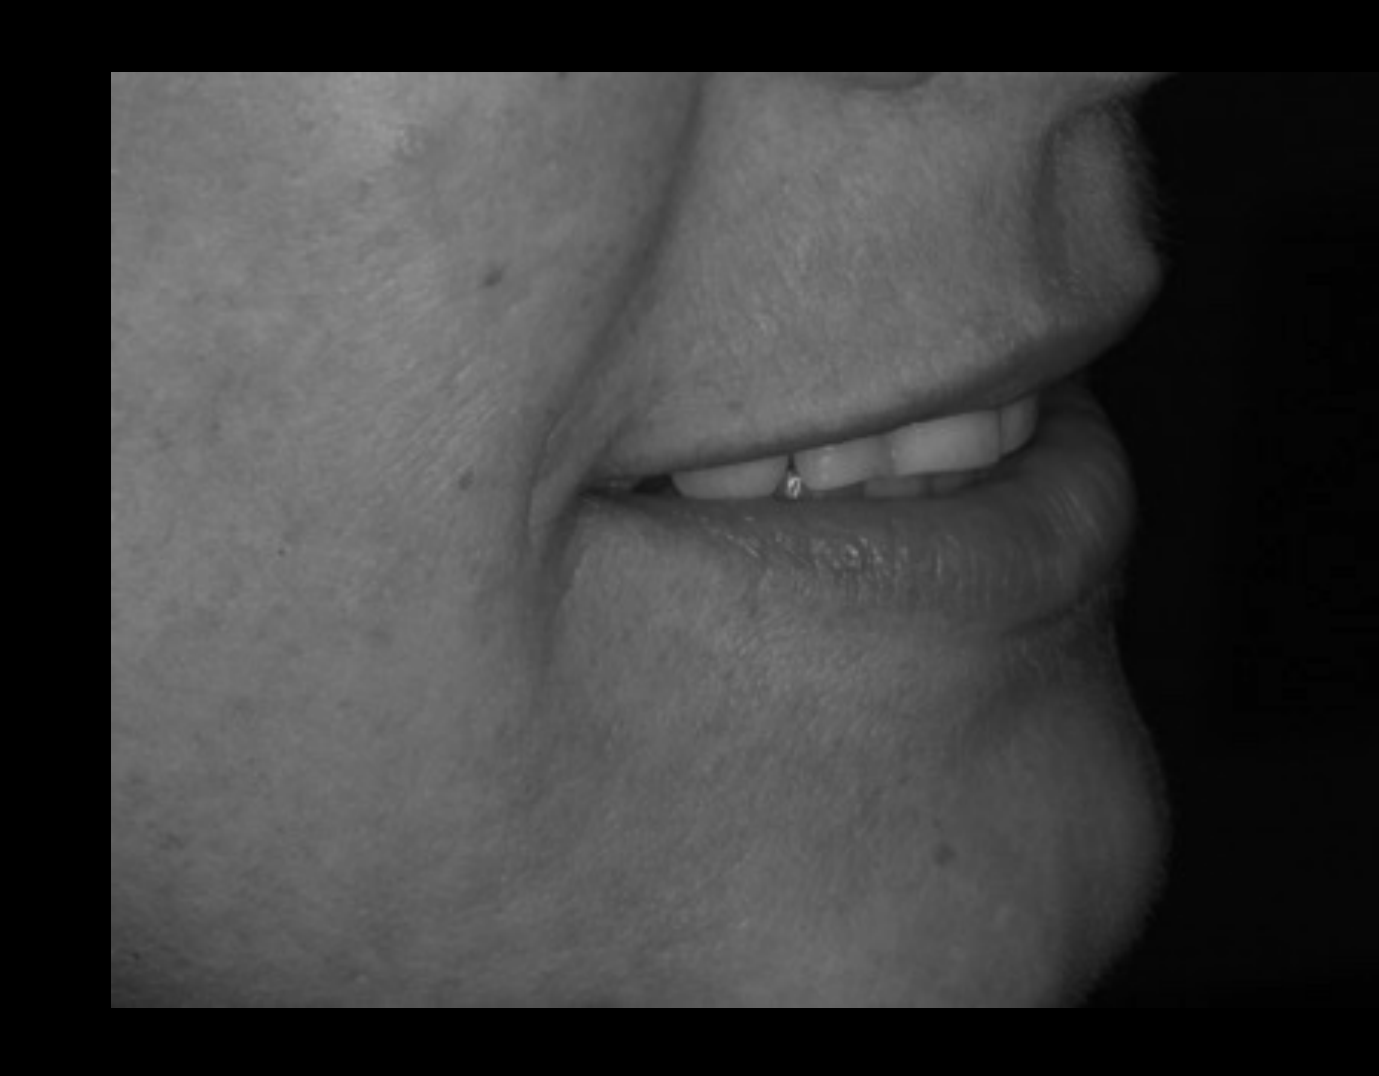
Lip support assessment.
Ridge Reduction and Facial Support121314
Evaluation of ridge reduction and facial support.
Tooth Position Within the Face15
The Face16
Determination of tooth position within the face.
Where do you want your front teeth?
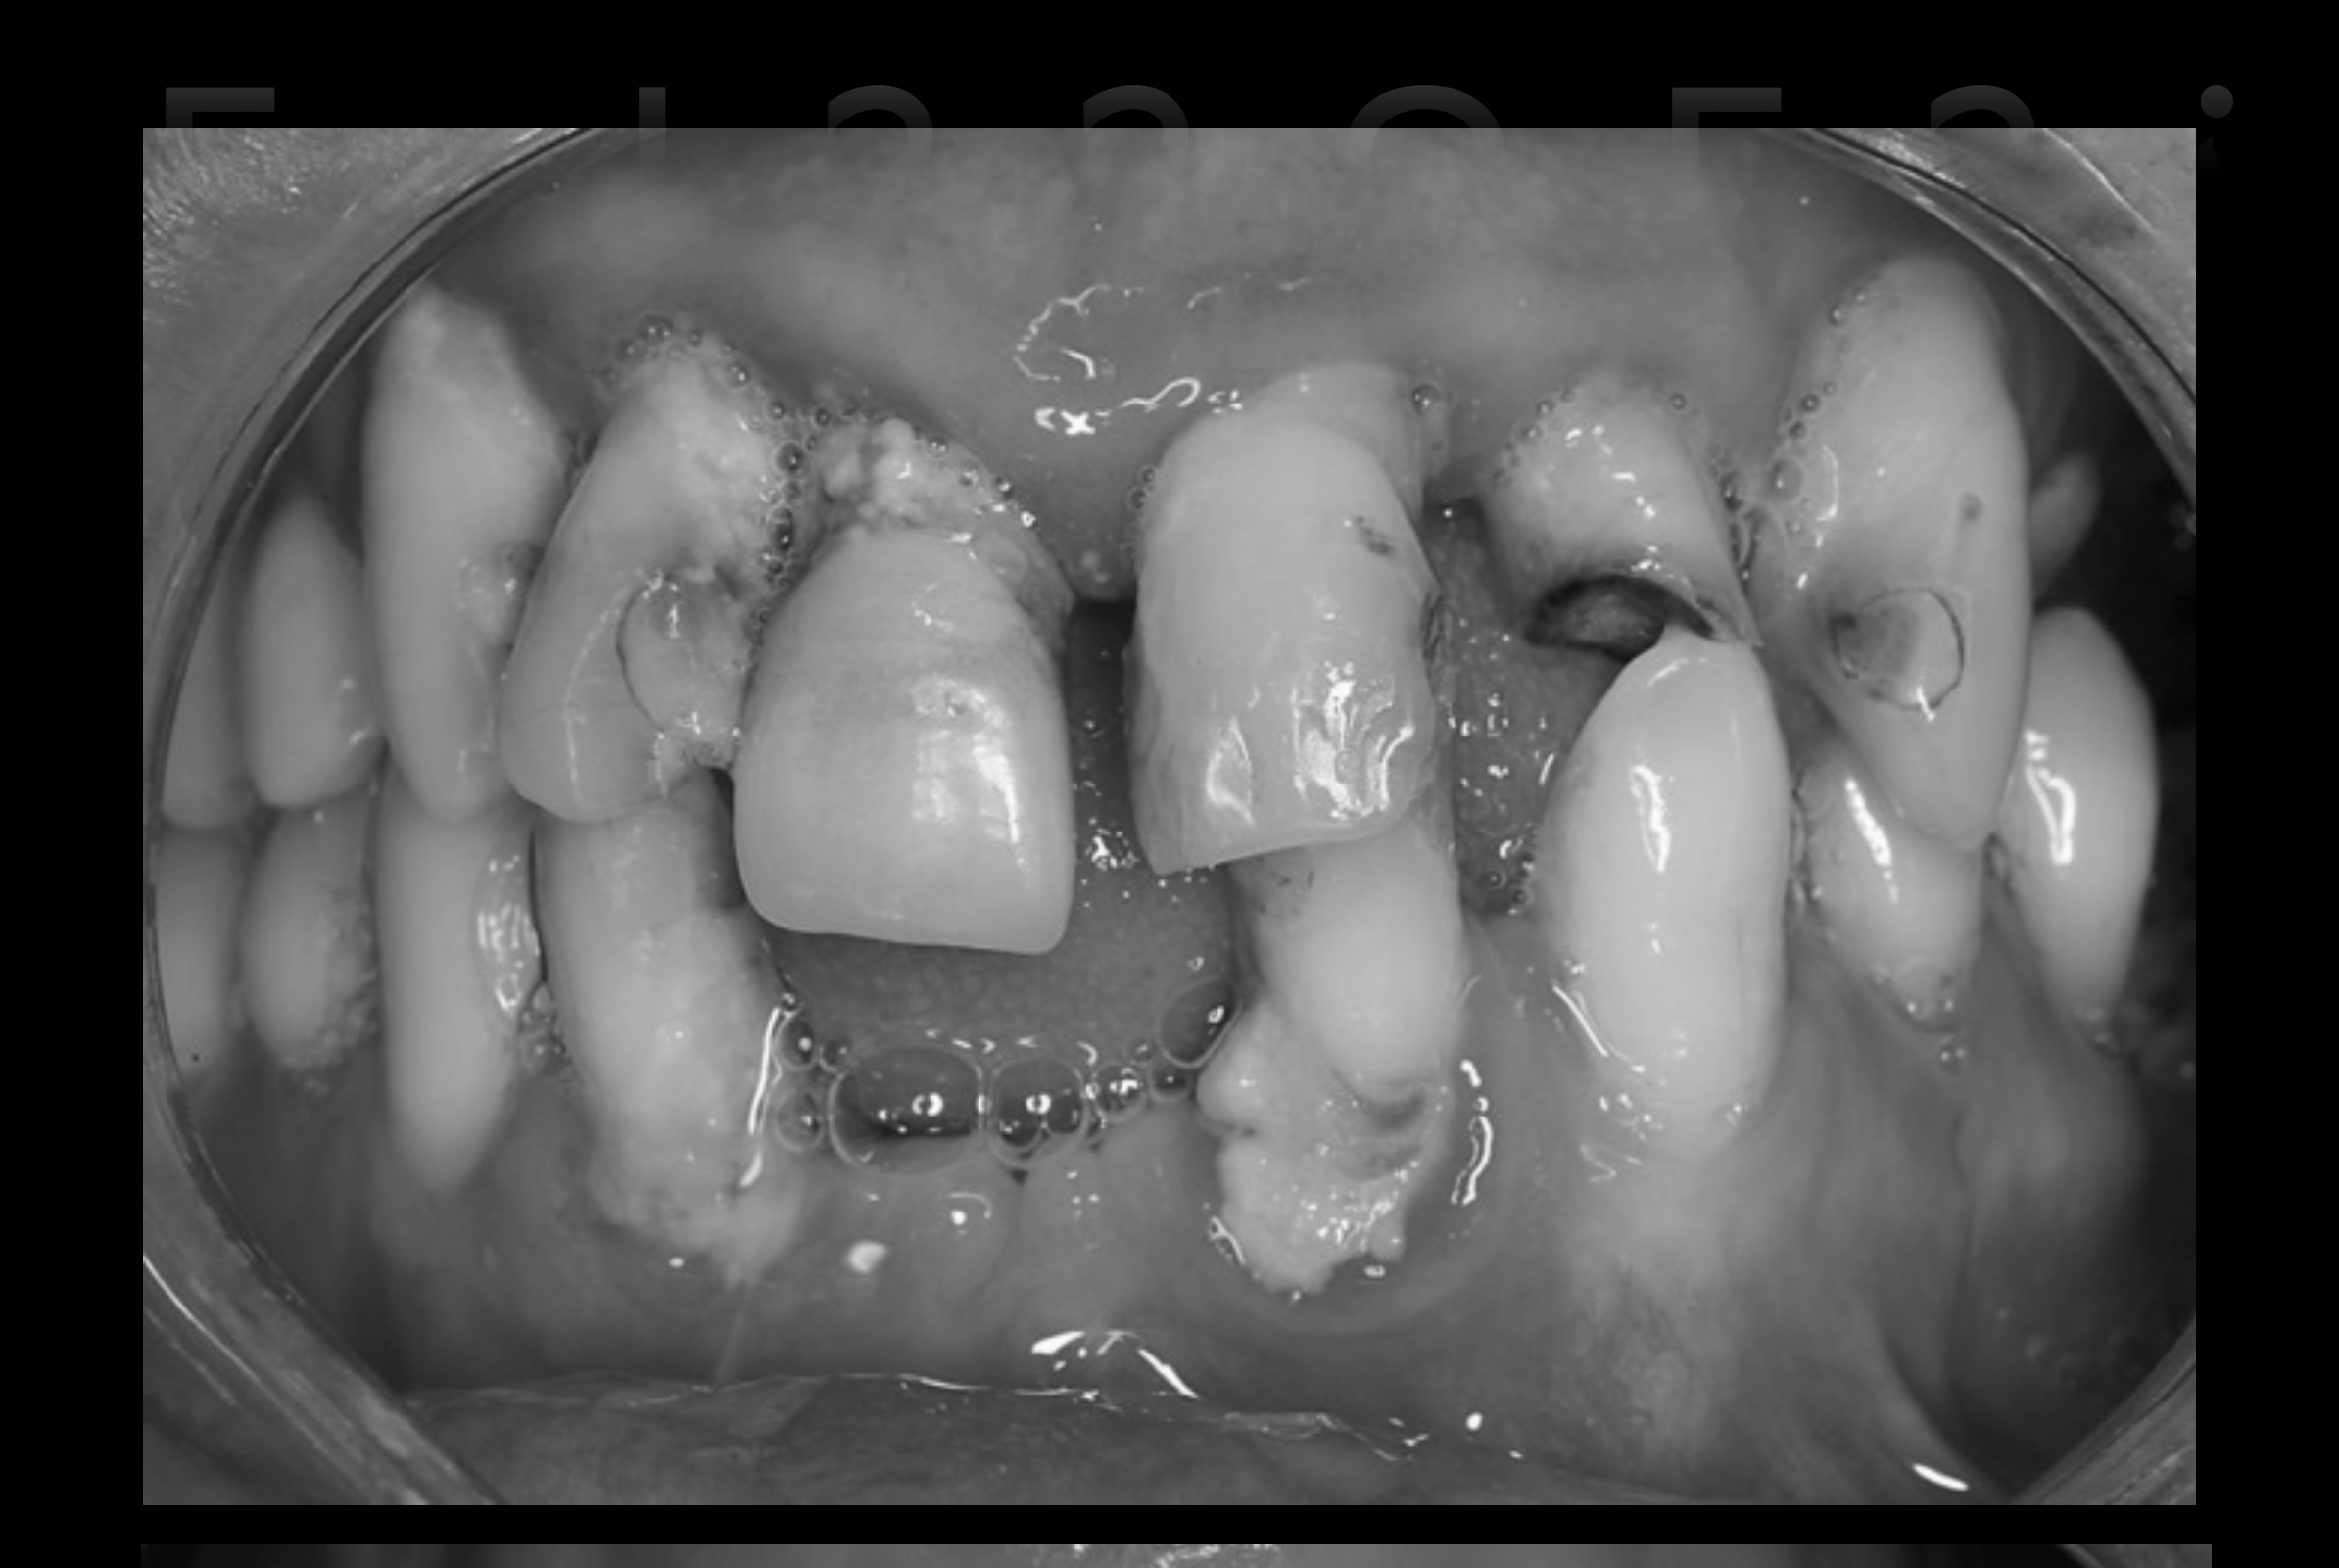
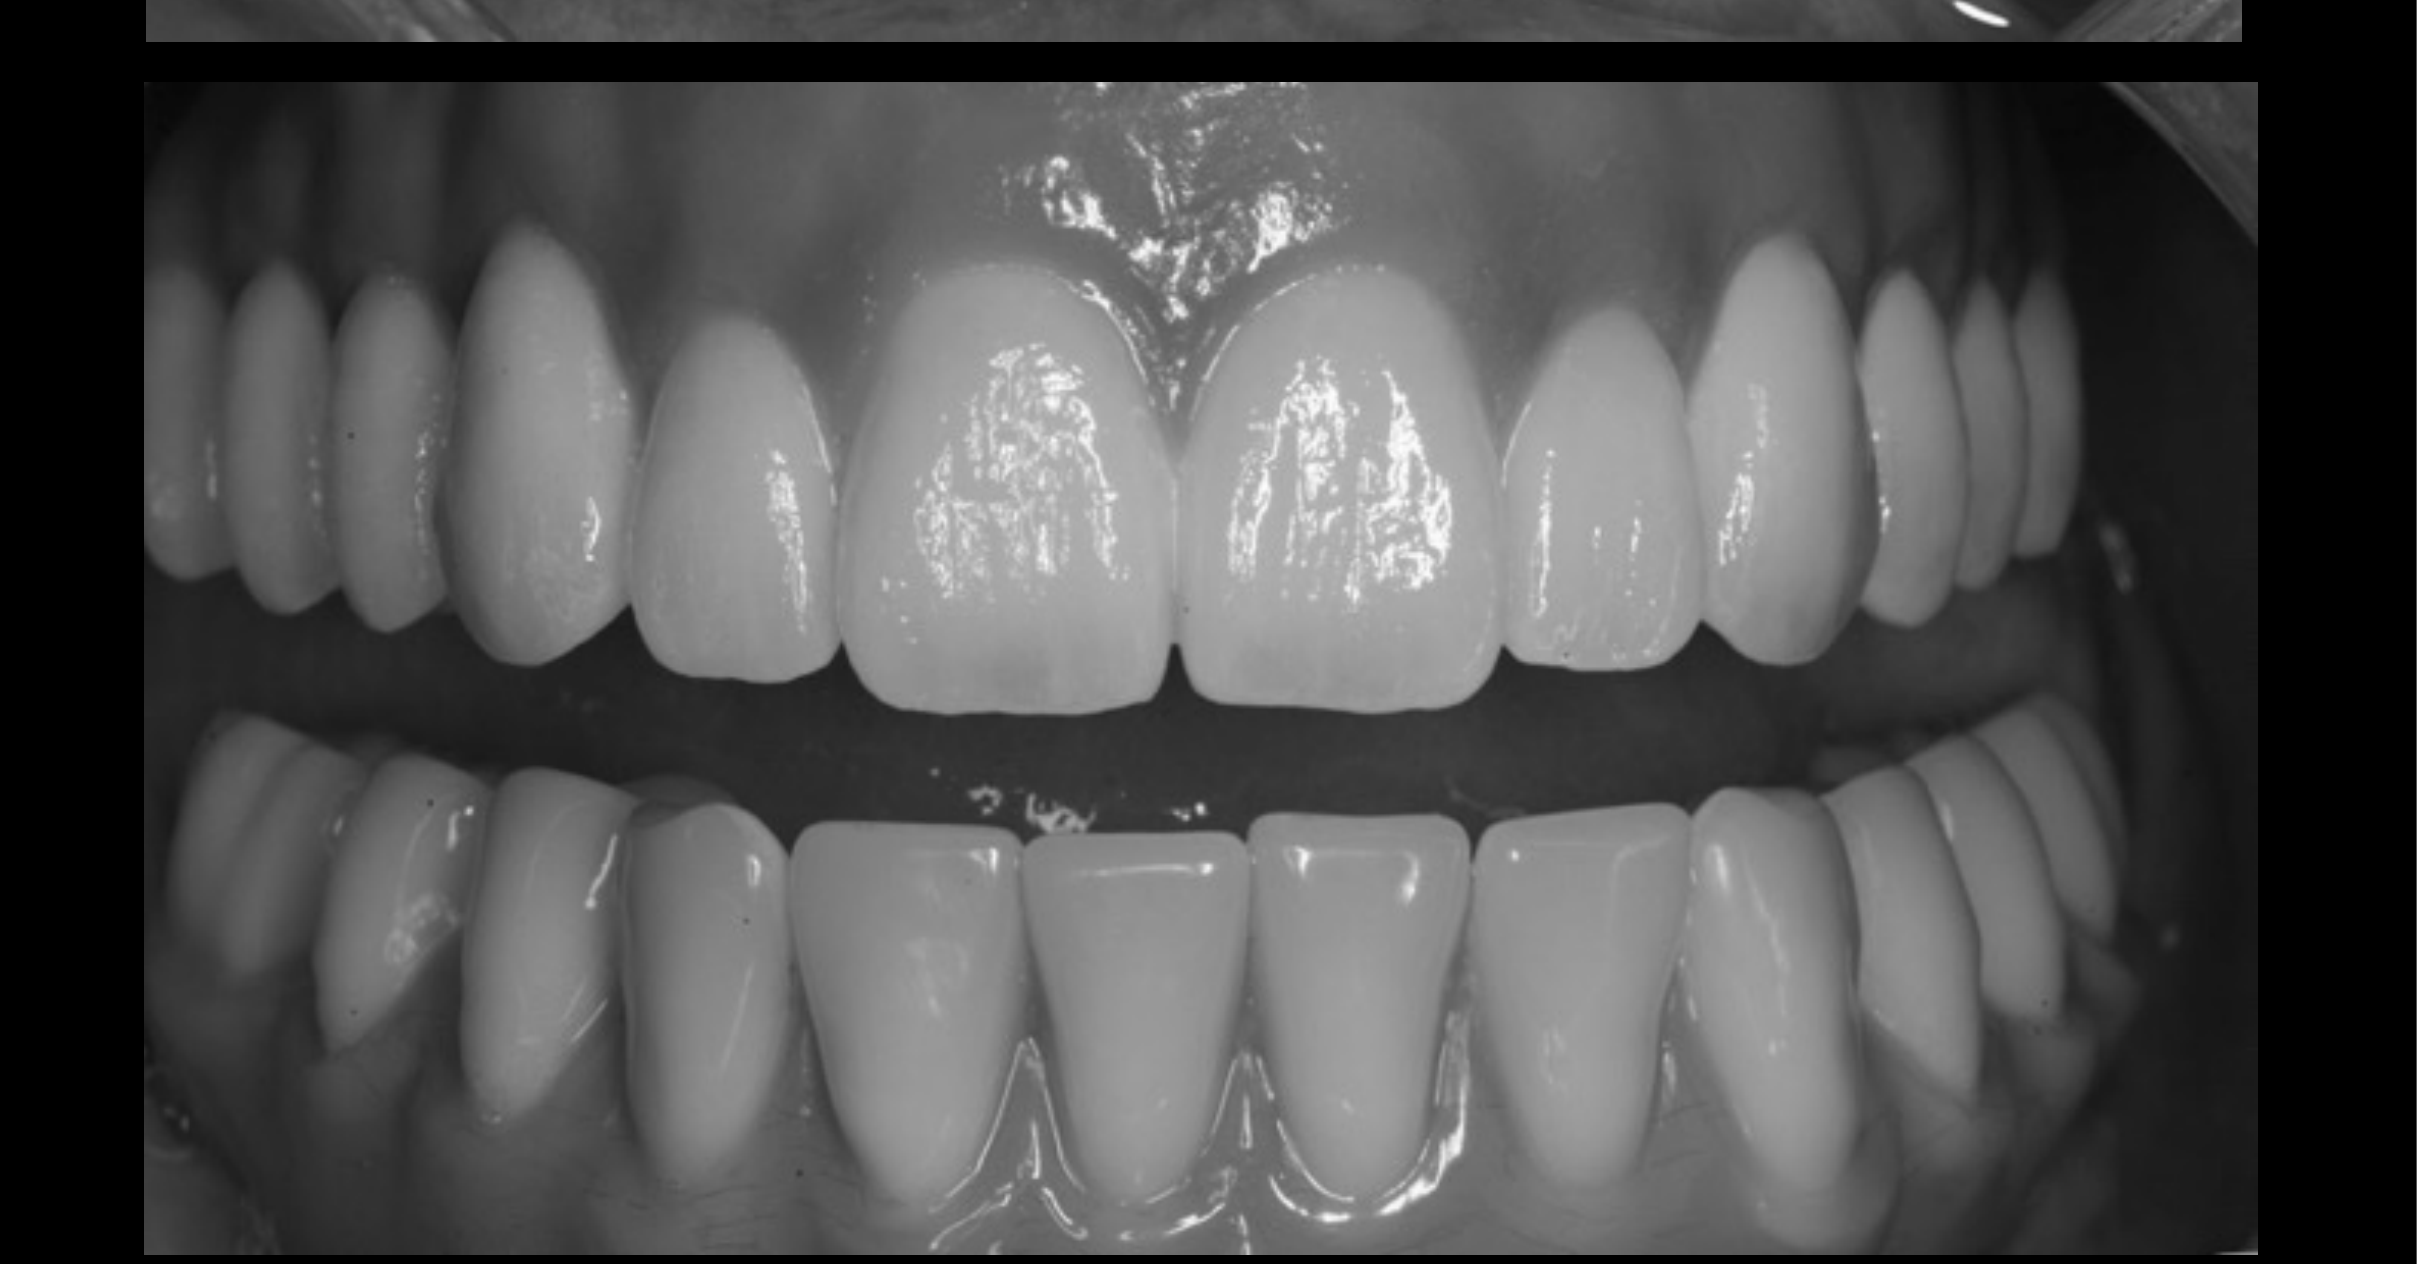
Tooth Aesthetics and Function17
Key considerations regarding tooth aesthetics and functional requirements.
 |  |
Phonetic and Functional Analysis18
- M-Ah
- Interocclusal rest space: 4 mm
- Dental exposure (Mx): 2–3 mm
- F, V
- Vermillion border: 1 mm lingual
- E
- Interlabial space occupied by Mx teeth: 72%
- S
- Mandibular movement: Horizontal 2 mm
- Interarch space: 2 mm
Fradeani M. Esthetic Analysis: A systematic approach to prosthetic treatment. Quintessence, Illinois. 2004. Spear F, Kokich V, Mathews D. Interdisciplinary management of anterior dental esthetics. J Am Dent Assoc 2006;137:160-169. Pound E. Let “s” be your guide. J Prosthet Dent. 1977;38:482-489.
 |  |
Digital Smile Design
Clinical Applications19
- Ability to quantify changes to technician
- More useful for tooth-borne prosthetics – limitations with face bow
- Visualisation of final result
- Patient communication
Coachman C, Calamata M. Digital Smile Design: A Tool for Treatment Planning and Communication in Esthetic Dentistry. Quintessence Dental Technology 2012.
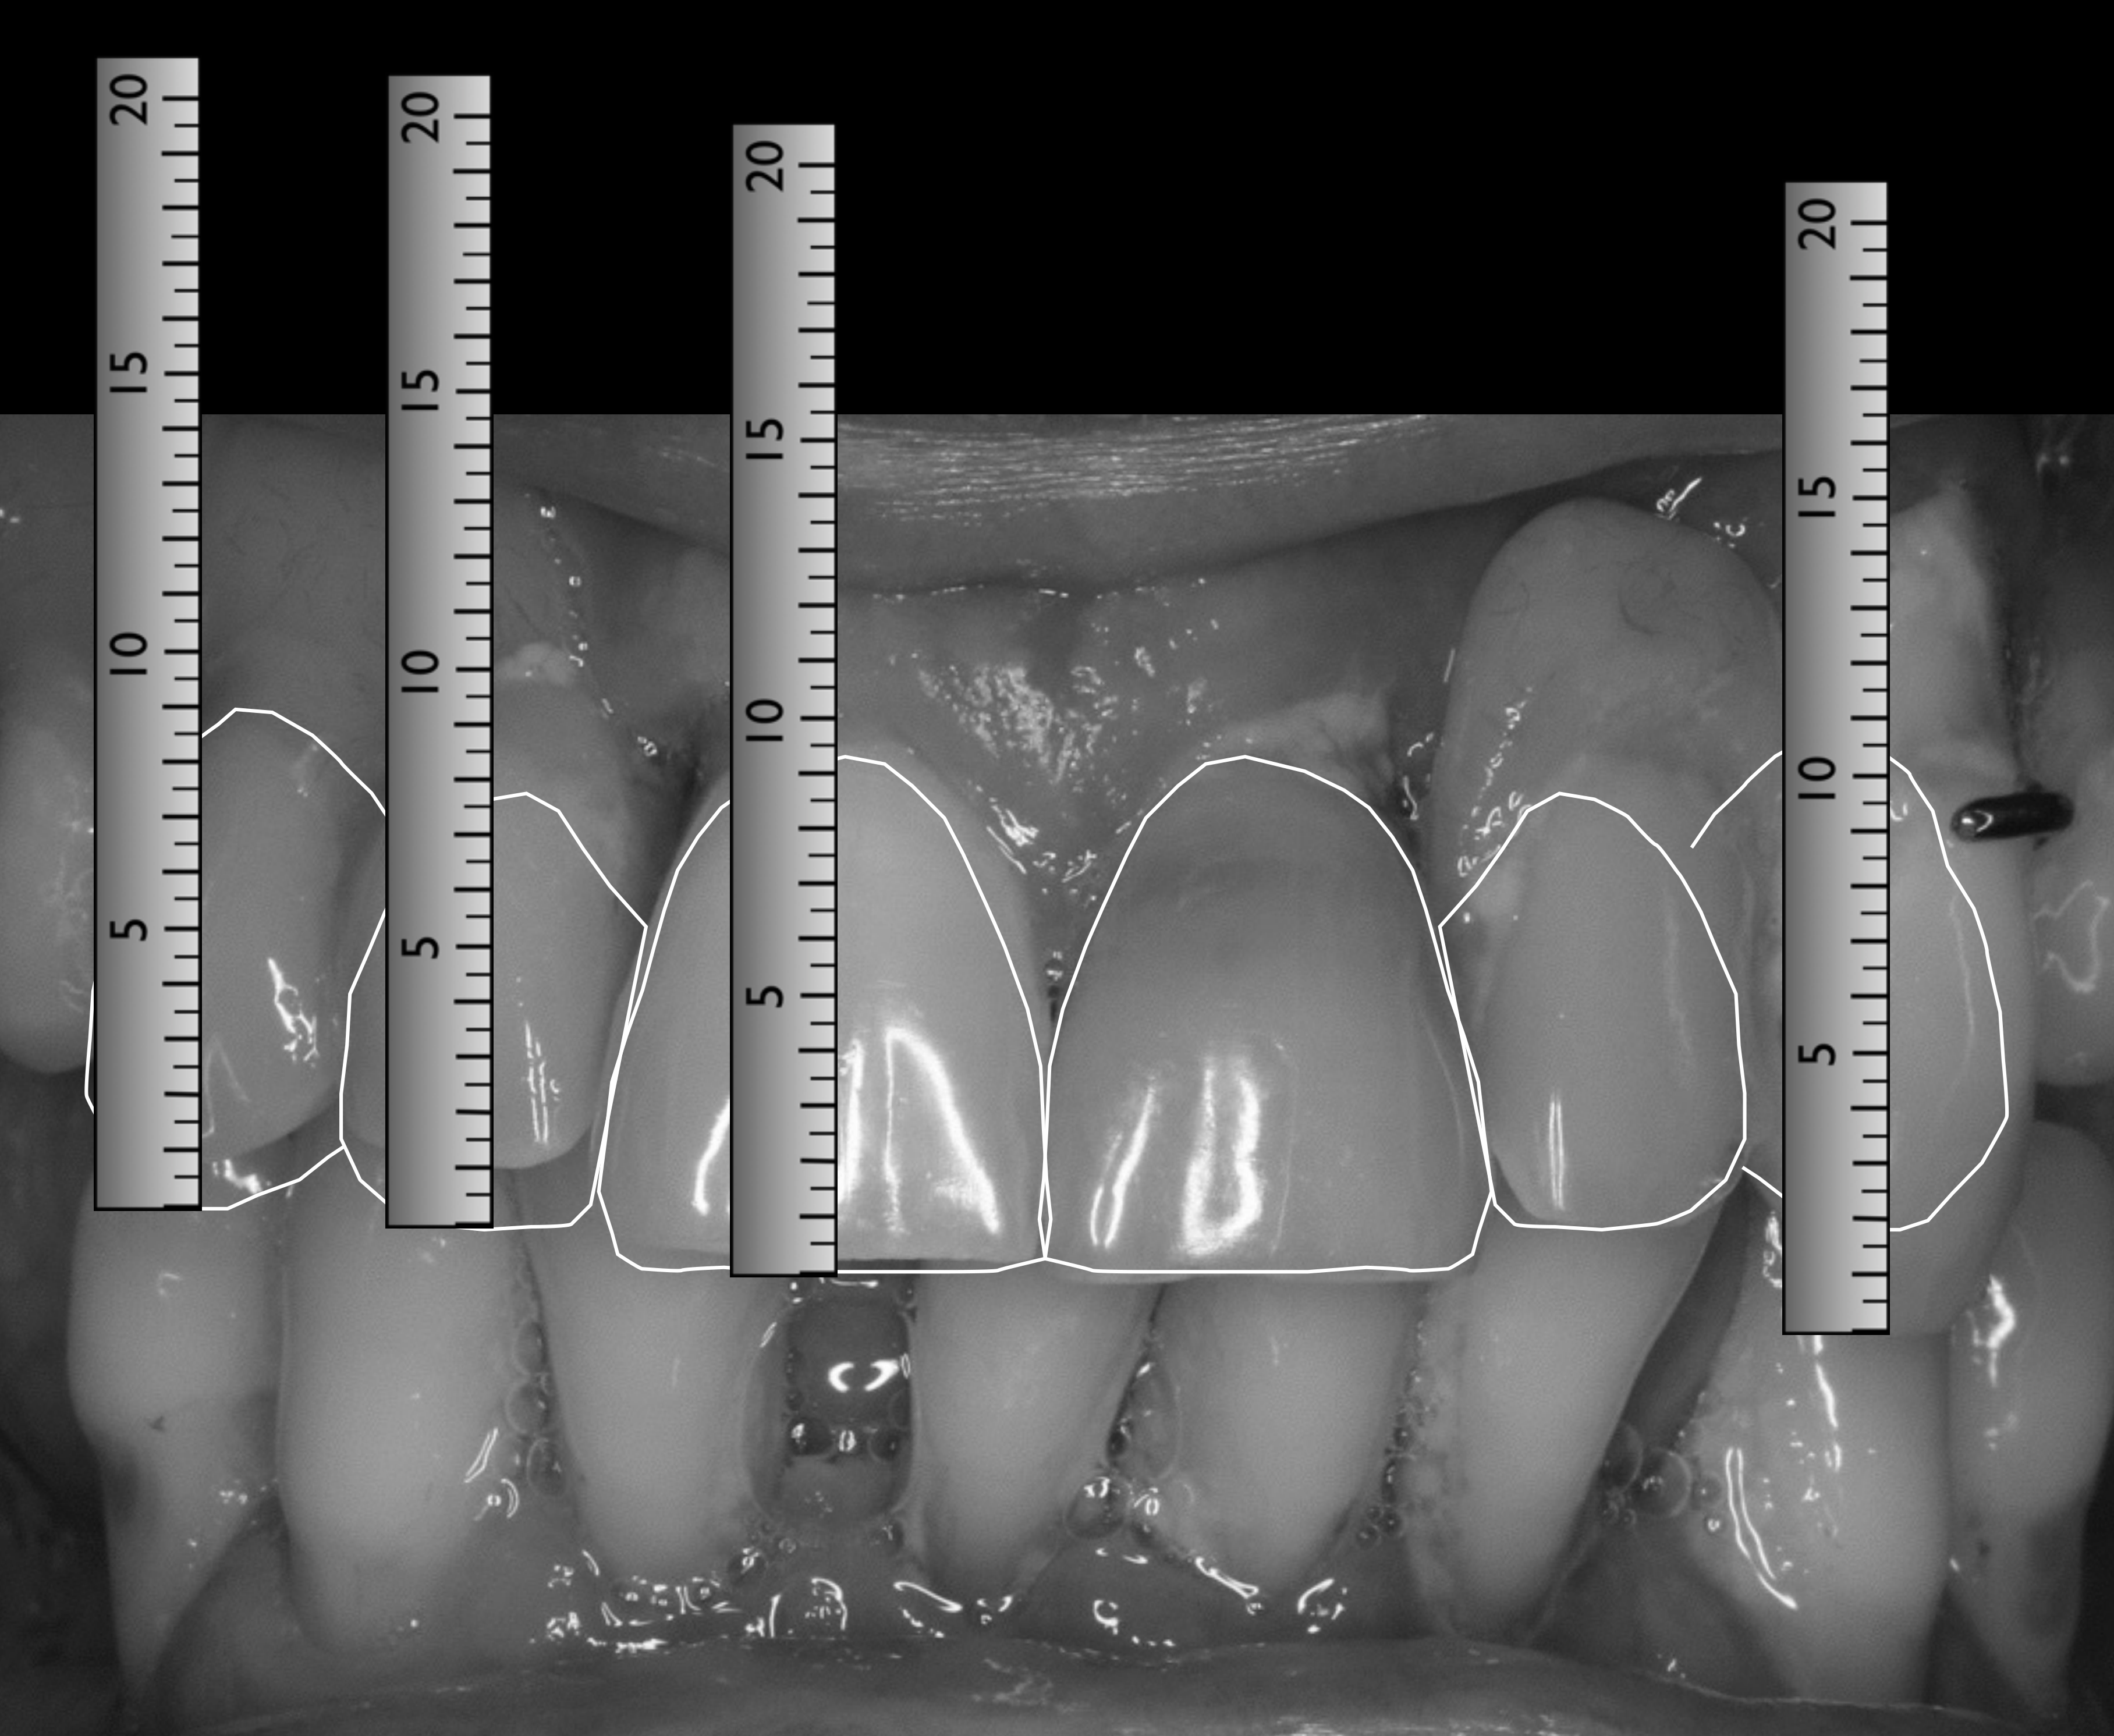
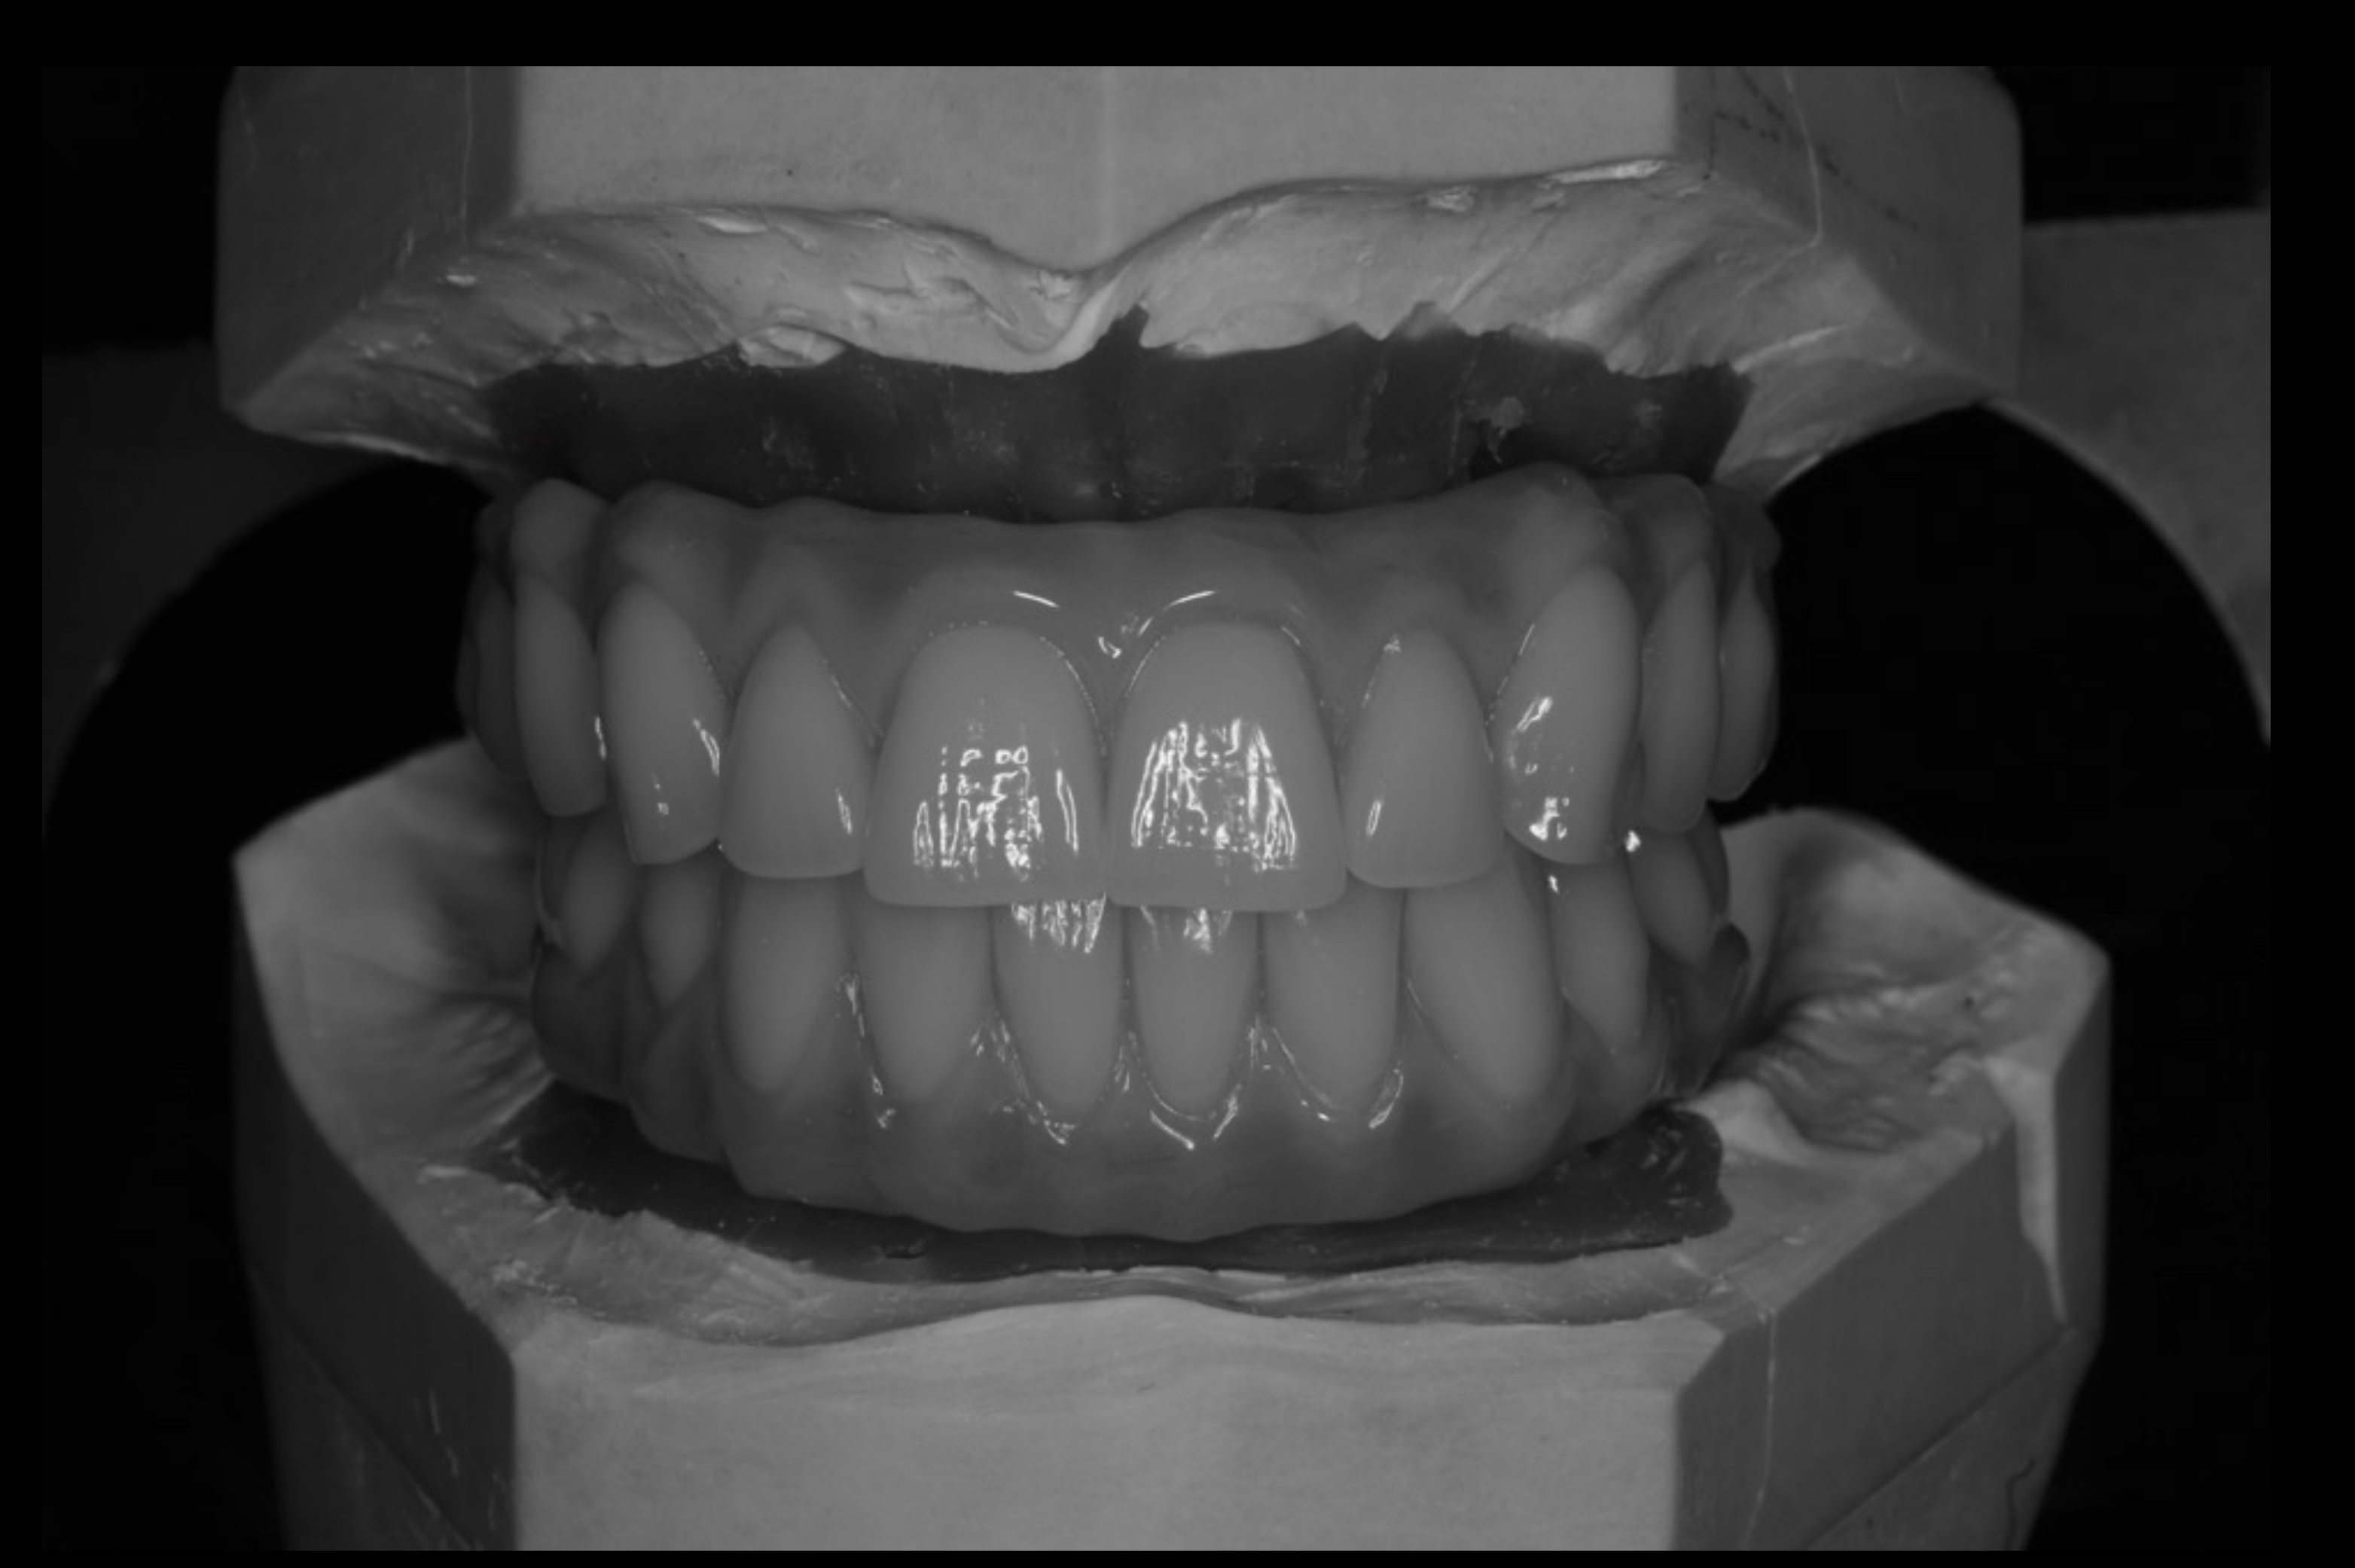
Face Bow and Digital Tools20212223
Digital ruler.
Tooth outline.
“Real Face Bow”

Treatment Planning and Virtual Surgery
Implant and Prosthetic Tooth Junction2425
The junction between the implant and prosthetic tooth determines lip support and the phonetic surface.
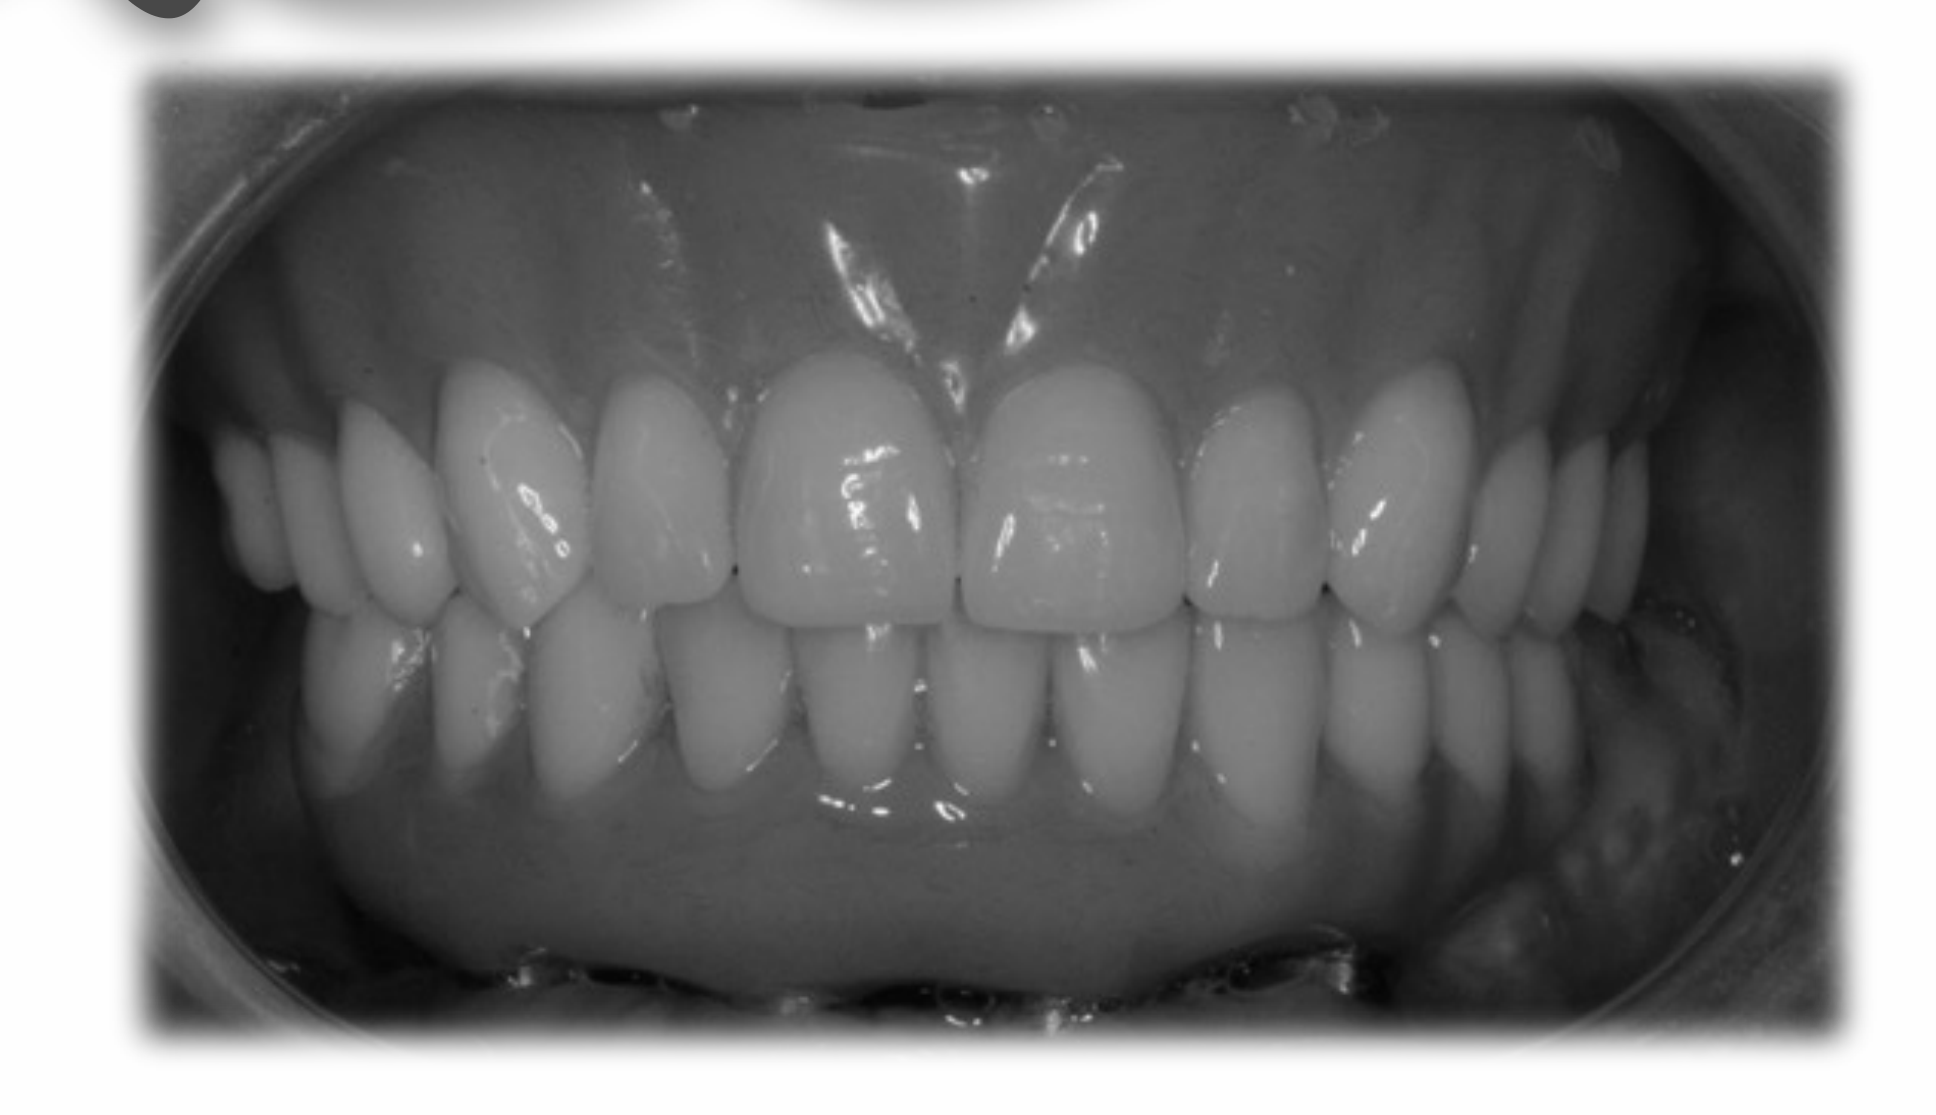
Radiographic Workup and NobelClinician26
The Face27
Transfer to radiographic workup and NobelClinician software.
 |  |
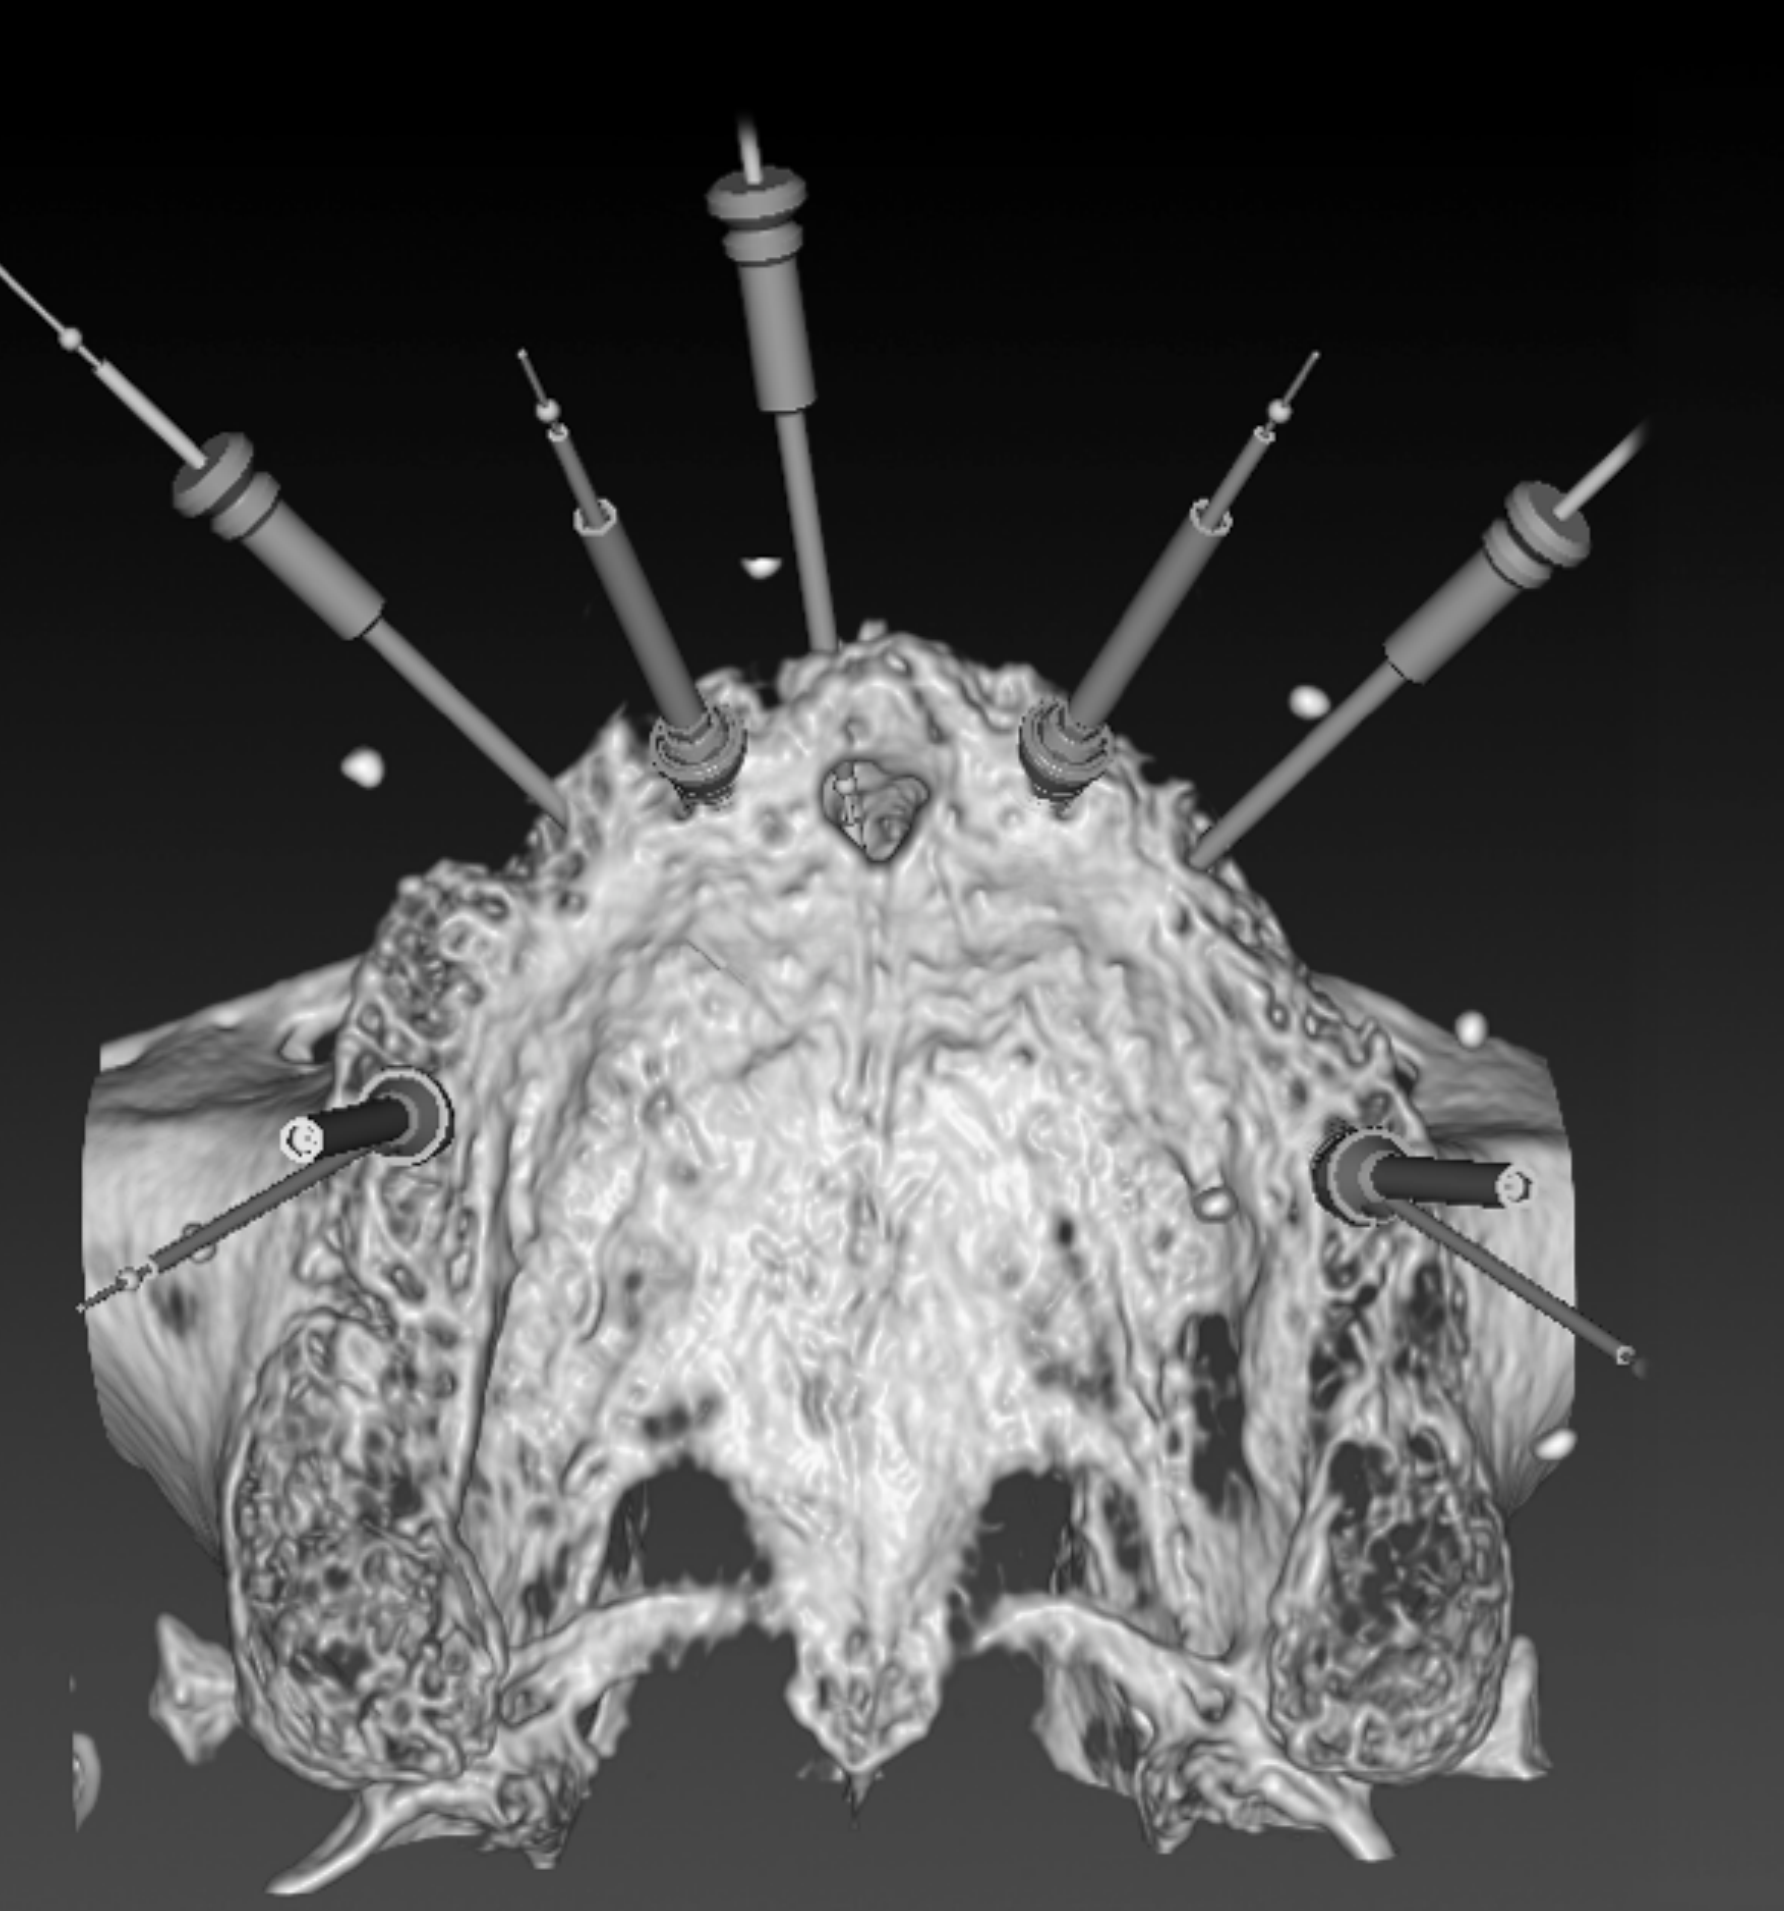
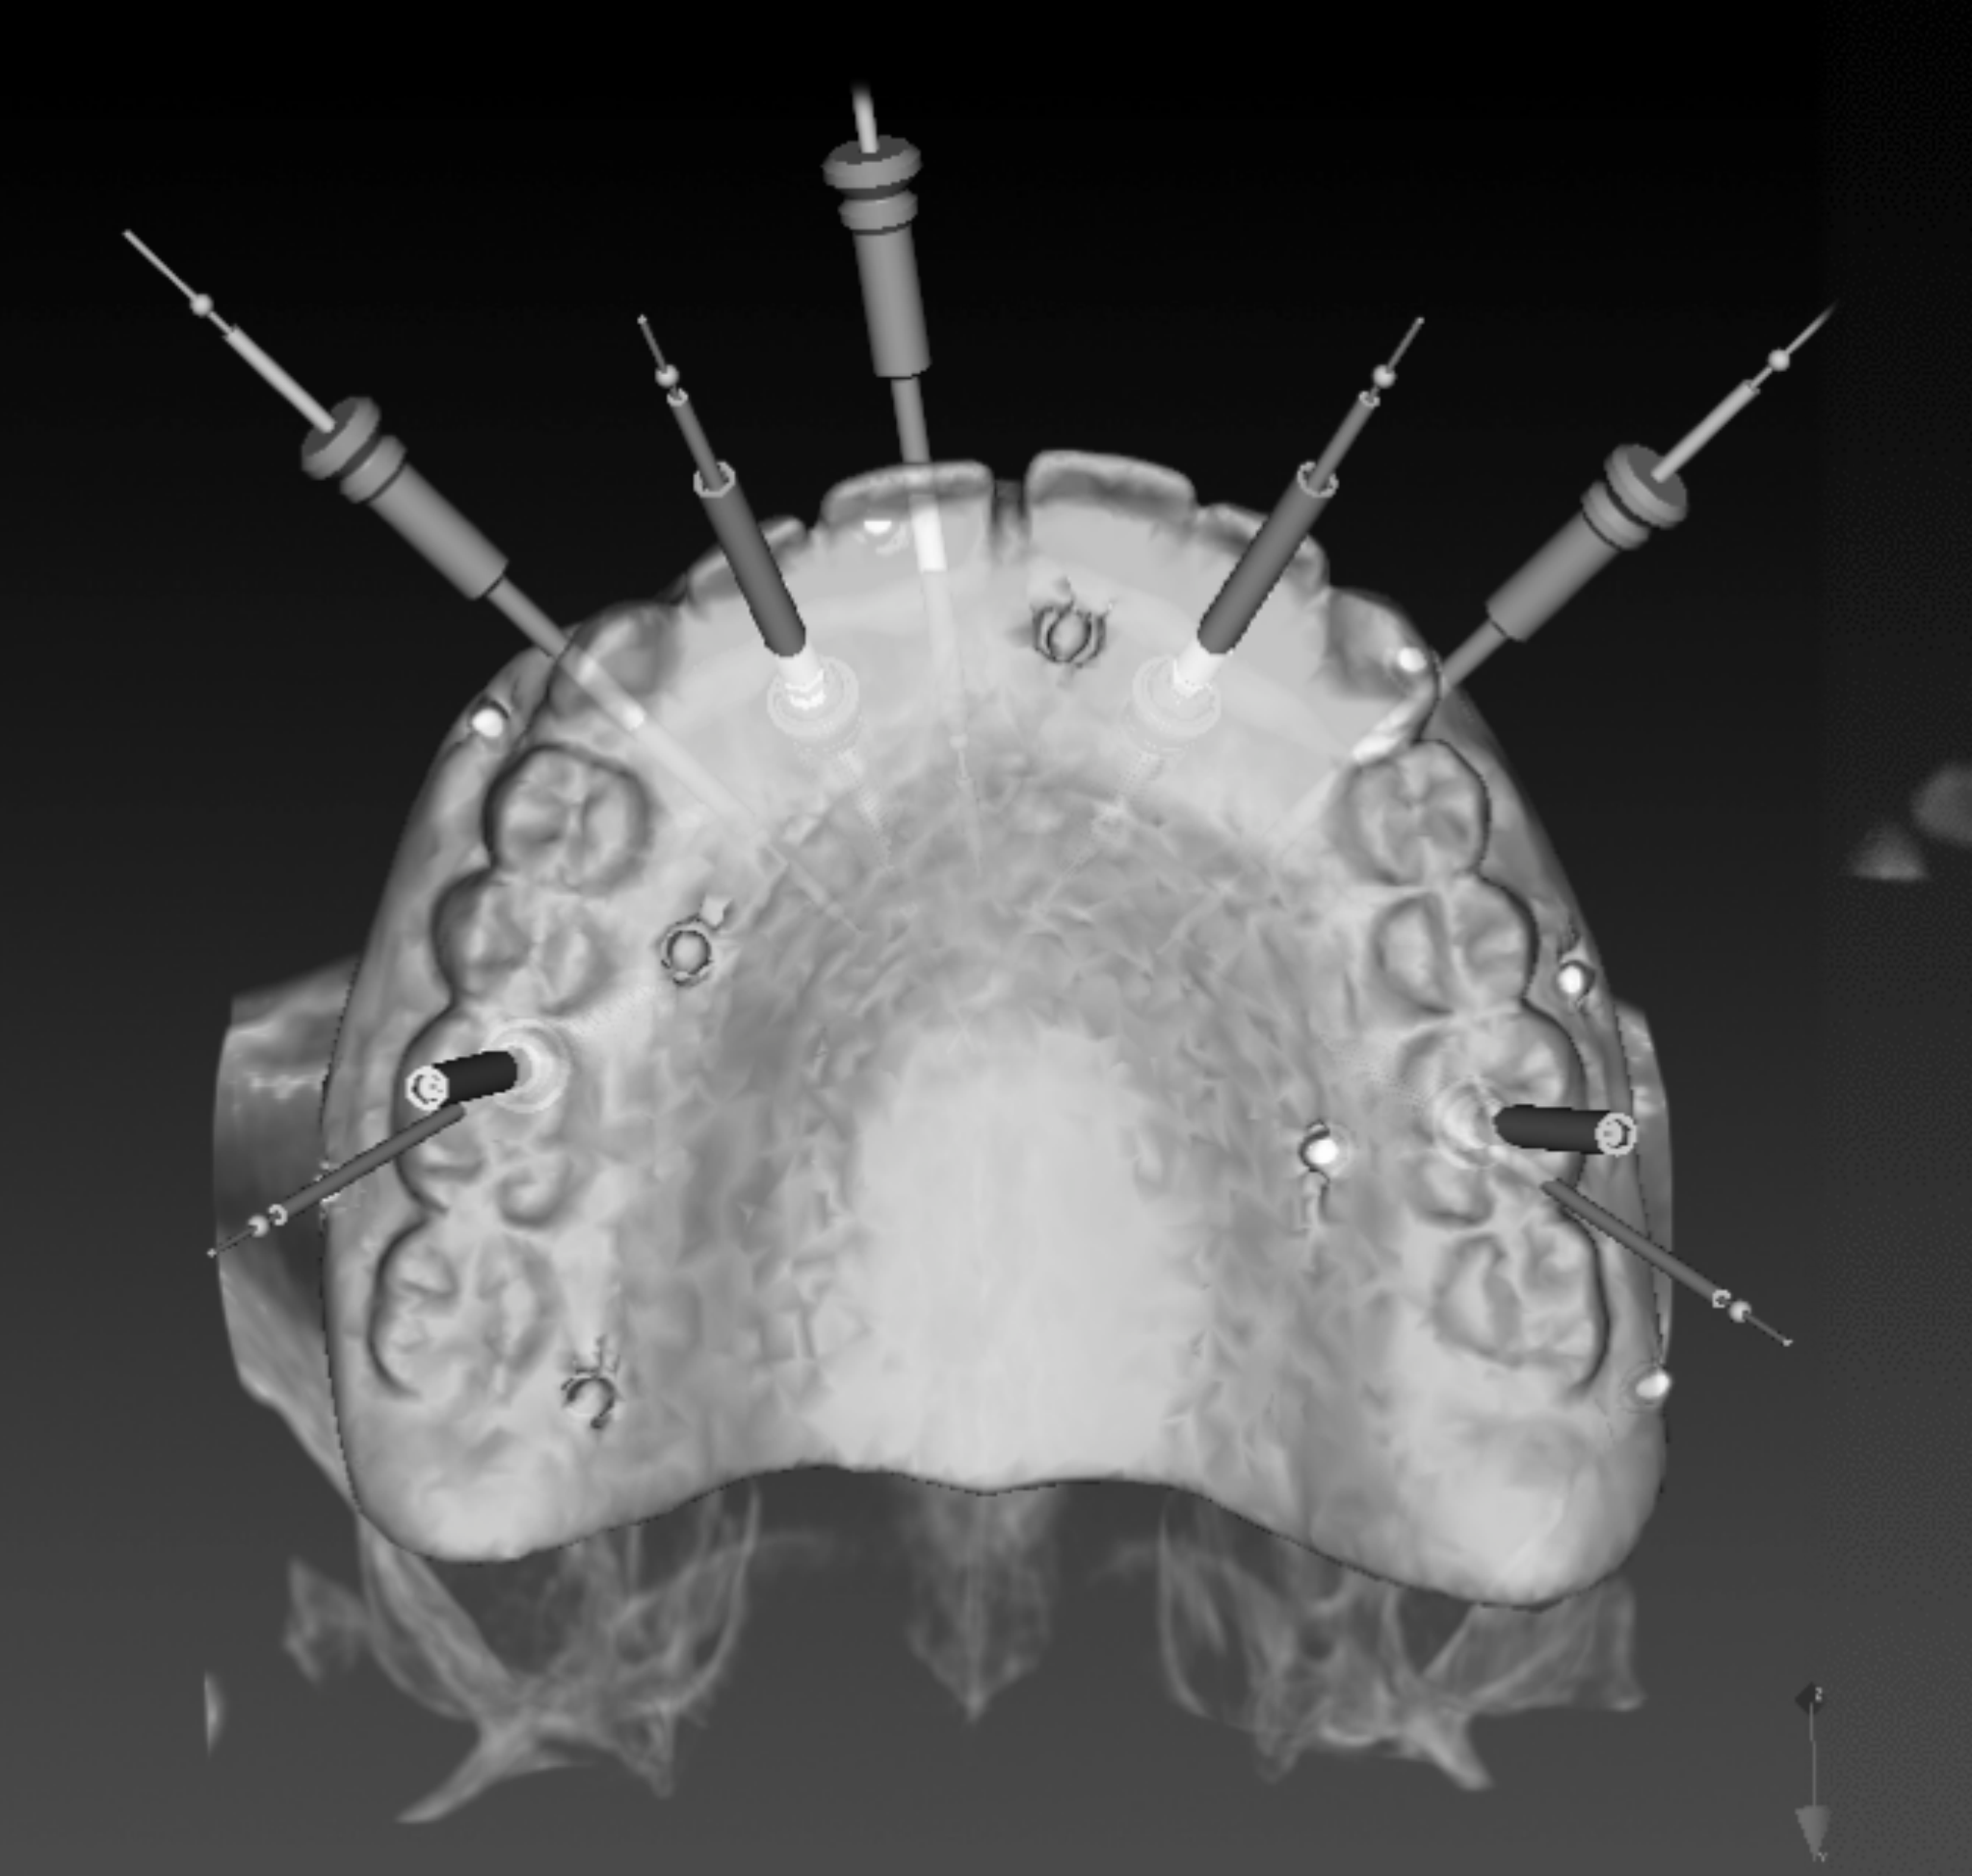
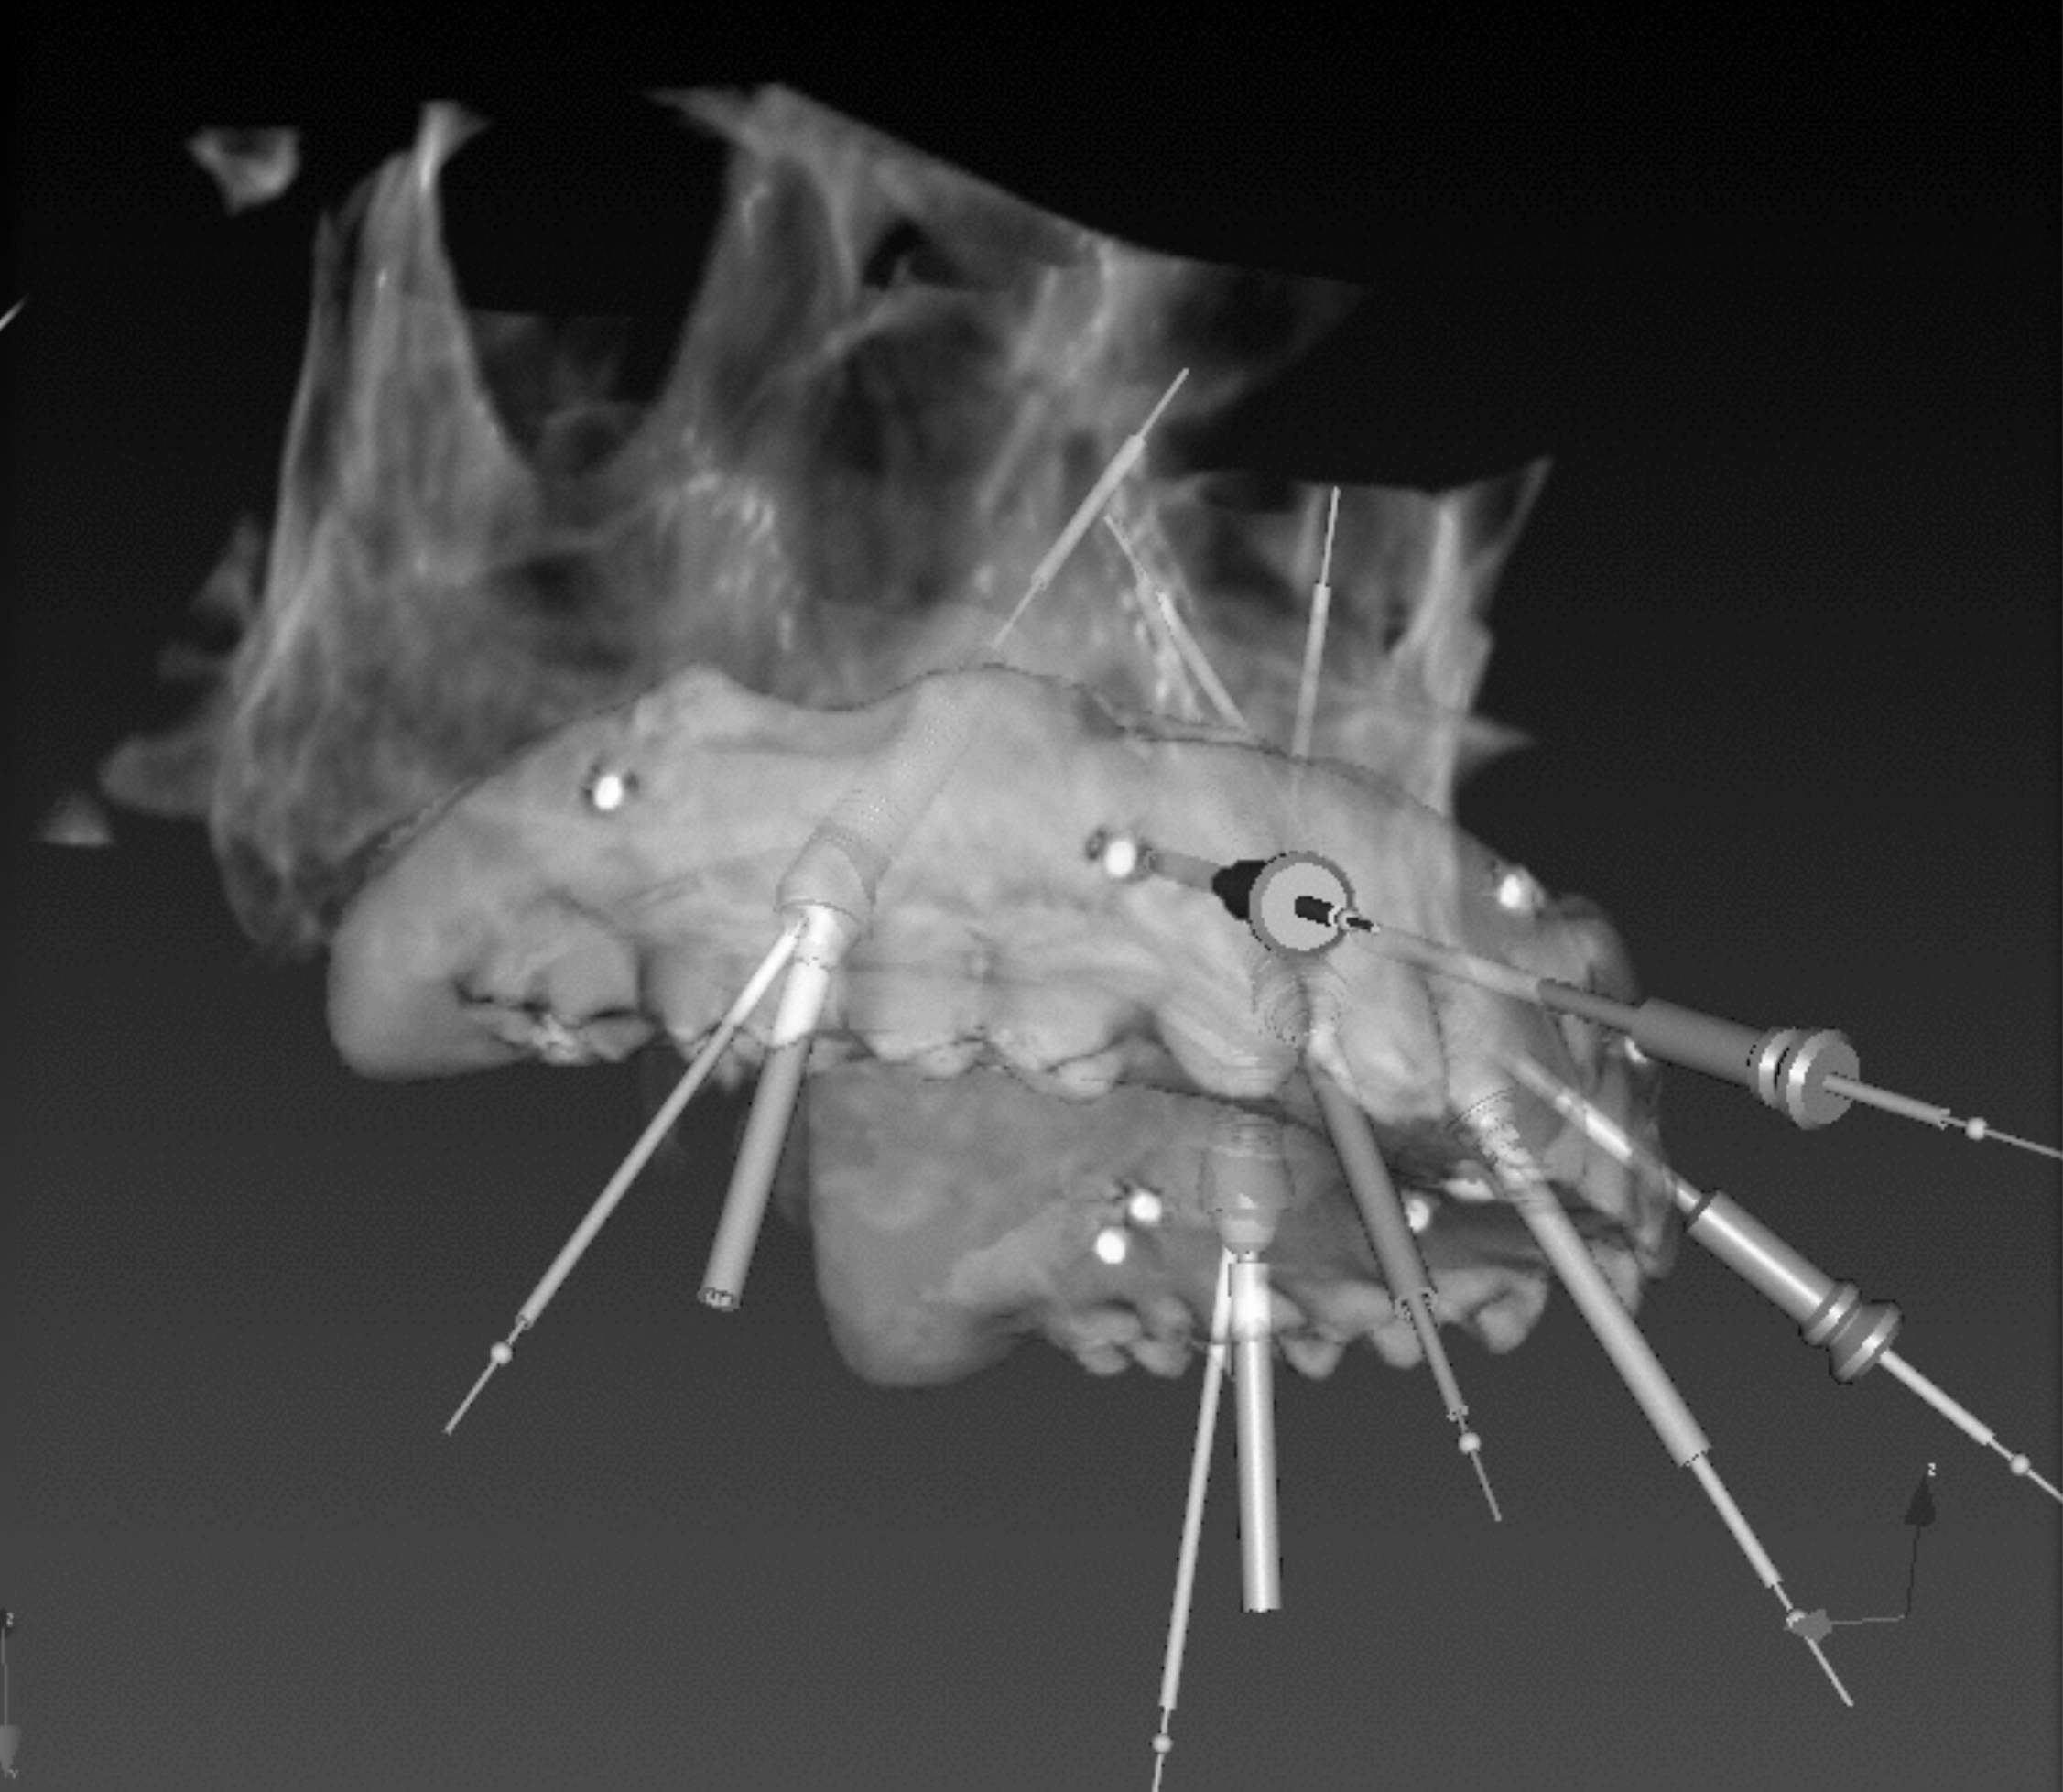
Prosthetically Driven Implant Placement28
Planning implant placement is prosthetically driven.
 |  |
 |
NobelClinician Planning – Virtual Surgery29
NobelClinician - Danielle Fox
Treatments
- Dental Code (x1!)
- Scan
- Edit CT scan
Software
- Scanner Orientation
- Refine Curve
- CT Preset
- Future Images
- Transfer Locations
- Slices
- Panoramic
- Perpendicular
- OK / Cancel
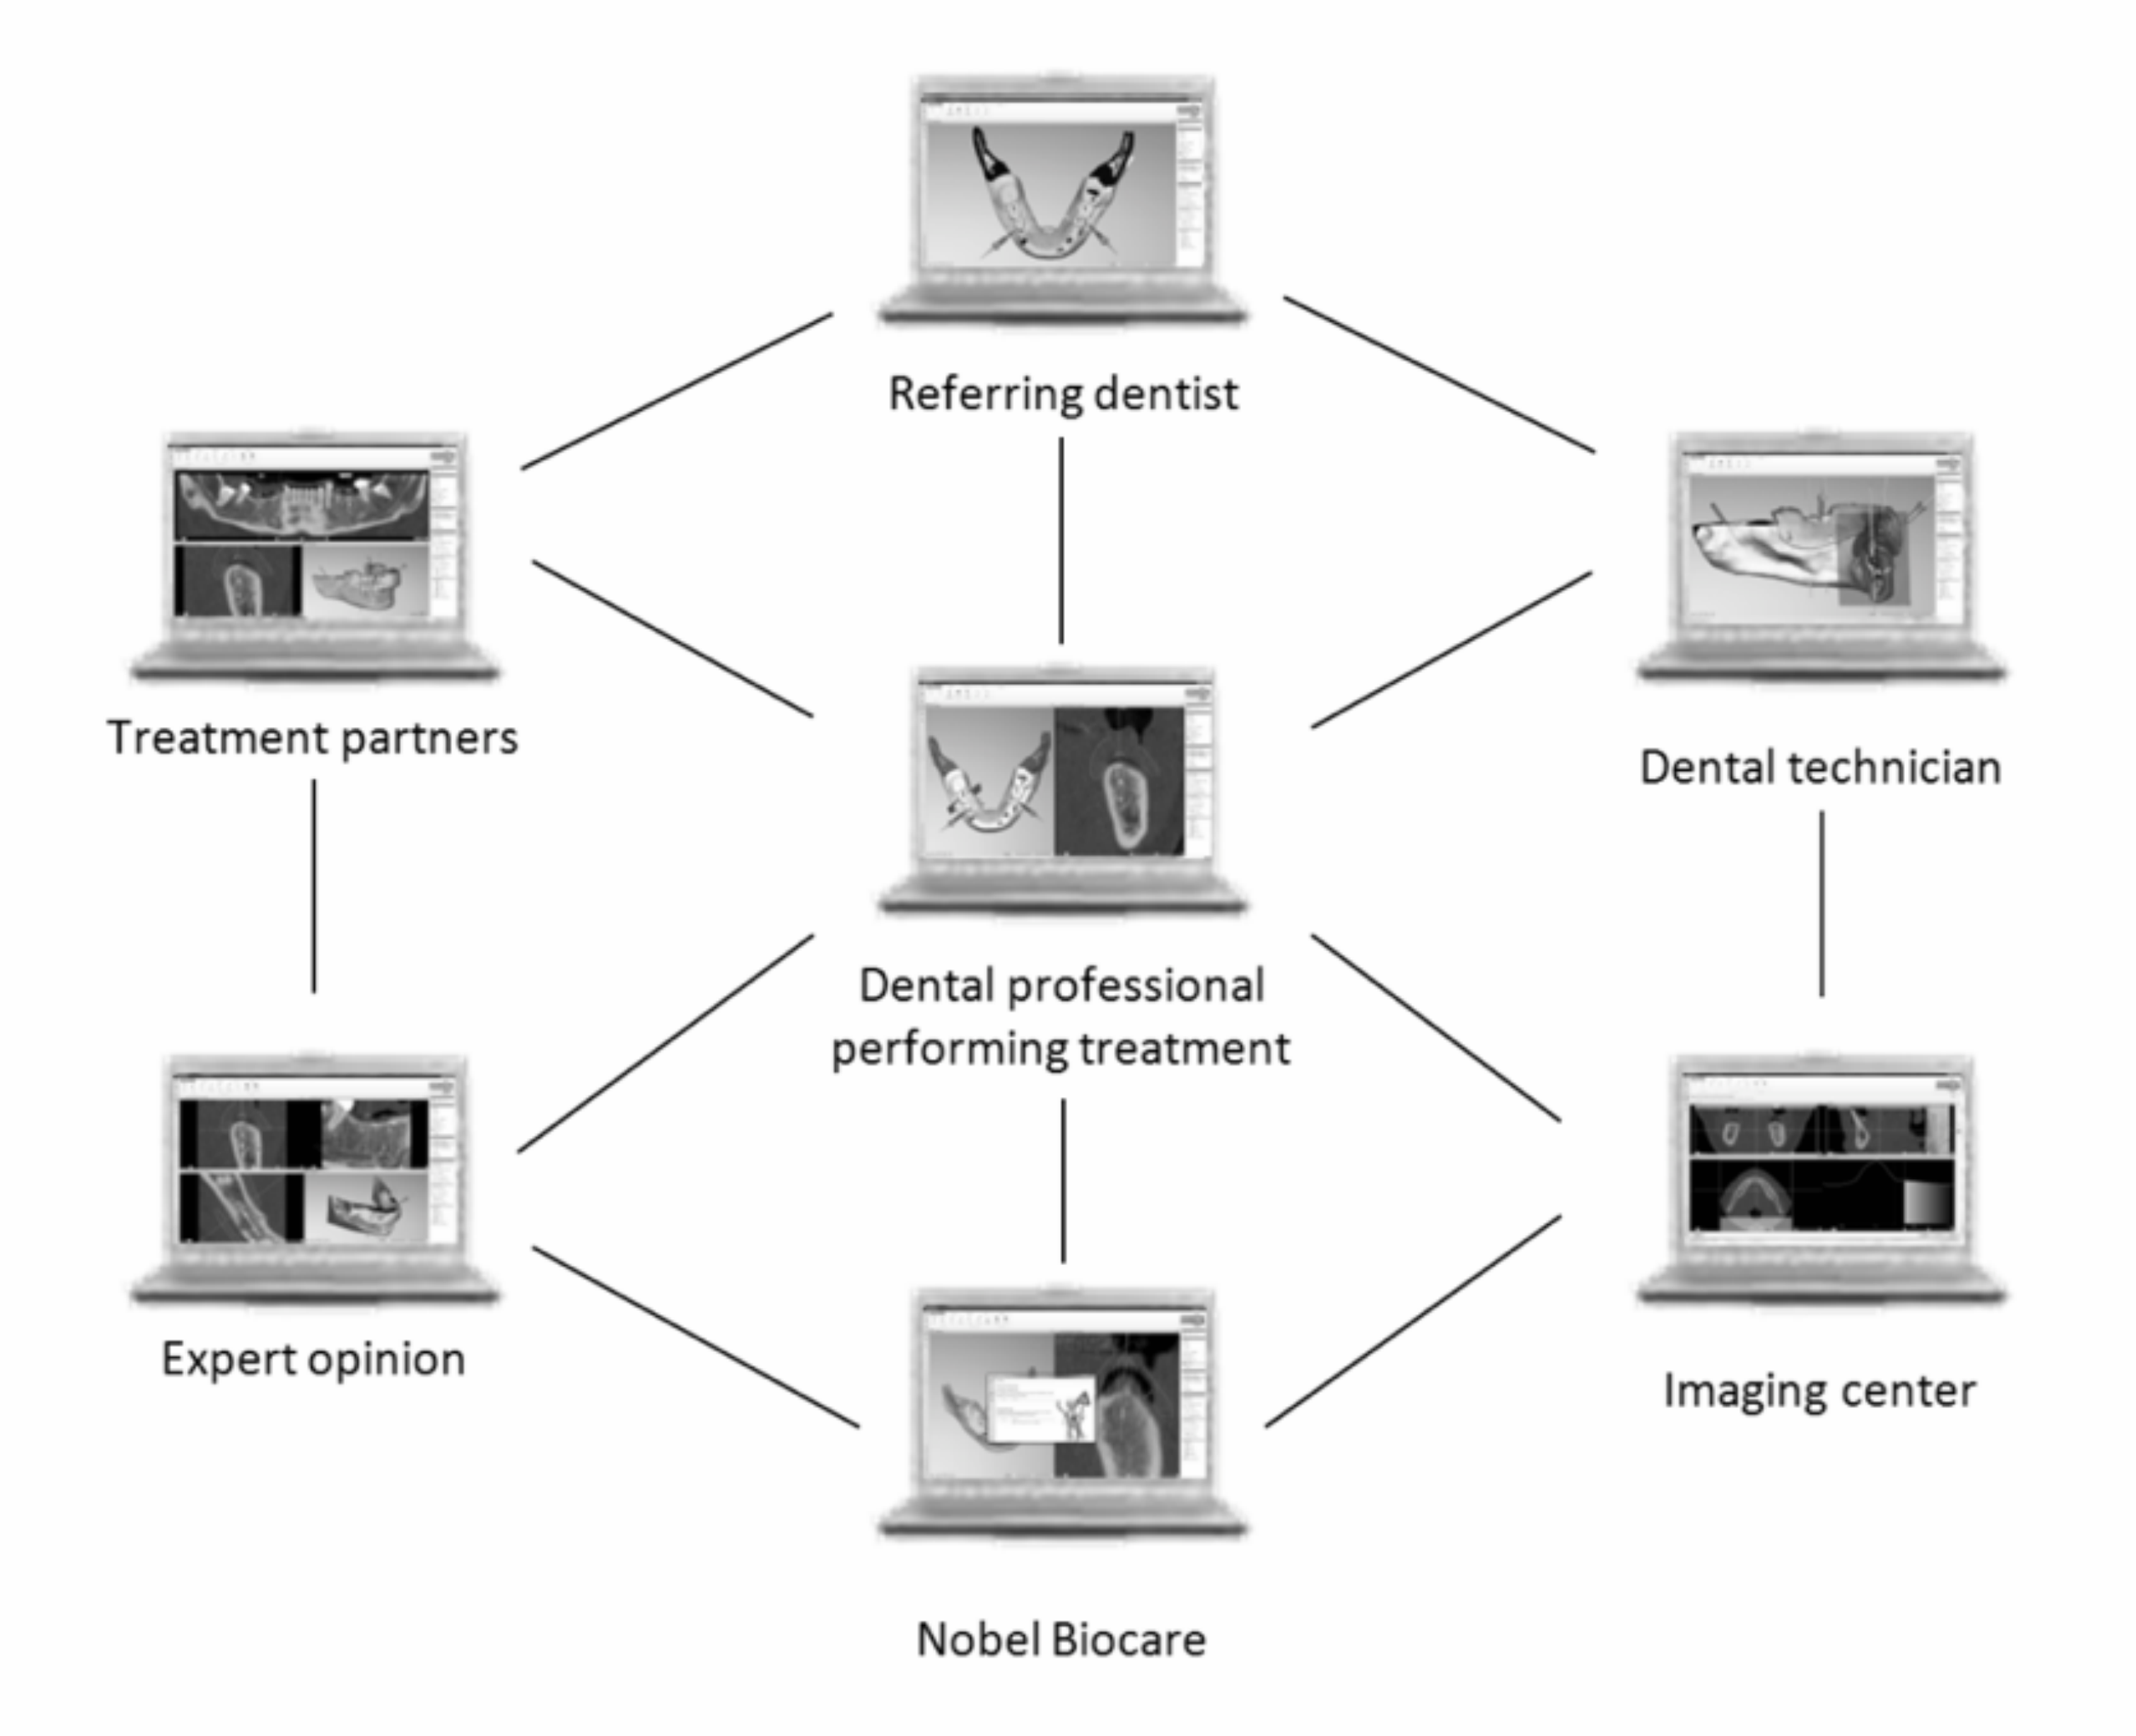
NobelConnect and Interdisciplinary Treatment303132
 |  |
Interaction Mode
- Brush
- Save
- Undo
- Radio
- Level / Window
- Change Workspace
- Set Focus
- Screenshot
- Rulers
Stereo Evaluation
- ( ) Attach to Core
- ( ) Attach to Guide
- (t) Master Model
- ( ) Treatments
- ( ) Teeth (7)
- ( ) Nerves (2)
- ( ) Teeth (3)
- ( ) Primelines (2)
- ( ) Registration (2)
- ( ) Space (4)
Use Slices File
- Critical for complex interdisciplinary treatment
Implant anchorage is then prosthetically directed.
Implant Surgical Pathways33
| Primary Pathway | Sub-Method / Description | Advanced Options / Materials |
|---|---|---|
| Graftless | Axial | Immediate Loading |
| Tilted | Anterior sinus posterior sinus pterygoid Zygoma other | |
| Grafting ↓ | Sinus Labial onlay Ridge splitting GBR Interpositional Distraction Osteogenesis LeFort 1 Free tissue transfer | Material Categories: • Autogenous • Allograft • Xenograft • Synthetic • BMPs • Gene Therapy |
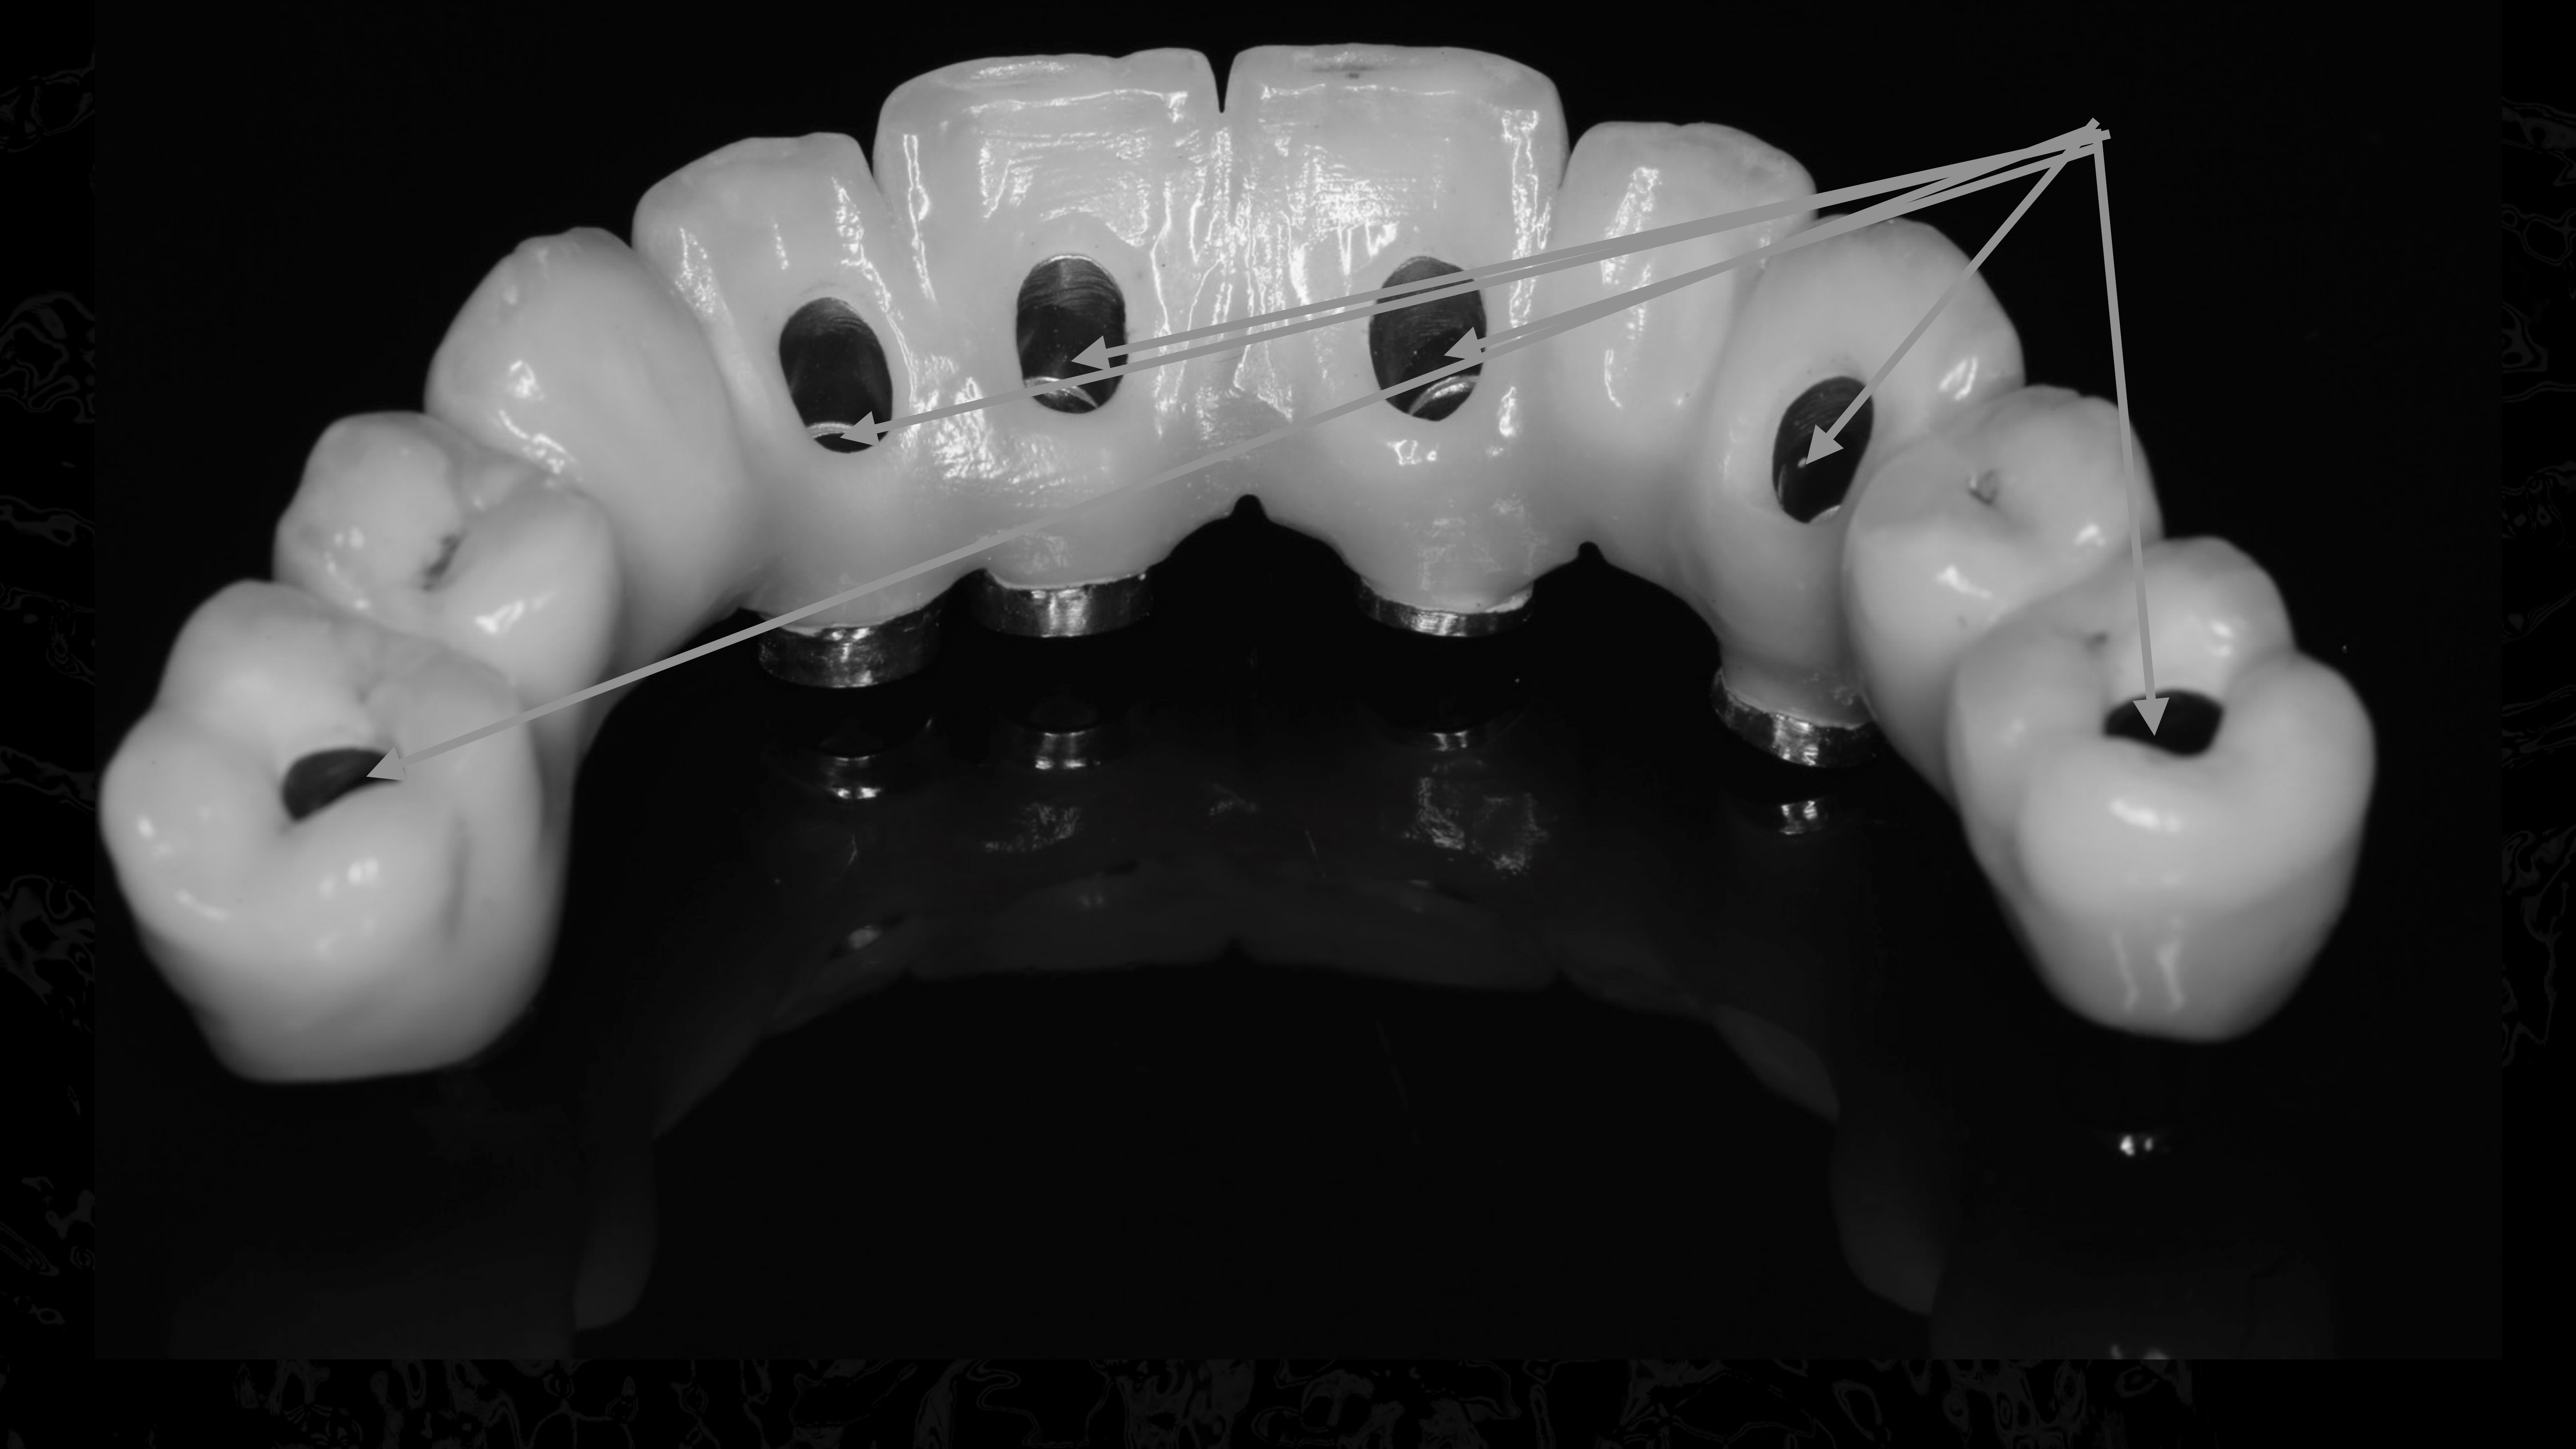
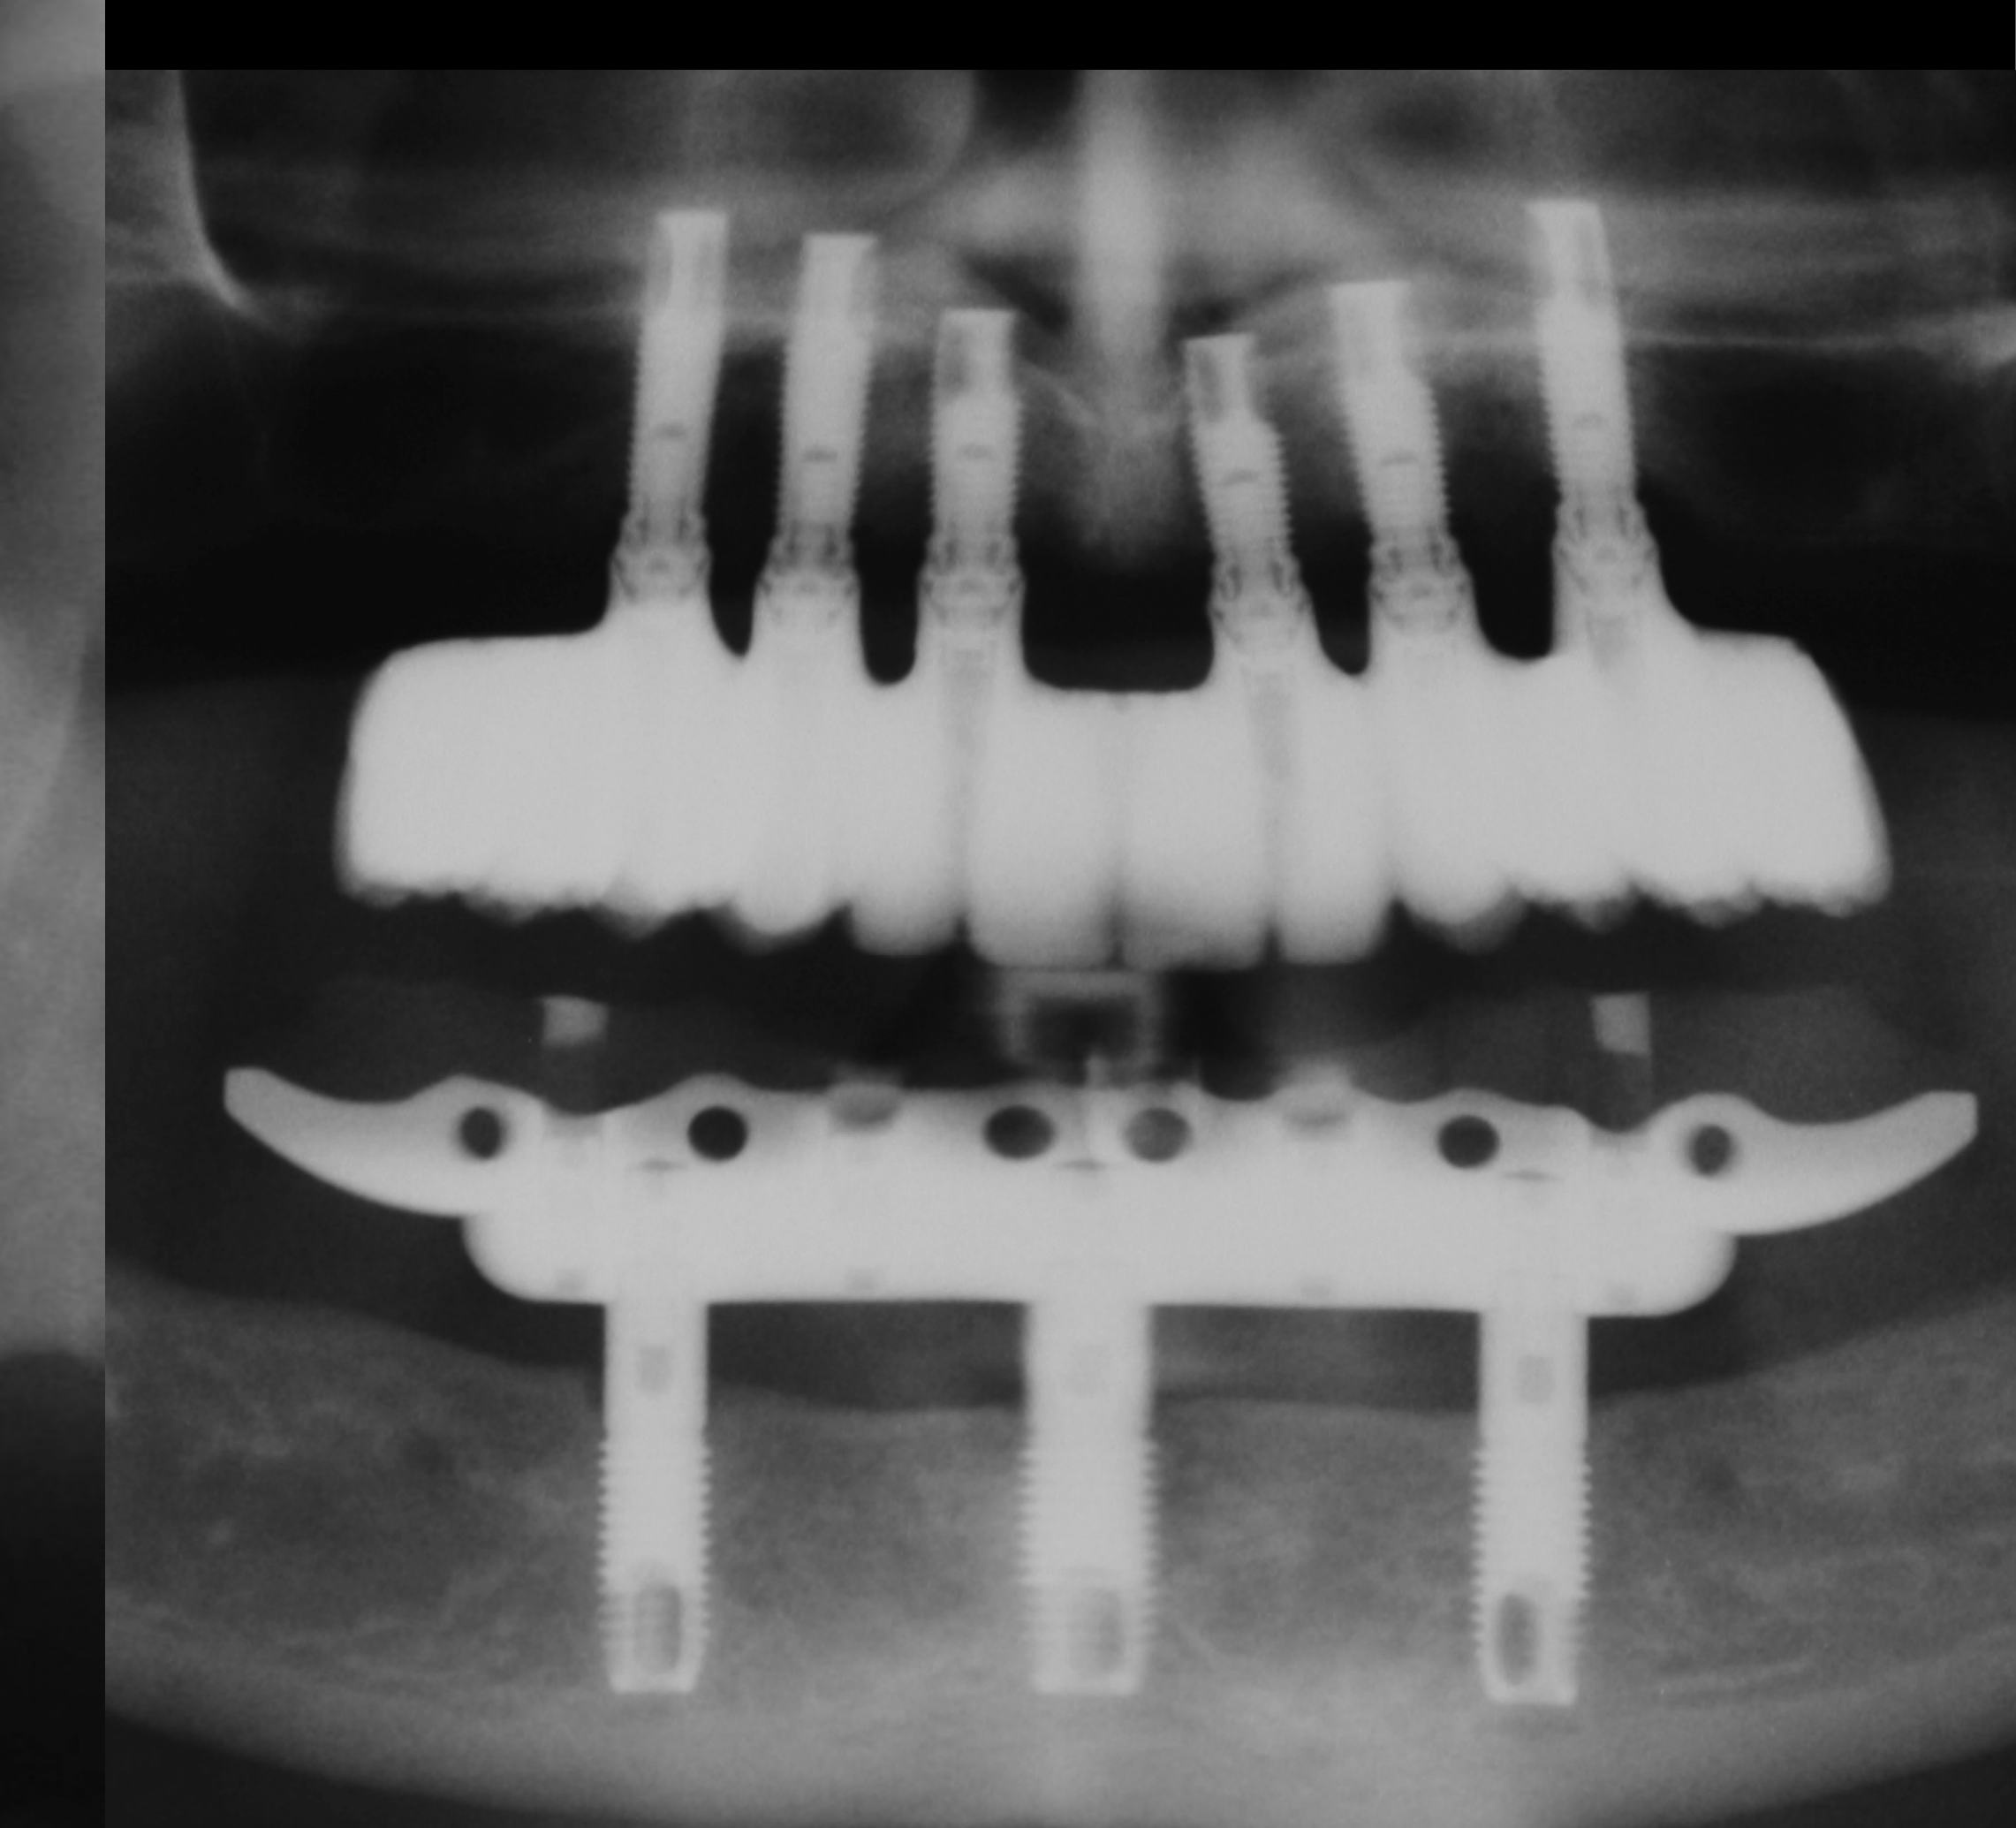
Axial Implants Without Grafting34
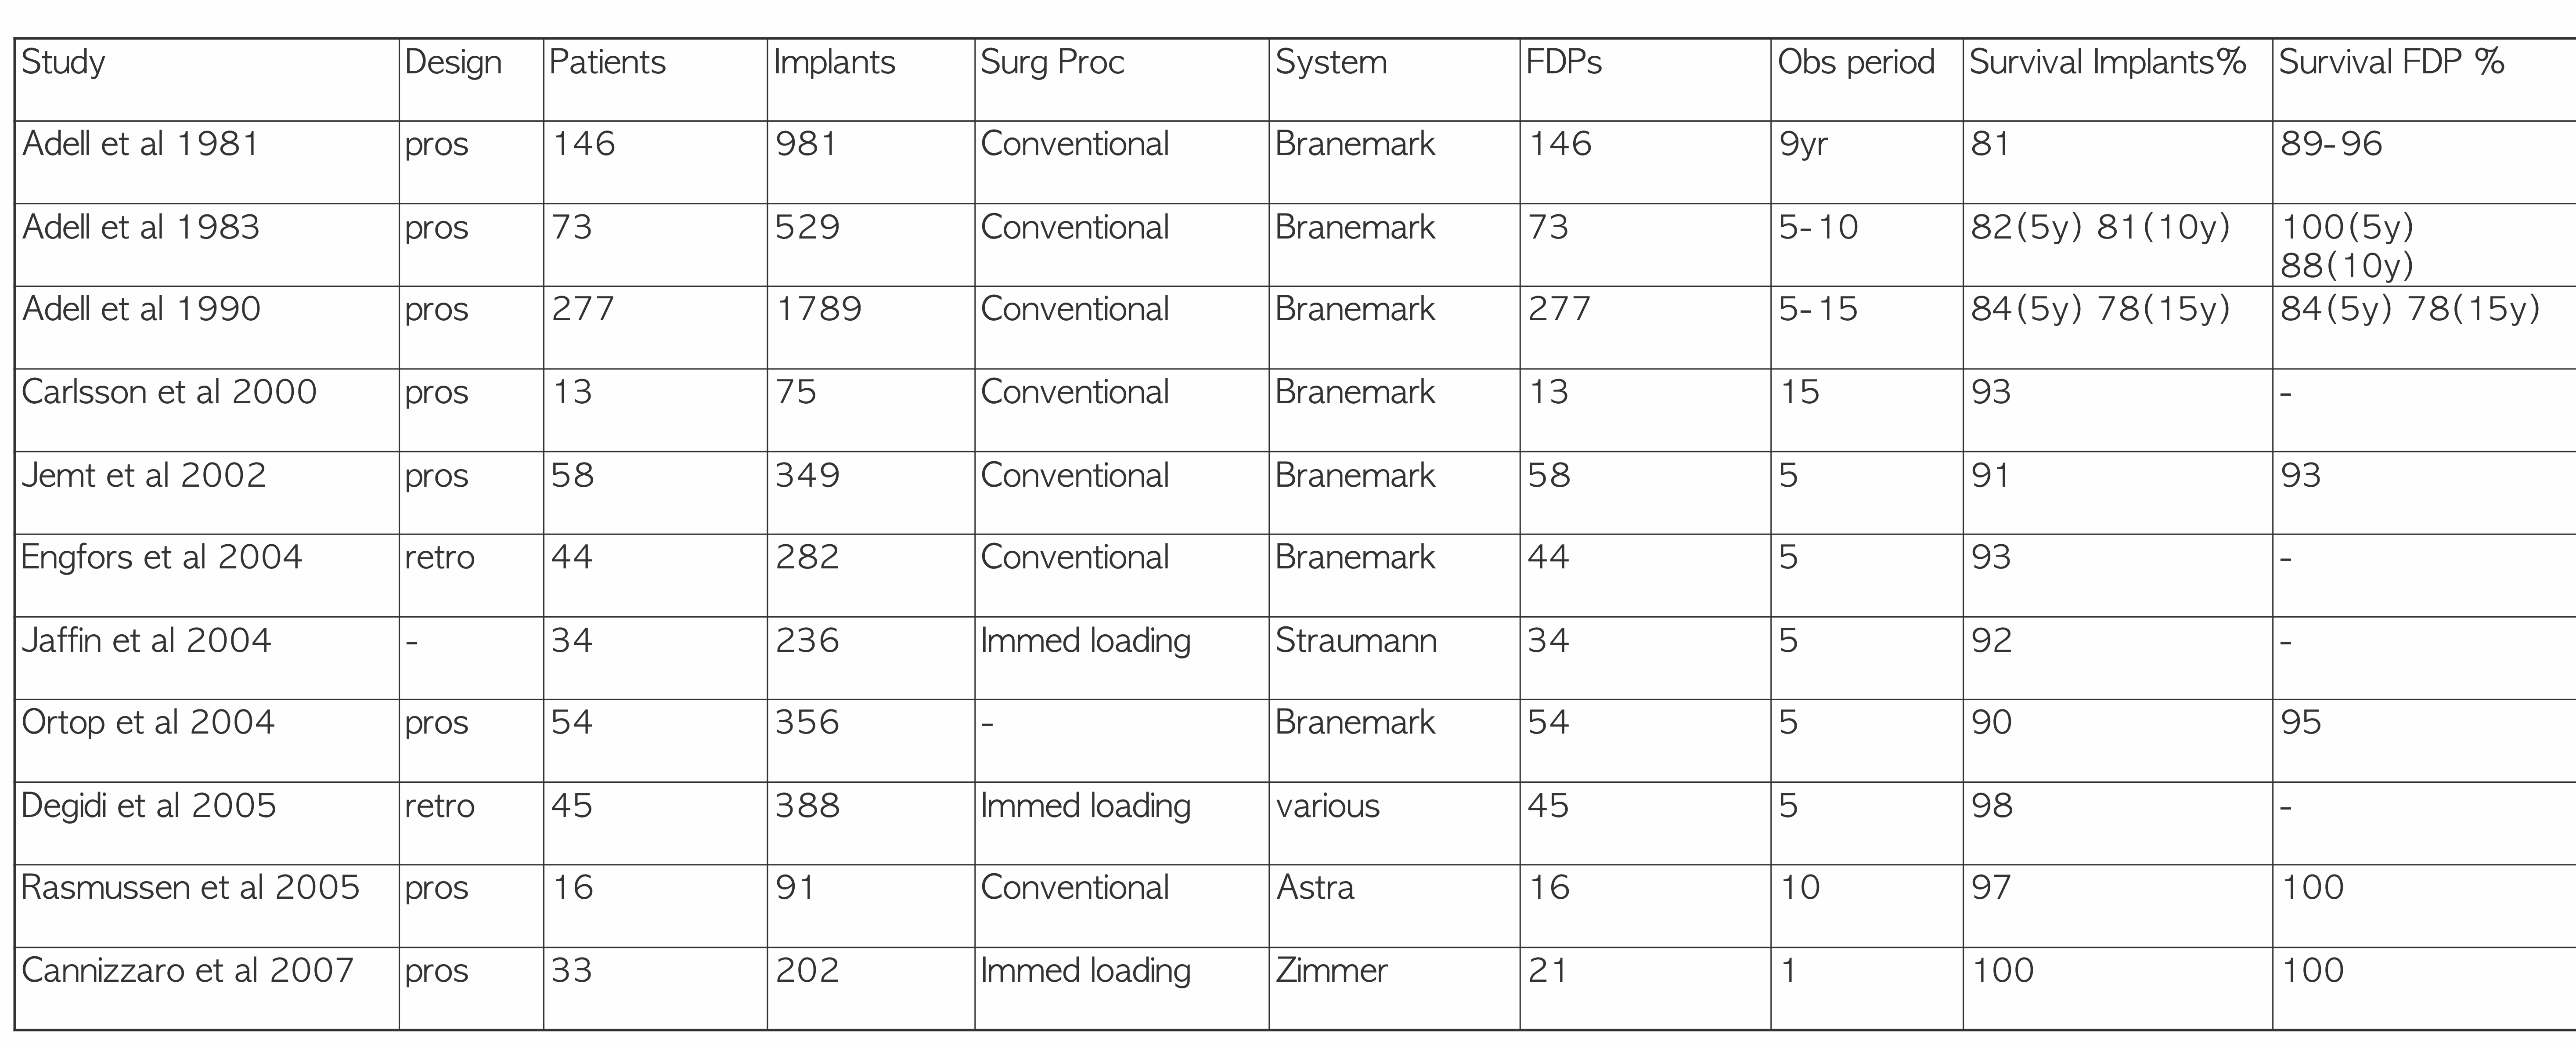
Studies Restoring the Edentulous Maxilla with Fixed Prostheses35
| Study | Design | Patients | Implants | Surg Proc | System | FDPs | Obs Period | Survival Implants % | Survival FDP % |
|---|---|---|---|---|---|---|---|---|---|
| Adell et al 1981 | pros | 146 | 981 | Conventional | Branemark | 146 | 9 yr | 81 | 89–96 |
| Adell et al 1983 | pros | 73 | 529 | Conventional | Branemark | 73 | 5–10 yr | 82 (5y), 81 (10y) | 100 (5y), 88 (10y) |
| Adell et al 1990 | pros | 277 | 1789 | Conventional | Branemark | 277 | 5–15 yr | 84 (5y), 78 (15y) | 84 (5y), 78 (15y) |
| Carlsson et al 2000 | pros | 13 | 75 | Conventional | Branemark | 13 | 15 yr | 93 | — |
| Jemt et al 2002 | pros | 58 | 349 | Conventional | Branemark | 58 | 5 yr | 91 | 93 |
| Engfors et al 2004 | retro | 44 | 282 | Conventional | Branemark | 44 | 5 yr | 93 | — |
| Jaffin et al 2004 | — | 34 | 236 | Immed loading | Straumann | 34 | 5 yr | 92 | — |
| Ortop et al 2004 | pros | 54 | 356 | — | Branemark | 54 | 5 yr | 90 | 95 |
| Degidi et al 2005 | retro | 45 | 388 | Immed loading | various | 45 | 5 yr | 98 | — |
| Rasmussen et al 2005 | pros | 16 | 91 | Conventional | Astra | 16 | 10 yr | 97 | 100 |
| Cannizzaro et al 2007 | pros | 33 | 202 | Immed loading | Zimmer | 21 | 1 yr | 100 | 100 |
Tilted Implants Without Grafting36
Tilted implants no grafting
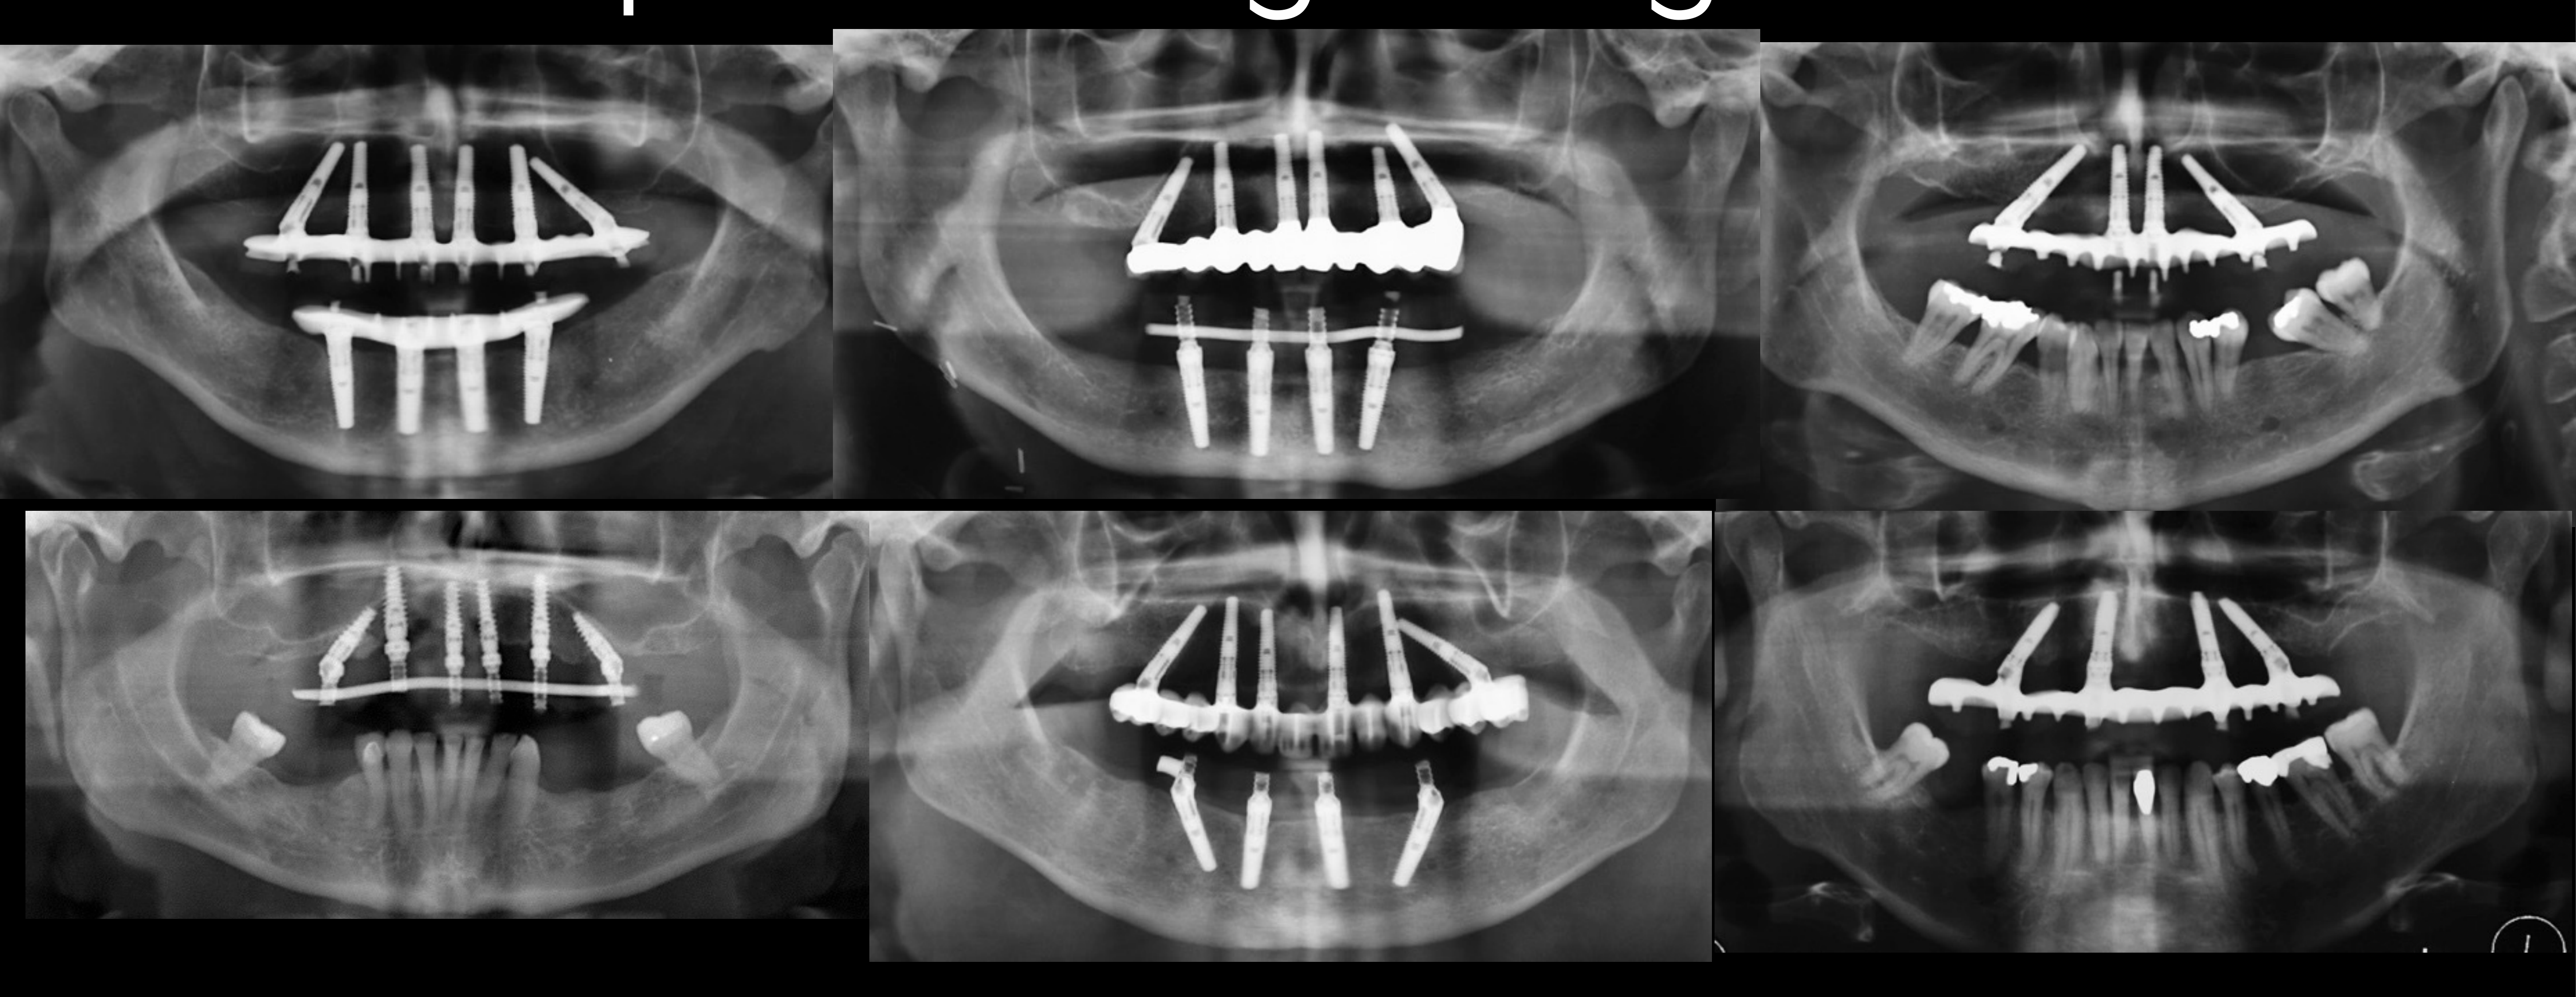
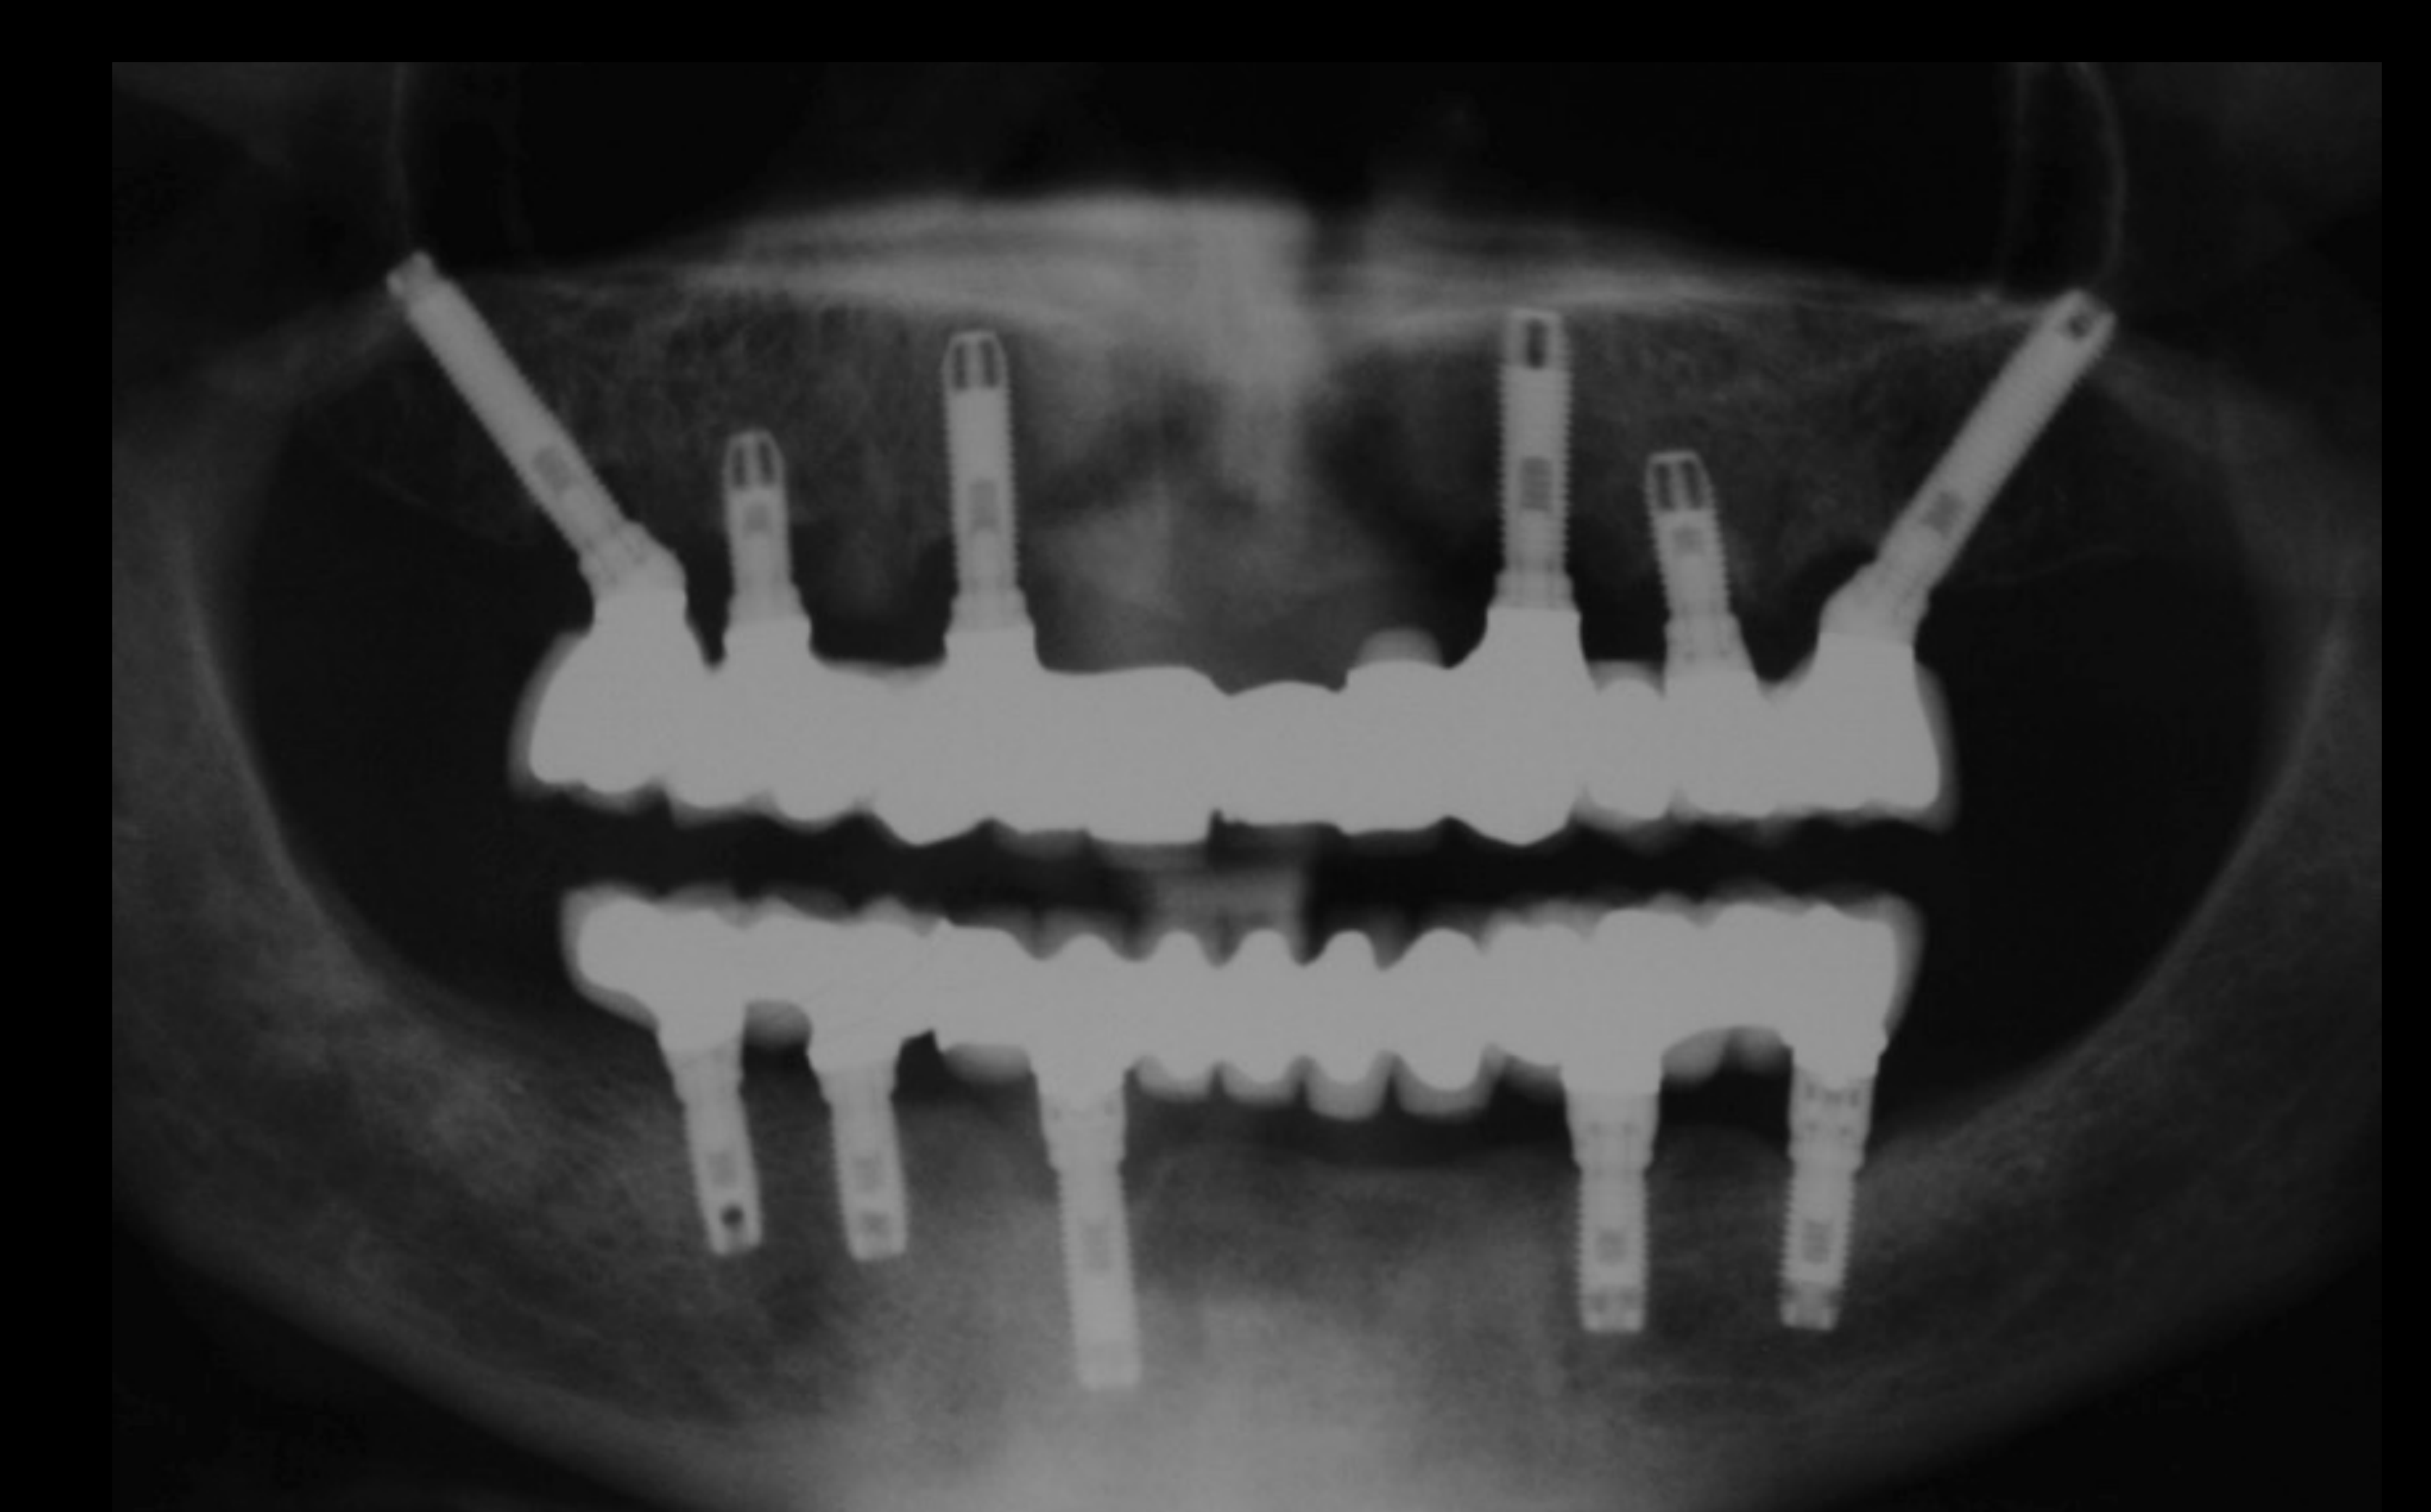
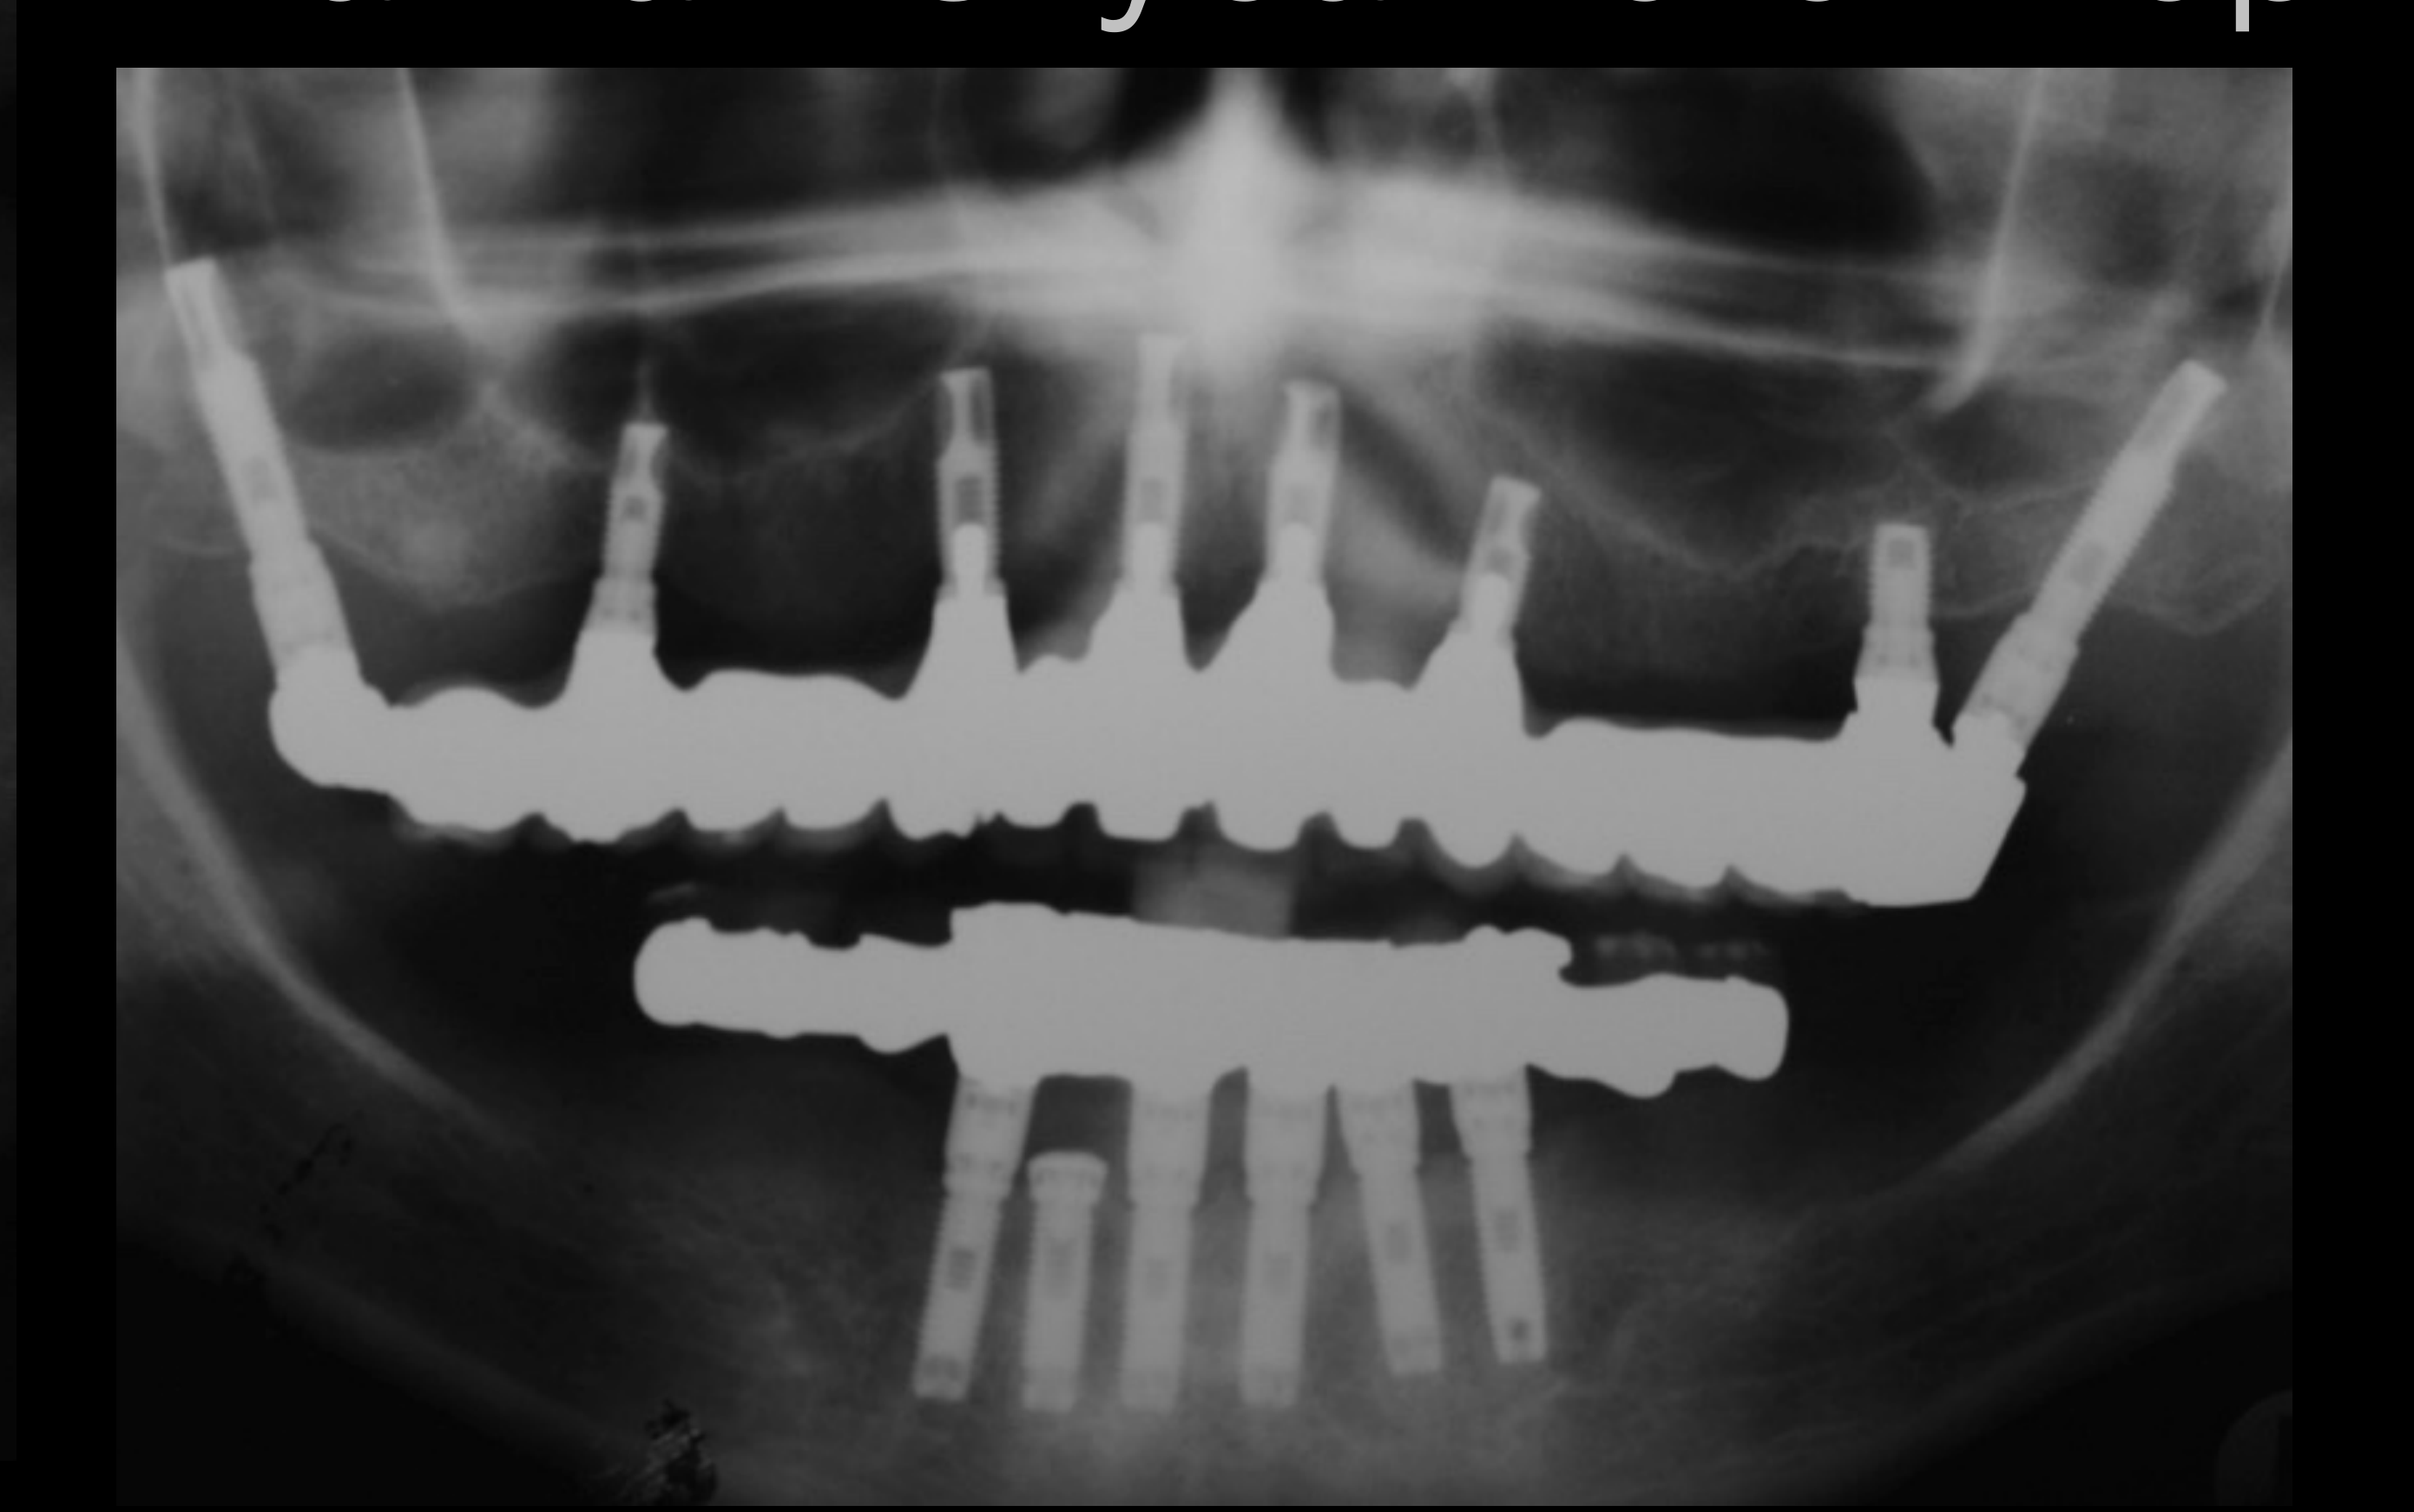
Follow-up Outcomes37
- Maxilla: 13-year follow-up and 17-year follow-up
- Mandible: 24-year follow-up
 |  |
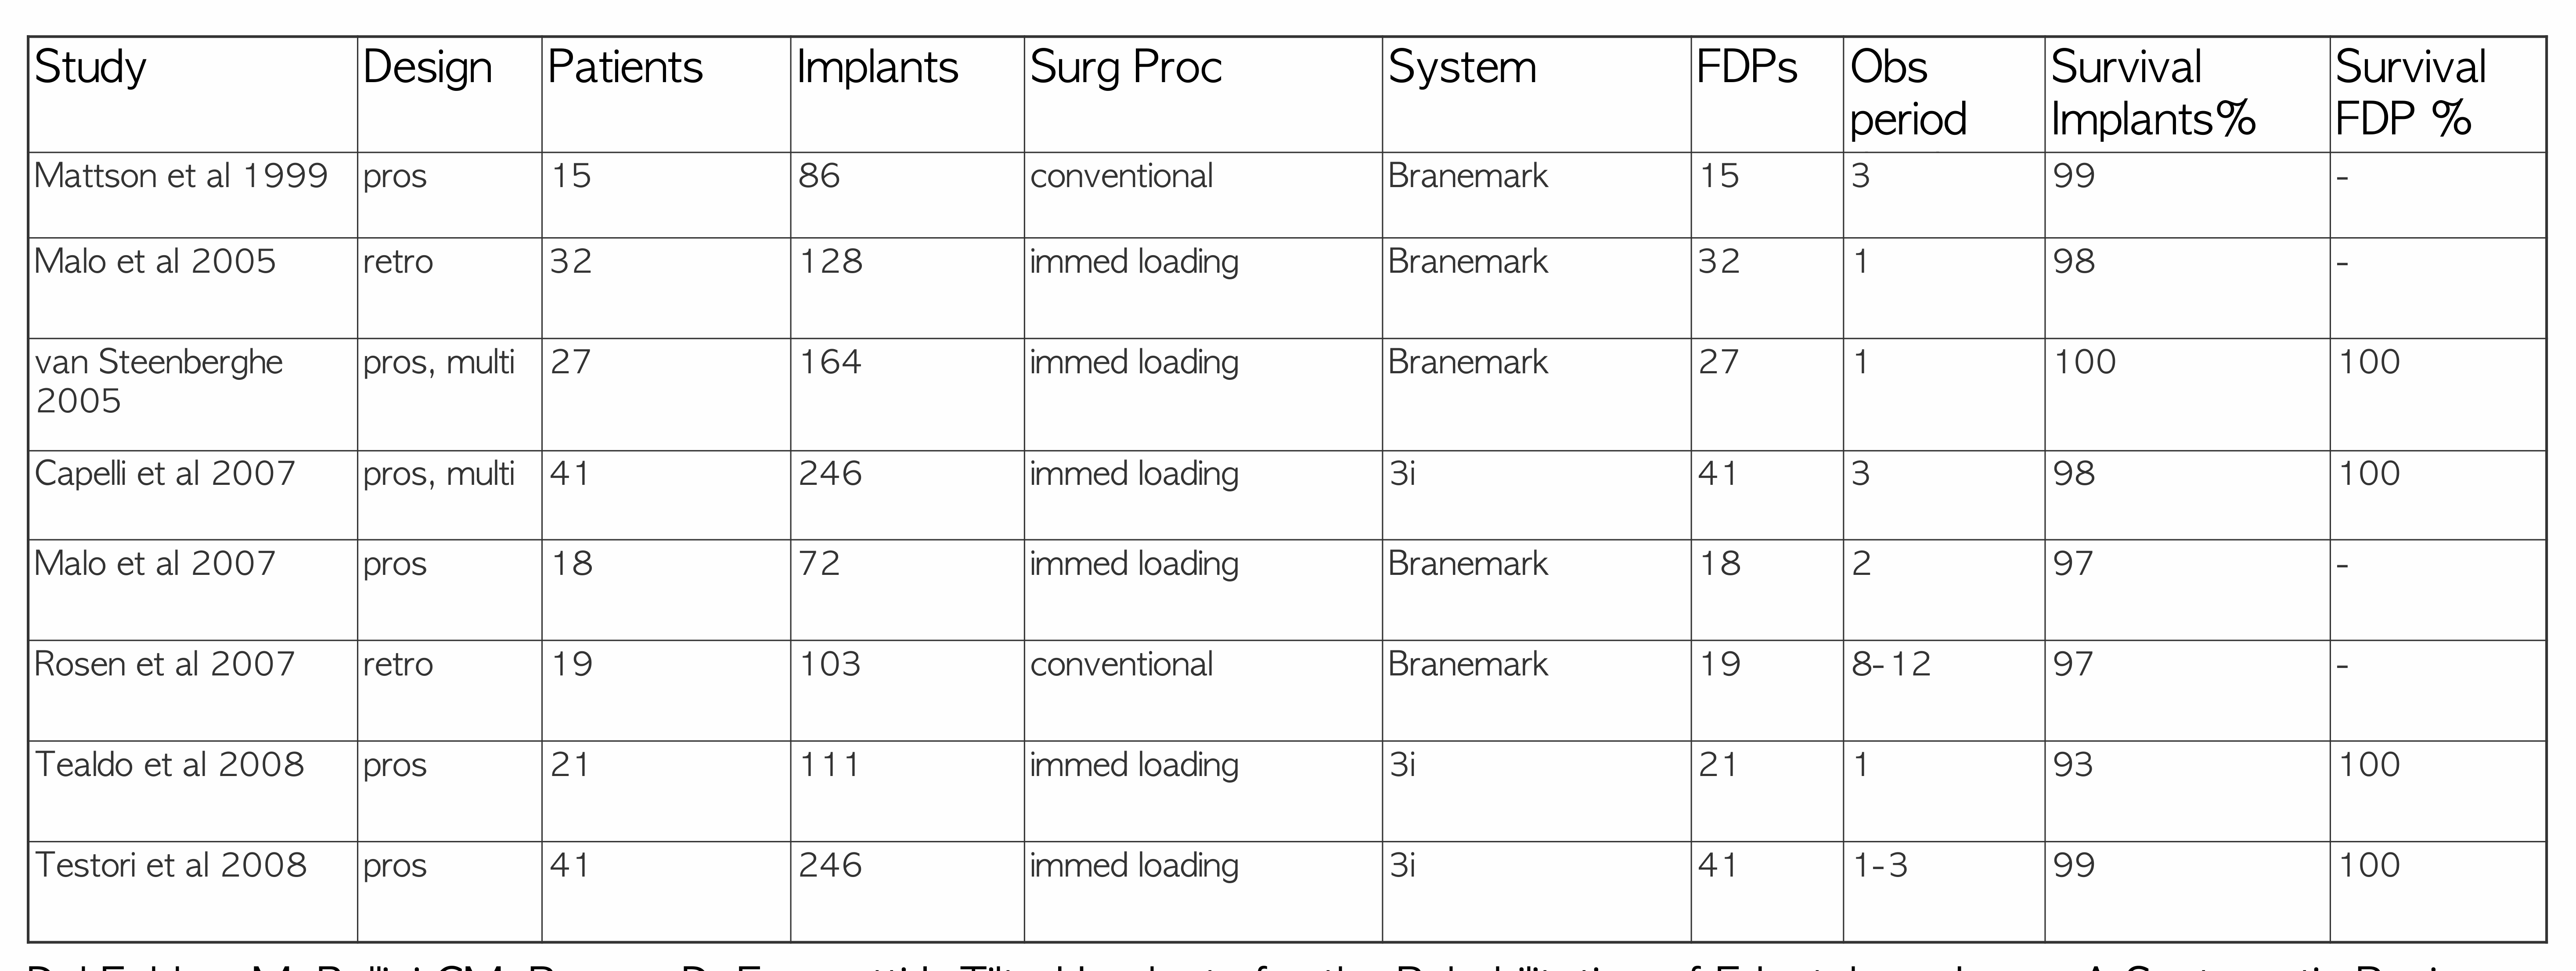
Clinical Outcomes of Tilted Implants38
| Study | Design | Patients | Implants | Surg Proc | System | FDPs | Obs period | Survival Implants % | Survival FDP % |
|---|---|---|---|---|---|---|---|---|---|
| Mattson et al 1999 | pros | 15 | 86 | conventional | Branemark | 15 | 3 | 99 | - |
| Malo et al 2005 | retro | 32 | 128 | immed loading | Branemark | 32 | 1 | 98 | - |
| van Steenberghe 2005 | pros, multi | 27 | 164 | immed loading | Branemark | 27 | 1 | 100 | 100 |
| Capelli et al 2007 | pros, multi | 41 | 246 | immed loading | 3i | 41 | 3 | 98 | 100 |
| Malo et al 2007 | pros | 18 | 72 | immed loading | Branemark | 18 | 2 | 97 | - |
| Rosen et al 2007 | retro | 19 | 103 | conventional | Branemark | 19 | 8-12 | 97 | - |
| Tealdo et al 2008 | pros | 21 | 111 | immed loading | 3i | 21 | 1 | 93 | 100 |
| Testori et al 2008 | pros | 41 | 246 | immed loading | 3i | 41 | 1-3 | 99 | 100 |
Del Fabbro M, Bellini CM, Romeo D, Francetti L. Tilted Implants for the Rehabilitation of Edentulous Jaws: A Systematic Review. Clin Implant Dent Relat Res. 2011
Patzelt, Bahat, Reynolds, Strub. The All-on-Four Treatment Concept: A Systematic Review. CIDRR 2014 16;6
Maxillary Fixed Prostheses Outcomes39
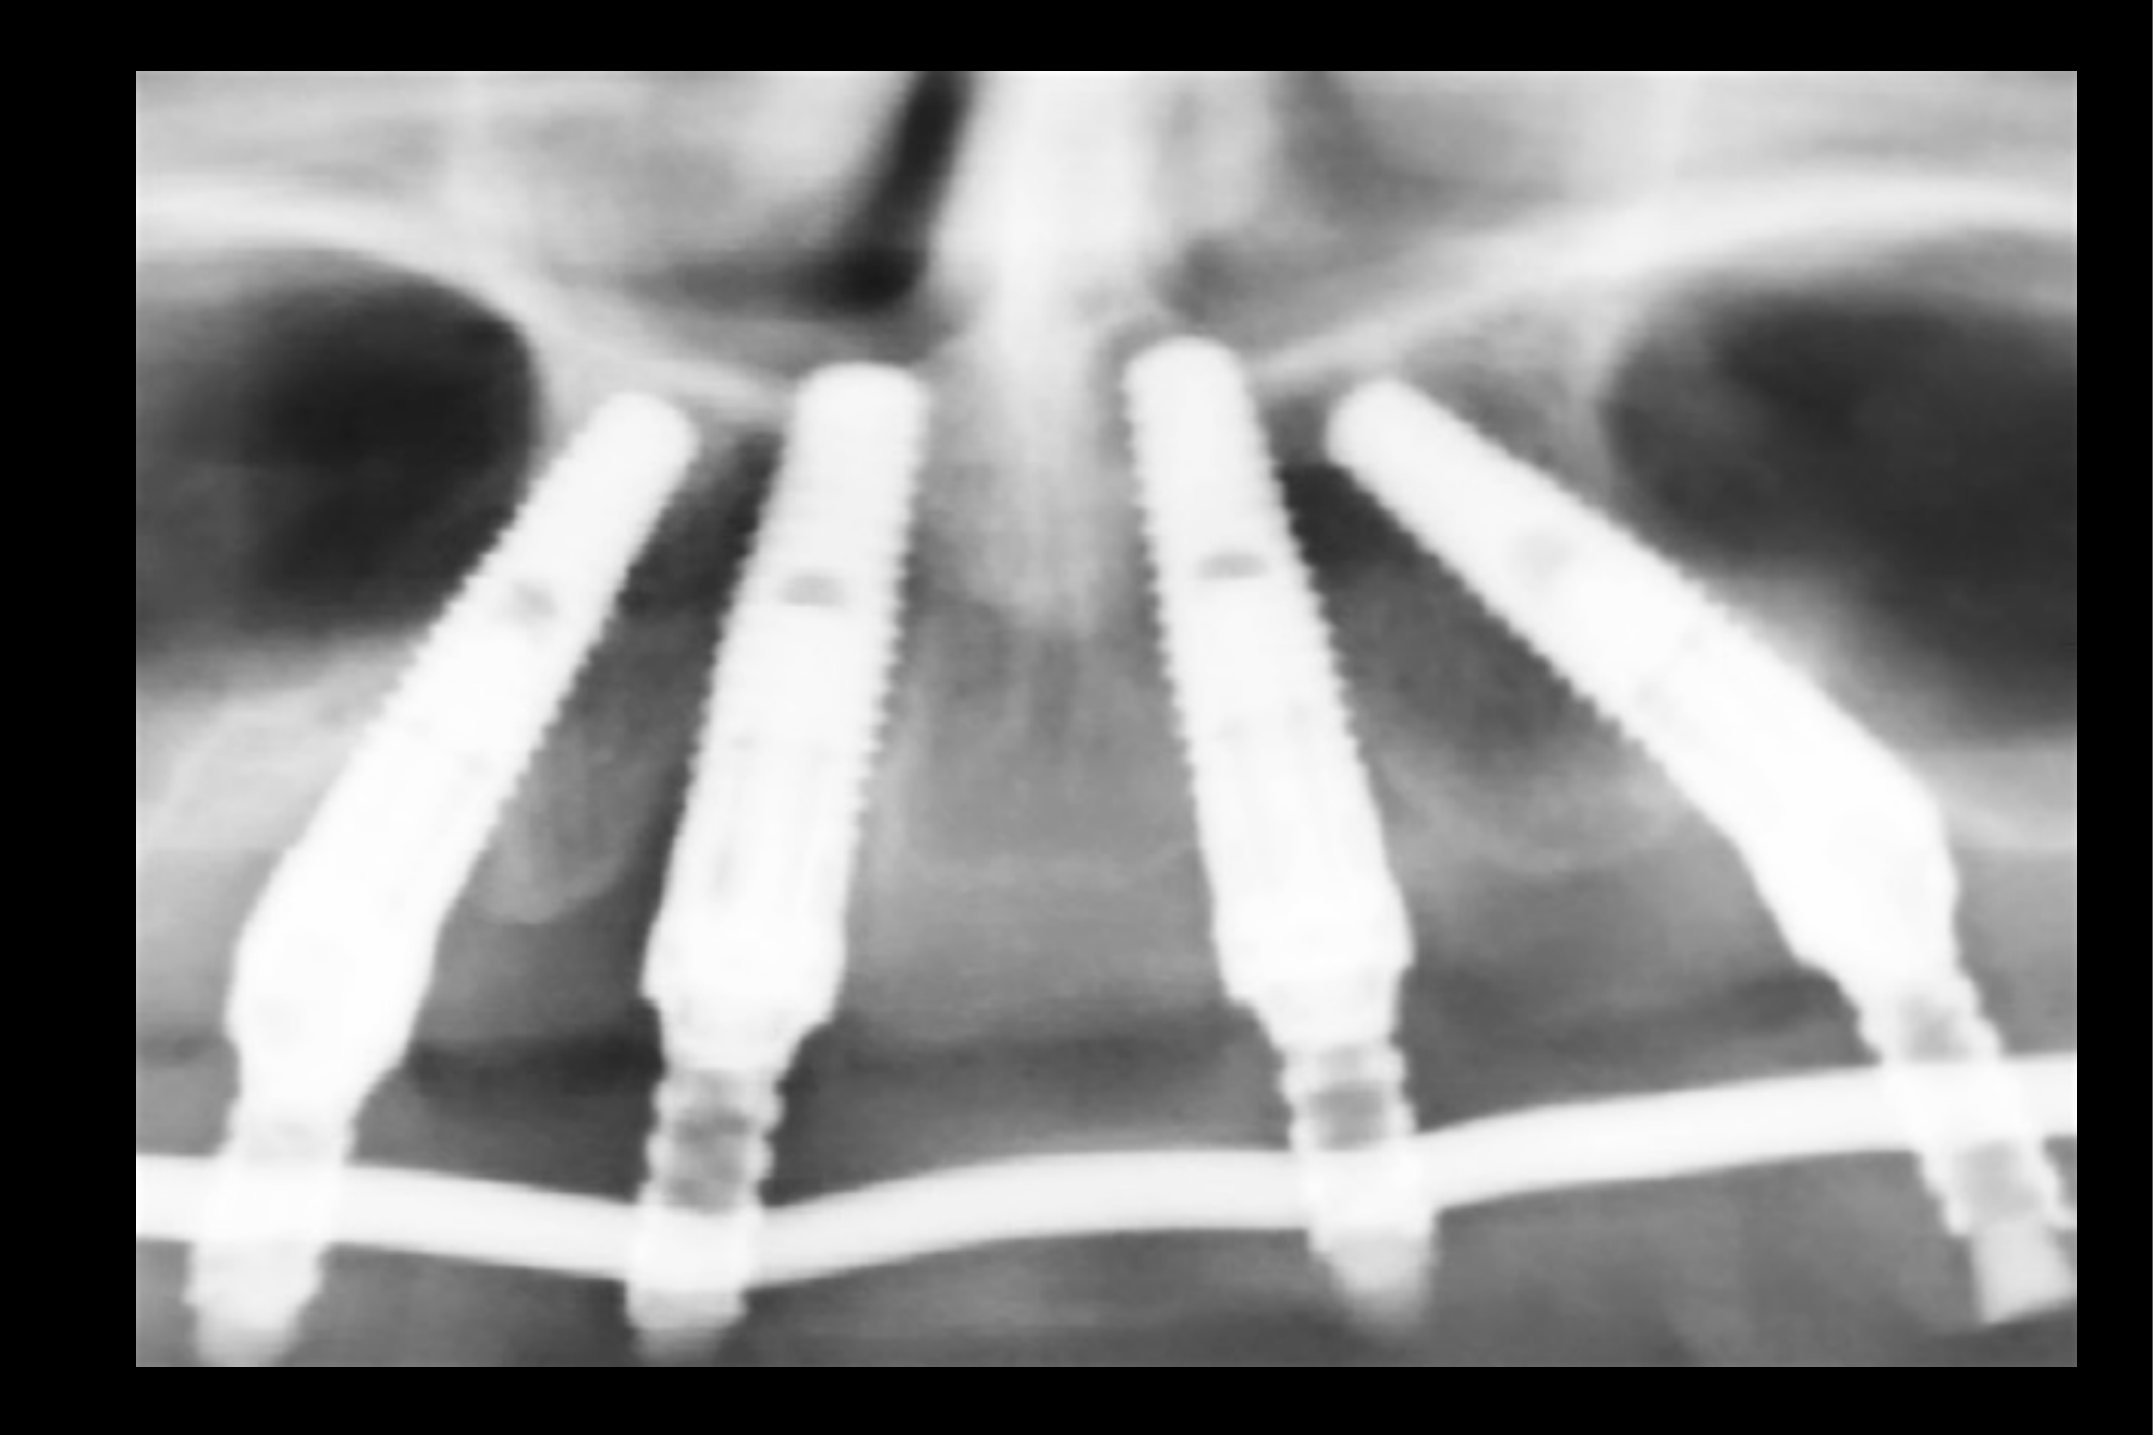
Studies restoring the edentulous maxilla with fixed prostheses using tilted implants without grafting show:
- No significant difference in failure rate or marginal bone levels between axial and tilted implants.
Menini M, Signori A, Tealdo T, Bevilacqua M, Pera F, Ravera G, Pera P. Tilted implants in the immediate loading rehabilitation of the maxilla: a systematic review. J Dent Res. 2012;91(9):821-7.
Del Fabbro M, Bellini CM, Romeo D, Francetti L. Tilted Implants for the Rehabilitation of Edentulous Jaws: A Systematic Review. Clin Implant Dent Relat Res. 2011
Patzelt, Bahat, Reynolds, Strub. The All-on-Four Treatment Concept: A Systematic Review. CIDRR 2014 16;6
Parel SM, Phillips WR. A risk assessment treatment planning protocol for the four implant immediately loaded maxilla: preliminary findings. J Prosthet Dent. 2011;106(6):359-66.
Maló P, Araújo Nobre MD, Lopes A, Rodrigues R. Double Full-Arch Versus Single Full-Arch, Four Implant-Supported Rehabilitations: A Retrospective, 5-Year Cohort Study. J Prosthodont. 2015;24(4):263-70.
Clinical Advantages40
- Allows for placement of longer implants → immediate loading
- Allows for improved anchorage in dense bone
- Allows for further distal extensions
- Does not have a negative effect on load distribution
- Relatively easier surgery compared to sinus lifting
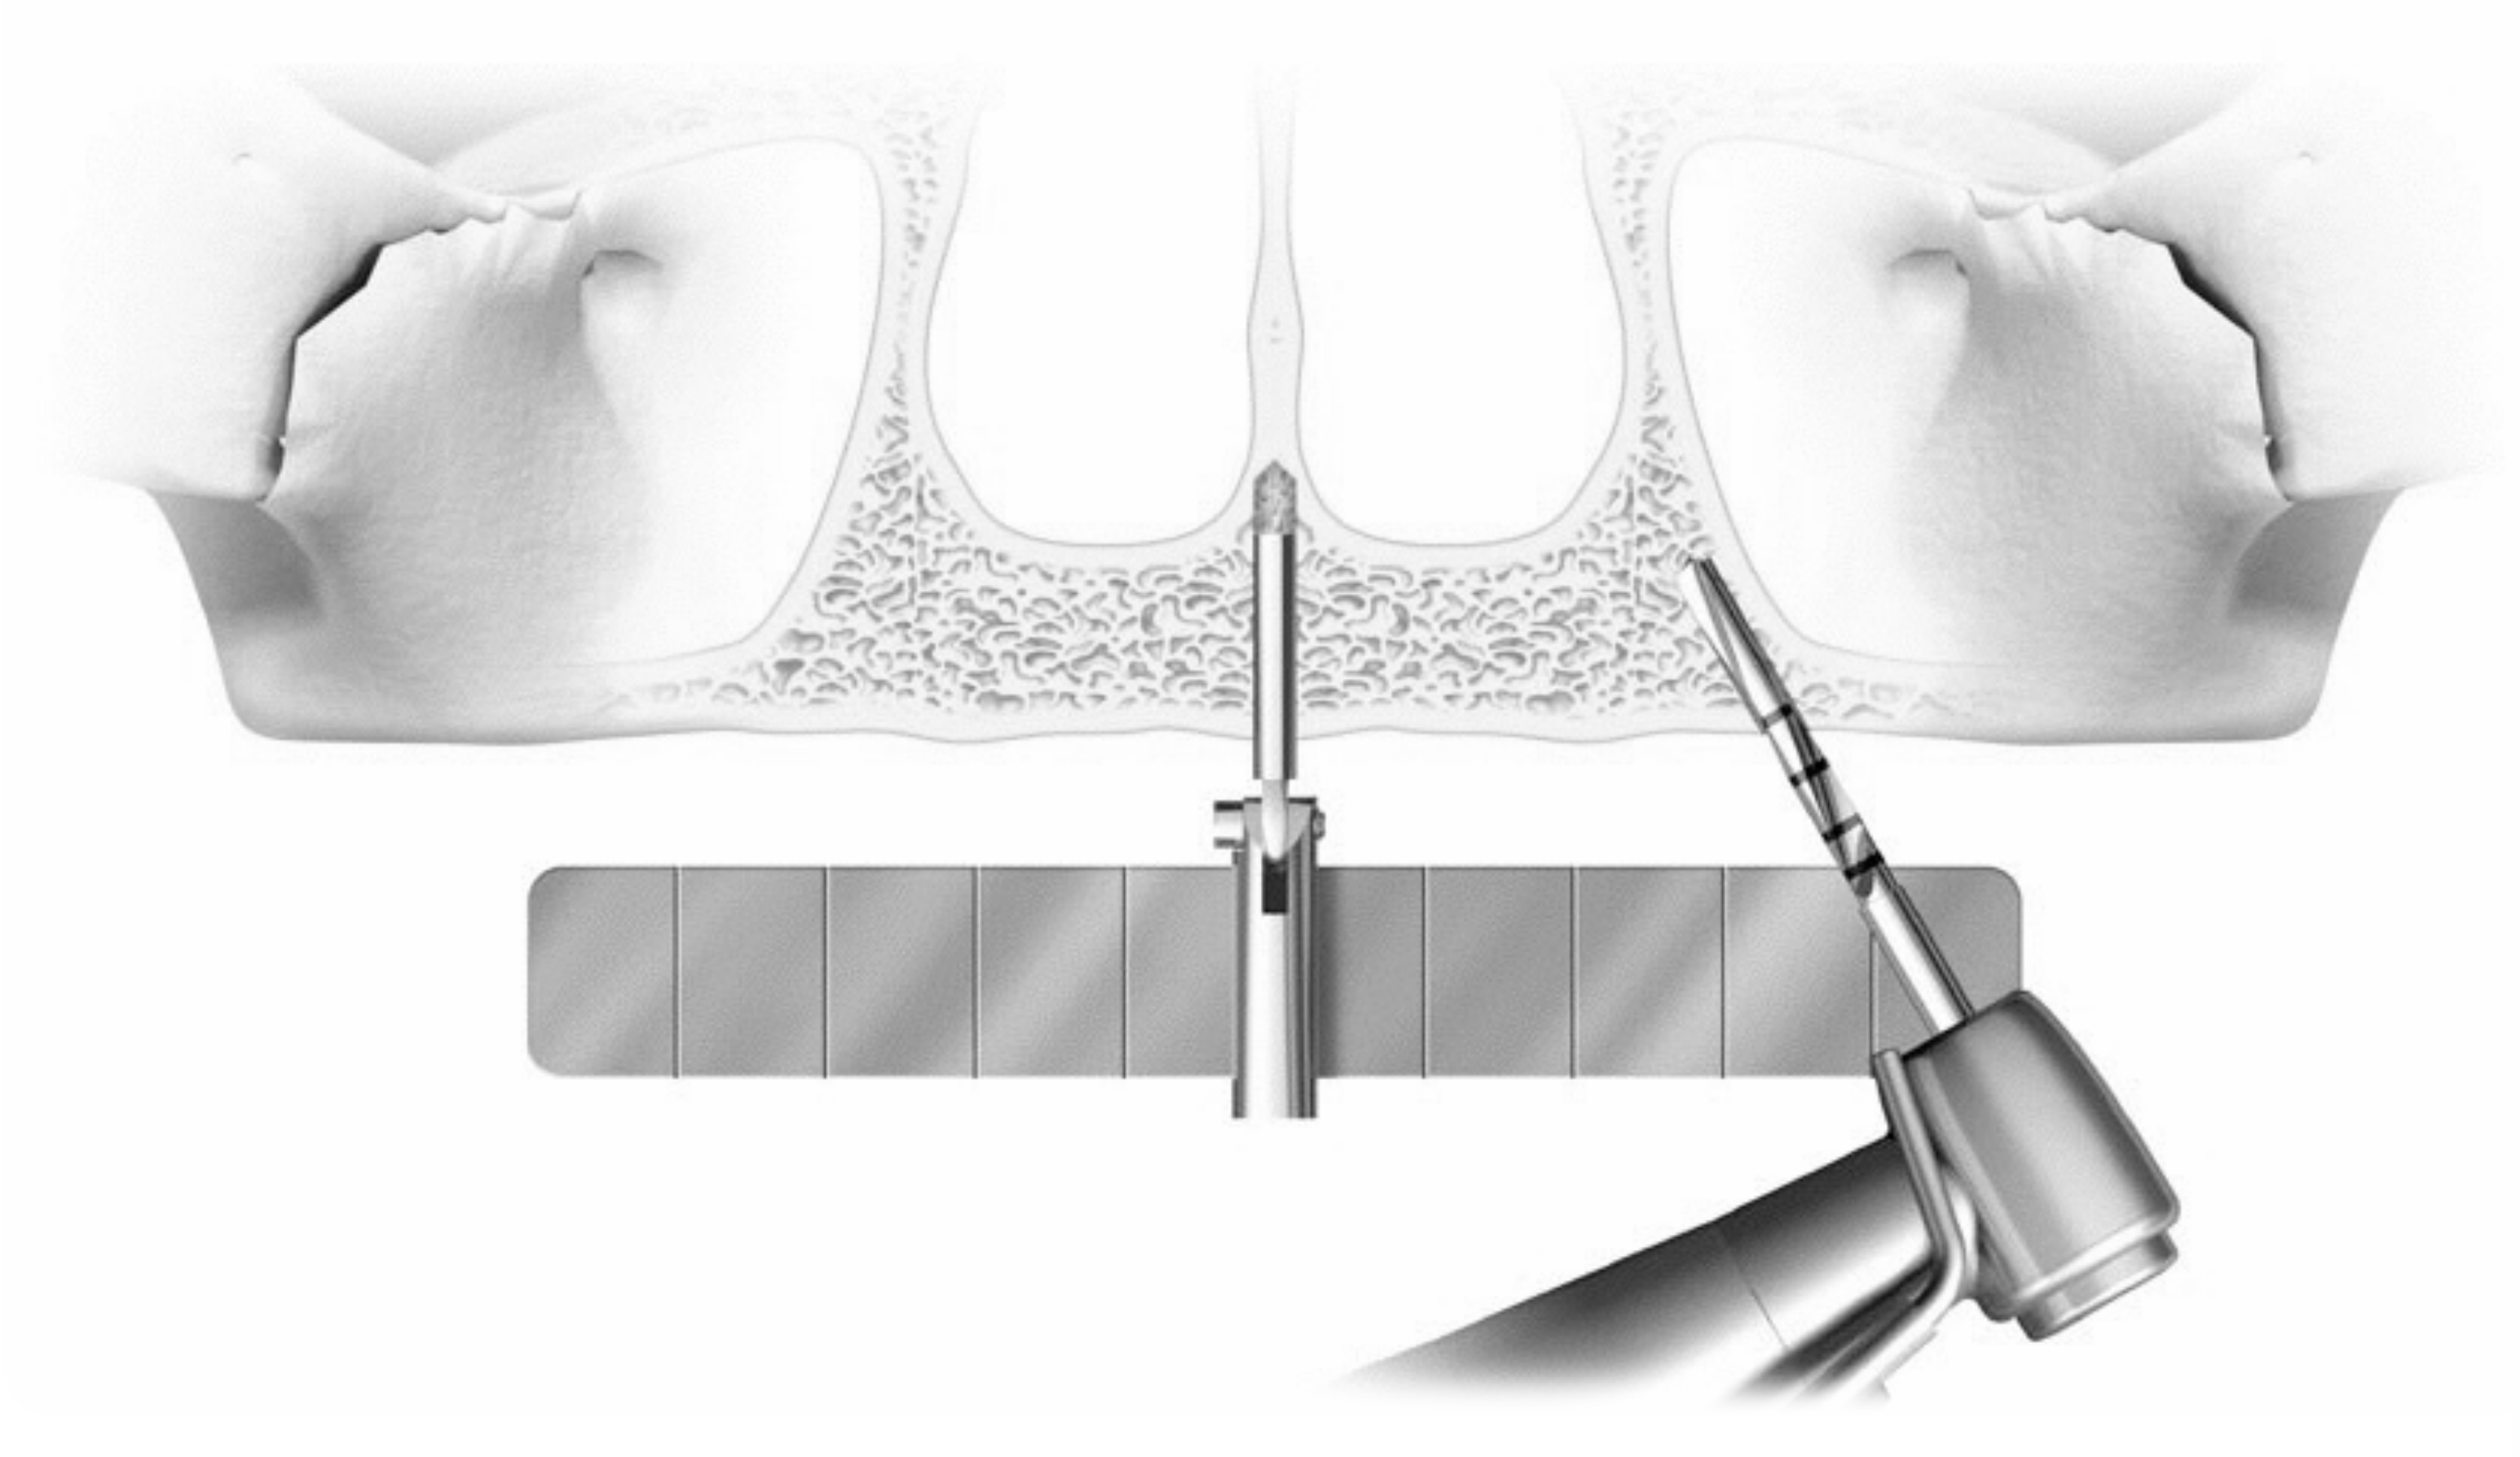
All-on-4 Outcomes41424344
- 20 maxillae, 18–42 months prospective single-cohort immediate loading
- Implant survival: 100%
- Marginal bone loss: 0.8 ± 0.4 mm axial, 0.9 ± 0.5 mm tilted
- No statistically significant difference in axial vs. tilted implants
Agliardi E, Panigatti S, Clericò M, Villa C, Malò P. Immediate rehabilitation of the edentulous jaws with full fixed prostheses supported by four implants: interim results of a single cohort prospective study. Clin Oral Implants Res. 2010 May; 21(5):459–65.
- 61 maxillae, 1–5 years prospective single-cohort immediate loading
- Implant survival: 98.36%
- Marginal bone loss: 0.9 ± 0.7 mm
- No difference in axial vs. tilted implants
Agliardi EL, Francetti L, Romeo D, Del Fabbro M. Immediate rehabilitation of the edentulous maxilla: preliminary results of a single-cohort prospective study. Int J Oral Maxillofac Implants. 2009 Sep-Oct;24(5):887-95.
 |  |
Systematic Review Findings45
- 13 papers
- 4,804 implants, 1,201 prostheses loaded within 48 hours
- 99% implant success at 3 years
- 99.9% prosthesis success at 3 years
- Marginal bone loss: 1.3 ± 0.4 mm at 3 years
- No significant difference between axial and tilted implants
- Most failures occurred with smokers and patients on bisphosphonate medication
- Short-term results
S. B. M. Patzelt, O Bahat, BDS, M. A. Reynolds, J. R. Strub, The All-on-Four Treatment Concept: A Systematic Review. Clin Oral Impl Res 2013
All-on-6 Outcomes4647
- 41 maxillae, mean 22-month follow-up, prospective multicenter immediate loading
- 4 axial implants, 2 tilted
- Implant survival: 98.8%
- Marginal bone loss: 0.9 ± 0.4 mm axial, 0.8 ± 0.5 mm tilted
- No difference in axial vs. tilted implants
- Prosthesis success rate: 100%
Testori T, Del Fabbro M, Capelli M, Zuffetti F, Francetti L, Weinstein RL. Immediate occlusal loading and tilted implants for the rehabilitation of the atrophic edentulous maxilla: 1-year interim results of a multicenter prospective study. Clin Oral Implants Res. 2008 Mar;19(3):227-32.
- 19 patients with 4 or 6 implants, tilted distal implants
- 8–12 year follow-up (mean 10 years; pre-All-on-4)
- Implant success: 97%
- Marginal bone loss: 1.2 mm
- No difference in axial vs. tilted implants
Rosén A, Gynther G. Implant treatment without bone grafting in edentulous severely resorbed maxillas: a long-term follow-up study. J Oral Maxillofac Surg. 2007 May;65(5):1010–6.
Implant Failure and Risk Factors
Causes of Implant Failure
Multifactorial Reasons for Bone Loss48
- Cause / effect / association
- Early failure
- Late failure
- Peri-implantitis model
- Patient-related factors
- Due to inadequate healing initially (lower bone-to-implant contact [BIC] and degree of sustainable osseosufficiency)
Koka S, Zarb G. On osseointegration: The healing adaptation principle in the context of osseosufficiency, osseoseparation and dental implant failure. Int J Pros 2012;25:48-52. Zarb G. Implantomania: Prosthodontics at a crossroads. Int J Pros 2012;25:180-185. Albrektsson T, Buser D, Sennerby L. On crestral/marginal bone loss around dental implants. Int J Pros 2012;25:320-322.
Members: T Albrektsson, D Buser, S Chen, D Cochran, H De Bruyn, T Jemt, S Koka, M Nevins, L Sennerby, M Simion, T Taylor, A Wennerberg.
Patient Risk Factors
Patient Risk Stratification49
| Primary Factors | Secondary Factors |
|---|---|
| - Opposing natural dentition - Poor bone density - Bruxer - Male | - Smoker - Bone volume |
Patzelt, Bahat, Reynolds, Strub. The All-on-Four Treatment Concept: A Systematic Review. CIDRR 2014 16;6. Parel SM, Phillips WR. A risk assessment treatment planning protocol for the four implant immediately loaded maxilla: preliminary findings. J Prosthet Dent. 2011;106(6): 359-66.
Implant Stability Over Time
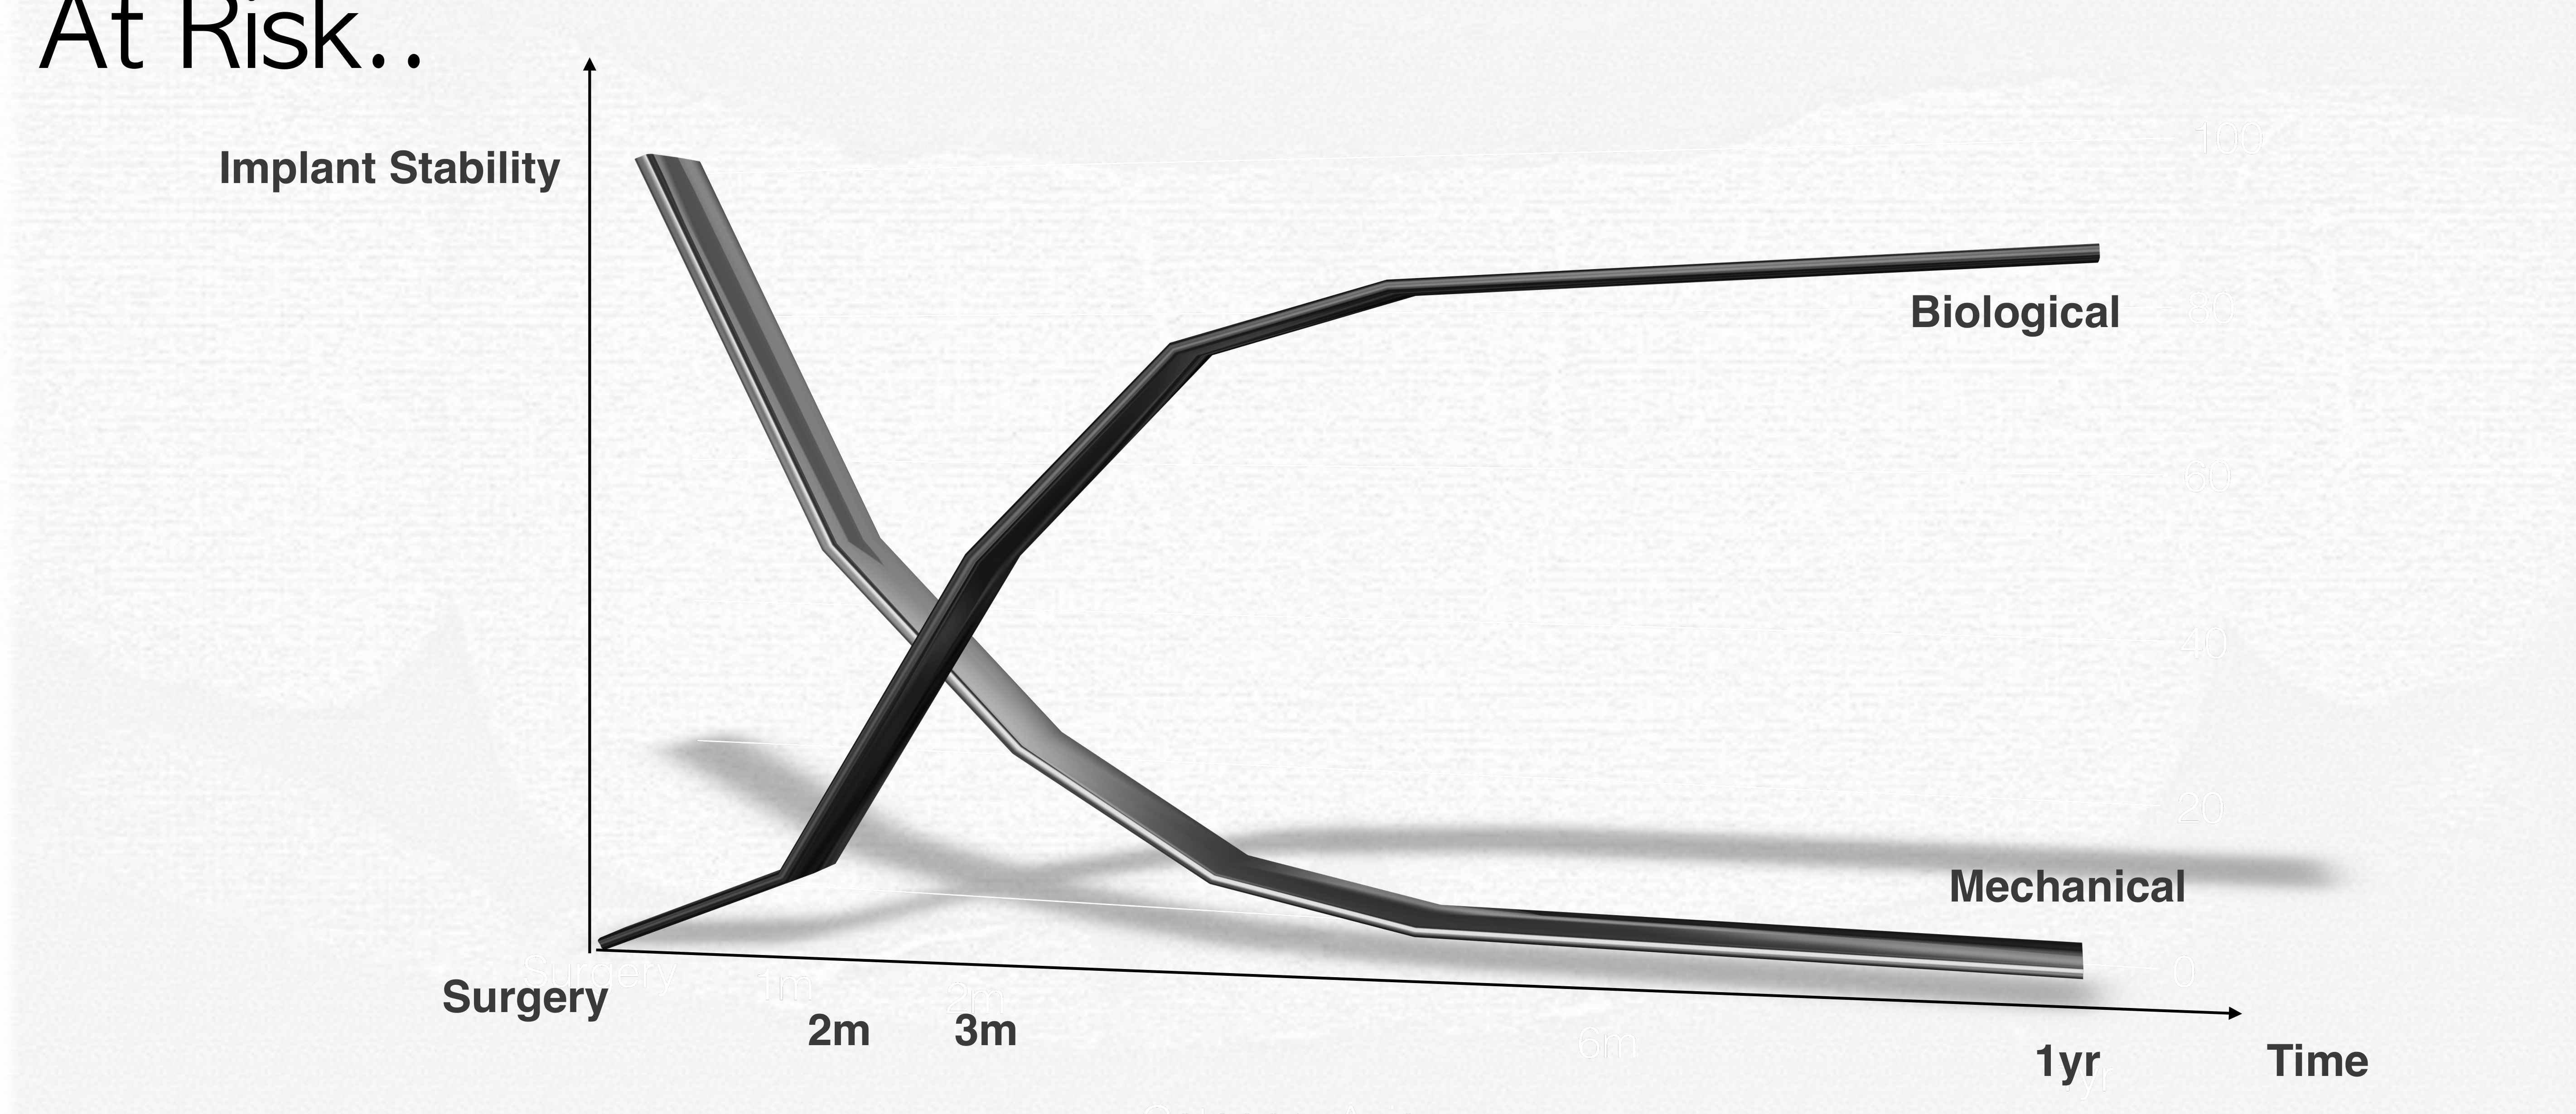
74% of failures occurred within 12 months of placement.
Failure Modes Over Time50
- Mechanical stability
- Biological stability
Timeline milestones: Surgery → 2 months → 3 months → 1 year
Patzelt, Bahat, Reynolds, Strub. The All-on-Four Treatment Concept: A Systematic Review. CIDRR 2014 16;6. Parel SM, Phillips WR. A risk assessment treatment planning protocol for the four implant immediately loaded maxilla: preliminary findings. J Prosthet Dent. 2011; 106(6): 359-66.
Maxillary Bone Considerations51
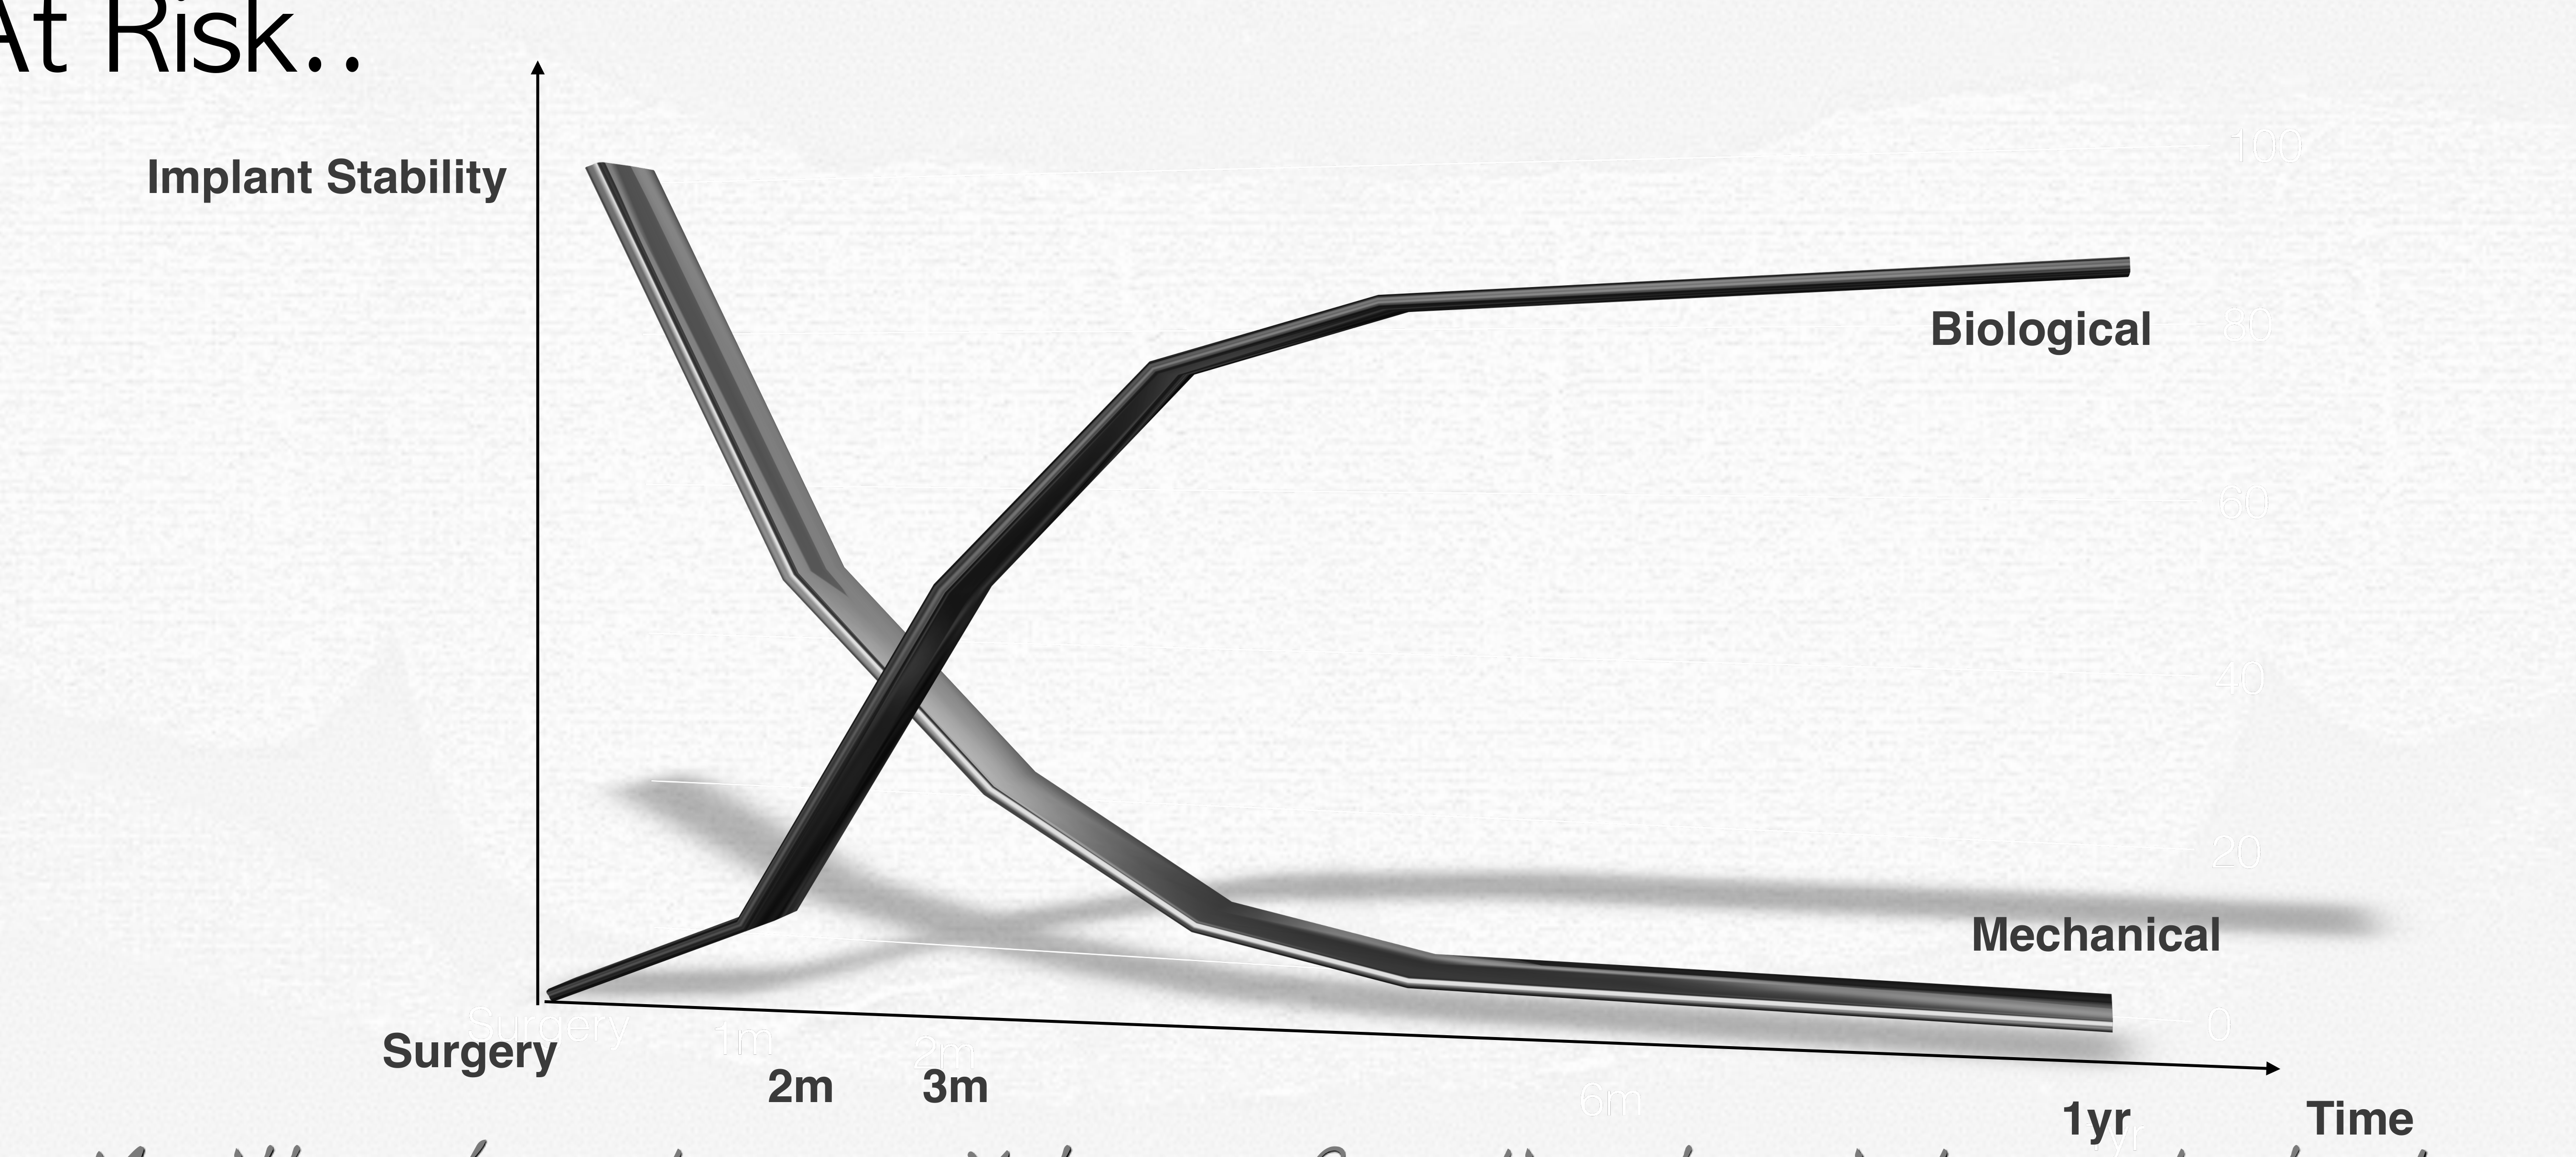
- Timeline / mechanical transition: Surgery → 2 months → 3 months → 1 year
- Maxillary bone demonstrates 3–4× lower functional resistance to load; implants are not as stable compared to mandibular bone.
Patzelt, Bahat, Reynolds, Strub. The All-on-Four Treatment Concept: A Systematic Review. CIDRR 2014 16; 6. Parel SM, Phillips WR. A risk assessment treatment planning protocol for the four implant immediately loaded maxilla: preliminary findings. J Prosthet Dent. 2011; 106(6): 359-66.
Factors Contributing to Failure in Immediately Loaded Maxillae52
- Depending on loading, four implants may be insufficient for complete stability, resulting in lower bone-to-implant contact (BIC) and greater susceptibility to integration breakdown, opportunistic infection, and bone loss.
- Risk is exacerbated by patient factors such as smoking, diabetes, IL-1 phenotype, history of periodontitis, and autoimmune disease.
- The All-on-4 concept may not be appropriate for larger arch forms and greater functional loads.
Chung S, McCullagh A, Irinakas T. Immediate loading in the maxillary arch: evidence-based guidelines to improve success rates: A review. J Oral Implantol. 2011;37:610-21.
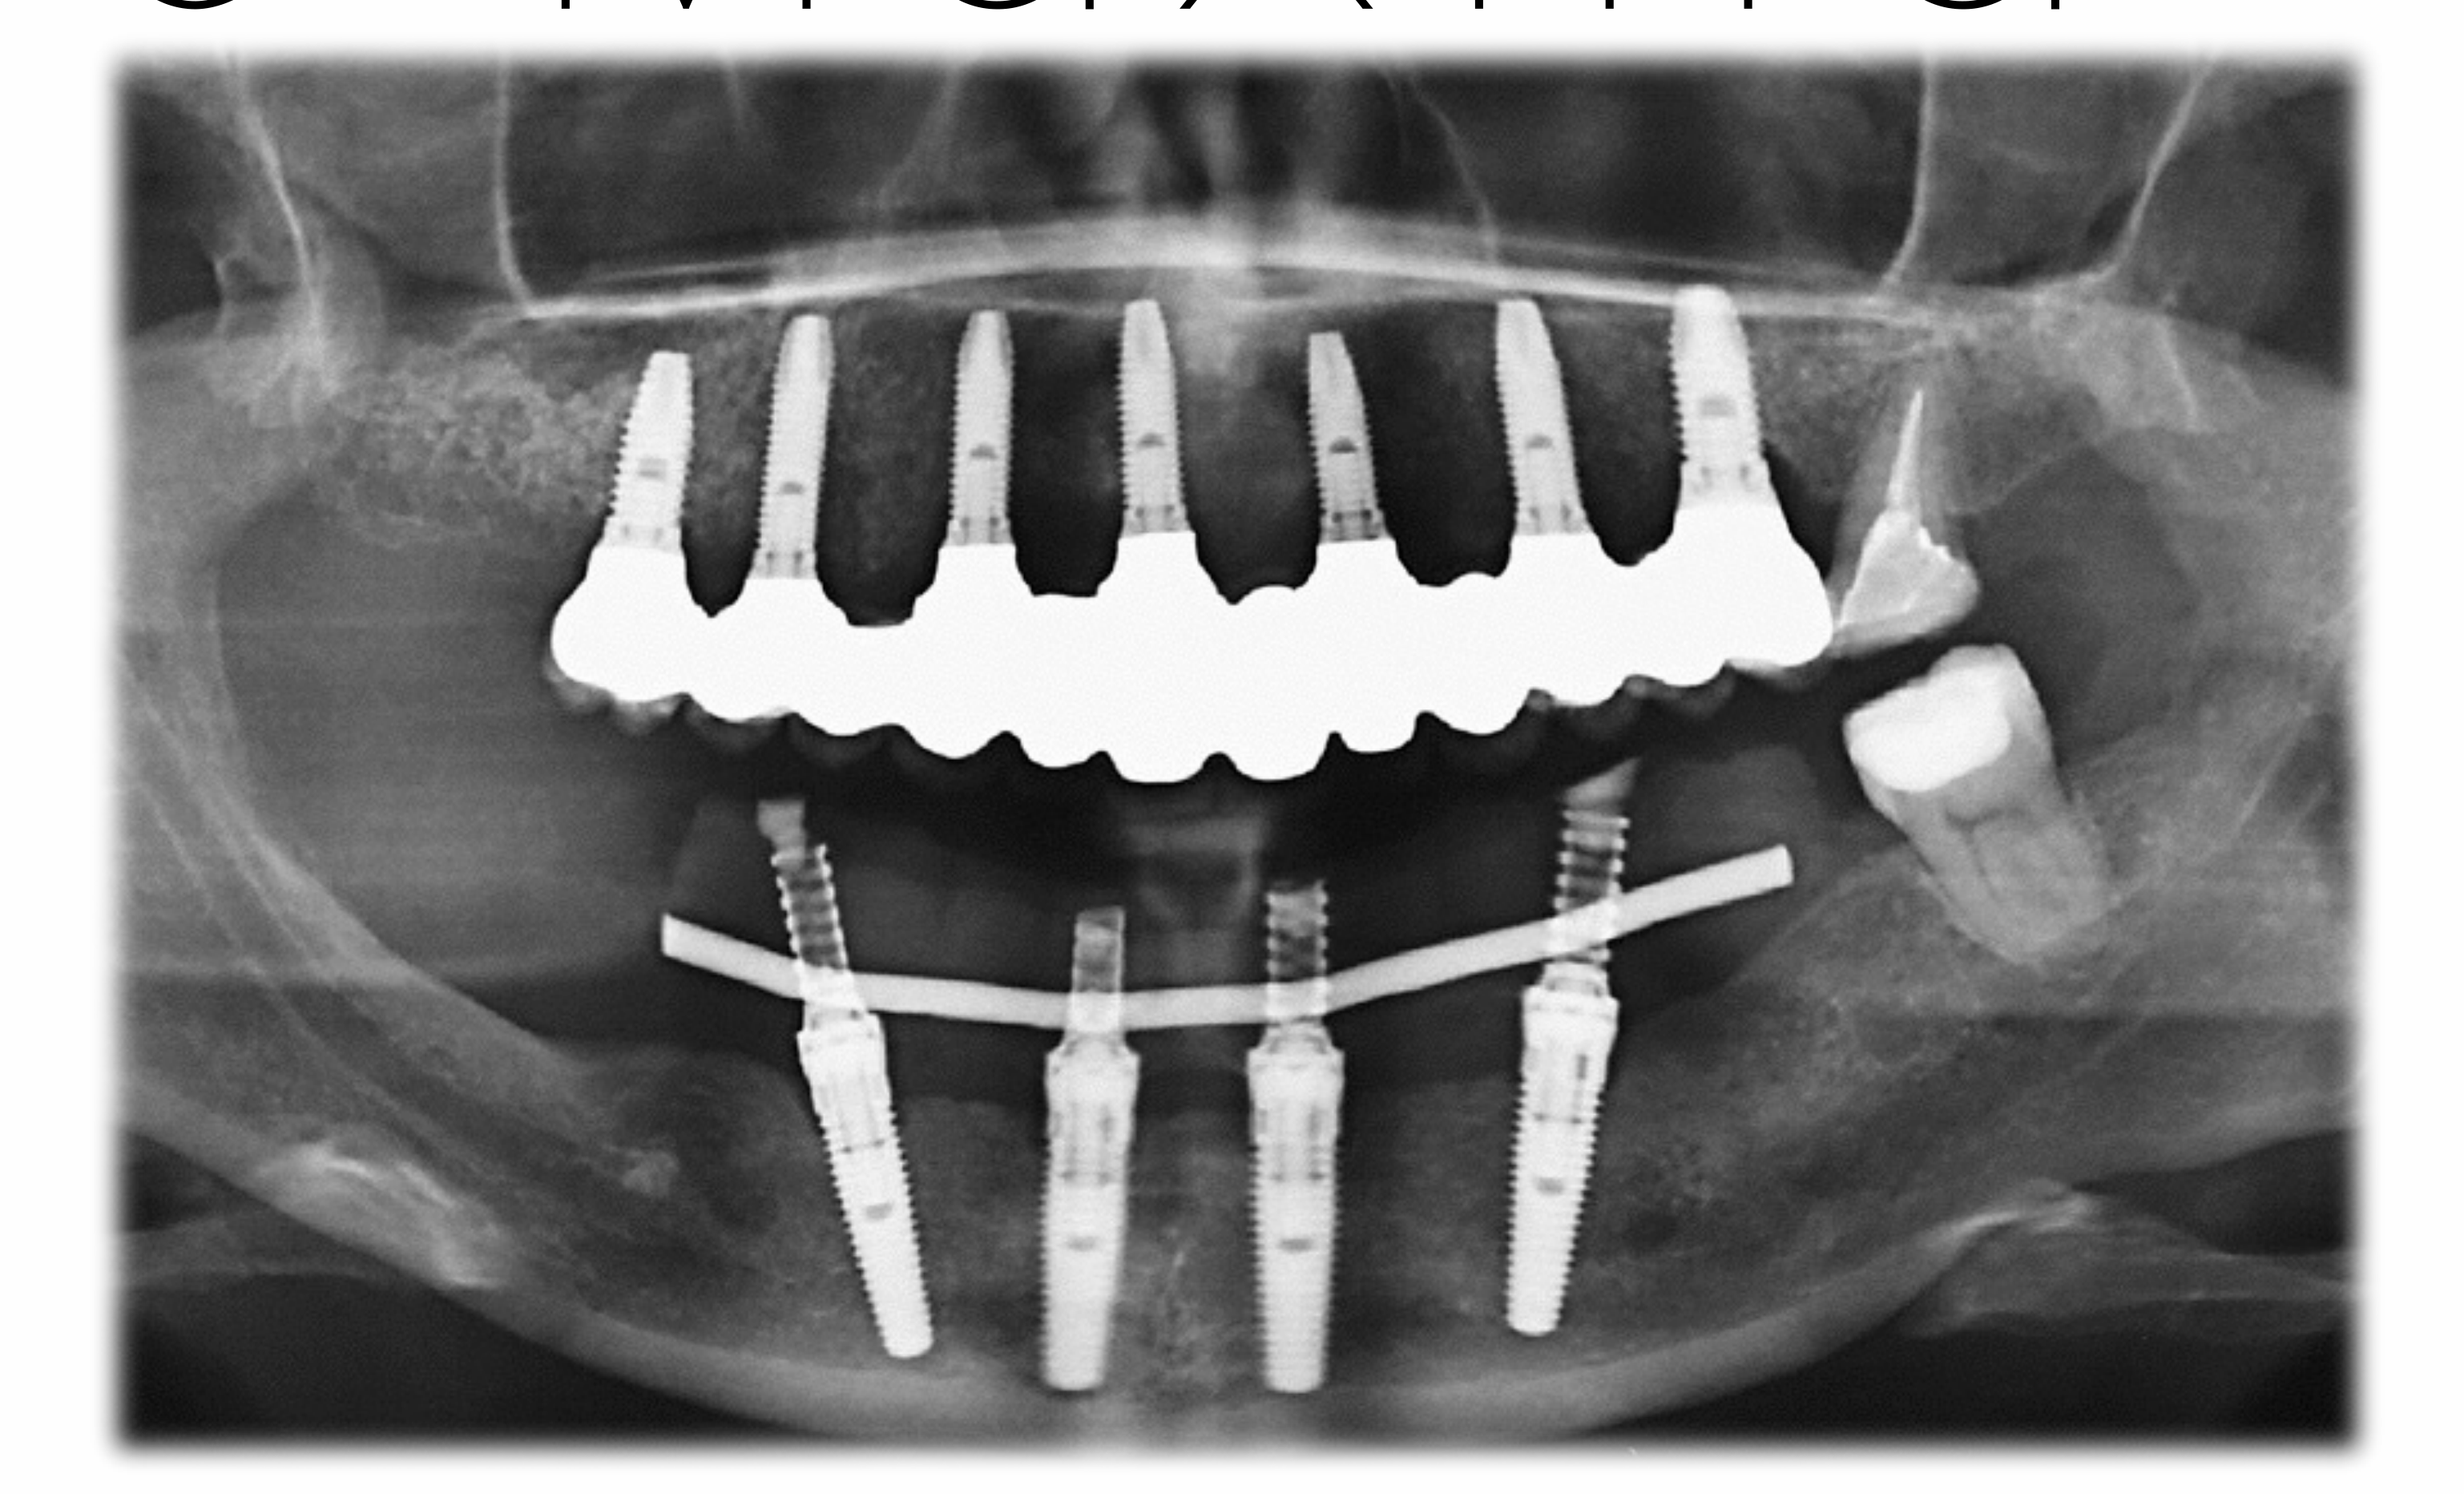
Management of the Atrophic Maxilla With Augmentation53
Augmentation
Iliac Crest Grafting54
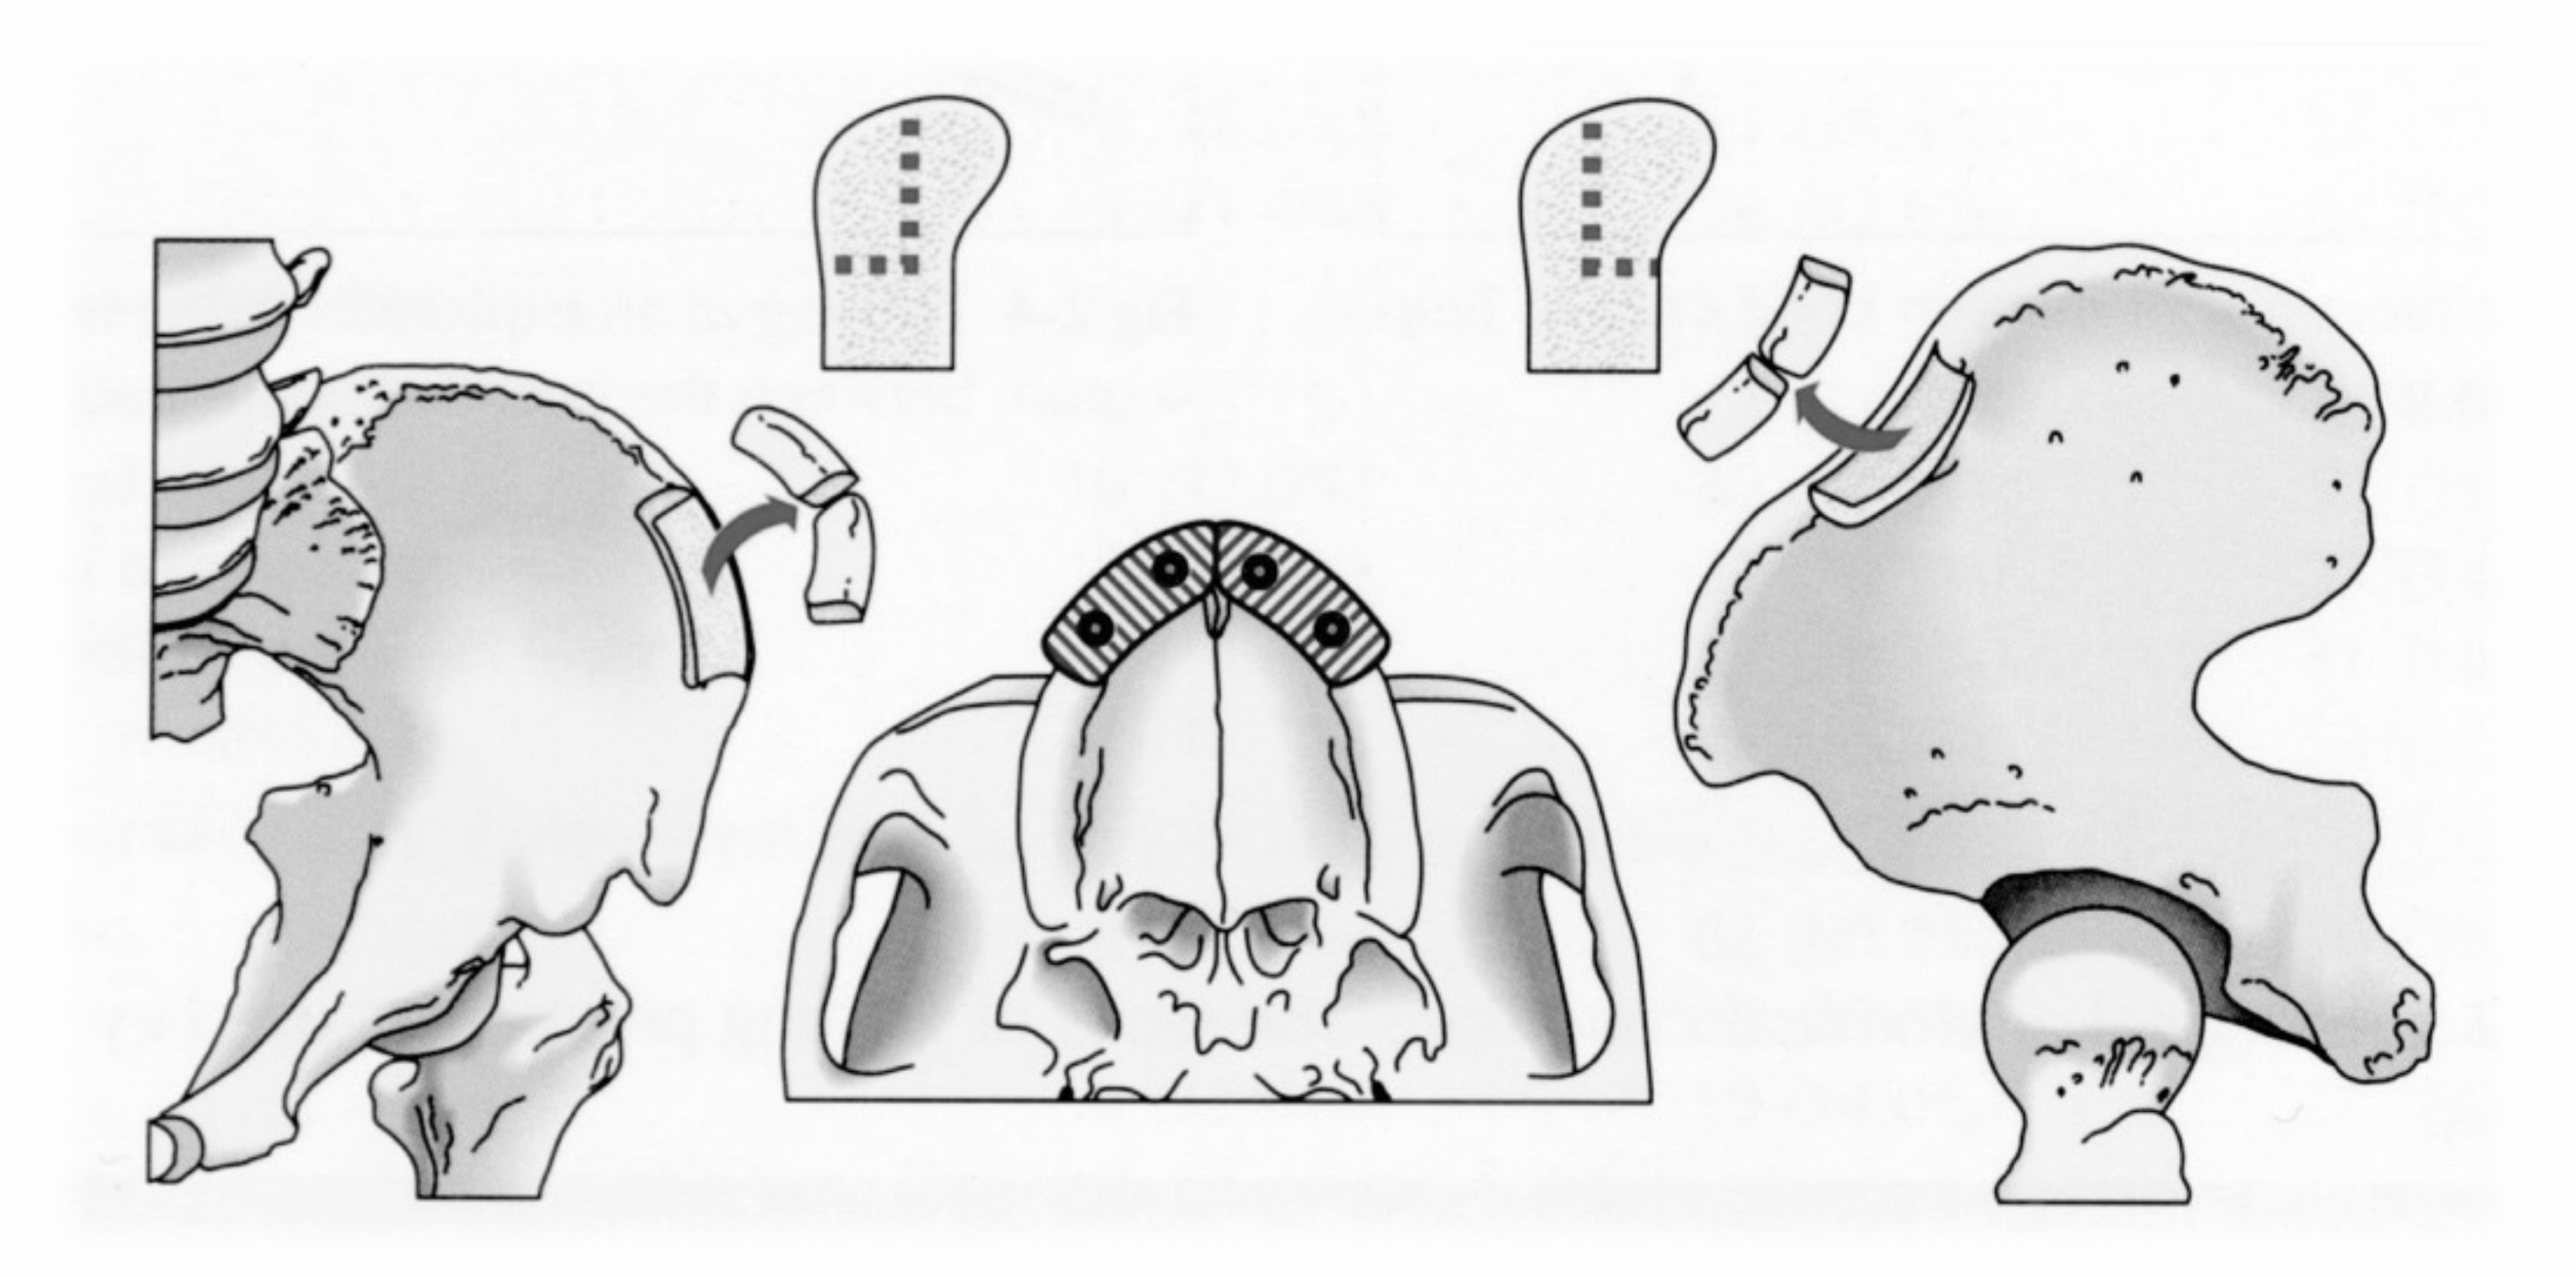 | 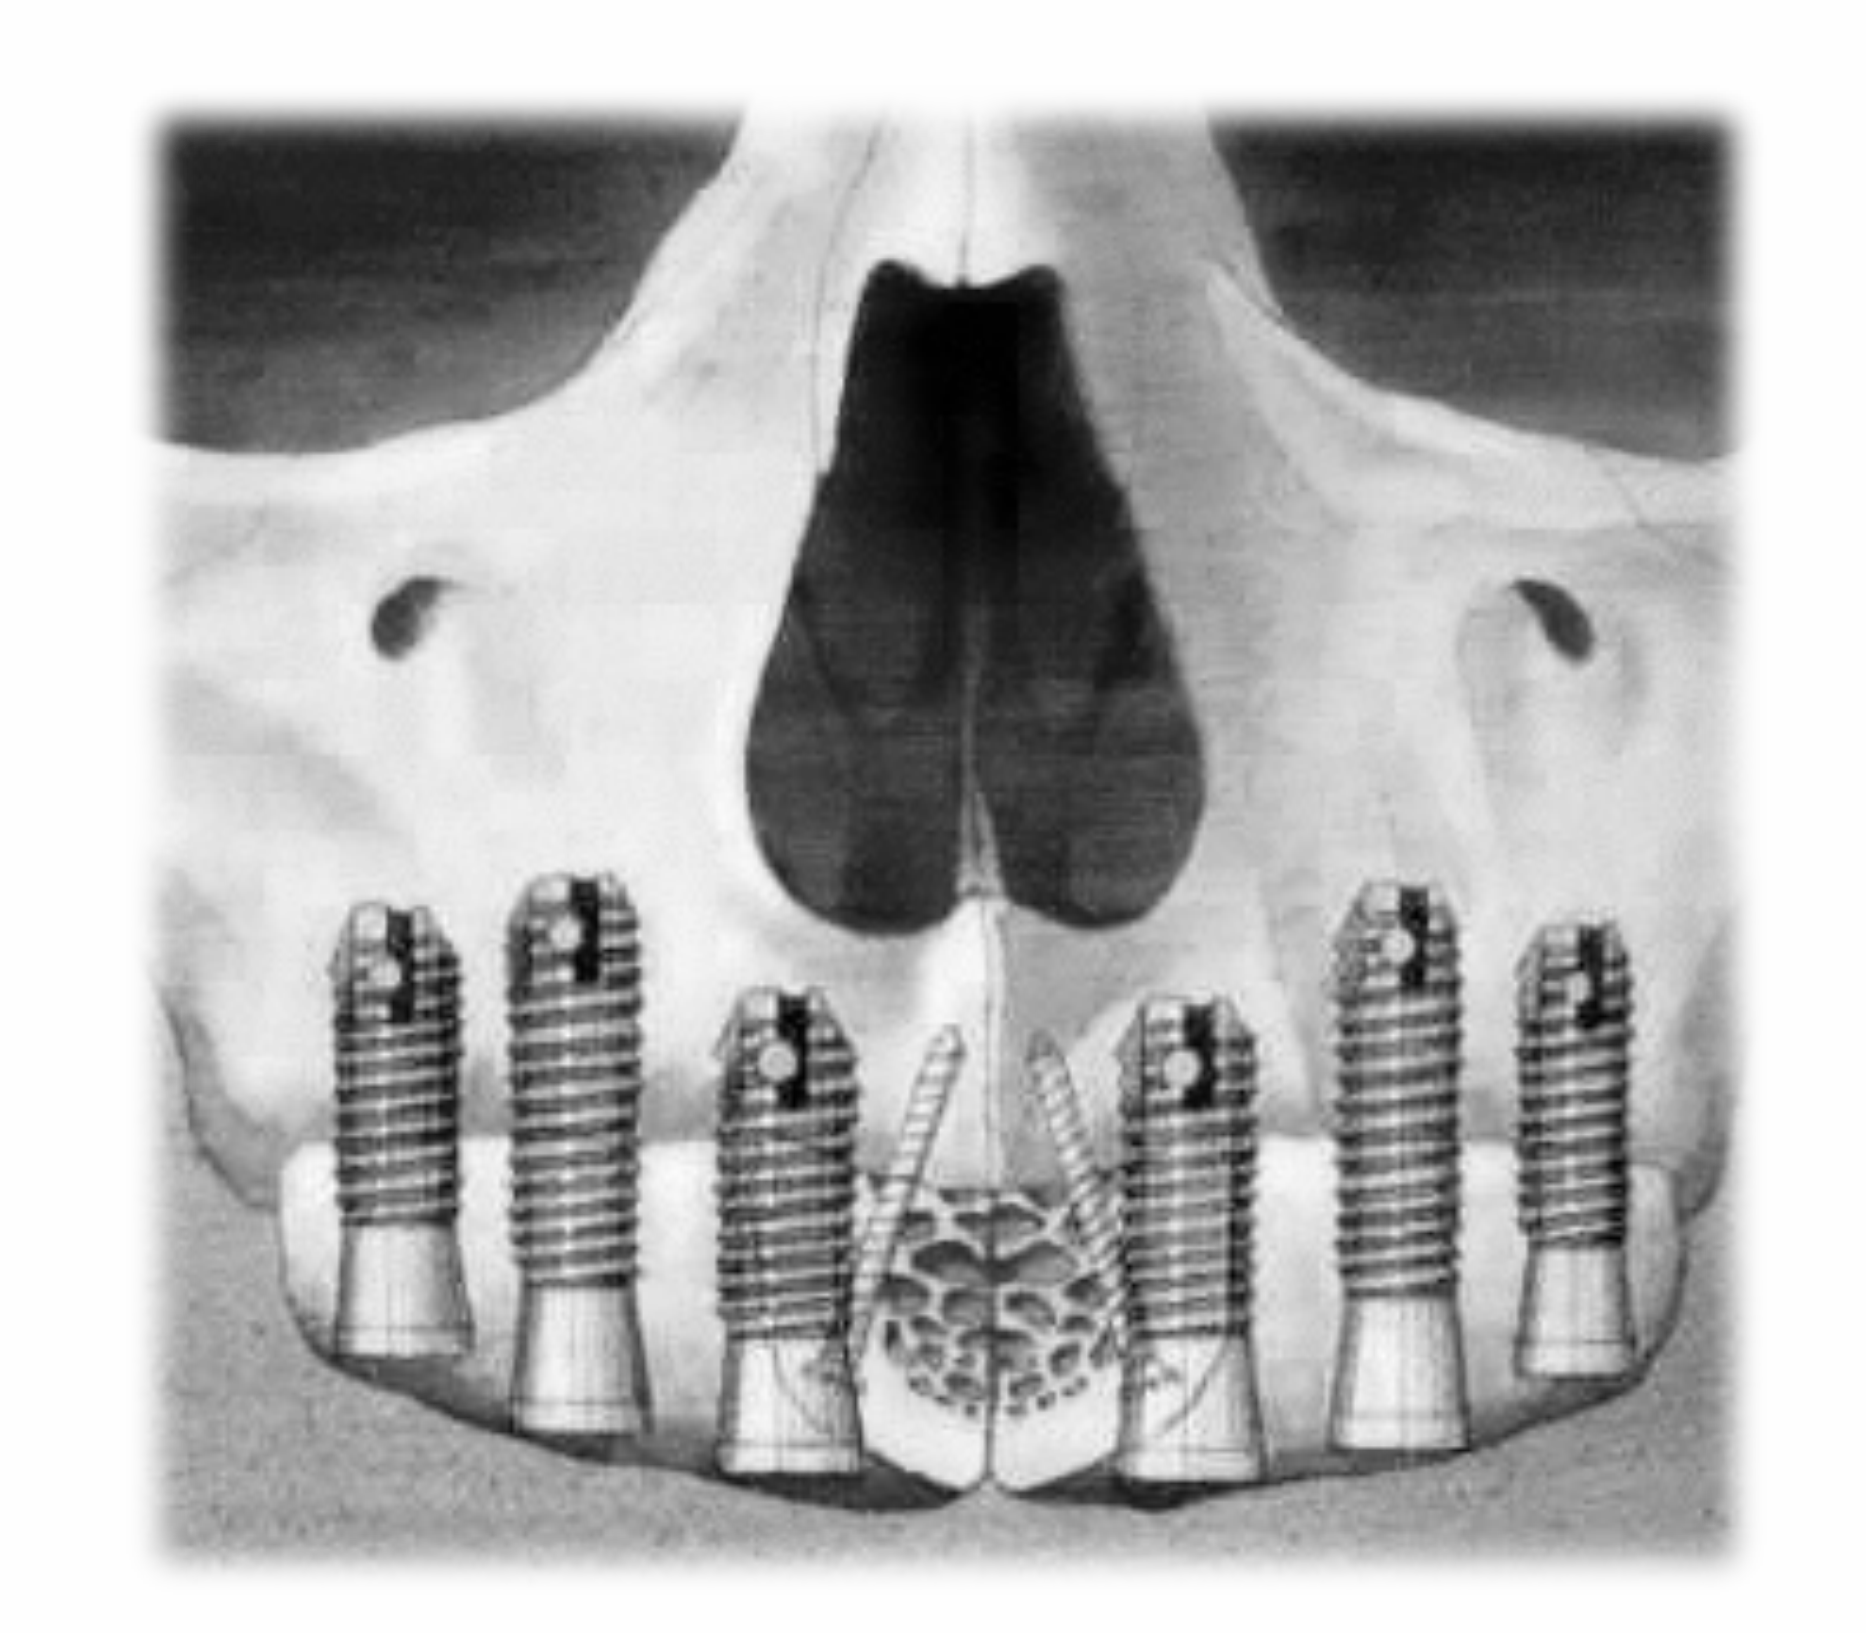 |
Maxillary Bone Graft Considerations55
- Donor site
- Recipient site preparation
- Fixation
- Implant installation: delayed vs. immediate
- Post-graft radiological requirements
- Complications
Minimum 1-year treatment plan
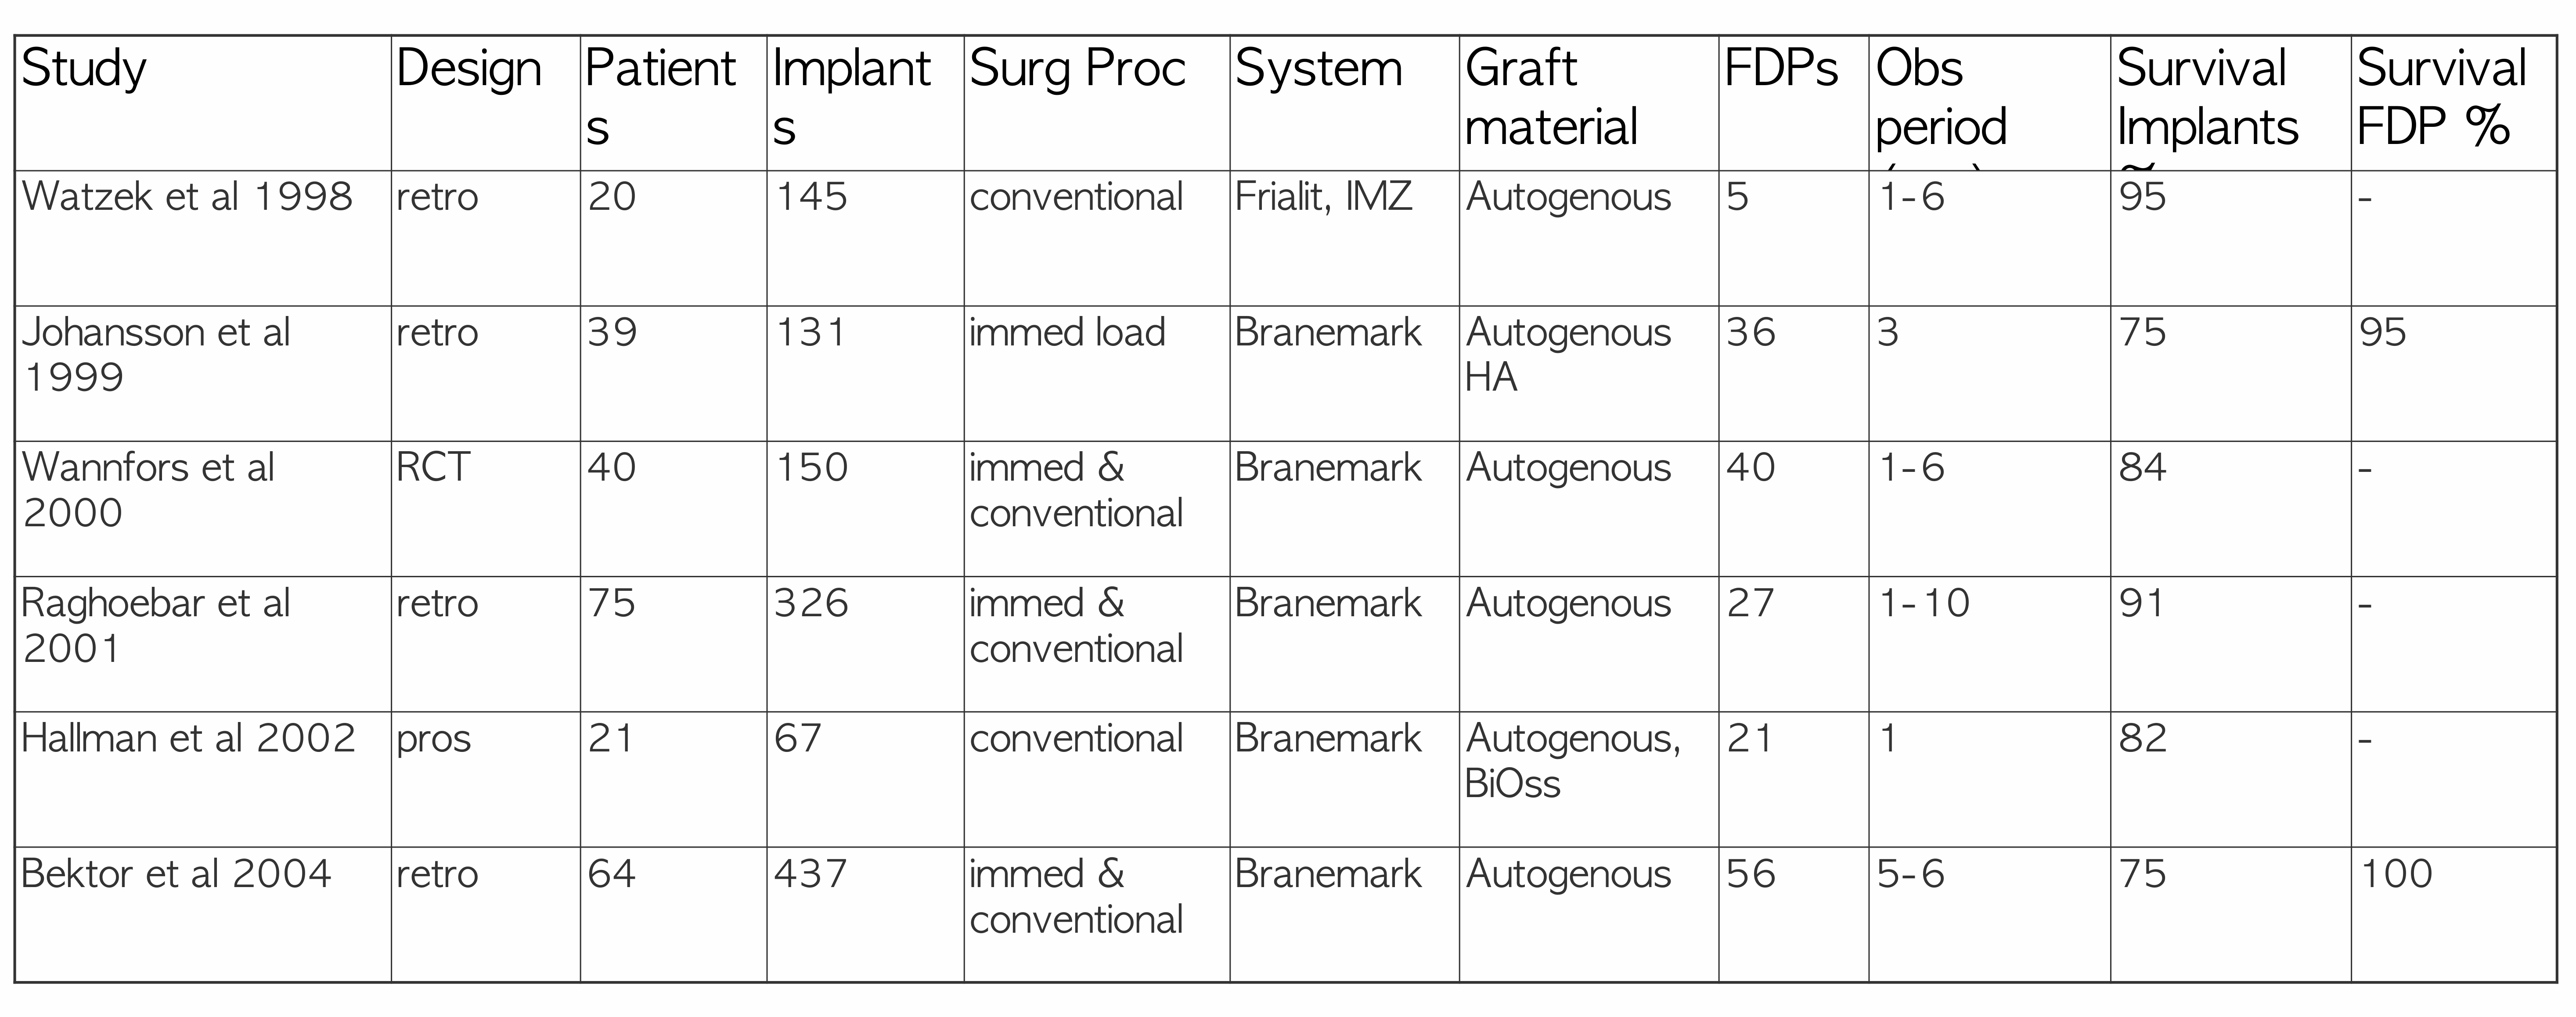
Sinus Lift Lateral Window Outcomes56
| Study | Design | Patients | Implants | Surg Proc | System | Graft material | FDPs | Obs period | Survival Implants (%) | Survival FDP (%) |
|---|---|---|---|---|---|---|---|---|---|---|
| Watzek et al. 1998 | retro | 20 | 145 | conventional | Frialit, IMZ | Autogenous | 5 | 1–6 | ~95 | — |
| Johansson et al. 1999 | retro | 39 | 131 | immed load | Brånemark | Autogenous HA | 36 | 3 | 75 | 95 |
| Wannfors et al. 2000 | RCT | 40 | 150 | immed & conventional | Brånemark | Autogenous | 40 | 1–6 | 84 | — |
| Raghoobar et al. 2001 | retro | 75 | 326 | immed & conventional | Brånemark | Autogenous | 27 | 1–10 | 91 | — |
| Hallman et al. 2002 | pros | 21 | 67 | conventional | Brånemark | Autogenous, Bio-Oss | 21 | 1 | 82 | — |
| Bektor et al. 2004 | retro | 64 | 437 | immed & conventional | Brånemark | Autogenous | 56 | 5–6 | 75 | 100 |
Systematic Review Findings57
- Implant survival more variable in augmented sinuses (36–100%, average ~90%)
- Amount of residual bone height is an important prognostic factor
- No evidence for the superiority of autogenous bone compared to substitutes
- Heterogeneous studies do not allow definitive statements
References
Graziani, F., Donos, N., Needleman, I., Gabriele, M., and Tonetti, M. (2004). Comparison of implant survival following sinus floor augmentation procedures with implants placed in pristine posterior maxillary bone: a systematic review. Clinical Oral Implants Research, 15, 677–682.
Pjetursson, B. E., Tan, W. C., Zwahlen, M., and Lang, N. P. (2008). A systematic review of the success of sinus floor elevation and survival of implants inserted in combination with sinus floor elevation. Journal of Clinical Periodontology, 35(8 Suppl), 216–240.
Nkenke, E., and Stelzle, F. (2009). Clinical outcomes of sinus floor augmentation for implant placement using autogenous bone or bone substitutes: a systematic review. Clinical Oral Implants Research, 20(Suppl 4), 124–133.
Rickert, D., Slater, J. J., Meijer, H. J., Vissink, A., and Raghoobar, G. M. (2012). Maxillary sinus lift with solely autogenous bone compared to a combination of autogenous bone and growth factors or (solely) bone substitutes. A systematic review. International Journal of Oral and Maxillofacial Surgery, 41(2), 160–167.
Zygoma Implants58
Zygoma Implant Outcomes
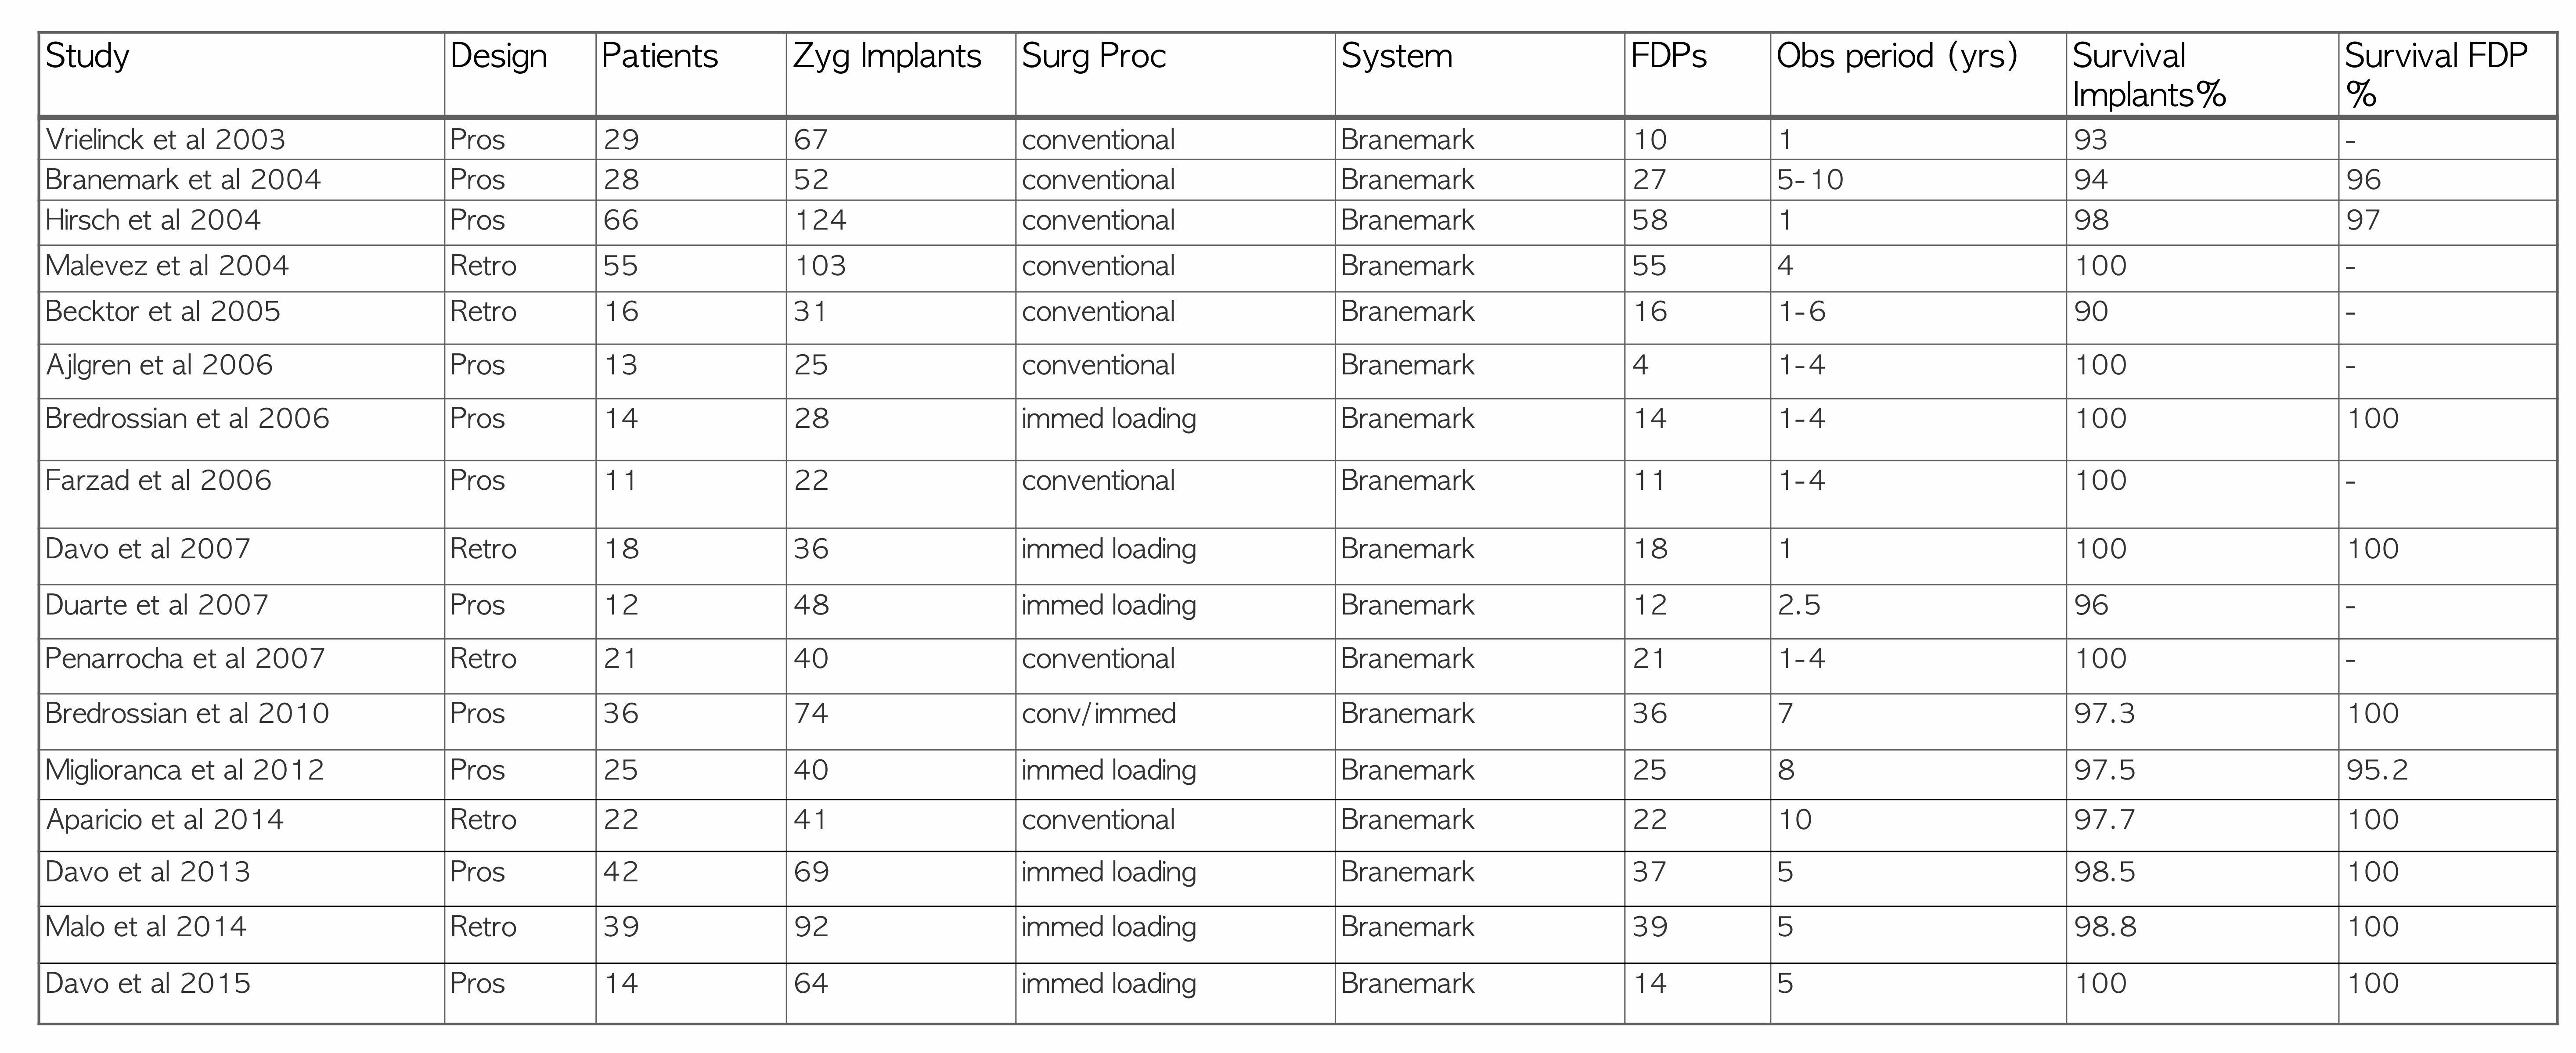
Clinical Studies: Edentulous Maxilla Restored with Fixed Prostheses and Zygomatic Implants59
| Study | Design | Patients | Zyg Implants | Surg Proc | System | FDPs | Obs period (yrs) | Survival Implants% | Survival FDP % |
|---|---|---|---|---|---|---|---|---|---|
| Vrielinck et al 2003 | Pros | 29 | 67 | conventional | Branemark | 10 | 1 | 93 | - |
| Branemark et al 2004 | Pros | 28 | 52 | conventional | Branemark | 27 | 5-10 | 94 | 96 |
| Hirsch et al 2004 | Pros | 66 | 124 | conventional | Branemark | 58 | 1 | 98 | 97 |
| Malevez et al 2004 | Retro | 55 | 103 | conventional | Branemark | 55 | 4 | 100 | - |
| Beccctor et al 2005 | Retro | 16 | 31 | conventional | Branemark | 16 | 1-6 | 90 | - |
| Ajlgren et al 2006 | Pros | 13 | 25 | conventional | Branemark | 4 | 1-4 | 100 | - |
| Bredrossian et al 2006 | Pros | 14 | 28 | immed loading | Branemark | 14 | 1-4 | 100 | 100 |
| Farzad et al 2006 | Pros | 11 | 22 | conventional | Branemark | 11 | 1-4 | 100 | - |
| Davo et al 2007 | Retro | 18 | 36 | immed loading | Branemark | 18 | 1 | 100 | 100 |
| Duarte et al 2007 | Pros | 12 | 48 | immed loading | Branemark | 12 | 2.5 | 96 | - |
| Penarrocha et al 2007 | Retro | 21 | 40 | conventional | Branemark | 21 | 1-4 | 100 | - |
| Bredrossian et al 2010 | Pros | 36 | 74 | conv/immed | Branemark | 36 | 7 | 97.3 | 100 |
| Miglioranca et al 2012 | Pros | 25 | 40 | immed loading | Branemark | 25 | 8 | 97.5 | 95.2 |
| Aparicio et al 2014 | Retro | 22 | 41 | conventional | Branemark | 22 | 10 | 97.7 | 100 |
| Davo et al 2013 | Pros | 42 | 69 | immed loading | Branemark | 37 | 5 | 98.5 | 100 |
| Malo et al 2014 | Retro | 39 | 92 | immed loading | Branemark | 39 | 5 | 98.8 | 100 |
| Davo et al 2015 | Pros | 14 | 64 | immed loading | Branemark | 14 | 5 | 100 | 100 |
Zygoma Implant Systematic Reviews6061
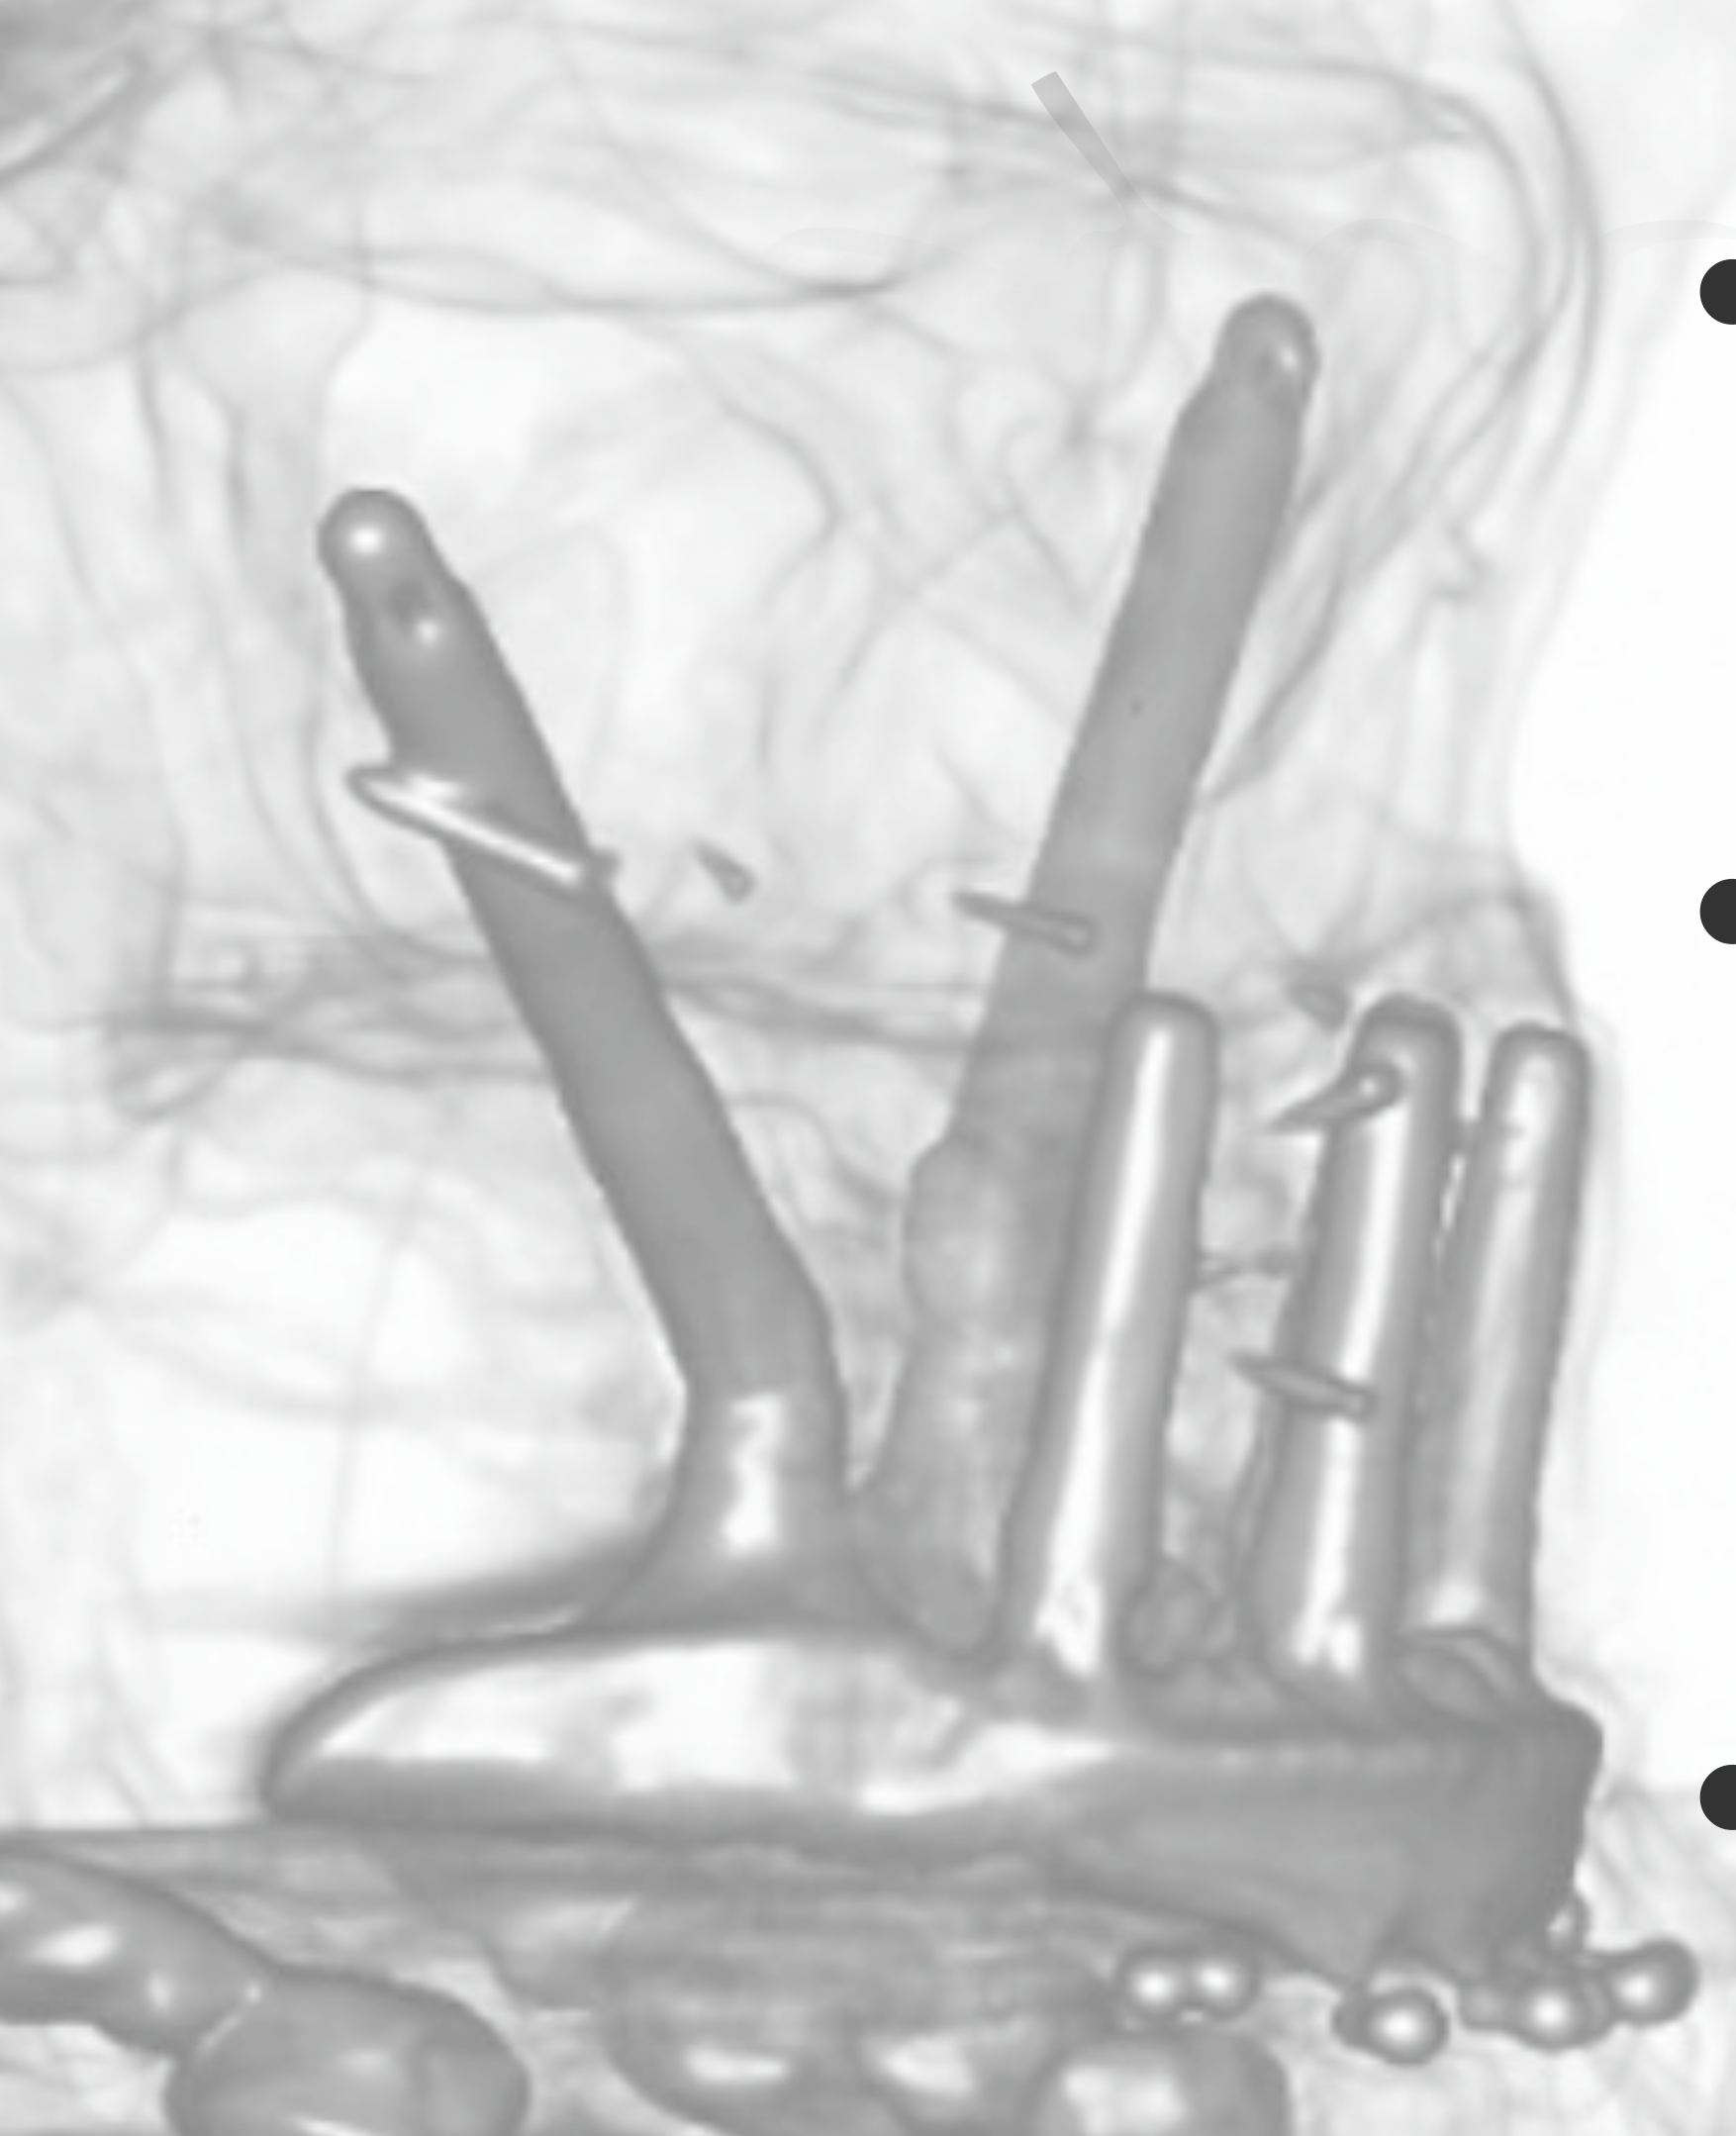
- Overall survival rate: 96.7% (including cancer patients)
- Intramaxillary immediate loaded (9 studies, 458 implants, 8 failures): ZI 98.3%
- 5 cases of sinusitis, all resolved
Chrcanovic BR, Abreu MH. Survival and complications of zygomatic implants: a systematic review. Oral Maxillofac Surg. 2013;17(2):81-93.
- 25 articles
- Overall survival rate 97.8% (1,541 ZI, 33 failures)
- Failure generally in the first year due to infection and sinusitis
Goiato MC, Pellizzer EP, Moreno A, Gennari-Filho H, Dos Santos DM, Santiago JF Jr, Dos Santos EG. Implants in the zygomatic bone for maxillary prosthetic rehabilitation: a systematic review. Int J Oral Maxillofac Surg. 2014;43:748-757. Review.
 |  |
Patient Satisfaction With Zygoma Implants62
- 16 patients:
- All satisfied; 50% with some complaints (50% prosthesis, 38% implants)
- 22 patients:
- 84% satisfaction above 80% (32% had 100% satisfaction)
- Satisfaction (high) approaching the general population
Sartori et al Evaluation of Patients Rehabilitated with Zygomatic Fixtures. J Oral Maxillofac Surg 2012;70:314-9.
Aparicio et al The Long Term Use of Zygomatic Implants: A 10 Year Clinical and Radiographic Report. Clin Impl Dent Relat Res 2012
Wang F, Monje A, Lin GH, Wu Y, Monje F, Wang HL, Davó R. Reliability of four zygomatic implant-supported prostheses for the rehabilitation of the atrophic maxilla: A systematic review IJOMI 2015;30:293-298.
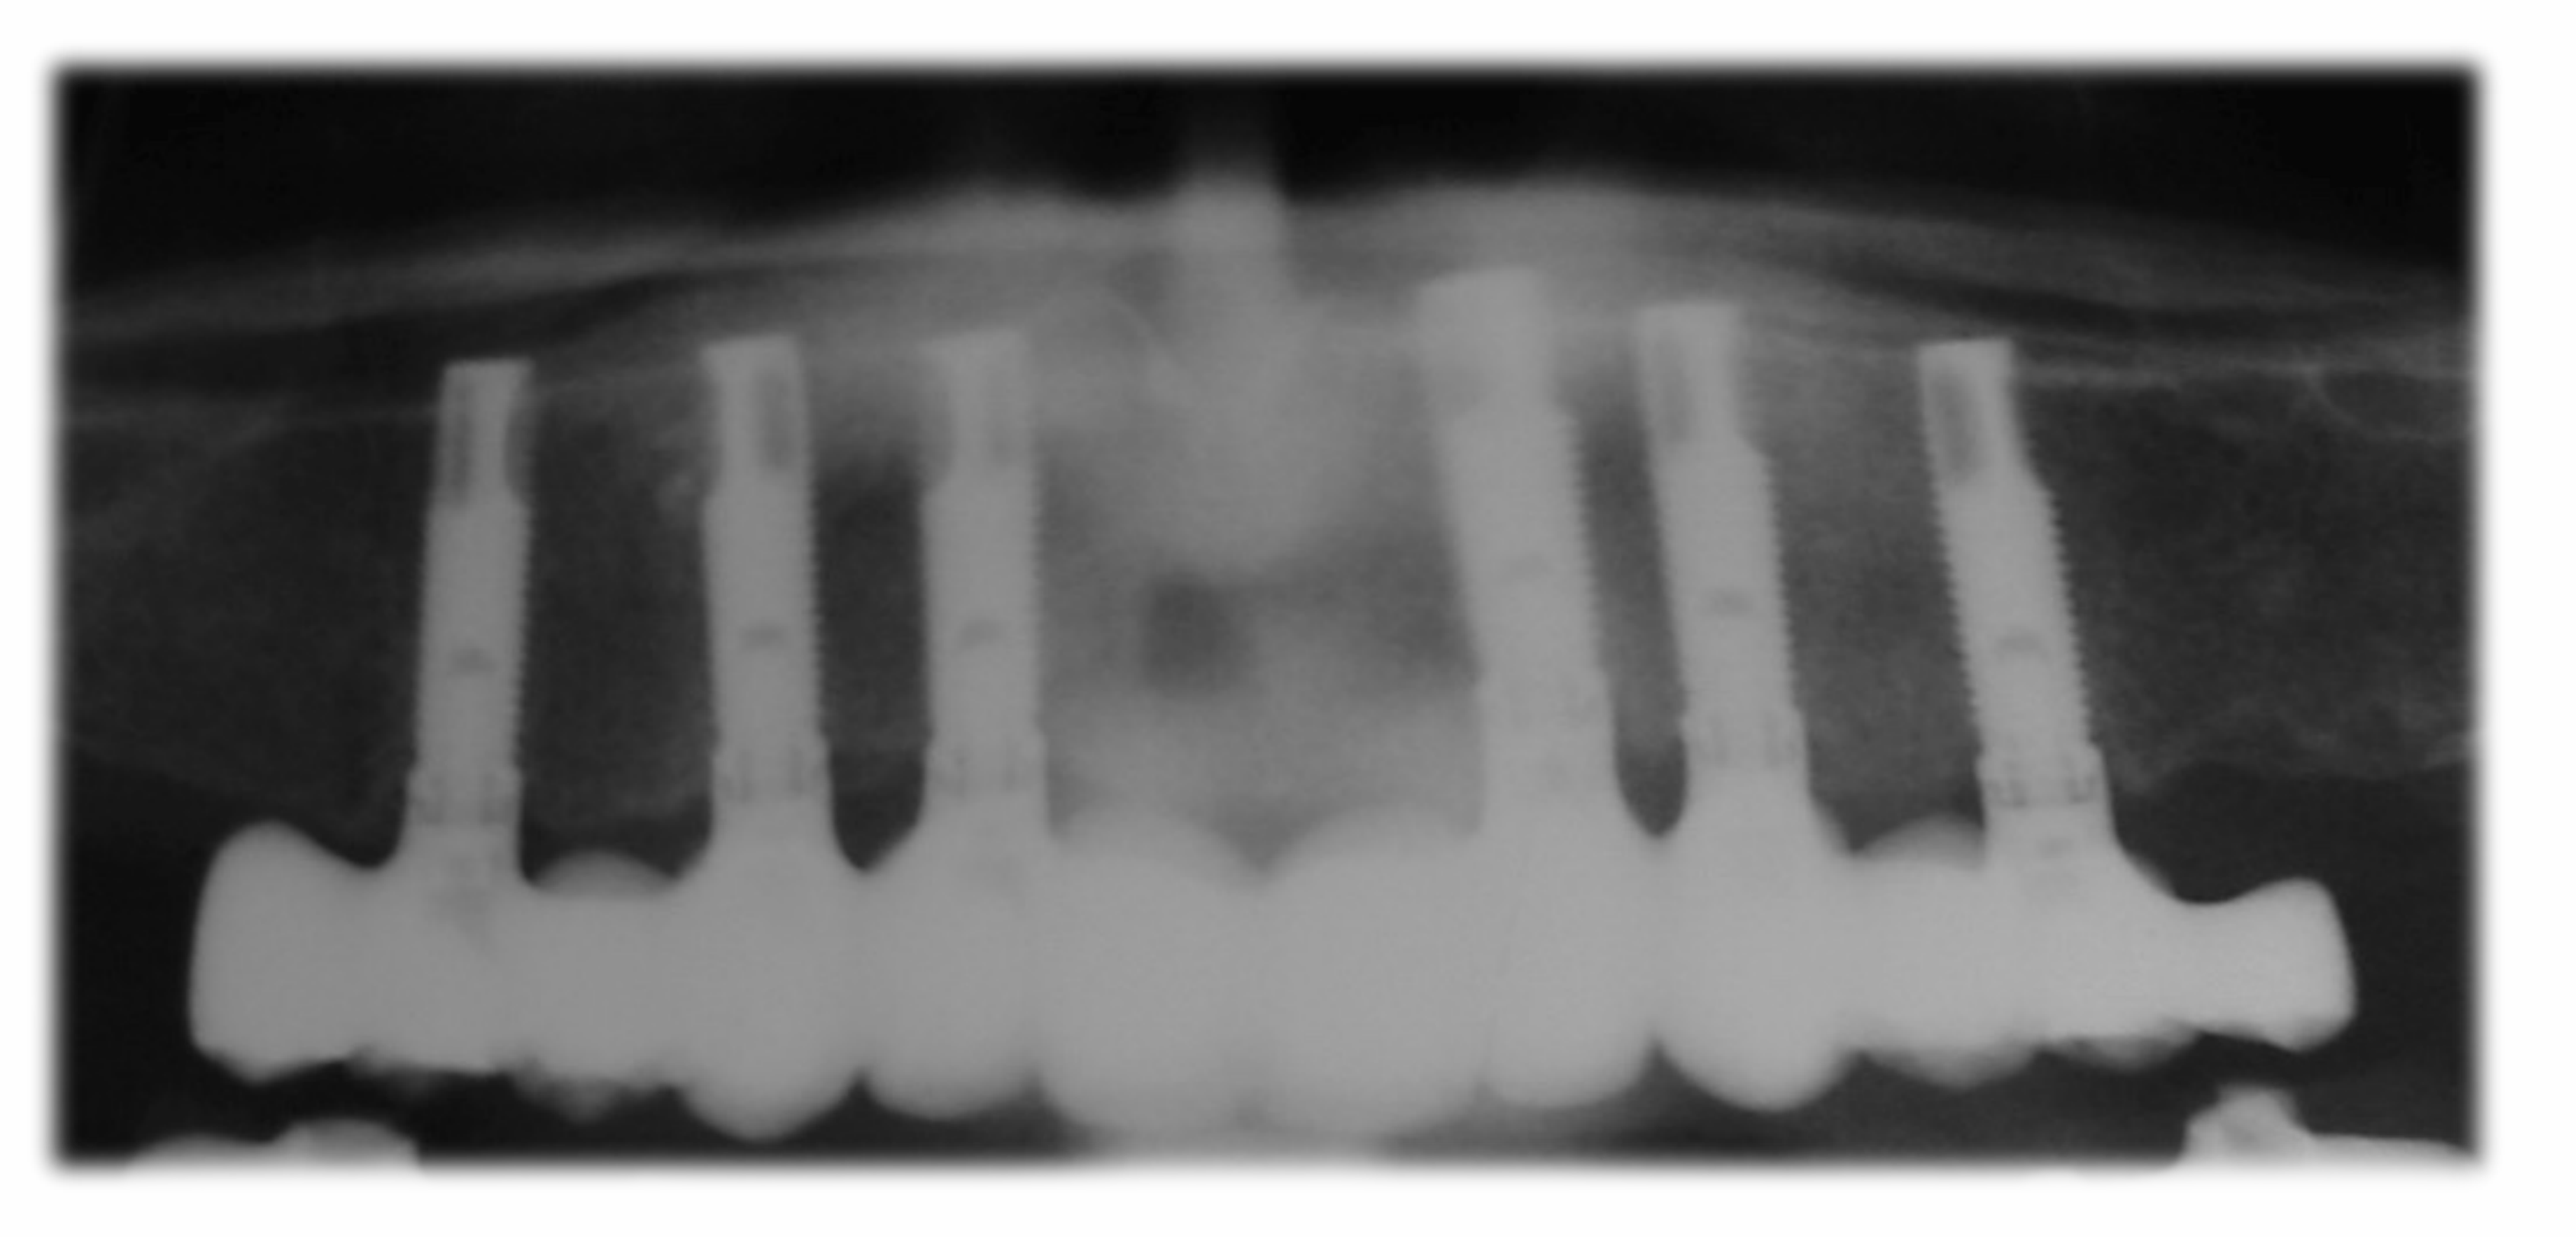
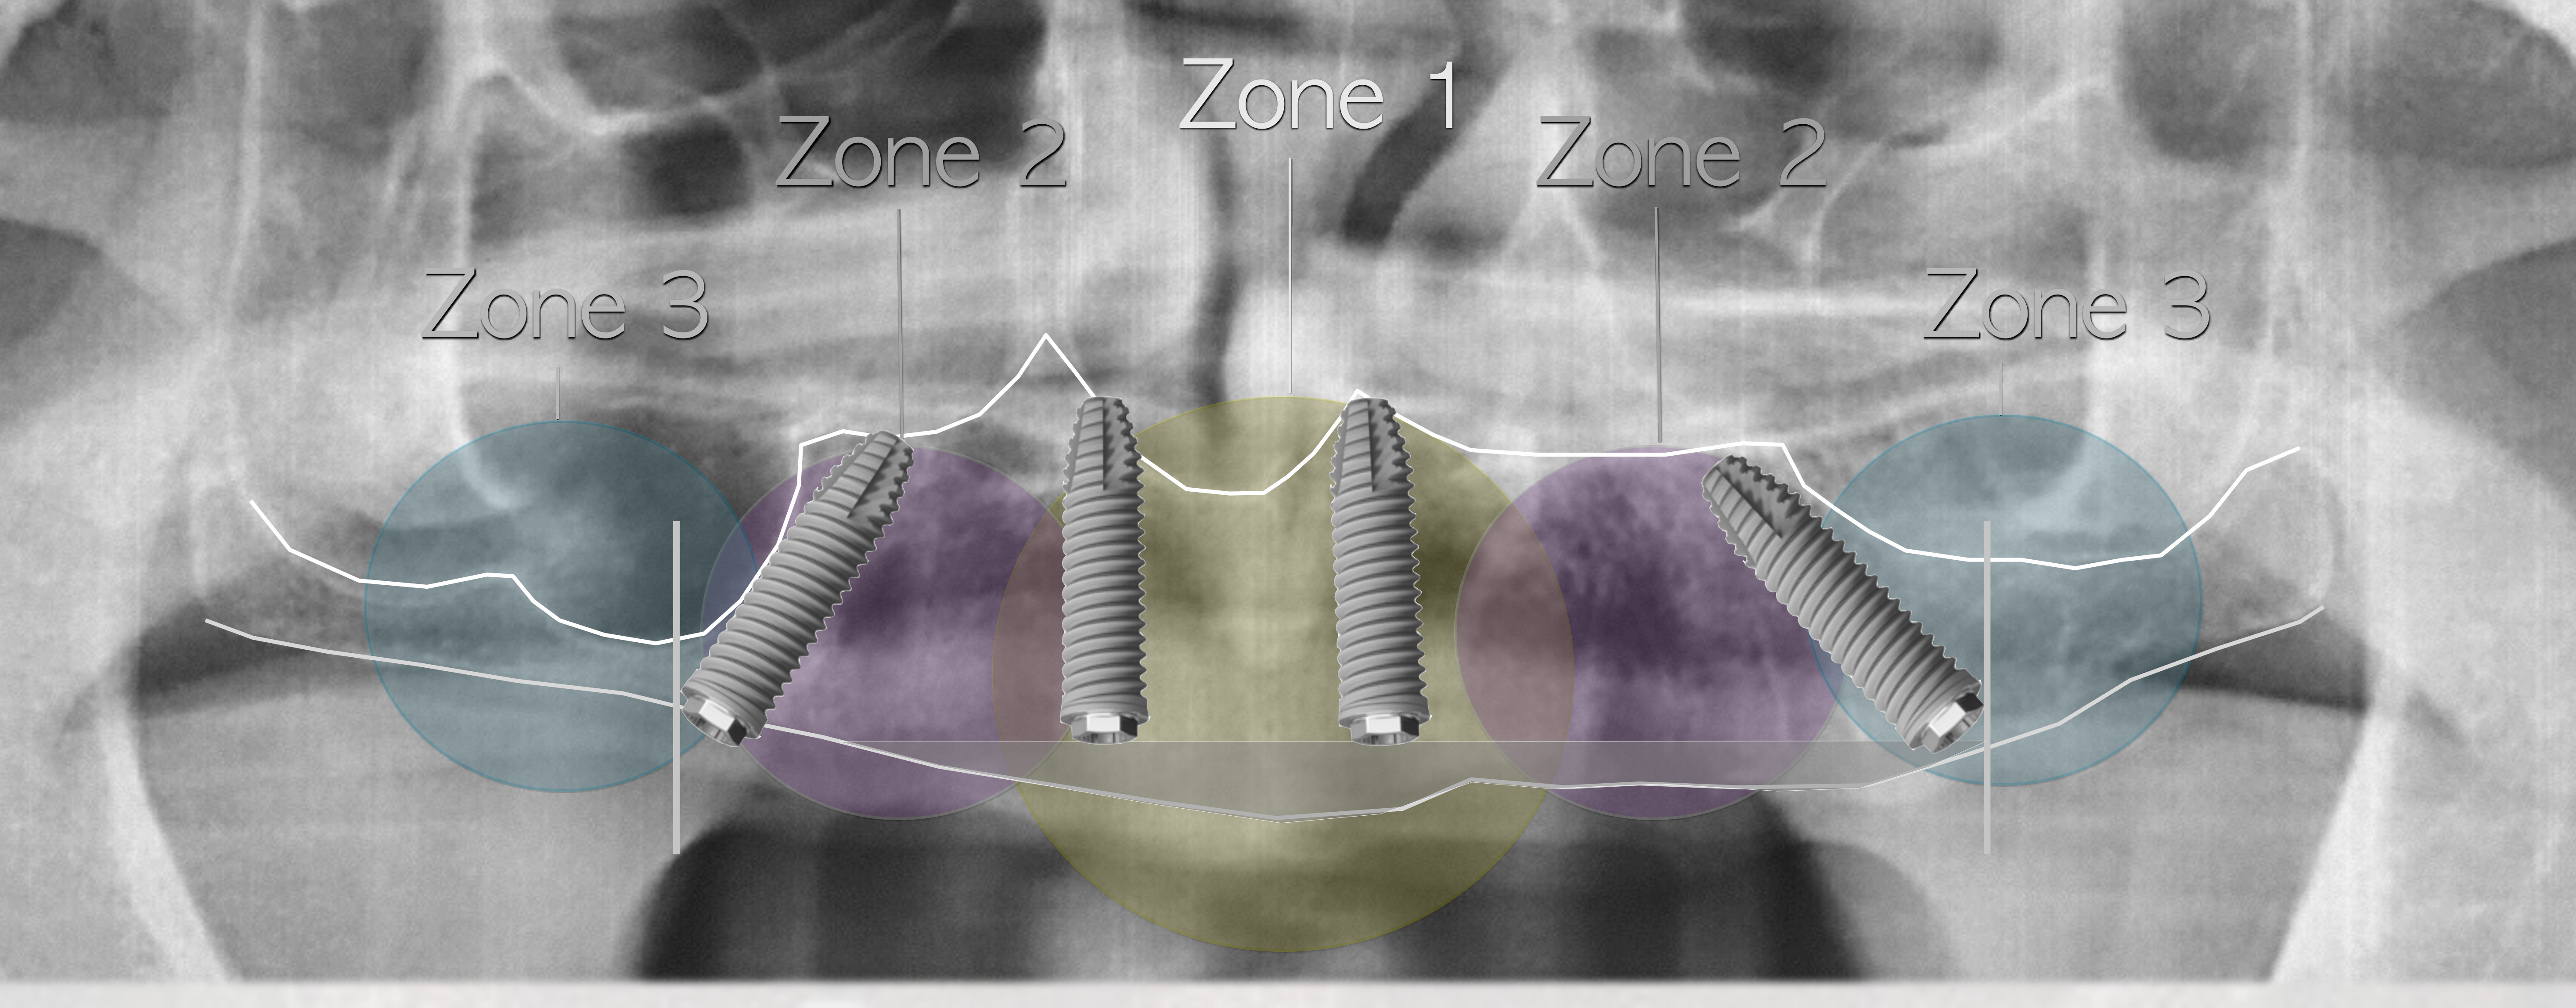
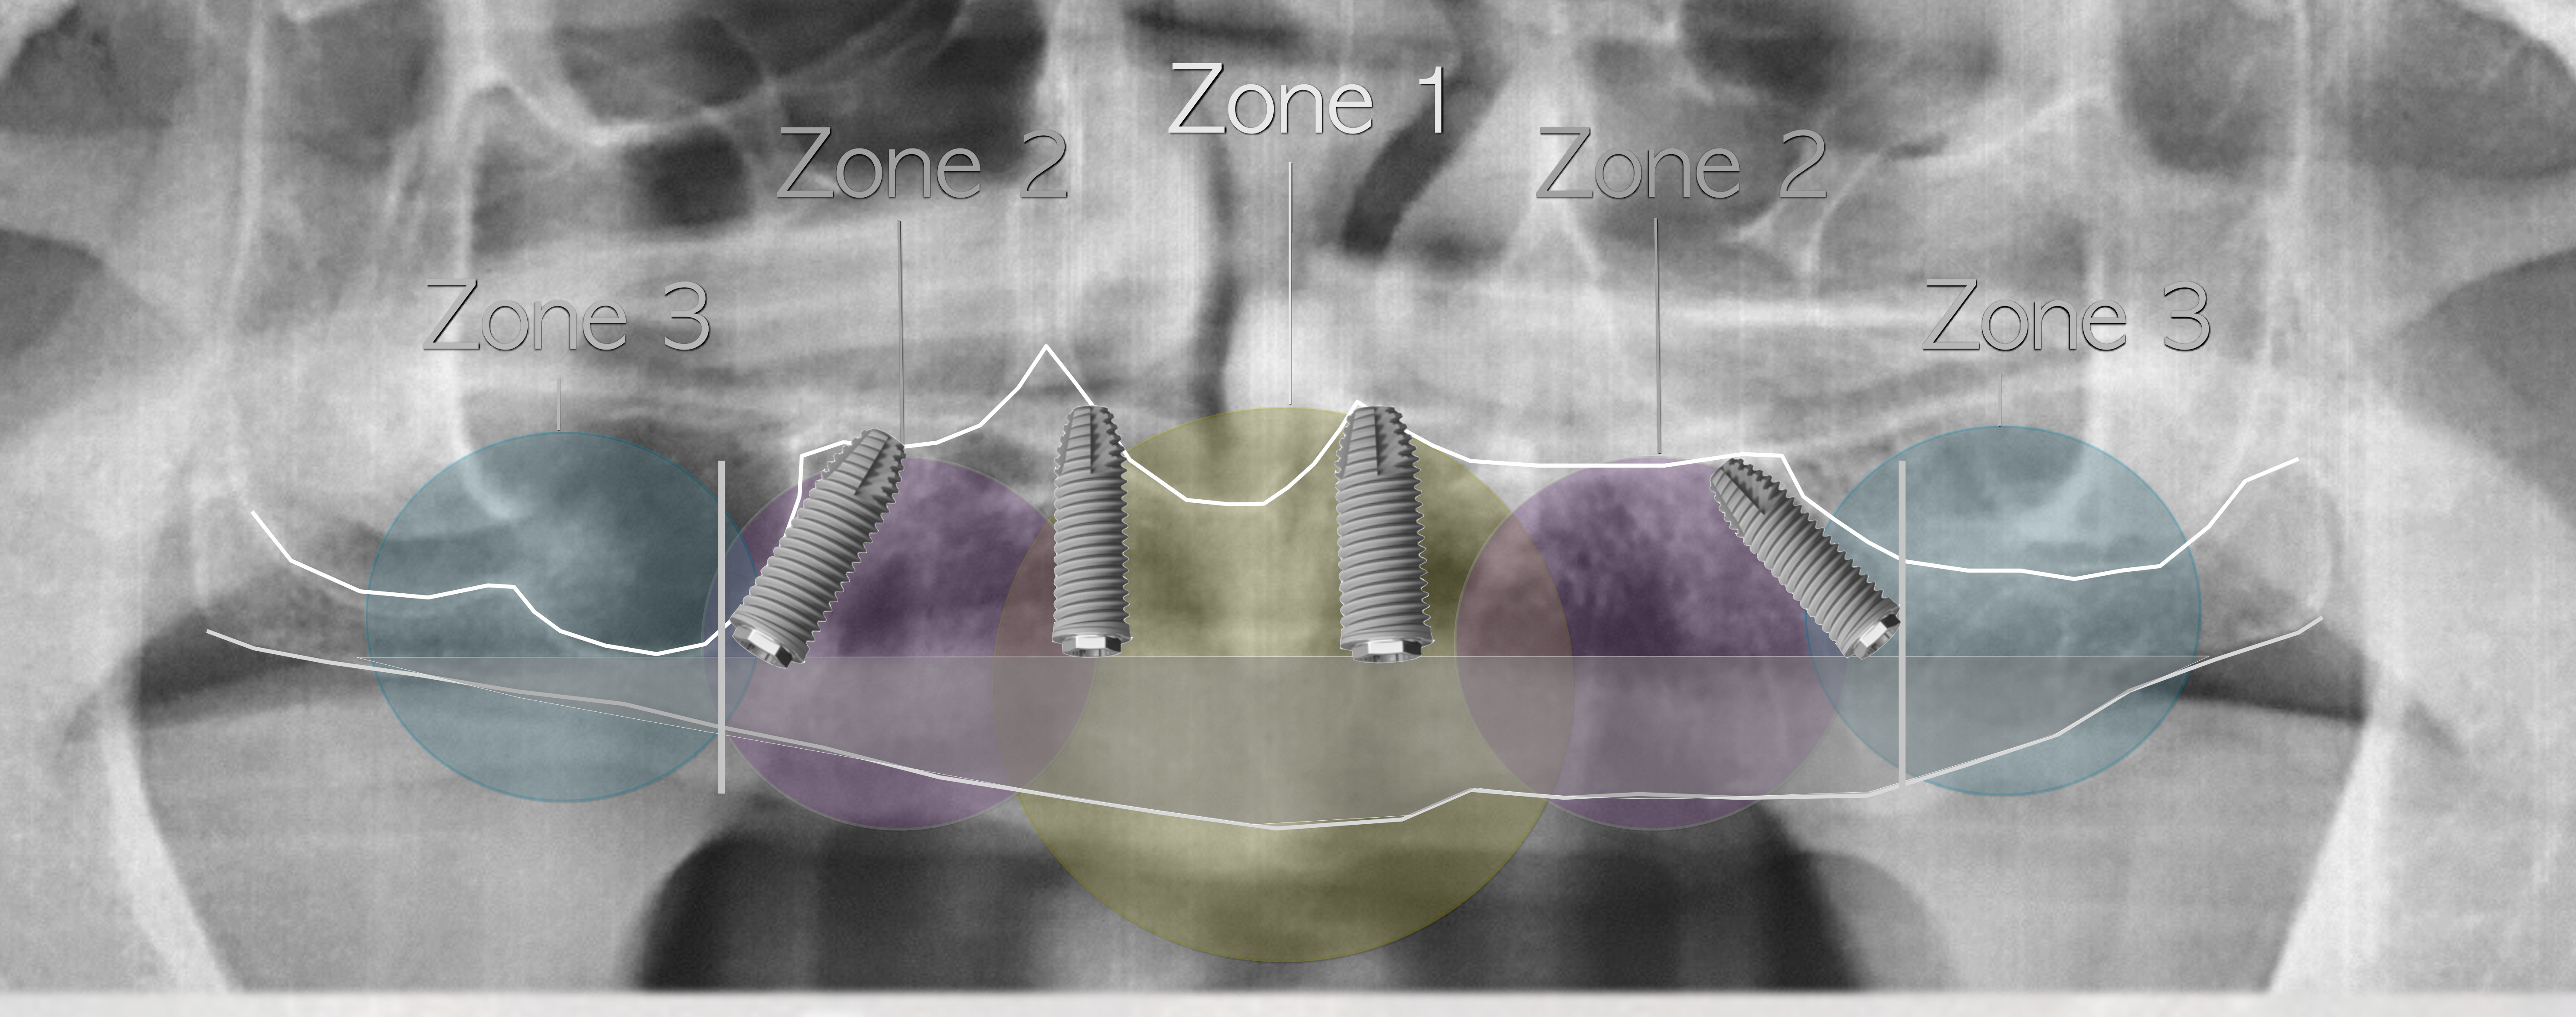
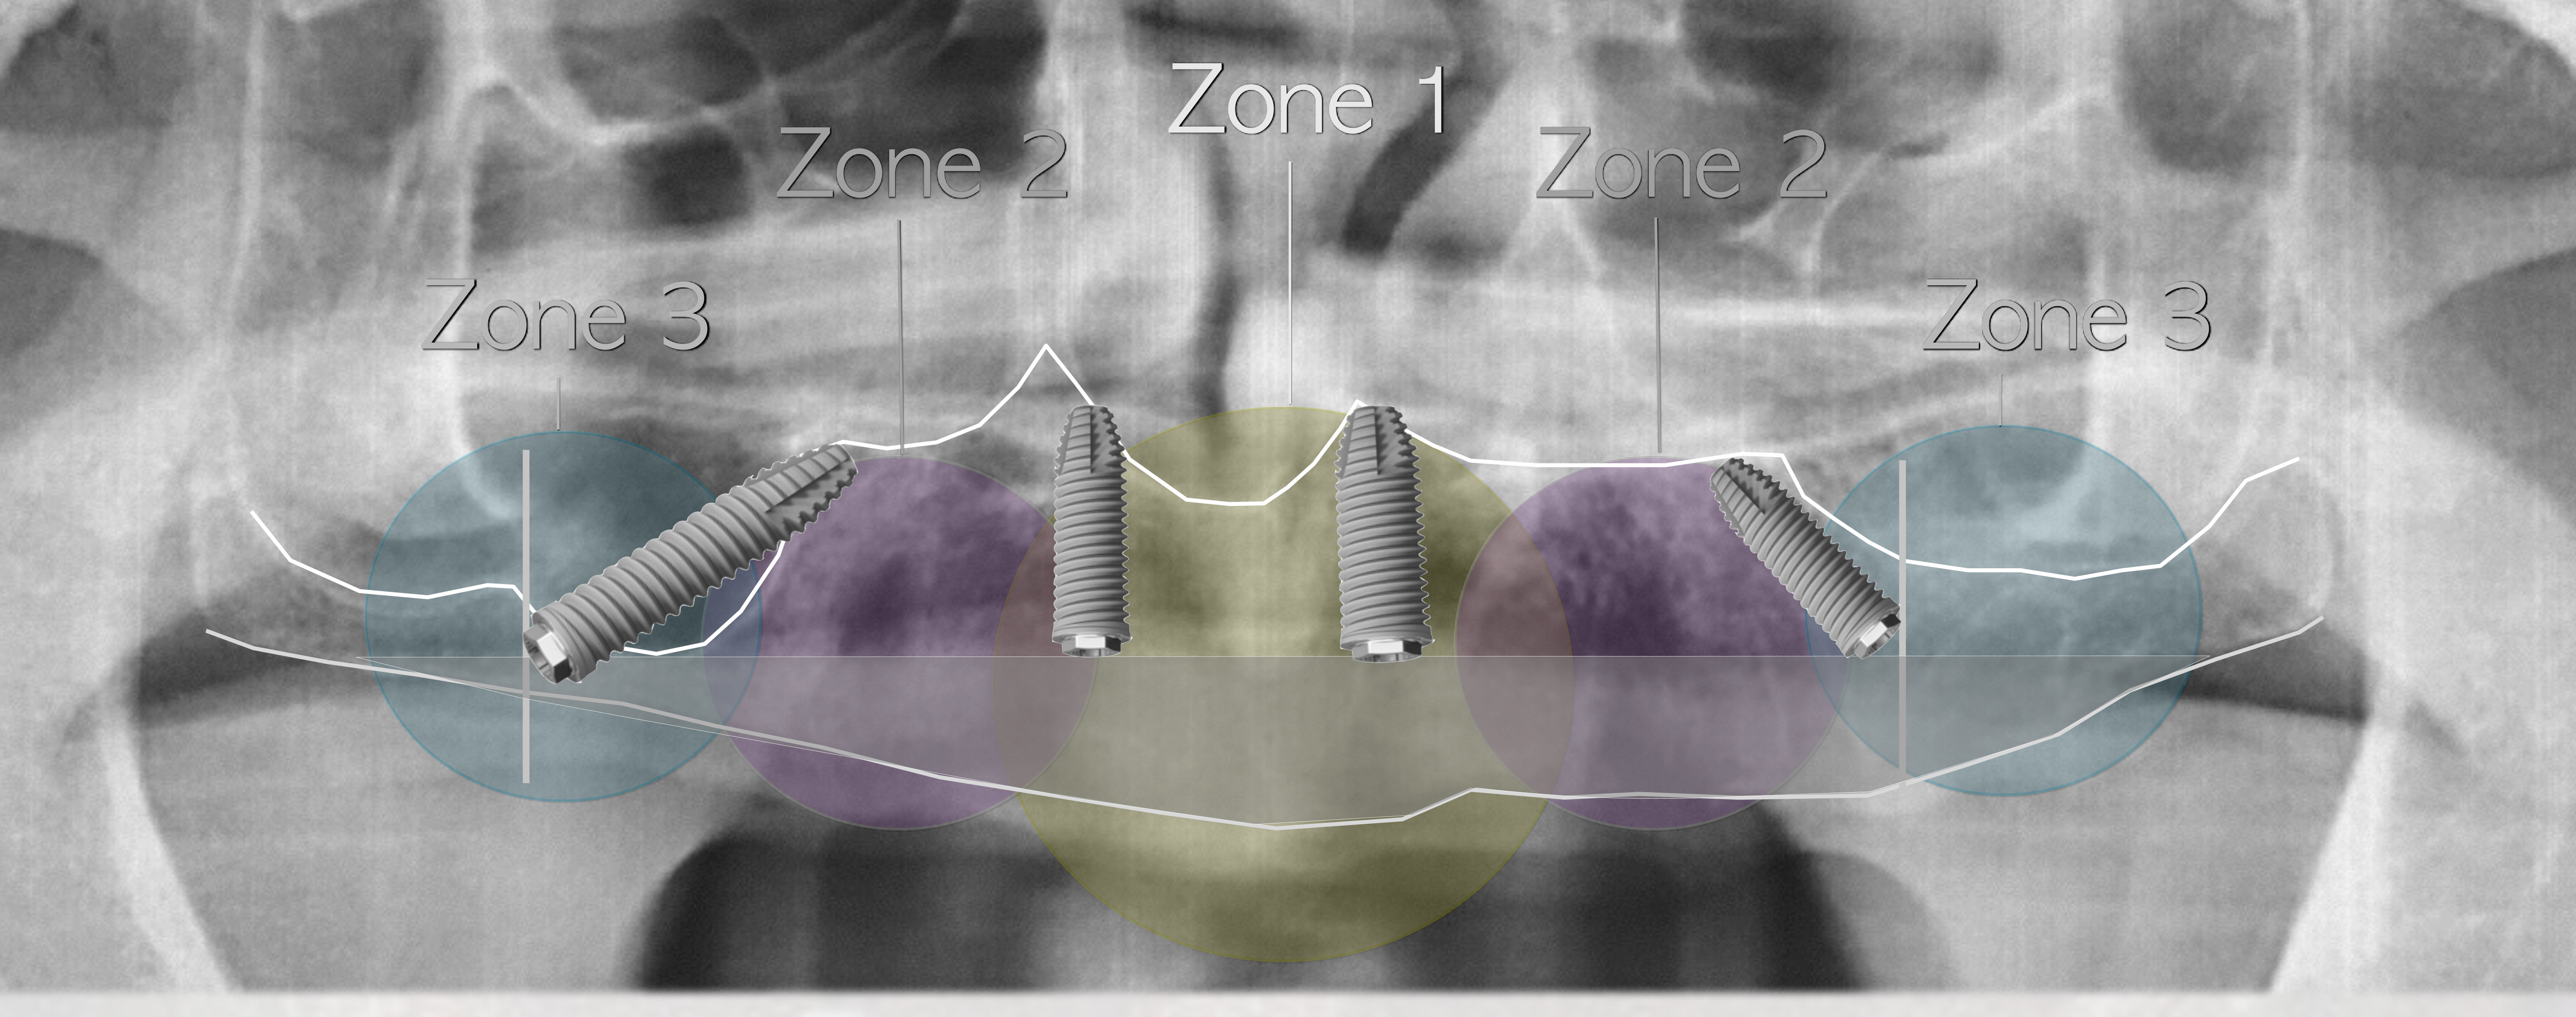
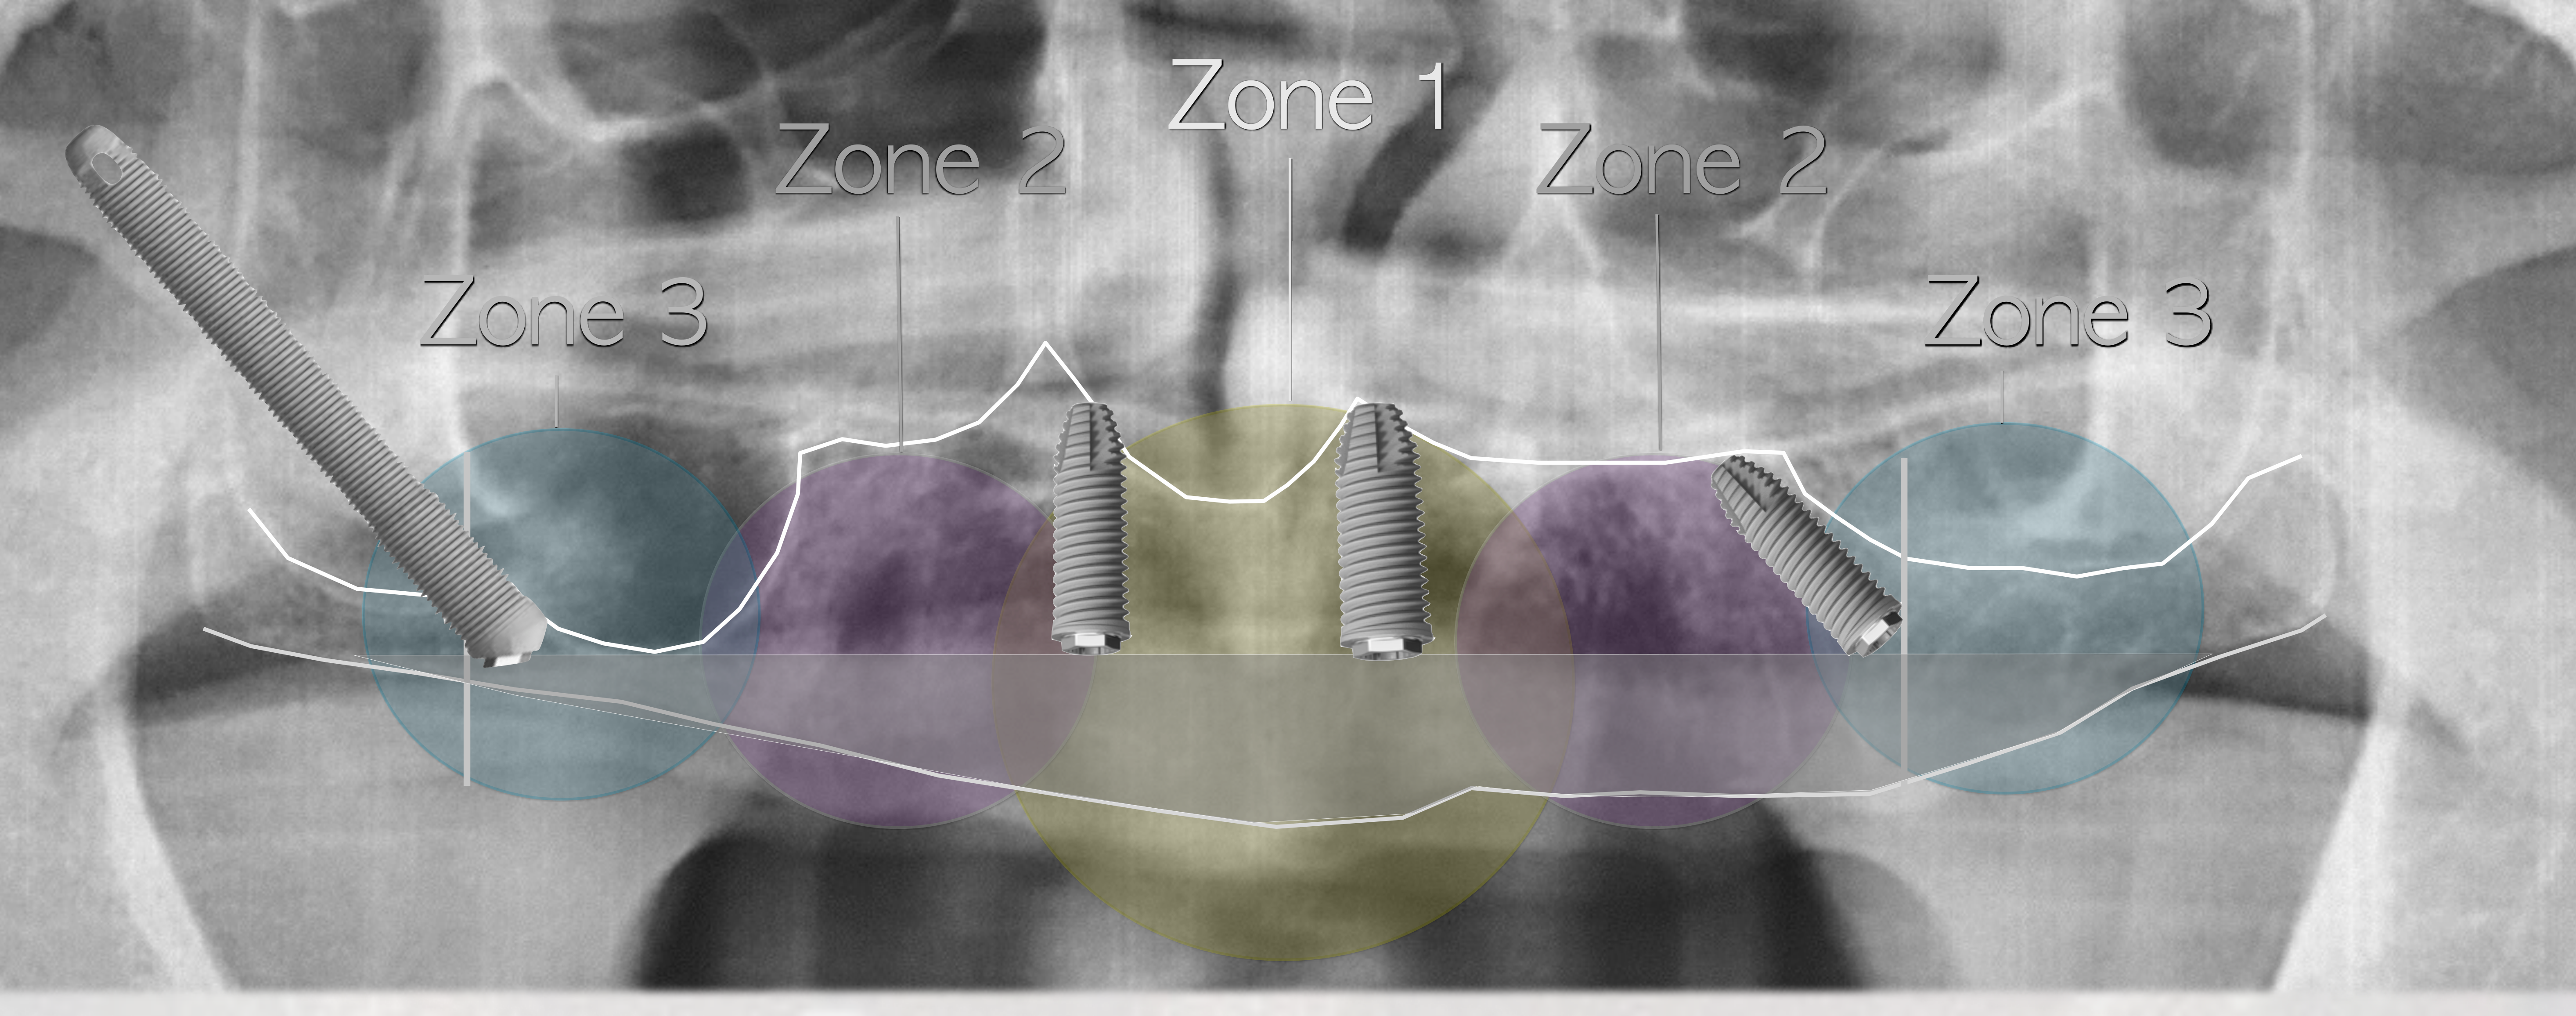
Zygoma Treatment Planning Guidelines6364656667
Bedrossian E. Rehabilitation of the edentulous maxilla with the zygoma concept: A 7-year prospective study IJOMI 2010:25; 1213-1221
- Zones 1, 2, & 3: Traditional axial implants
Bedrossian E. Rehabilitation of the edentulous maxilla with the zygoma concept: A 7-year prospective study IJOMI 2010:25;1213-1221
- Zones 1 & 2: Traditional axial and tilted implants
Bedrossian E. Rehabilitation of the edentulous maxilla with the zygoma concept: A 7-year prospective study IJOMI 2010:25;1213-1221
- Zone 1 only: Traditional axial and zygomatic implants
Bedrossian E. Rehabilitation of the edentulous maxilla with the zygoma concept: A 7-year prospective study IJOMI 2010:25;1213-1221
- Insufficient bone in all zones: Quad zygoma
Bedrossian E. Rehabilitation of the edentulous maxilla with the zygoma concept: A 7-year prospective study IJOMI 2010:25;1213-1221
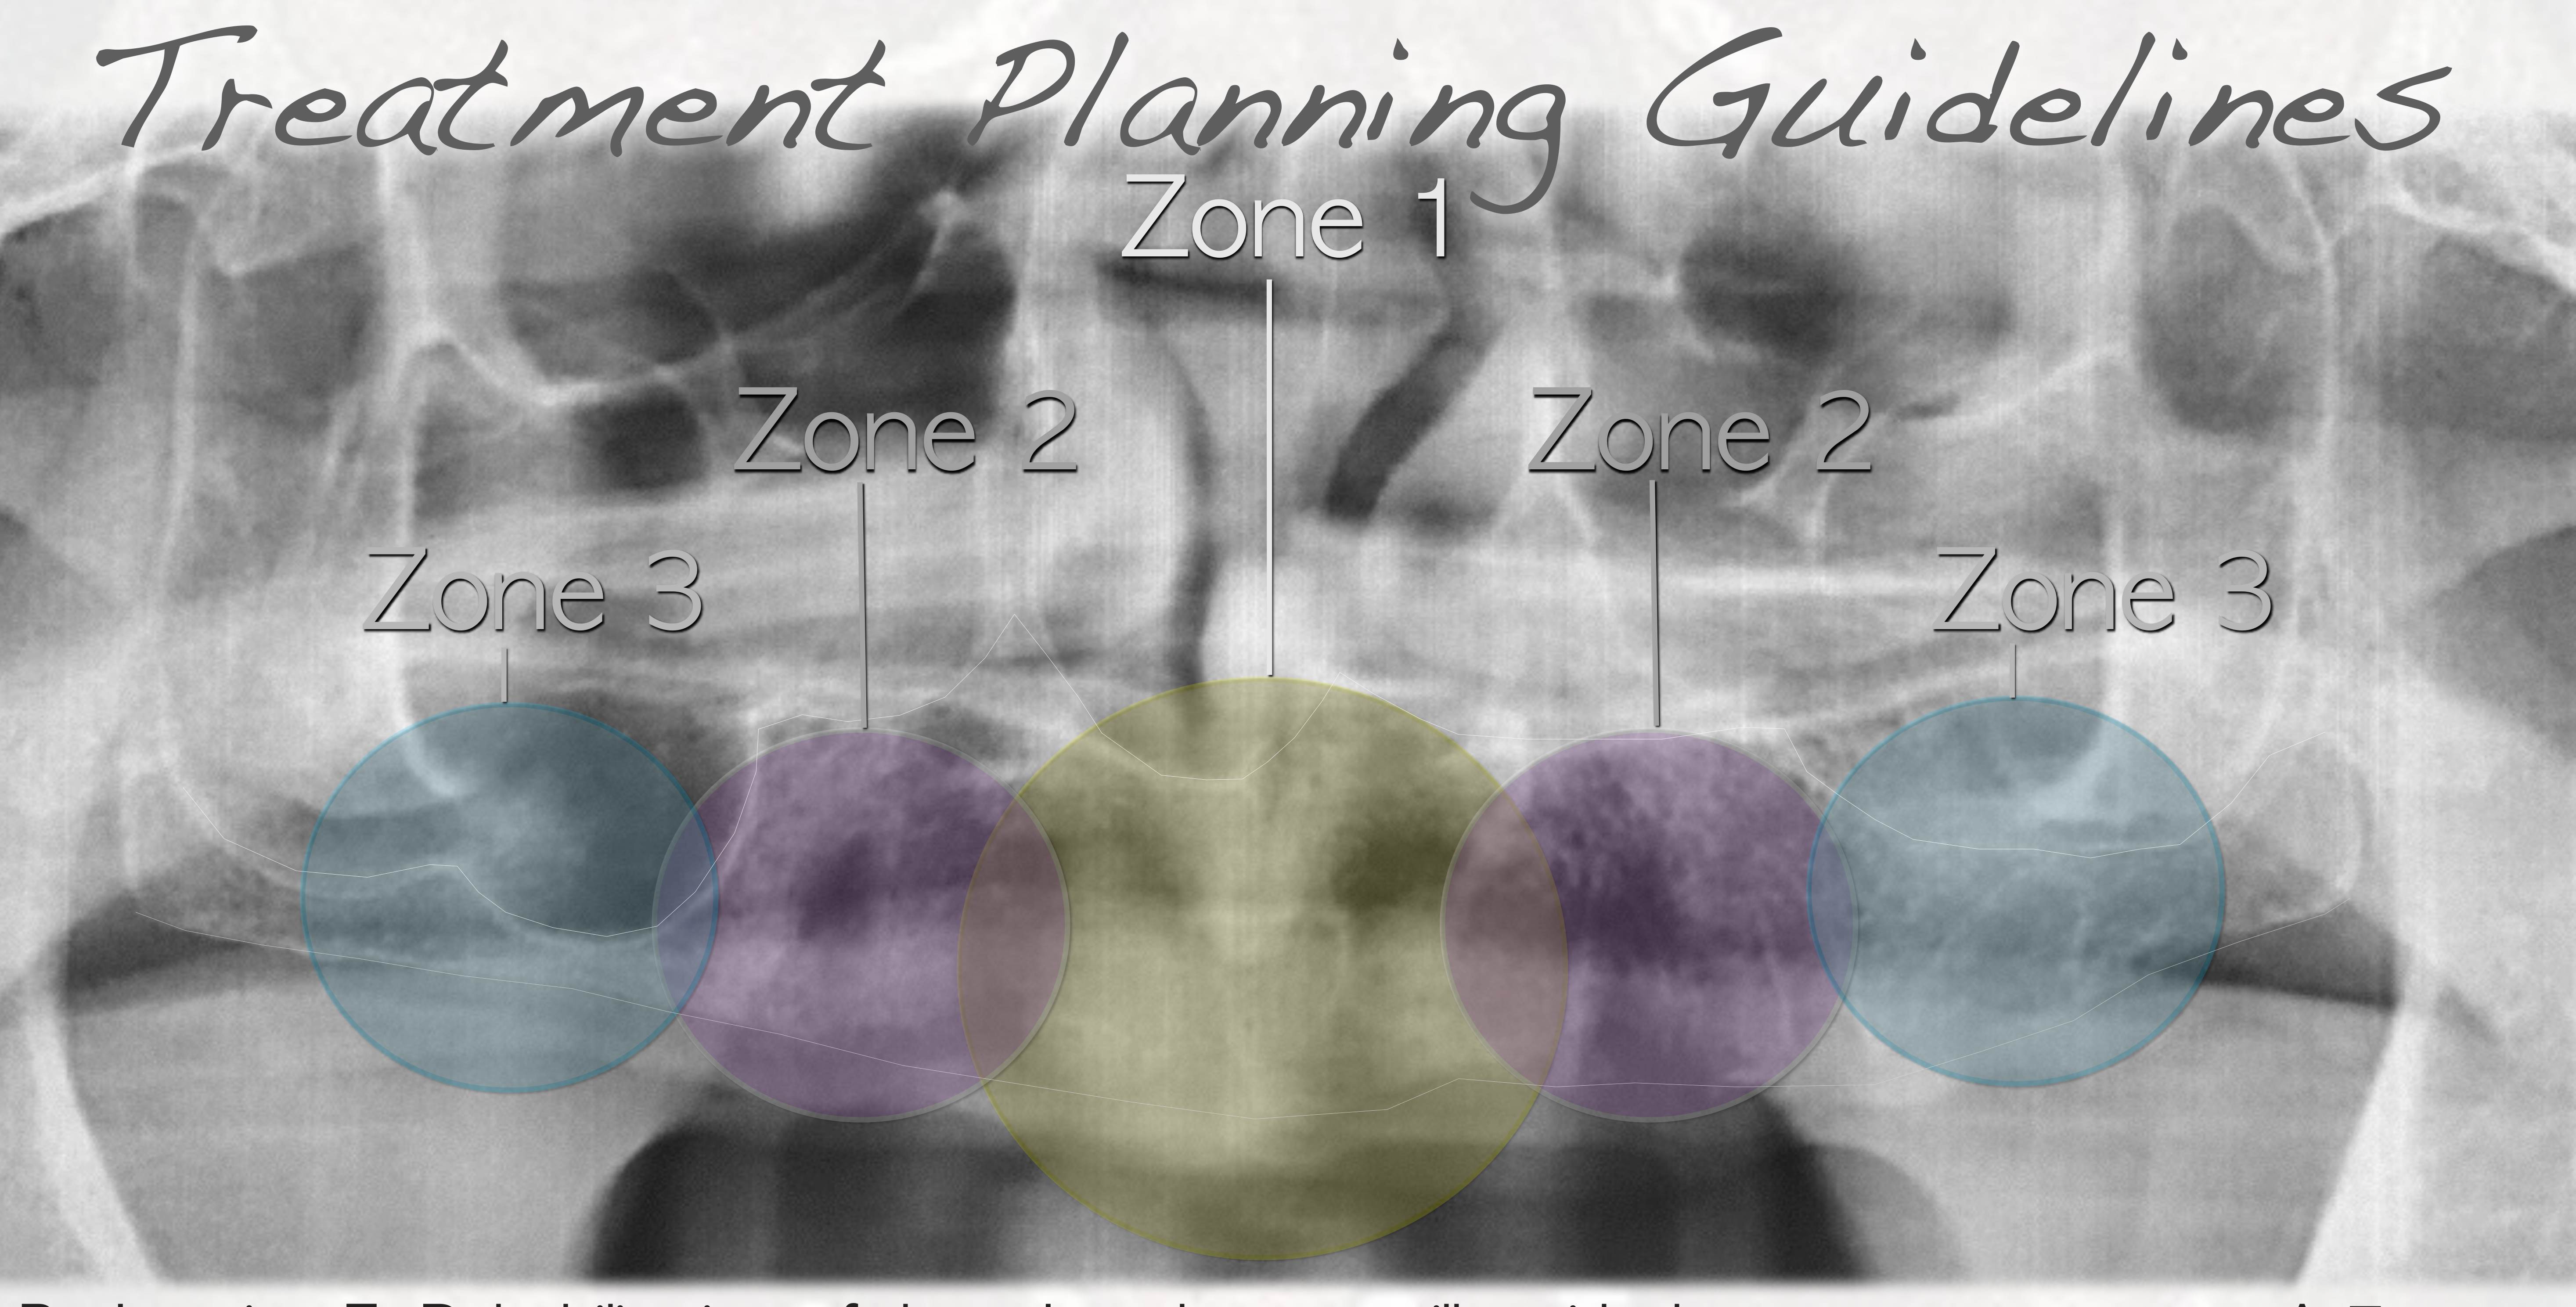

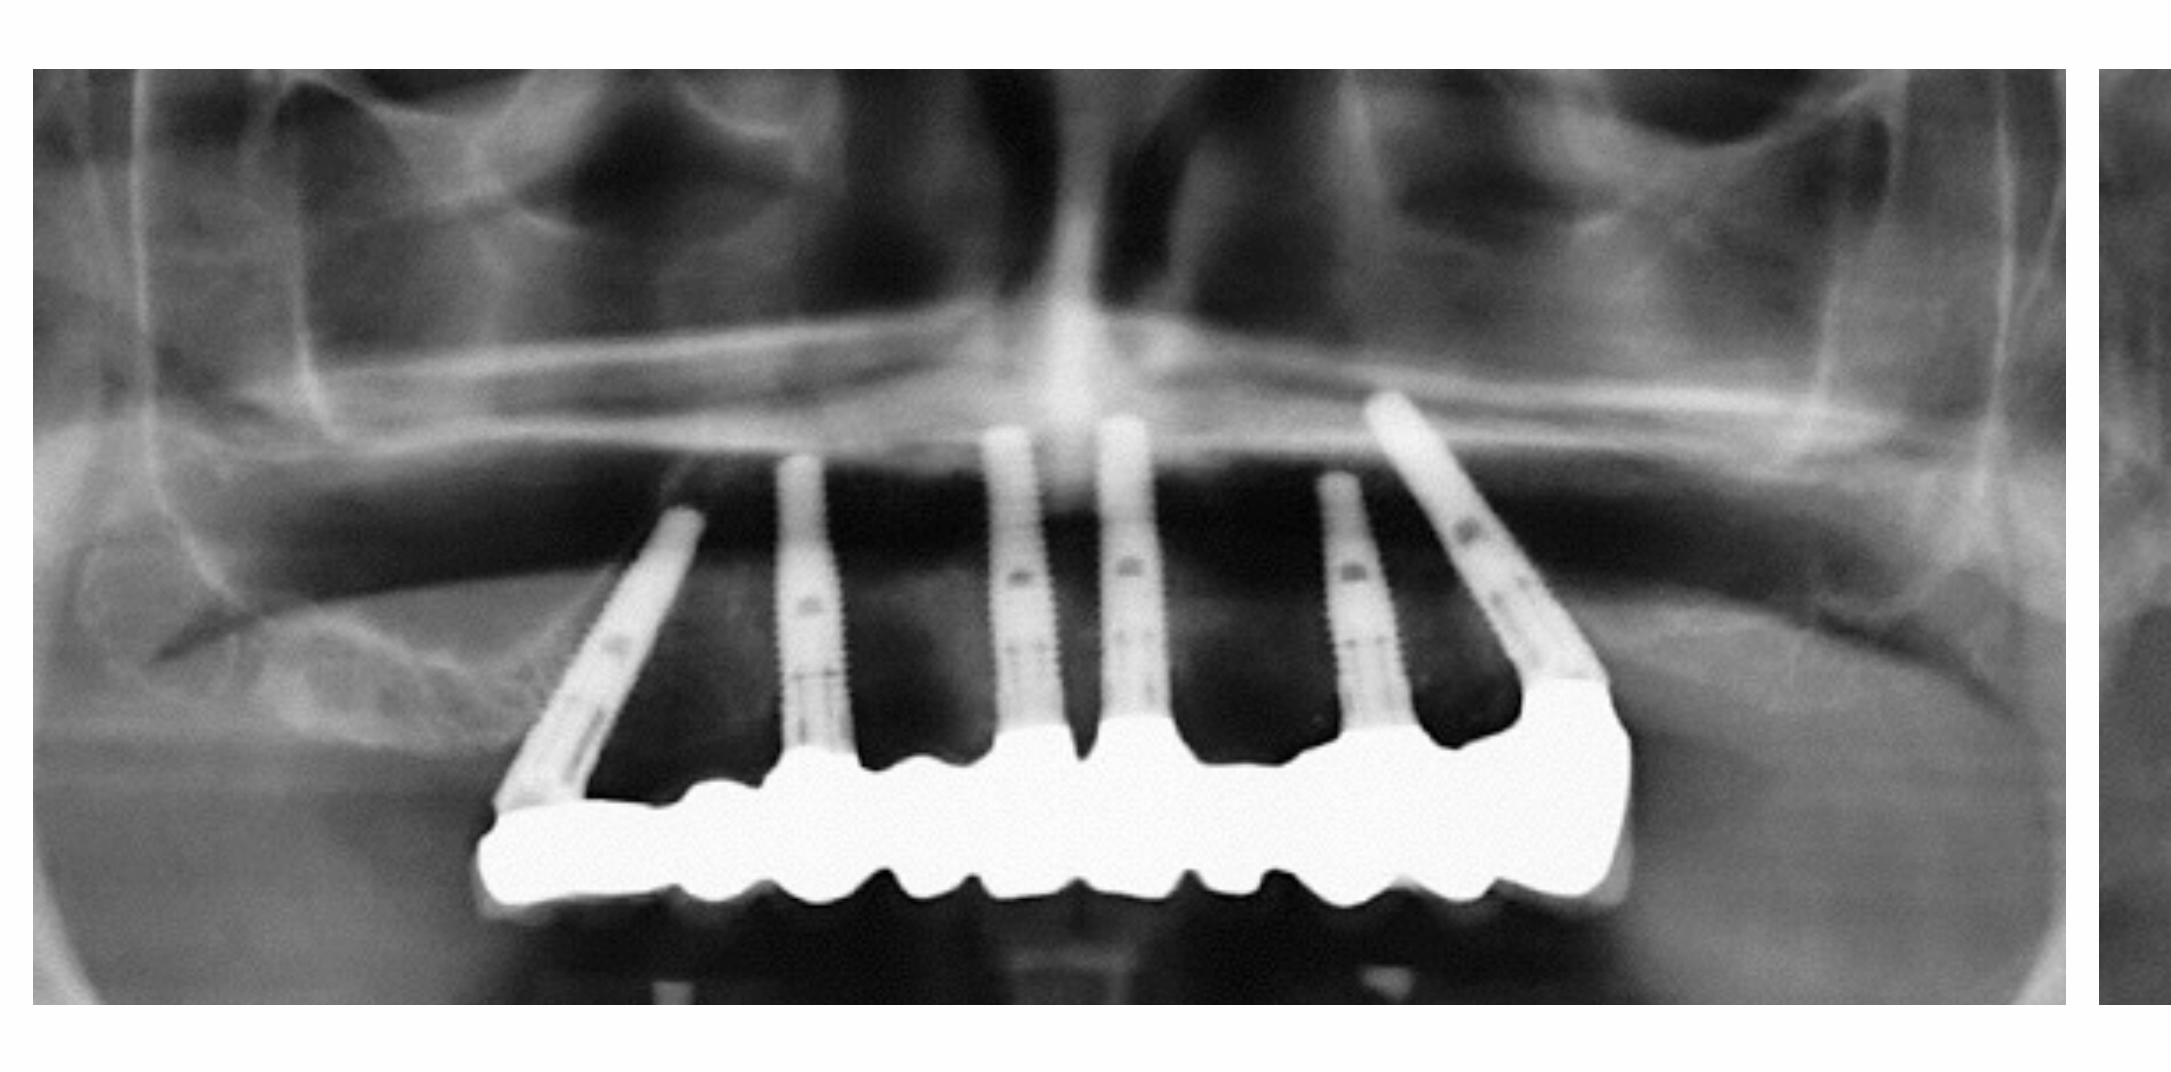
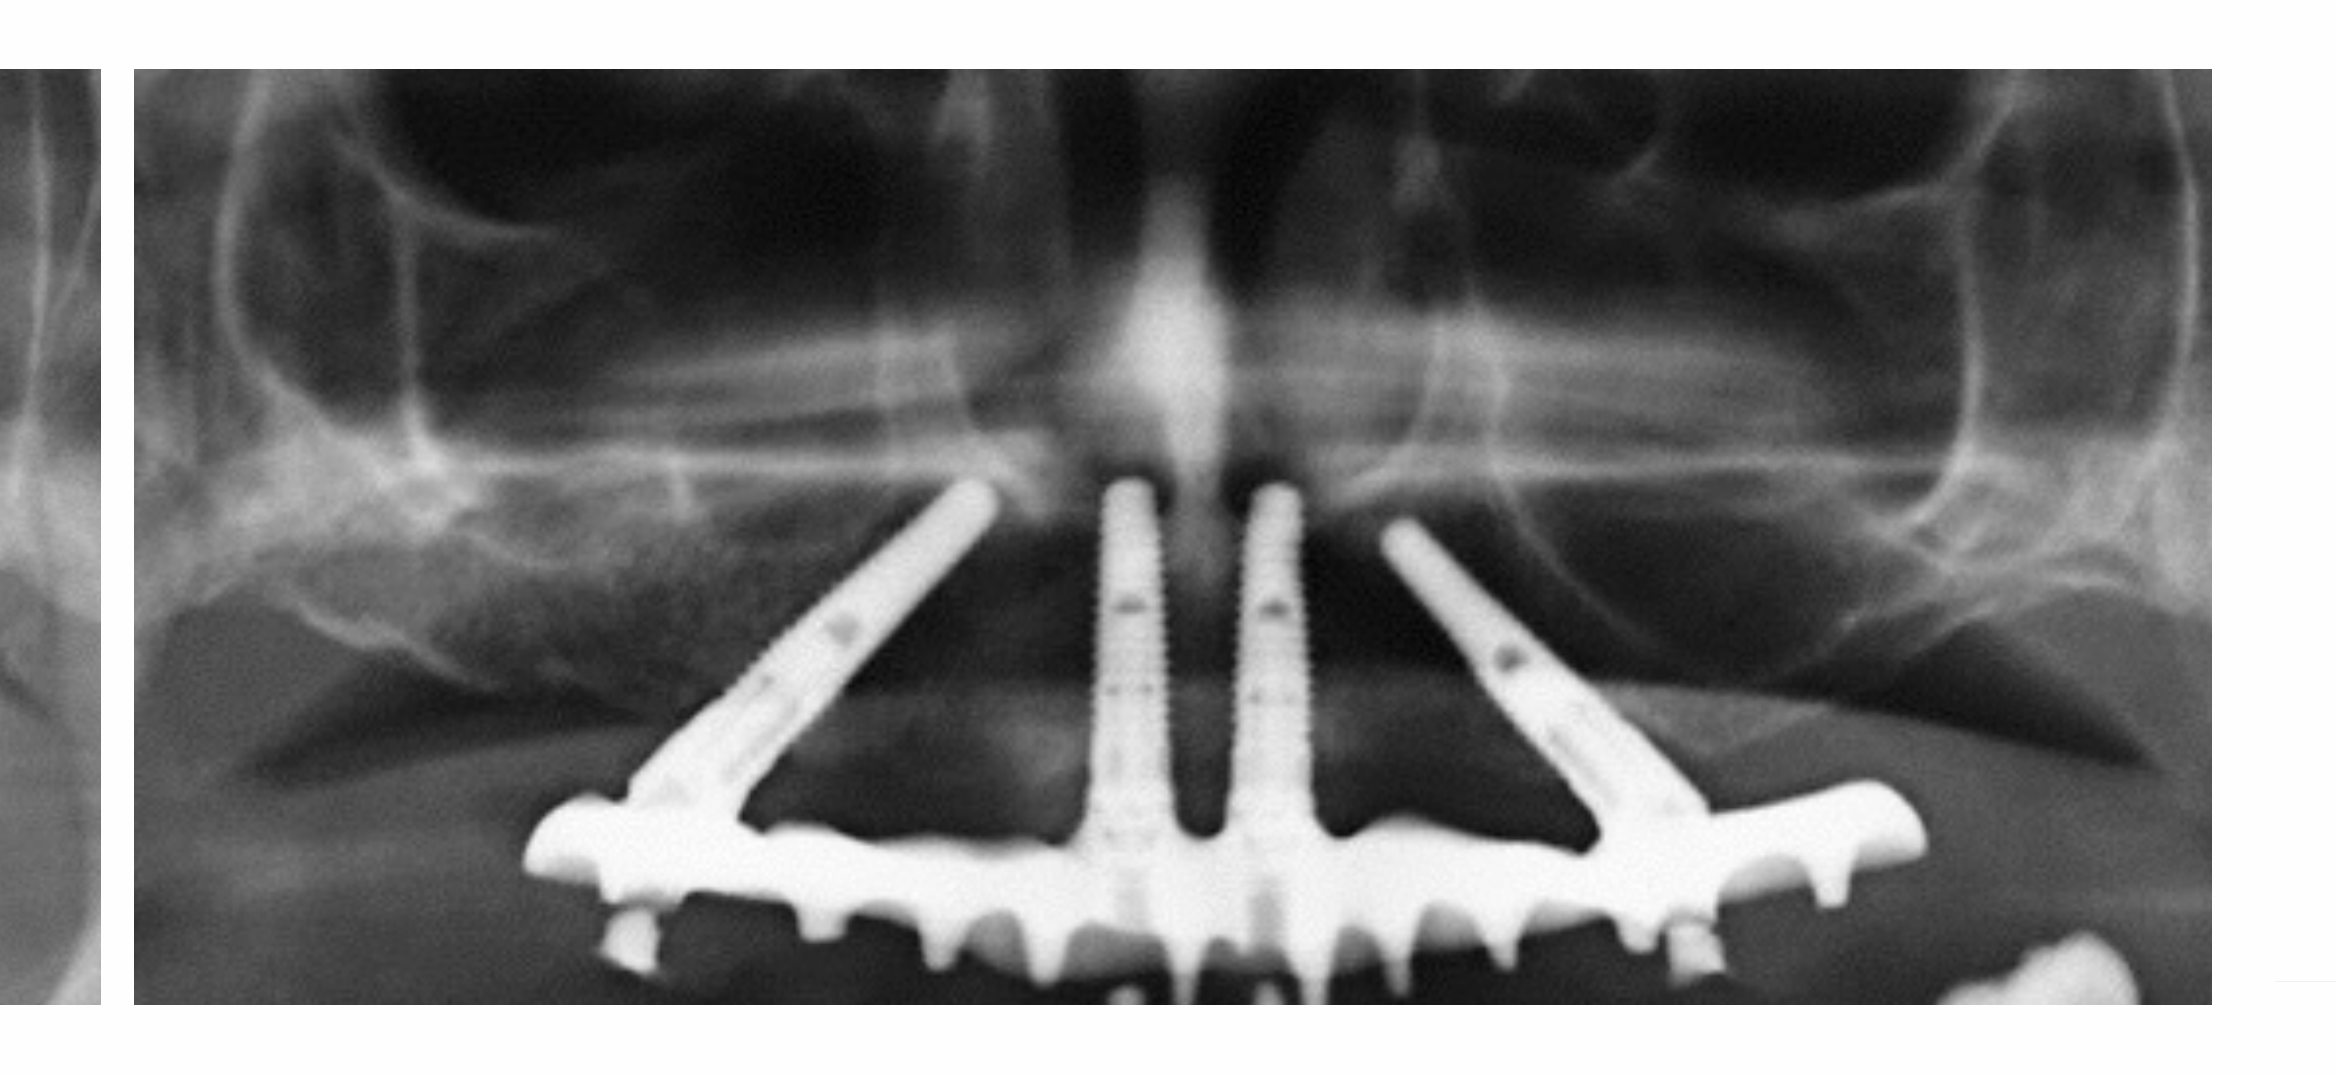

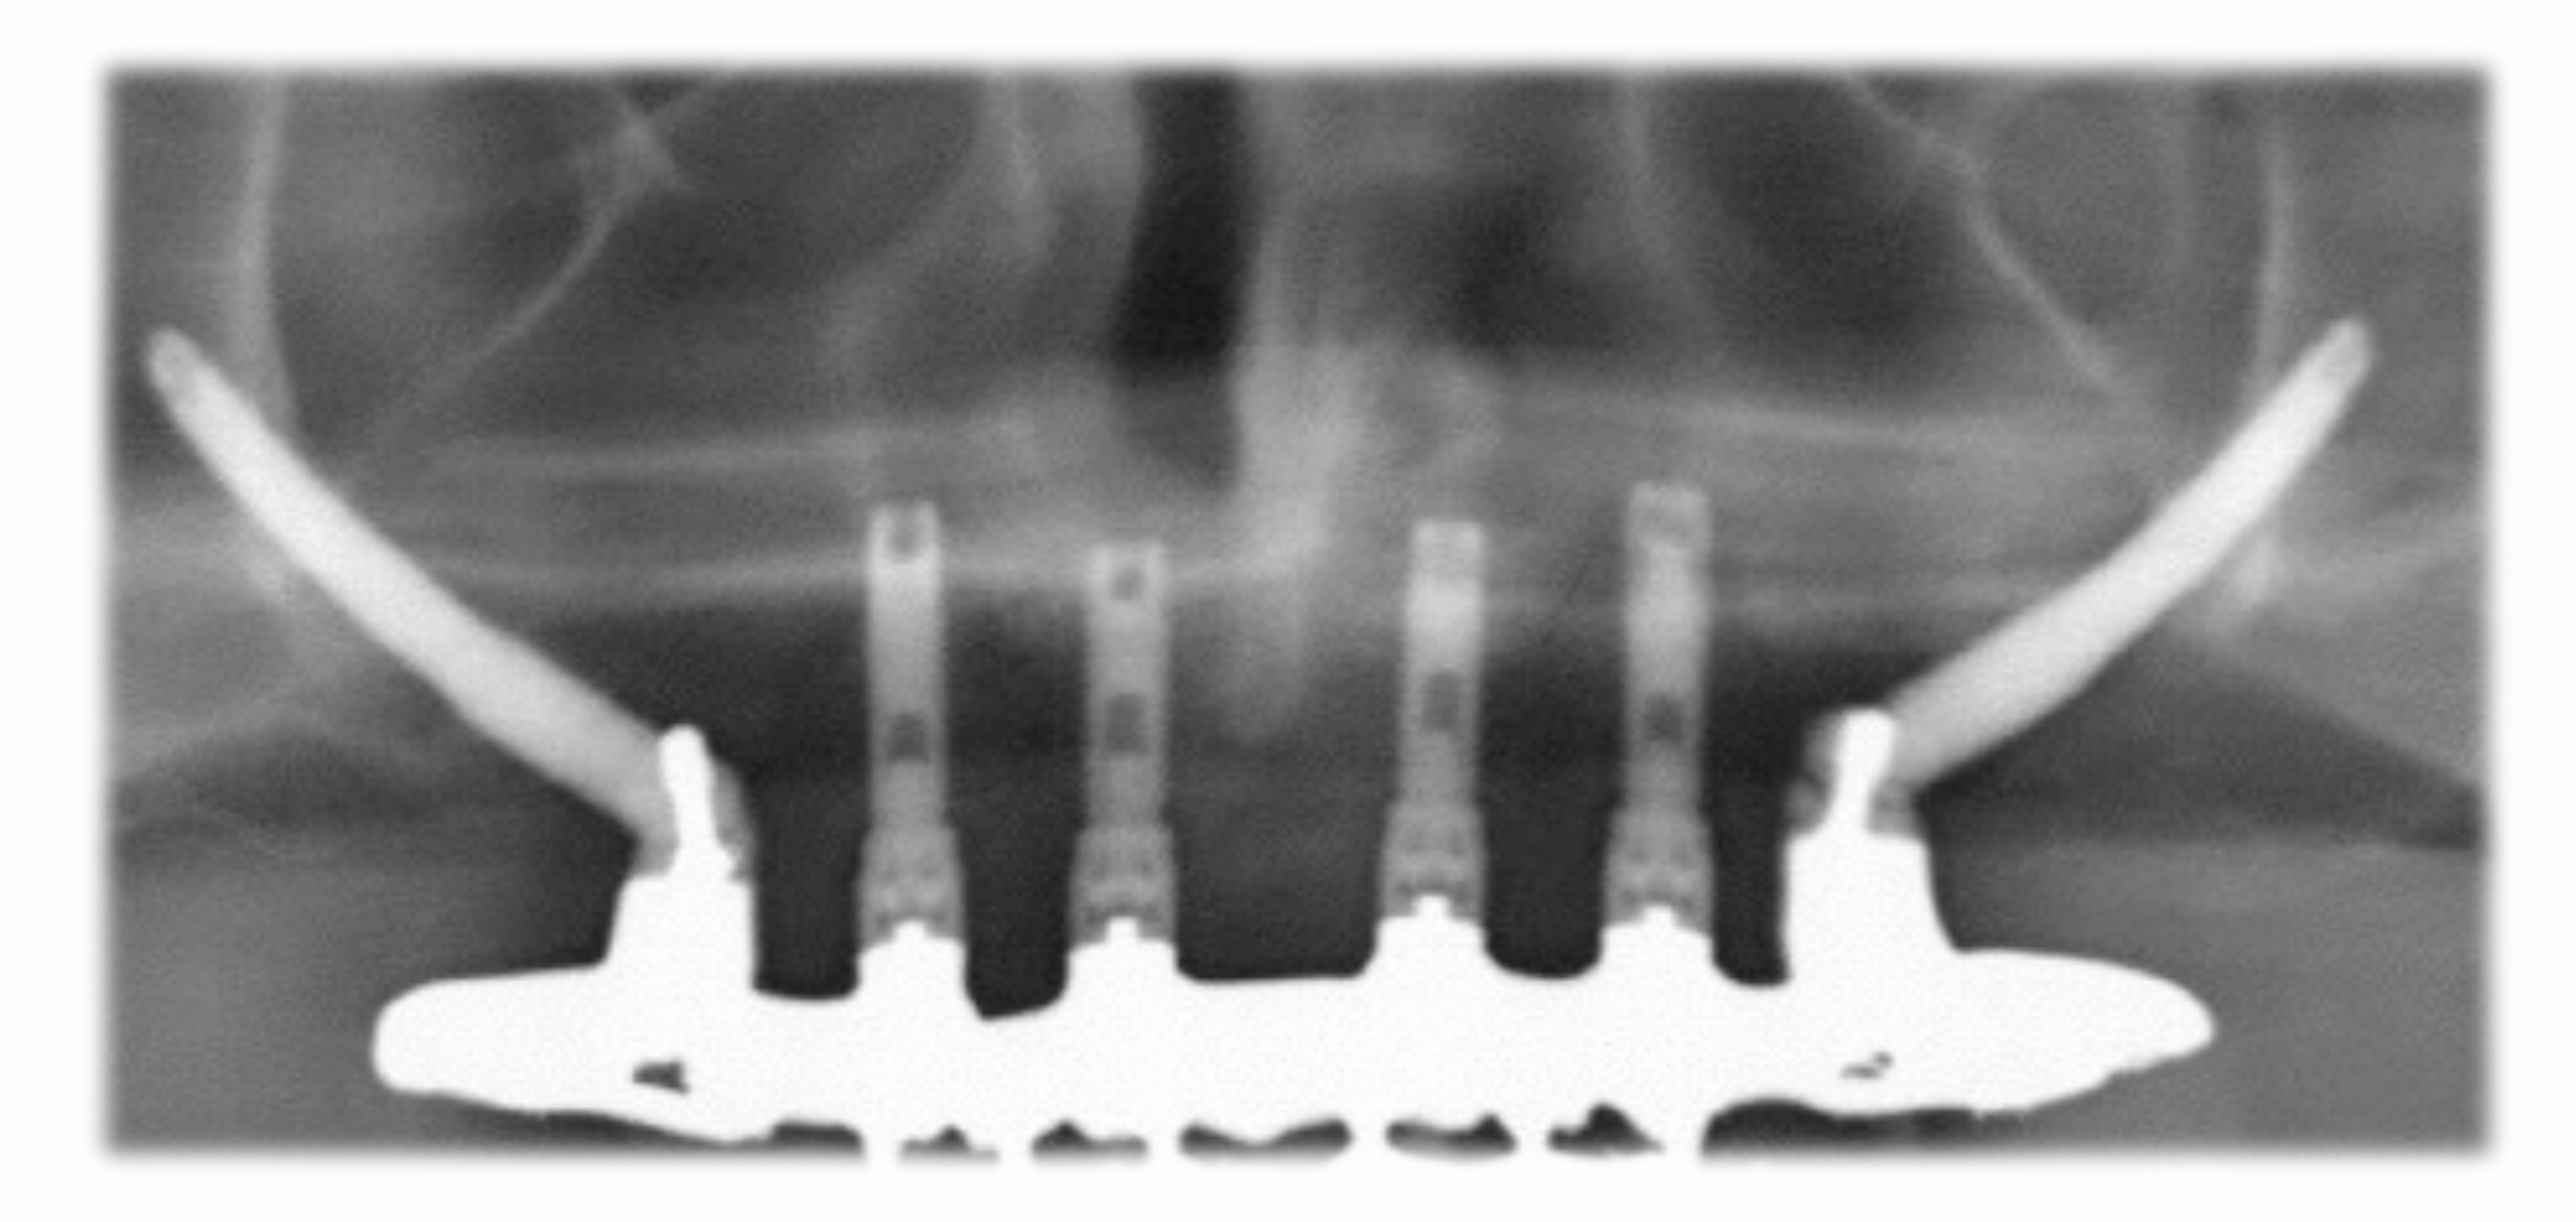
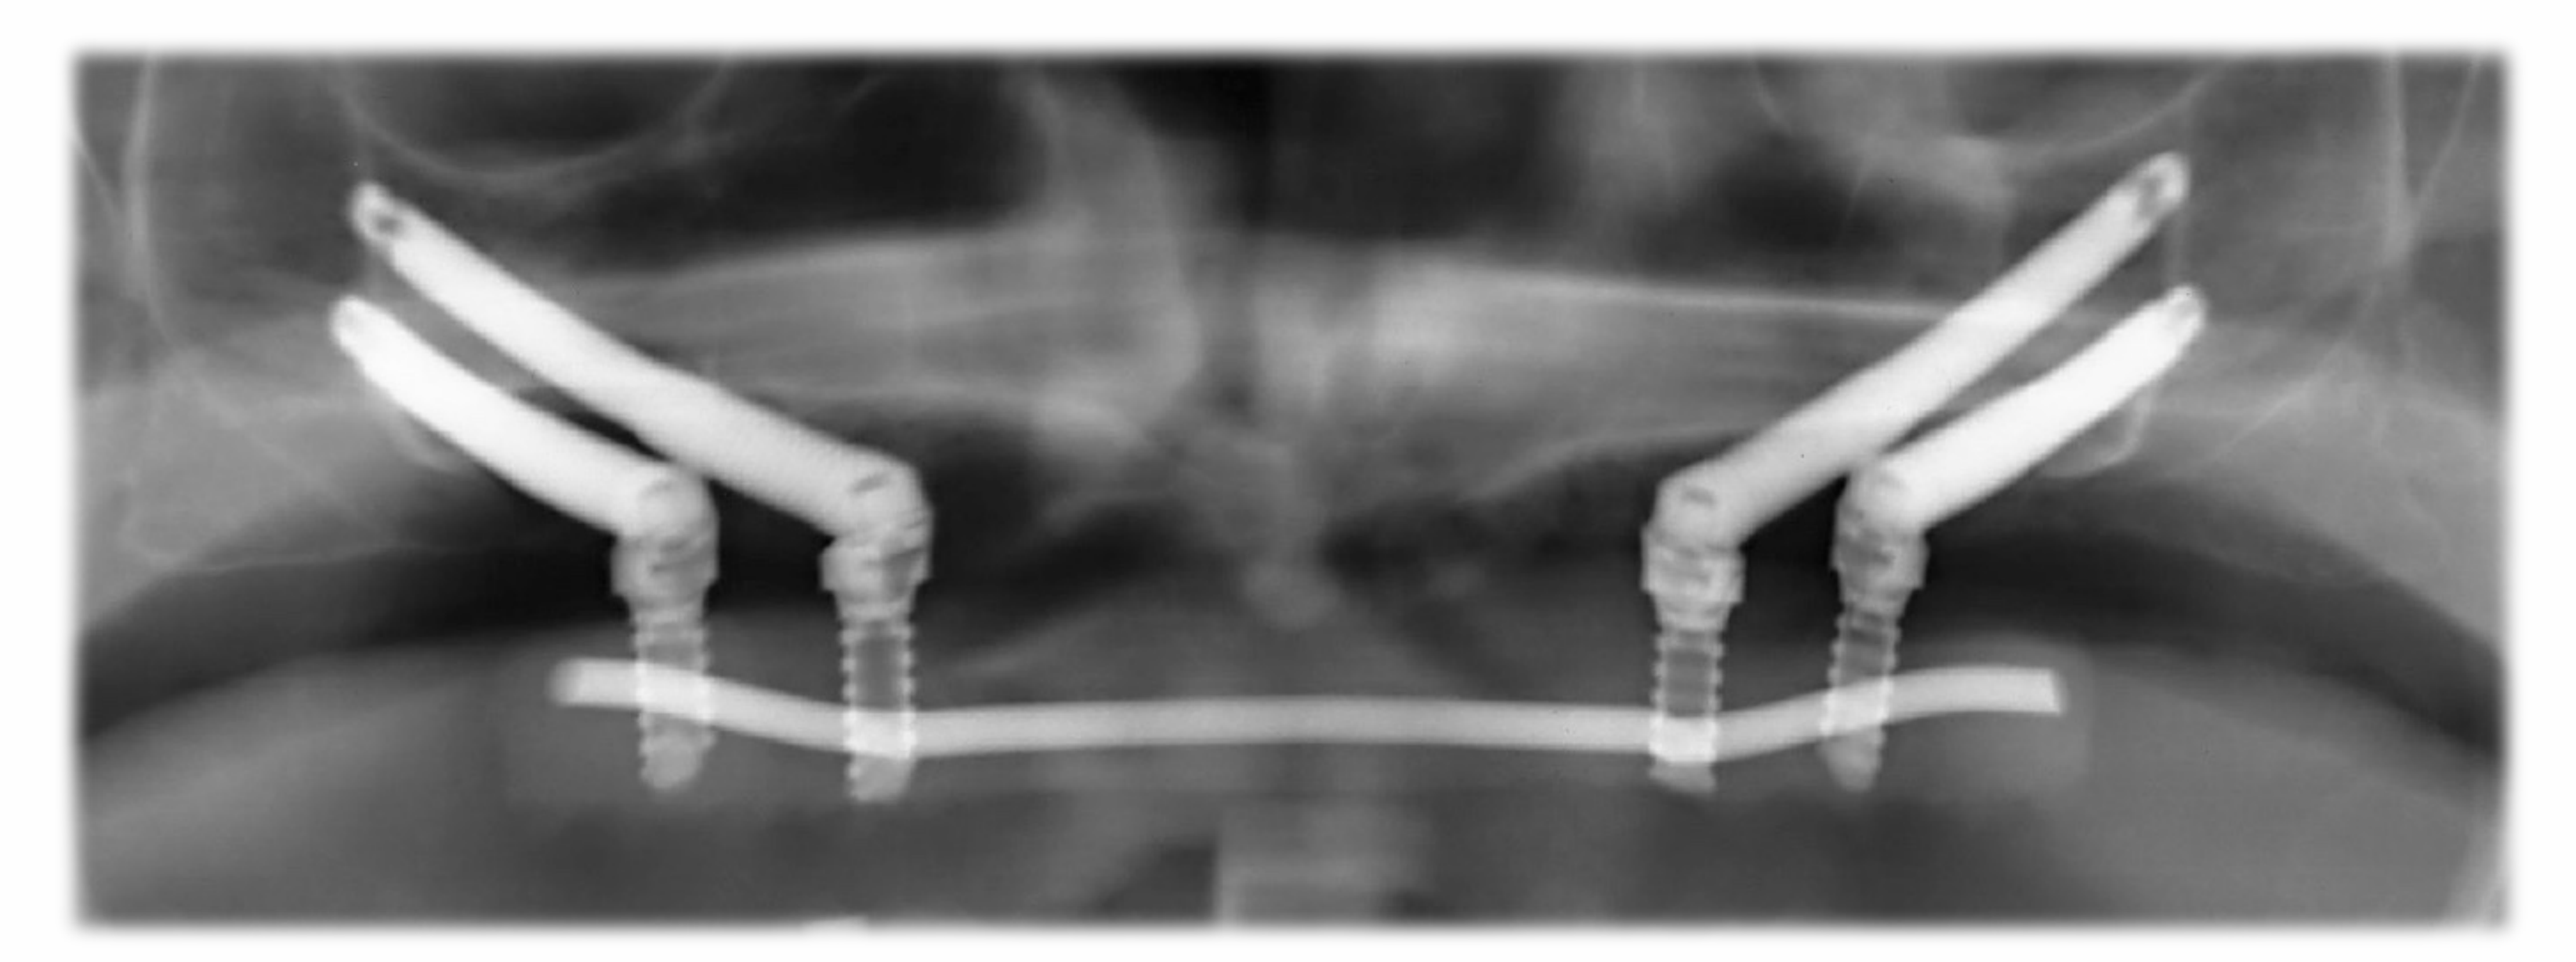
Maxillary Zone Distribution68
- Zone 3
- Zone 2
- Zone 1
Bedrossian E, Sullivan RM, Fortin Y, Malo P, Indresano T. Fixed-prosthetic implant restoration of the edentulous maxilla: a systematic pretreatment evaluation method. J Oral Maxillofac Surg. 2008;66(1):112-22.
Ridge Reduction and Implant Length697071
Ridge reduction affects implant length and AP spread.
Ridge reduction affects implant length and AP spread.
Maló P, Nobre Md, Lopes A. Immediate loading of ‘All-on-4’ maxillary prostheses using trans-sinus tilted implants without sinus bone grafting: a retrospective study reporting the 3-year outcome. Eur J Oral Implantol. 2013;6(3):273-83.
- Zone 1
- Zone 2
- Zone 3
- Zone 2
- Zone 3
Goiato MC, Pellizzer EP, Moreno A, Gennari-Filho H, dos Santos DM, Santiago JF Jr, dos Santos EG. Implants in the zygomatic bone for maxillary prosthetic rehabilitation: a systematic review. Int J Oral Maxillofac Surg. 2014;43(6):748-57.
Home Care and Cleansibility72
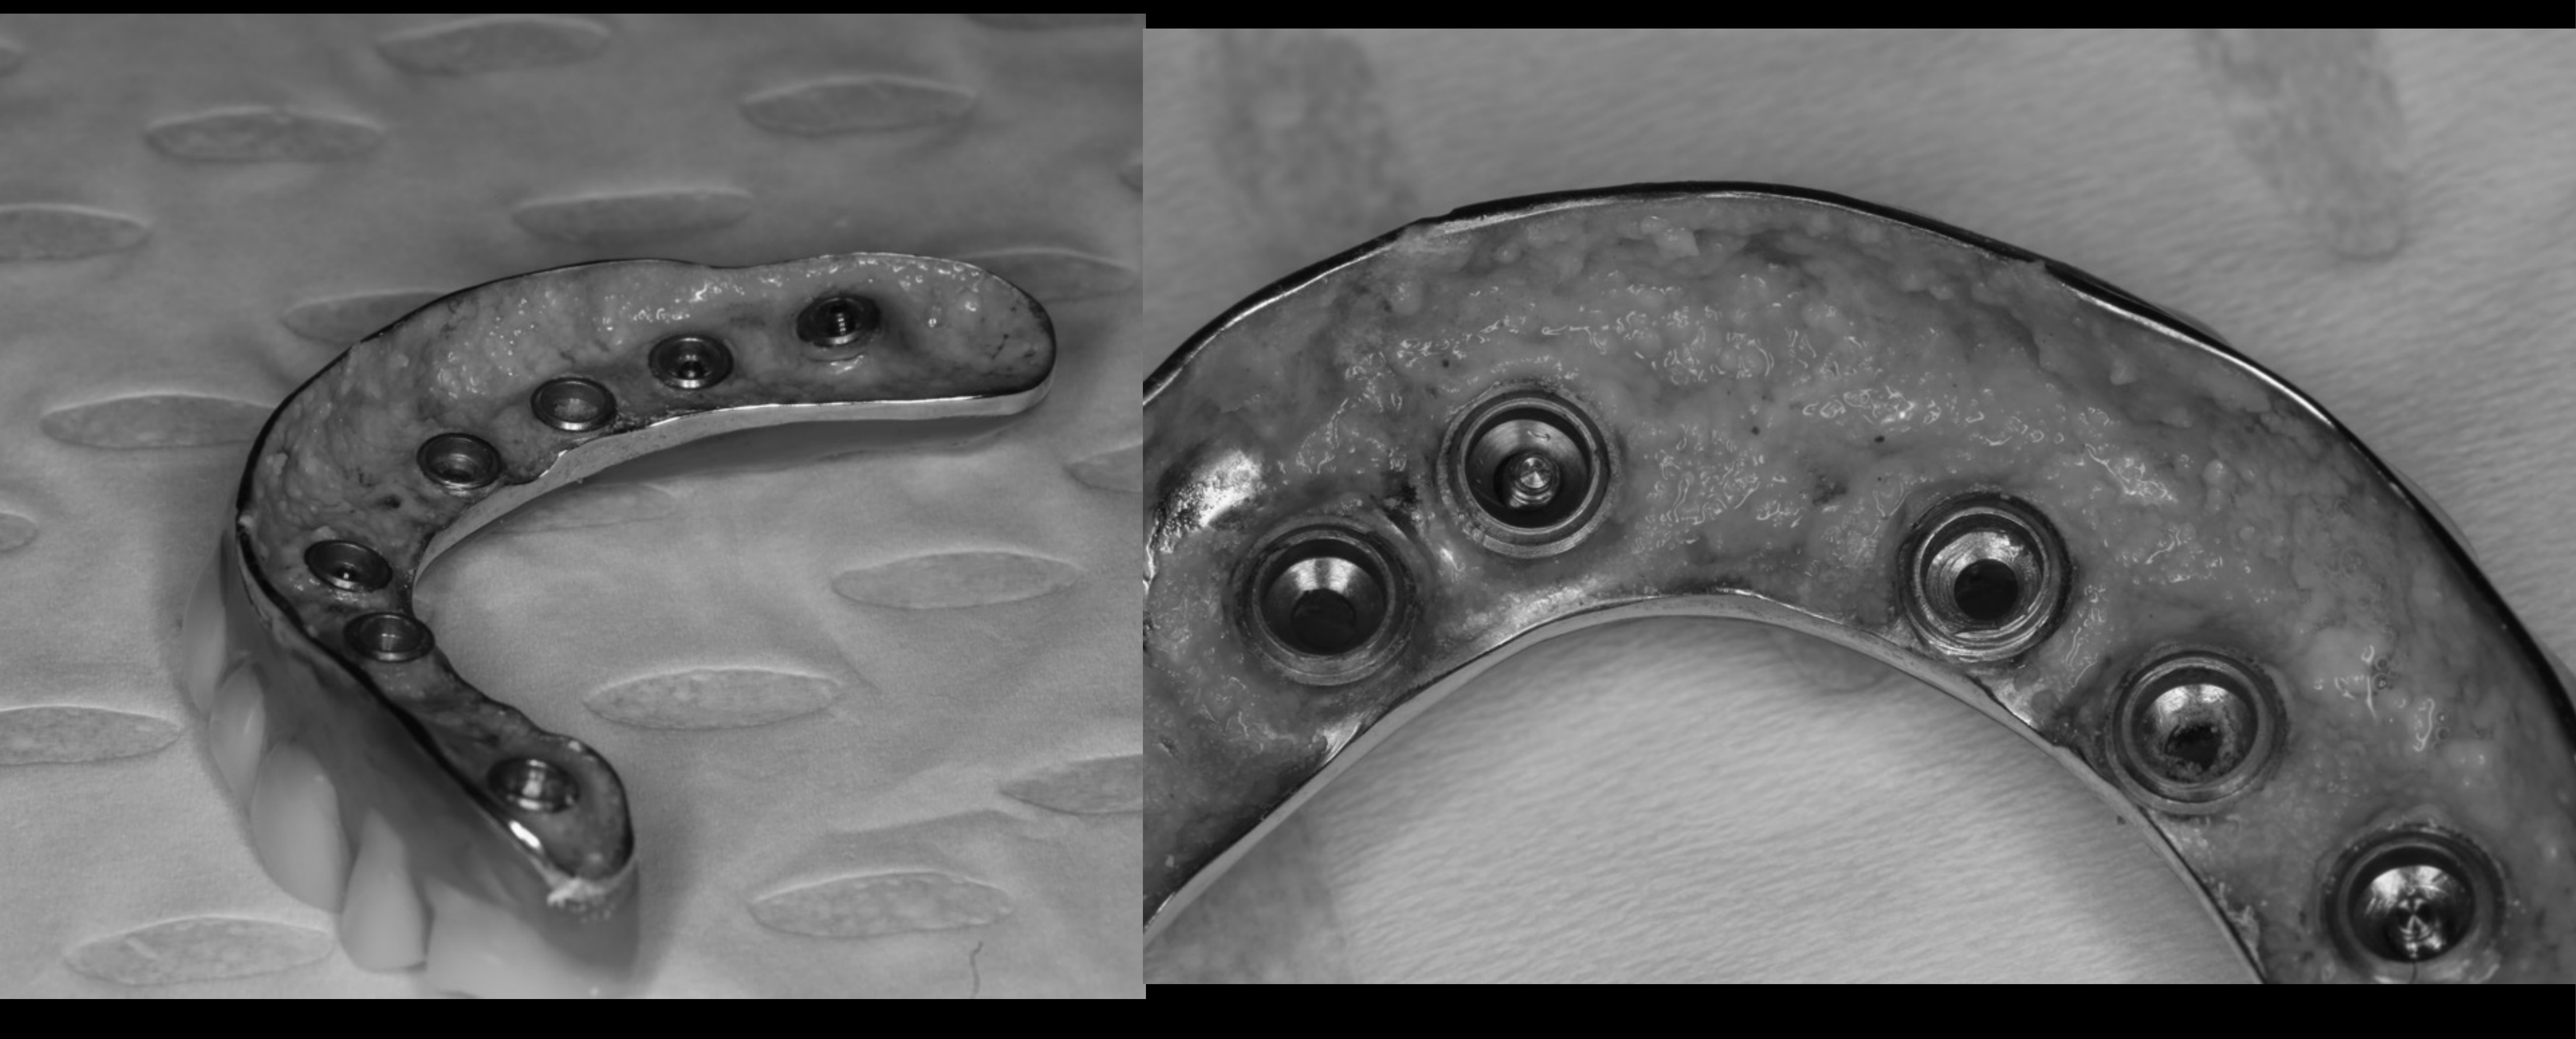
Patient Aids73
 | 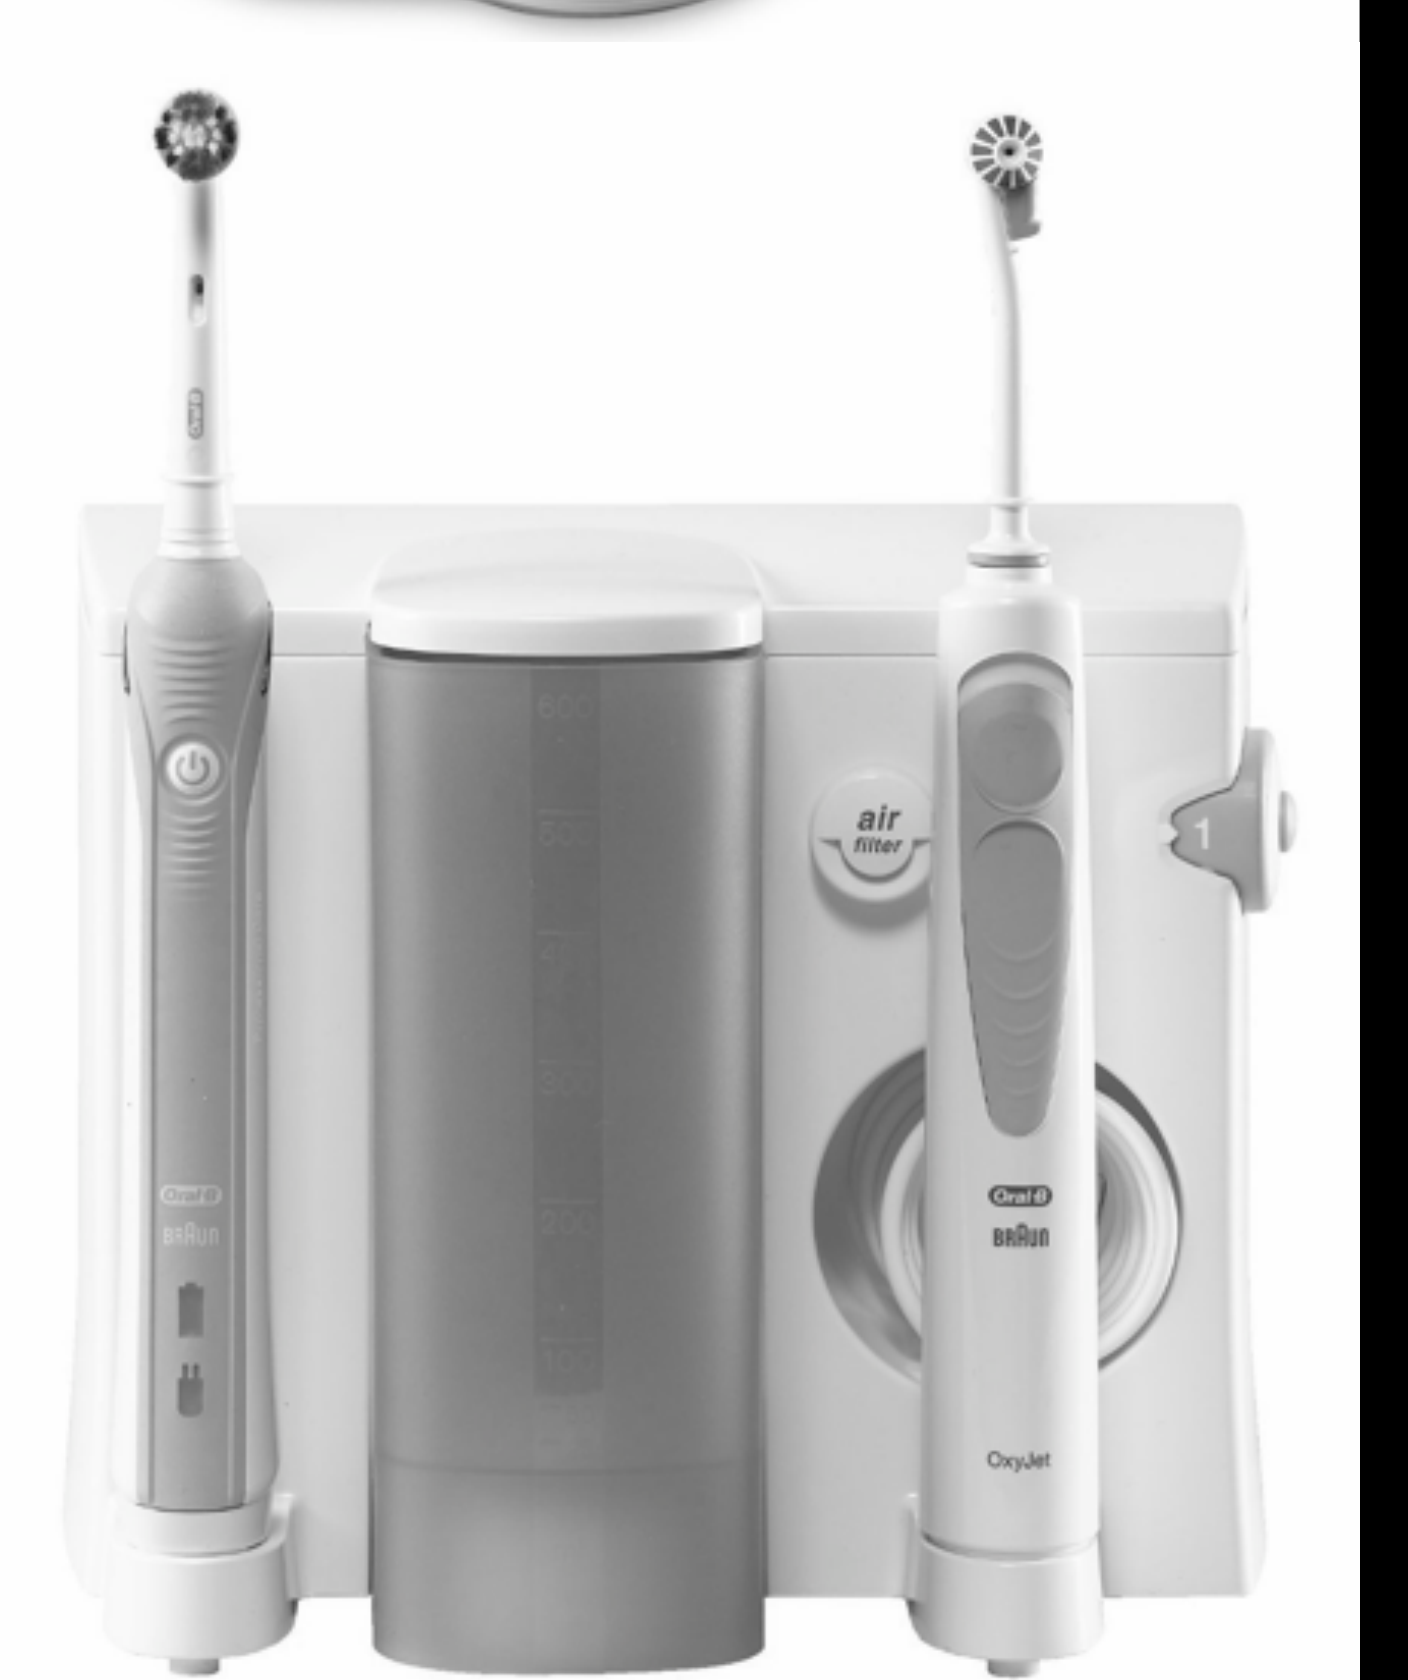 |
Cleansibility74
- Convex tissue fitting surface
Centrix® – Point of clinical excellence® (Centrix.com)
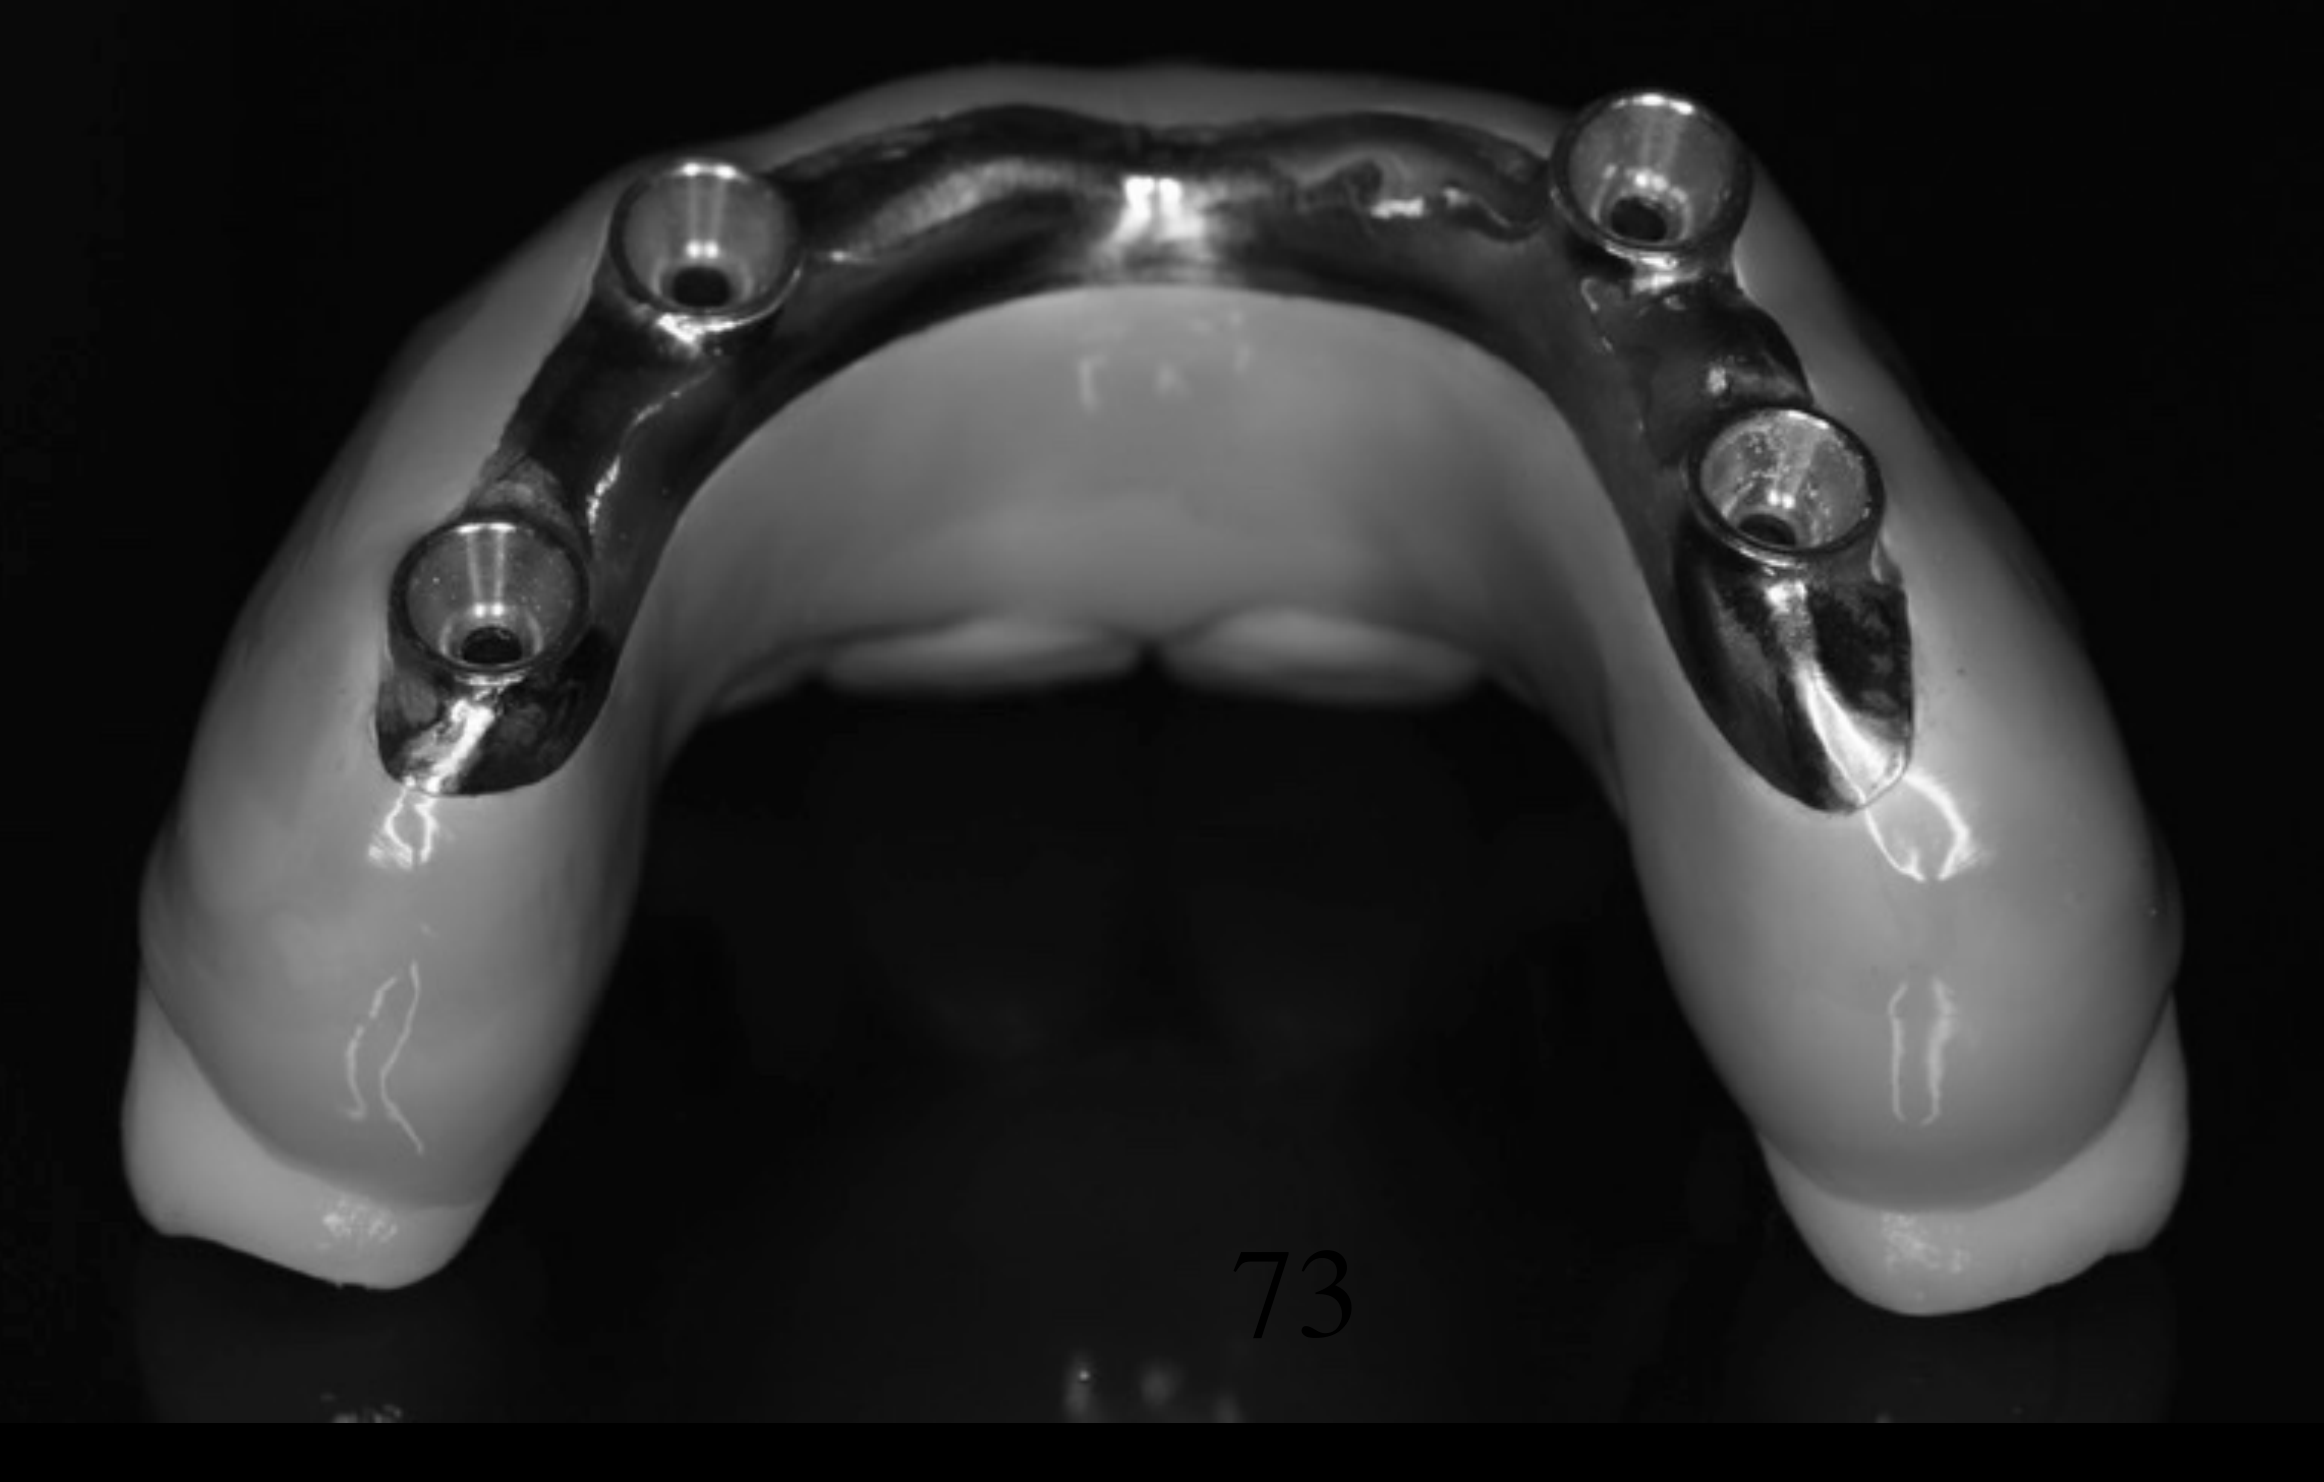
Definitive Bridge Options
Considerations by Arch75
- Mandible: Acrylic resin
- Maxilla: More wear resistant — ceramic if possible
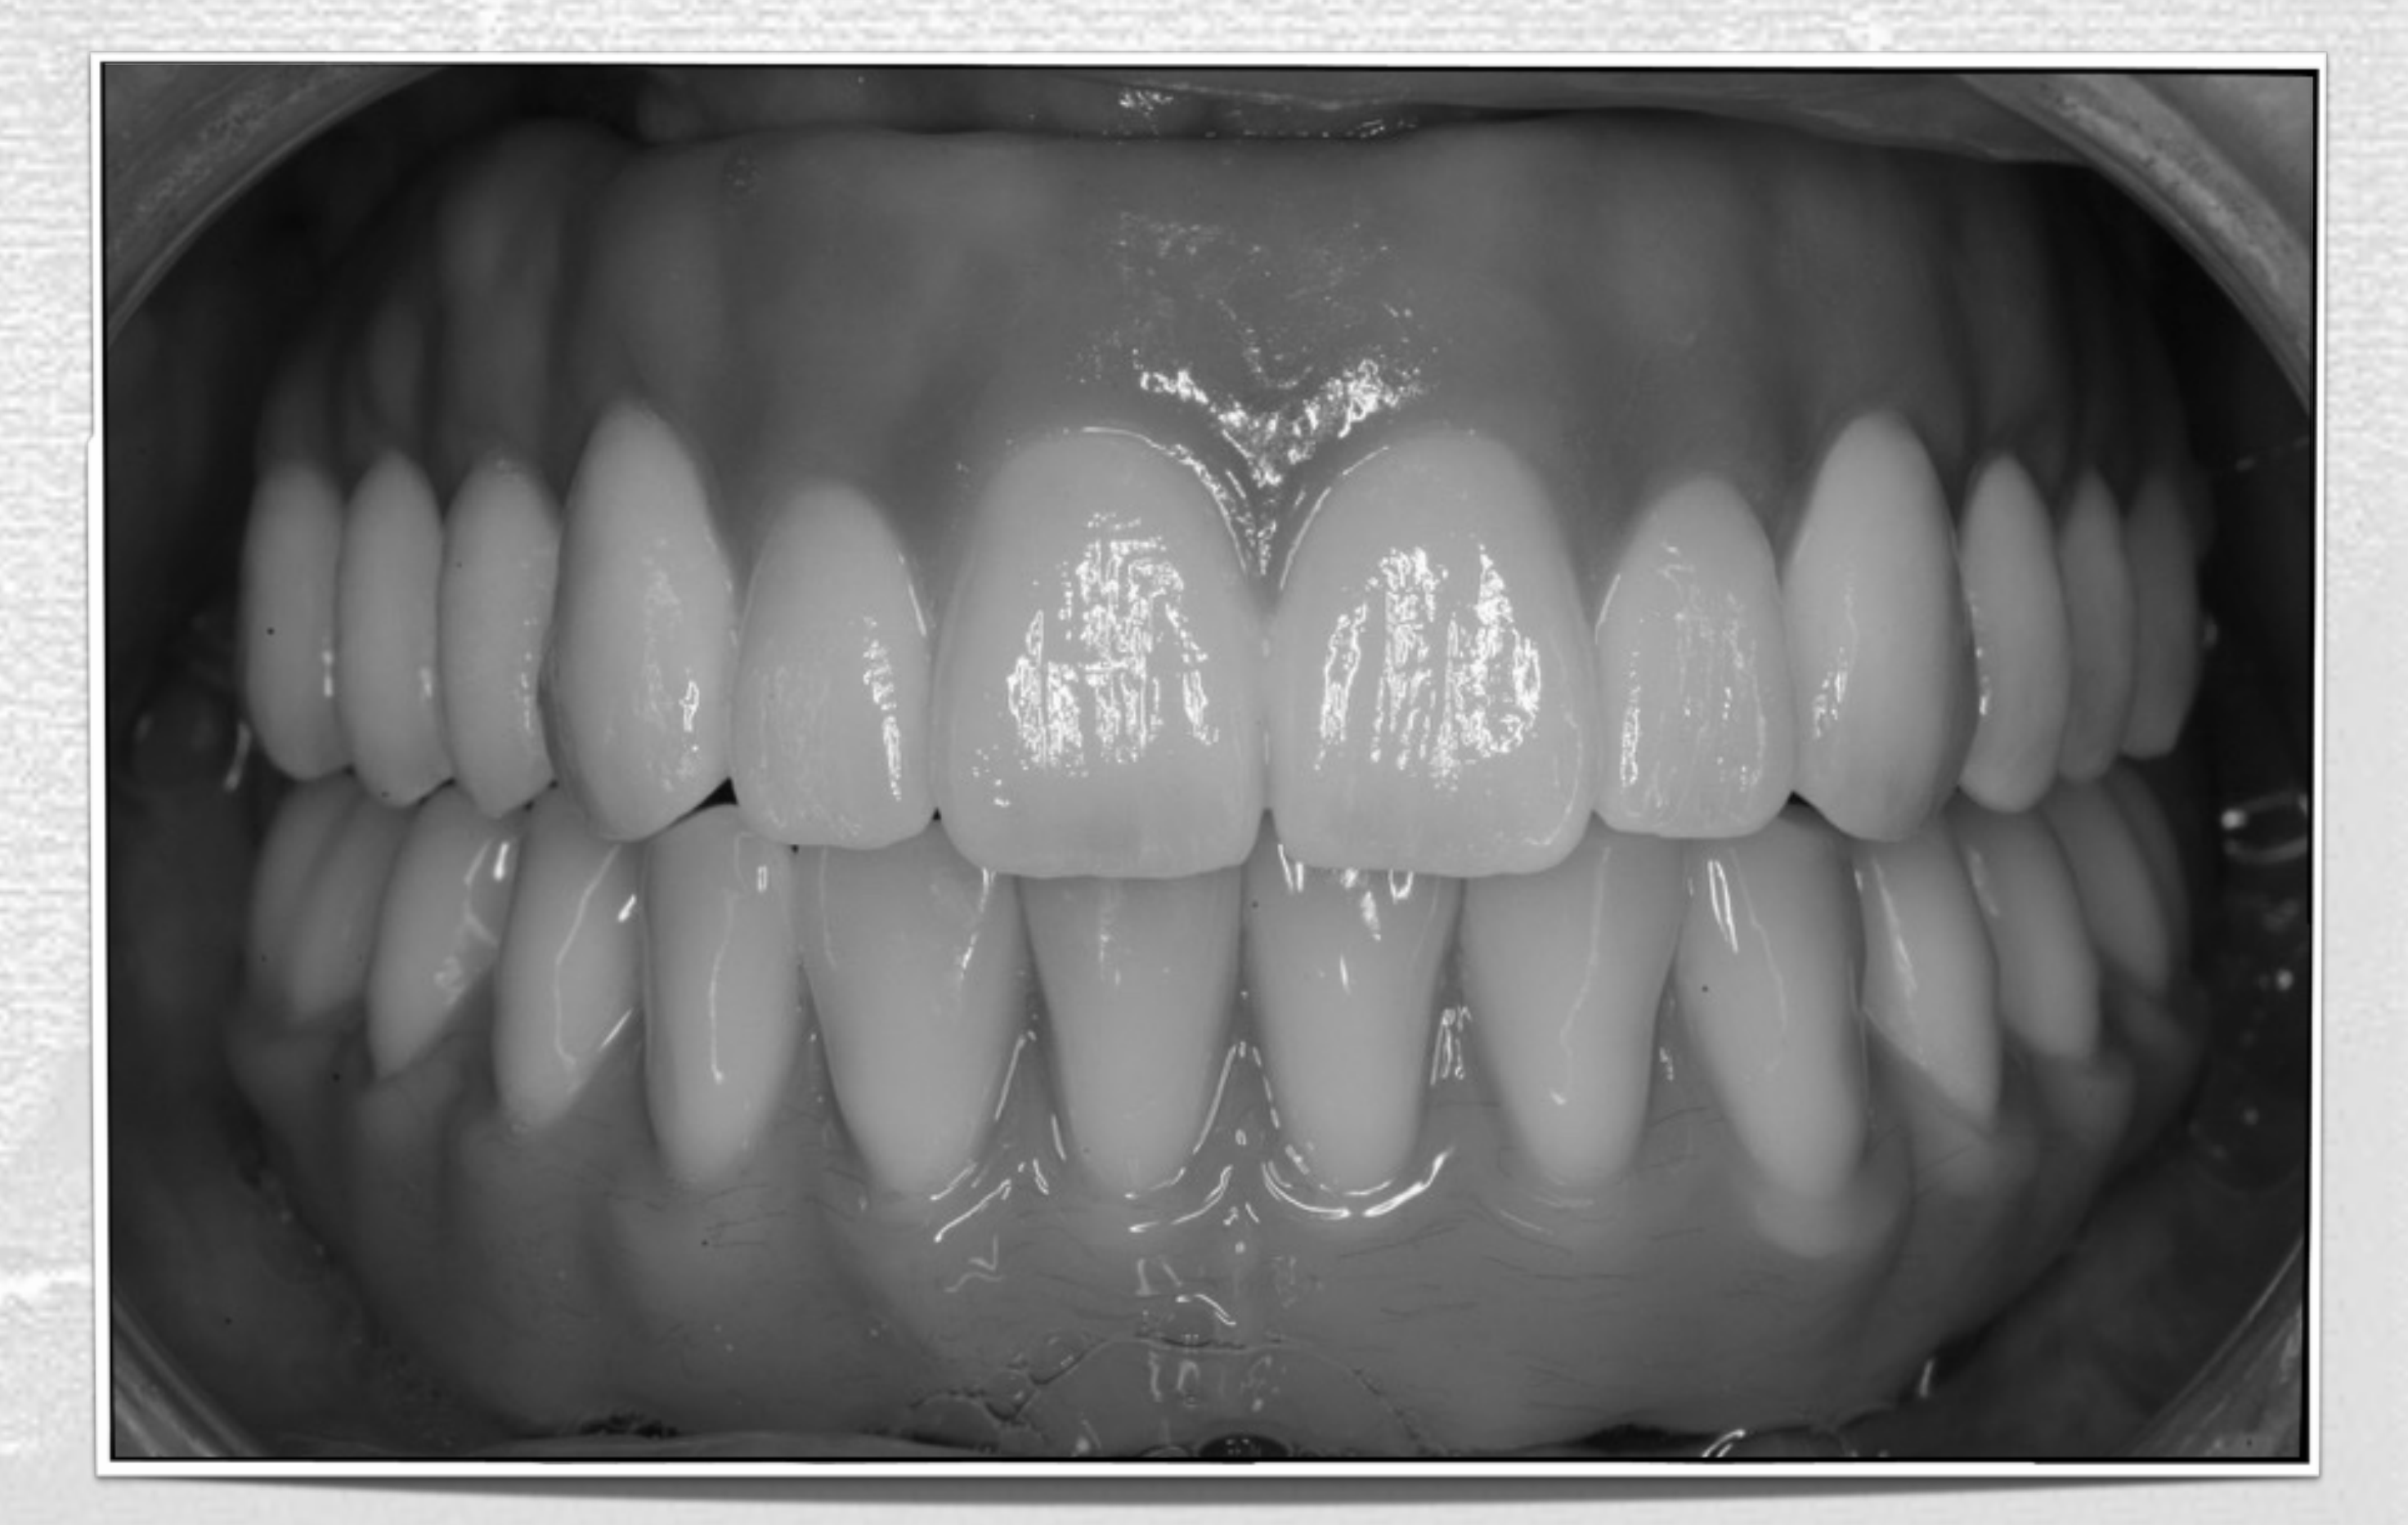
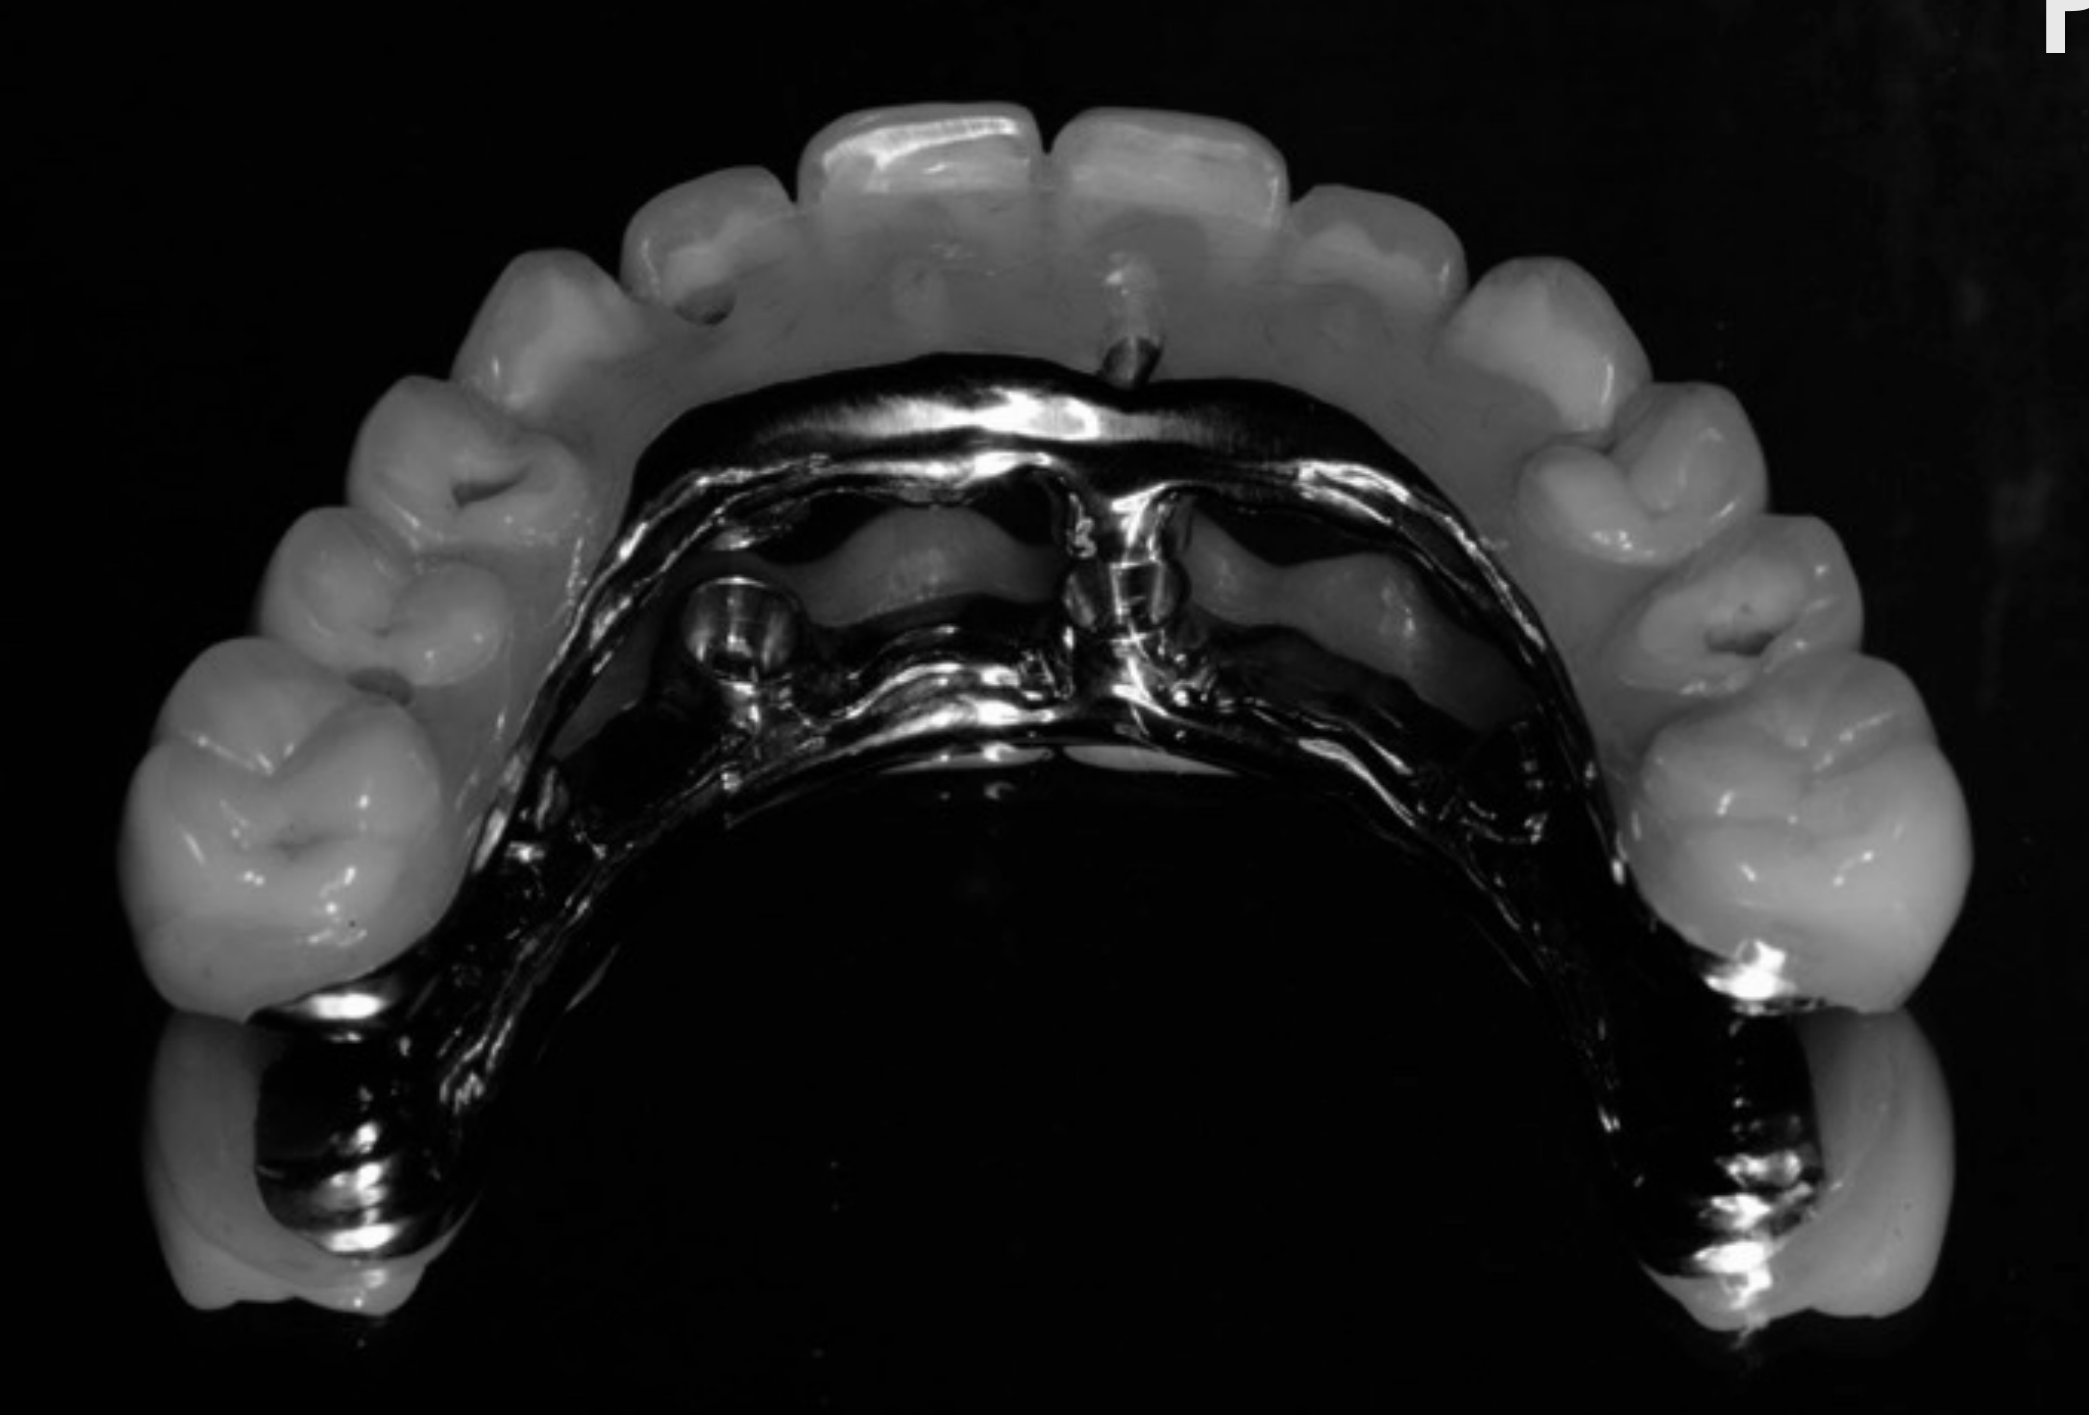
Maxillary Bridge Options
Procera Titanium Hybrid with Acrylic Teeth7677
- Maintenance is medium, but relatively easy to fix
- Retread required every 5–7 years for wear
- Staining around margins
- Acrylic resin fractures
- Tooth fractures
- Need occlusal splint
Severe Bruxism
Torsello F, di Torresanto VM, Ercoli C, Cordaro L. Evaluation of the marginal precision of one-piece complete arch titanium frameworks fabricated using five different methods for implant-supported restorations. Clin Oral Implants Res. 2008;19(8):772-9.
Hjalmarsson L, Örtorp A, Smedberg JI, Jemt T. Precision of fit to implants: a comparison of Cresco™ and Procera® implant bridge frameworks. Clin Implant Dent Relat Res. 2010;12(4):271-80.
 | 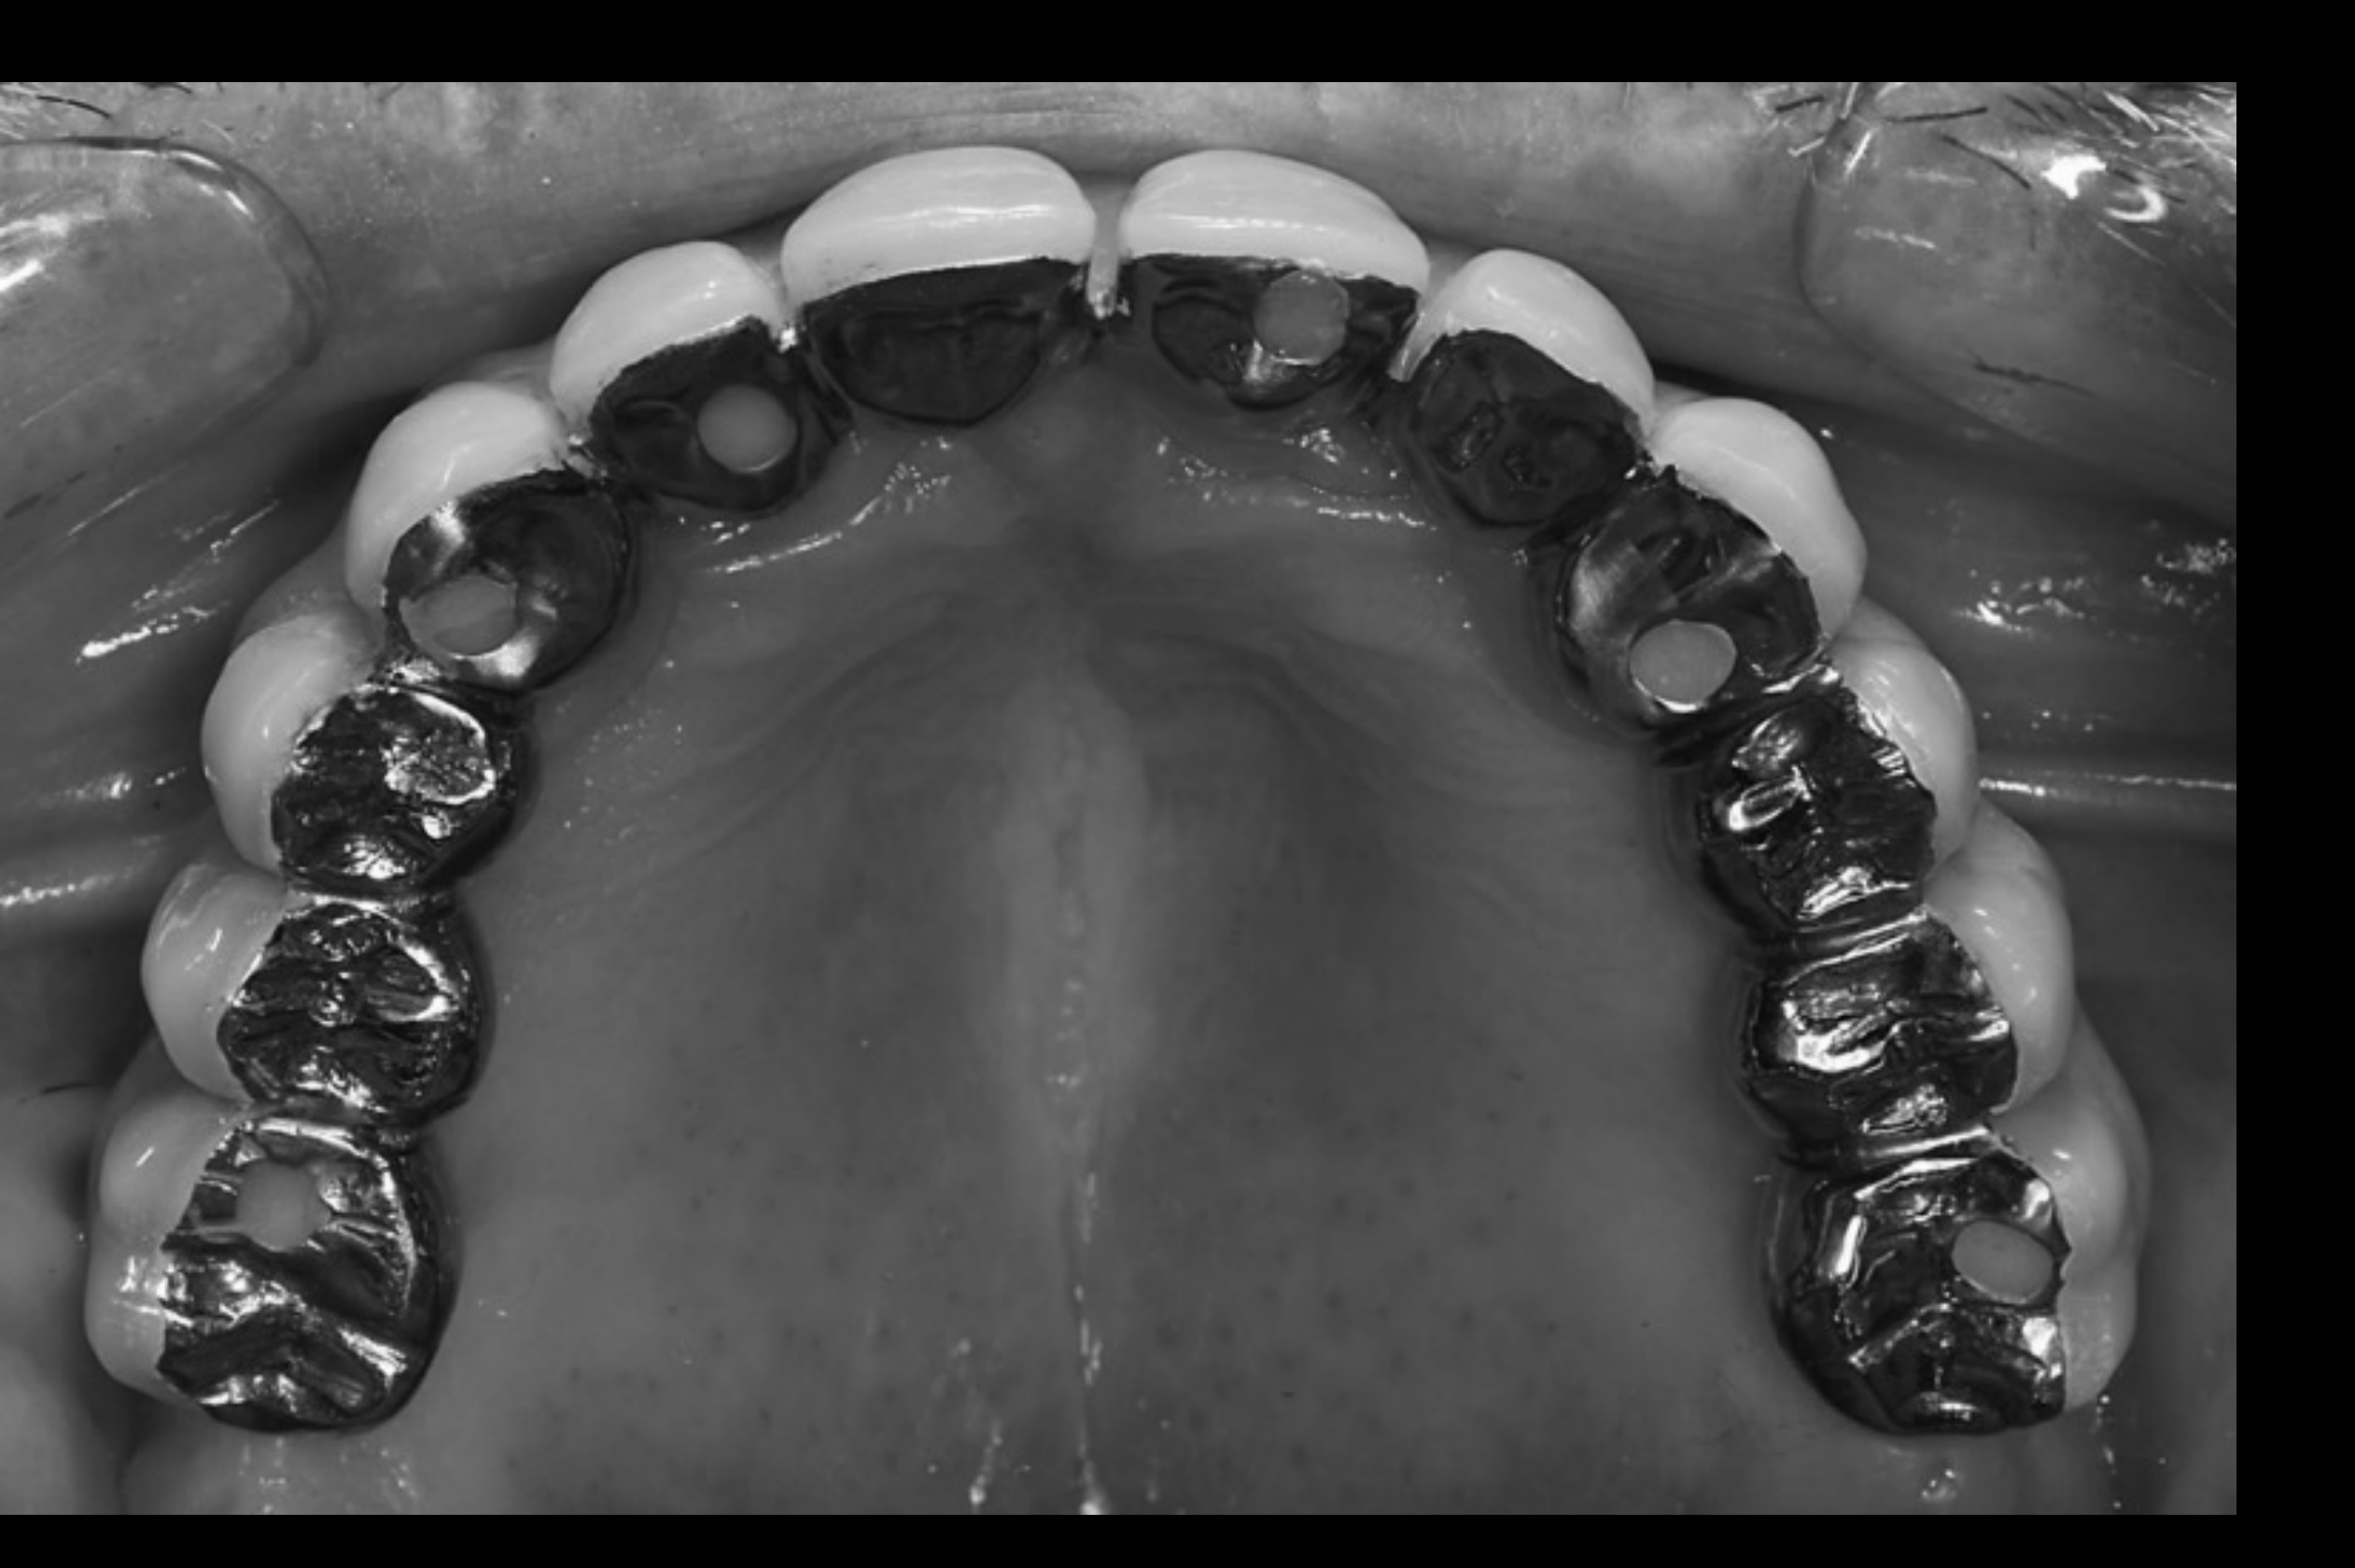 |
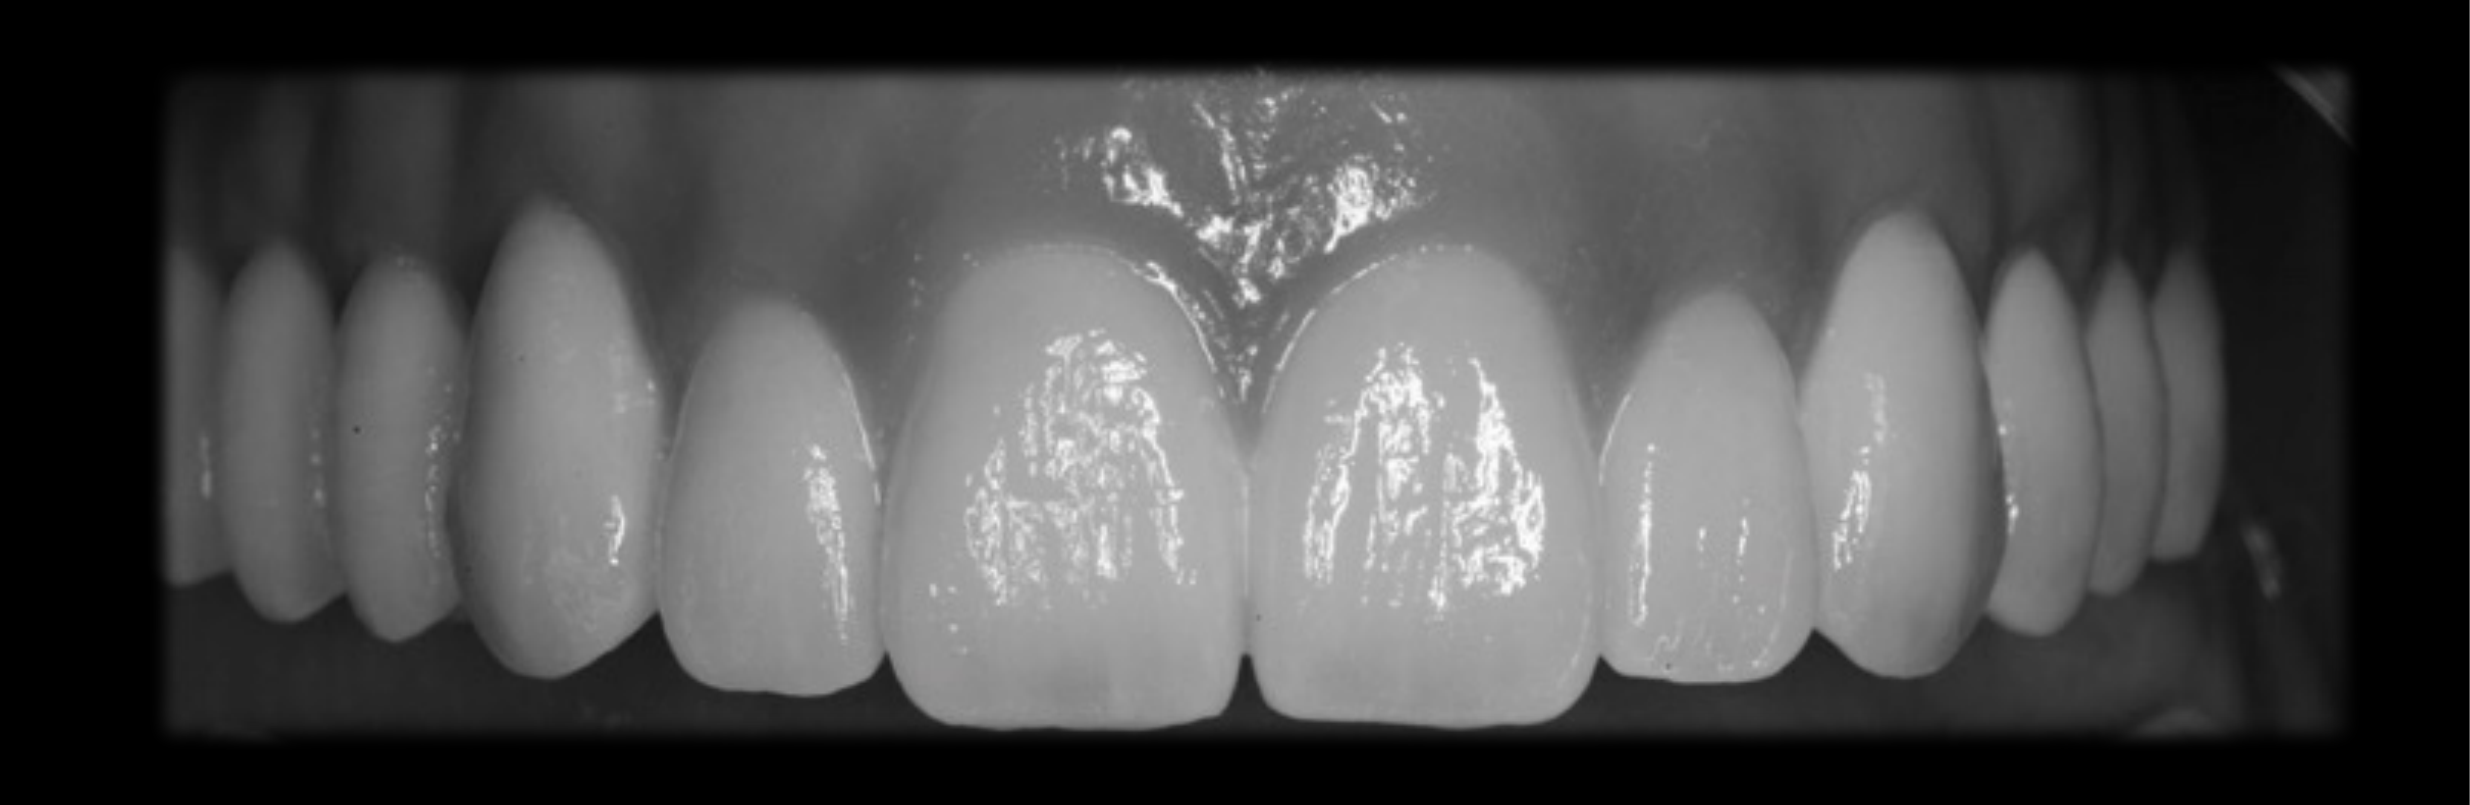
PFM – Gold Cemented Framework78
- Gold prices are getting crazy — US$11K for this one!
- Maintenance is low, but expensive and difficult to fix
 | 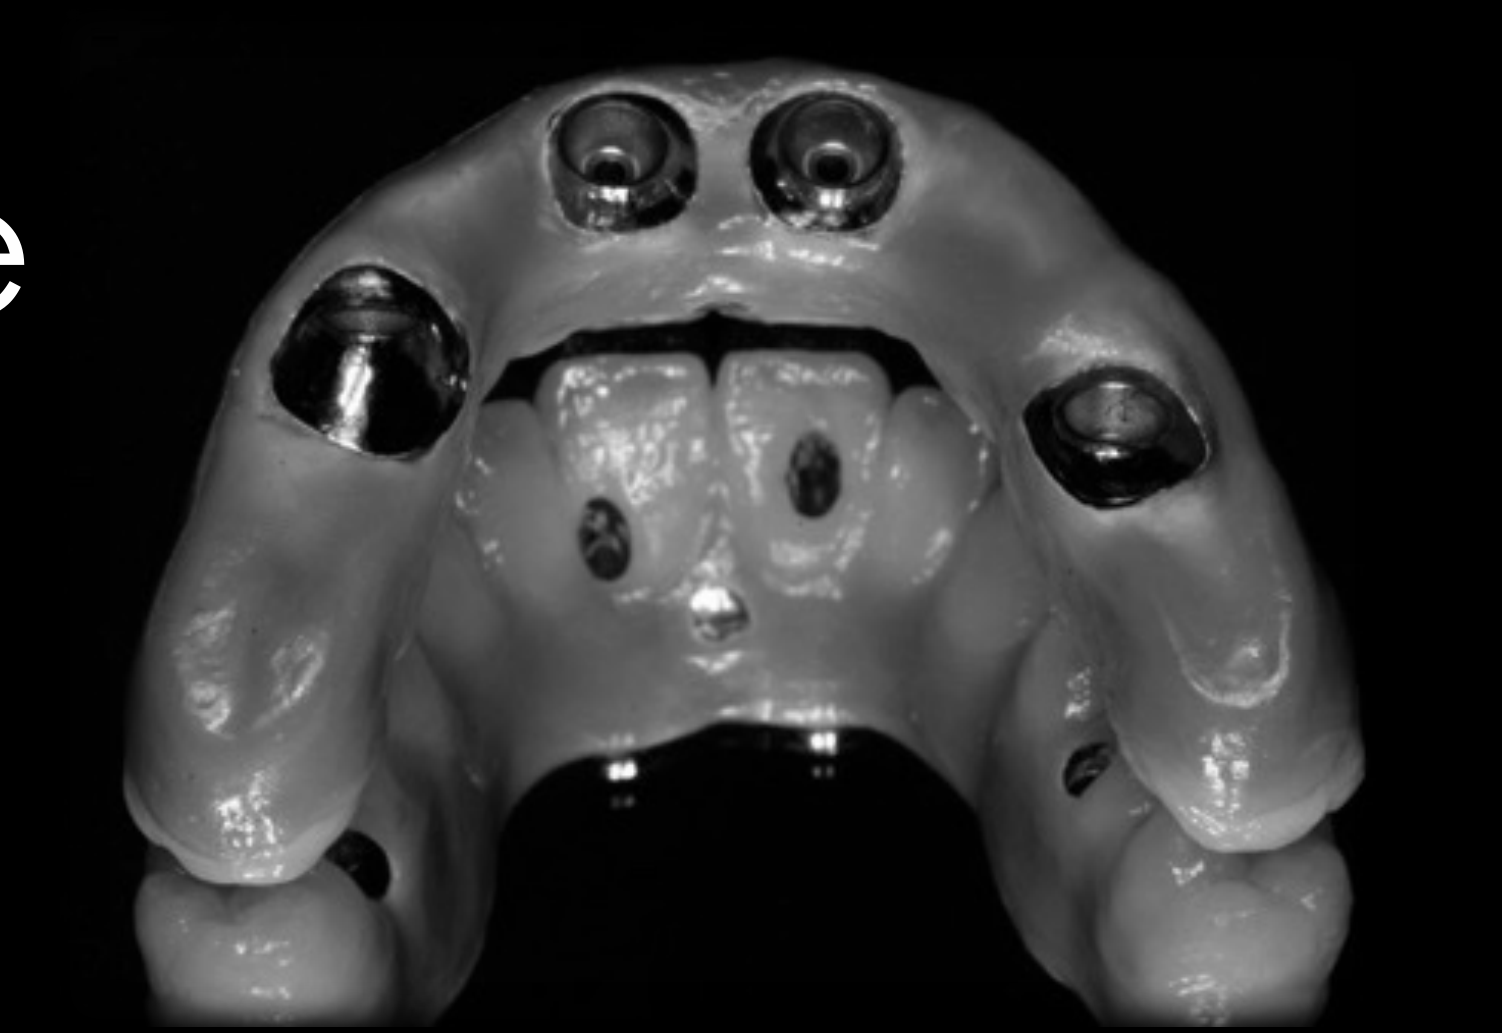 |
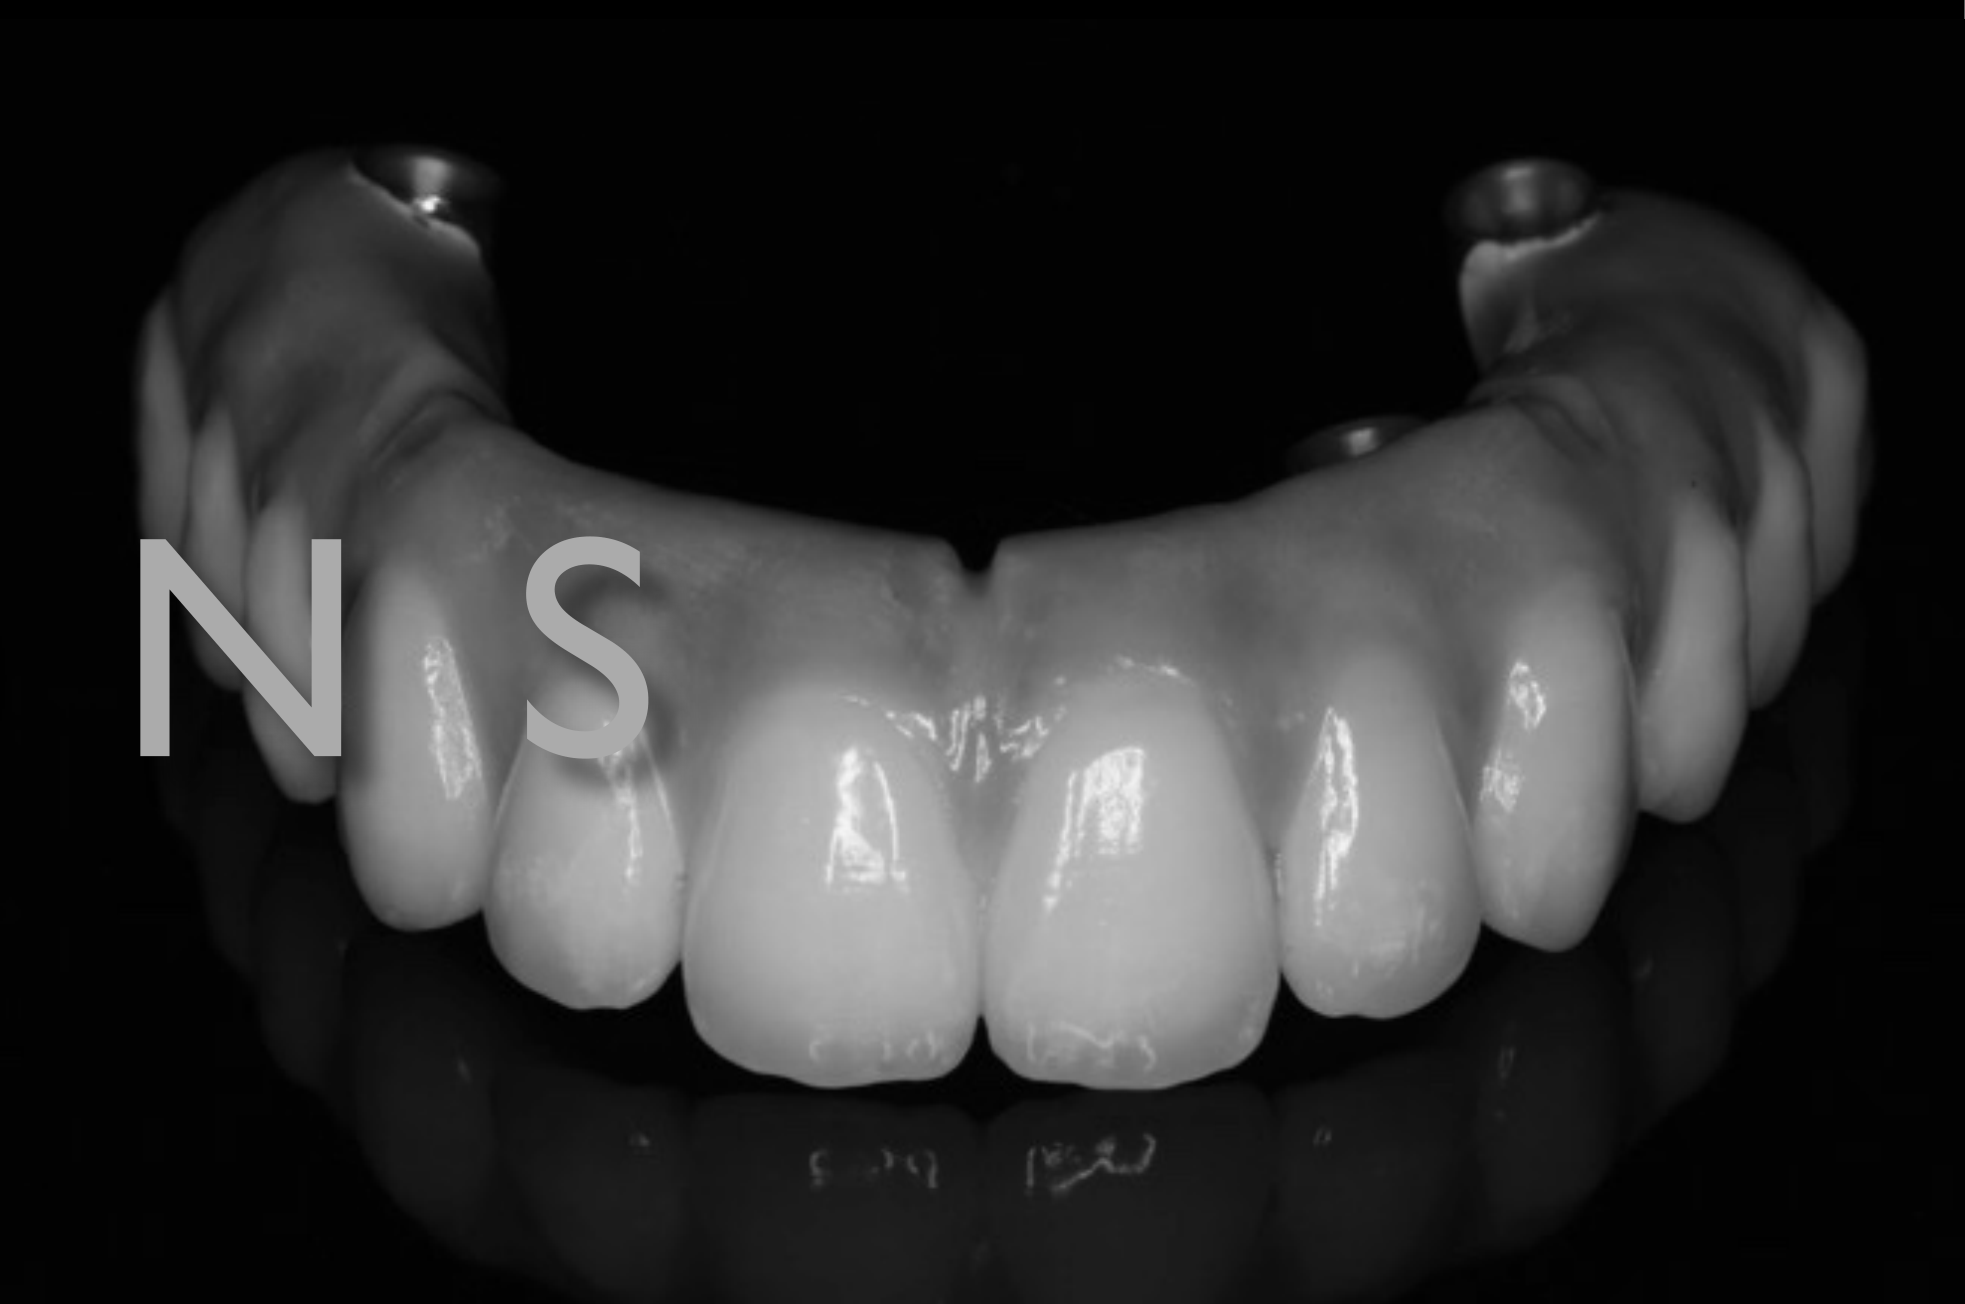
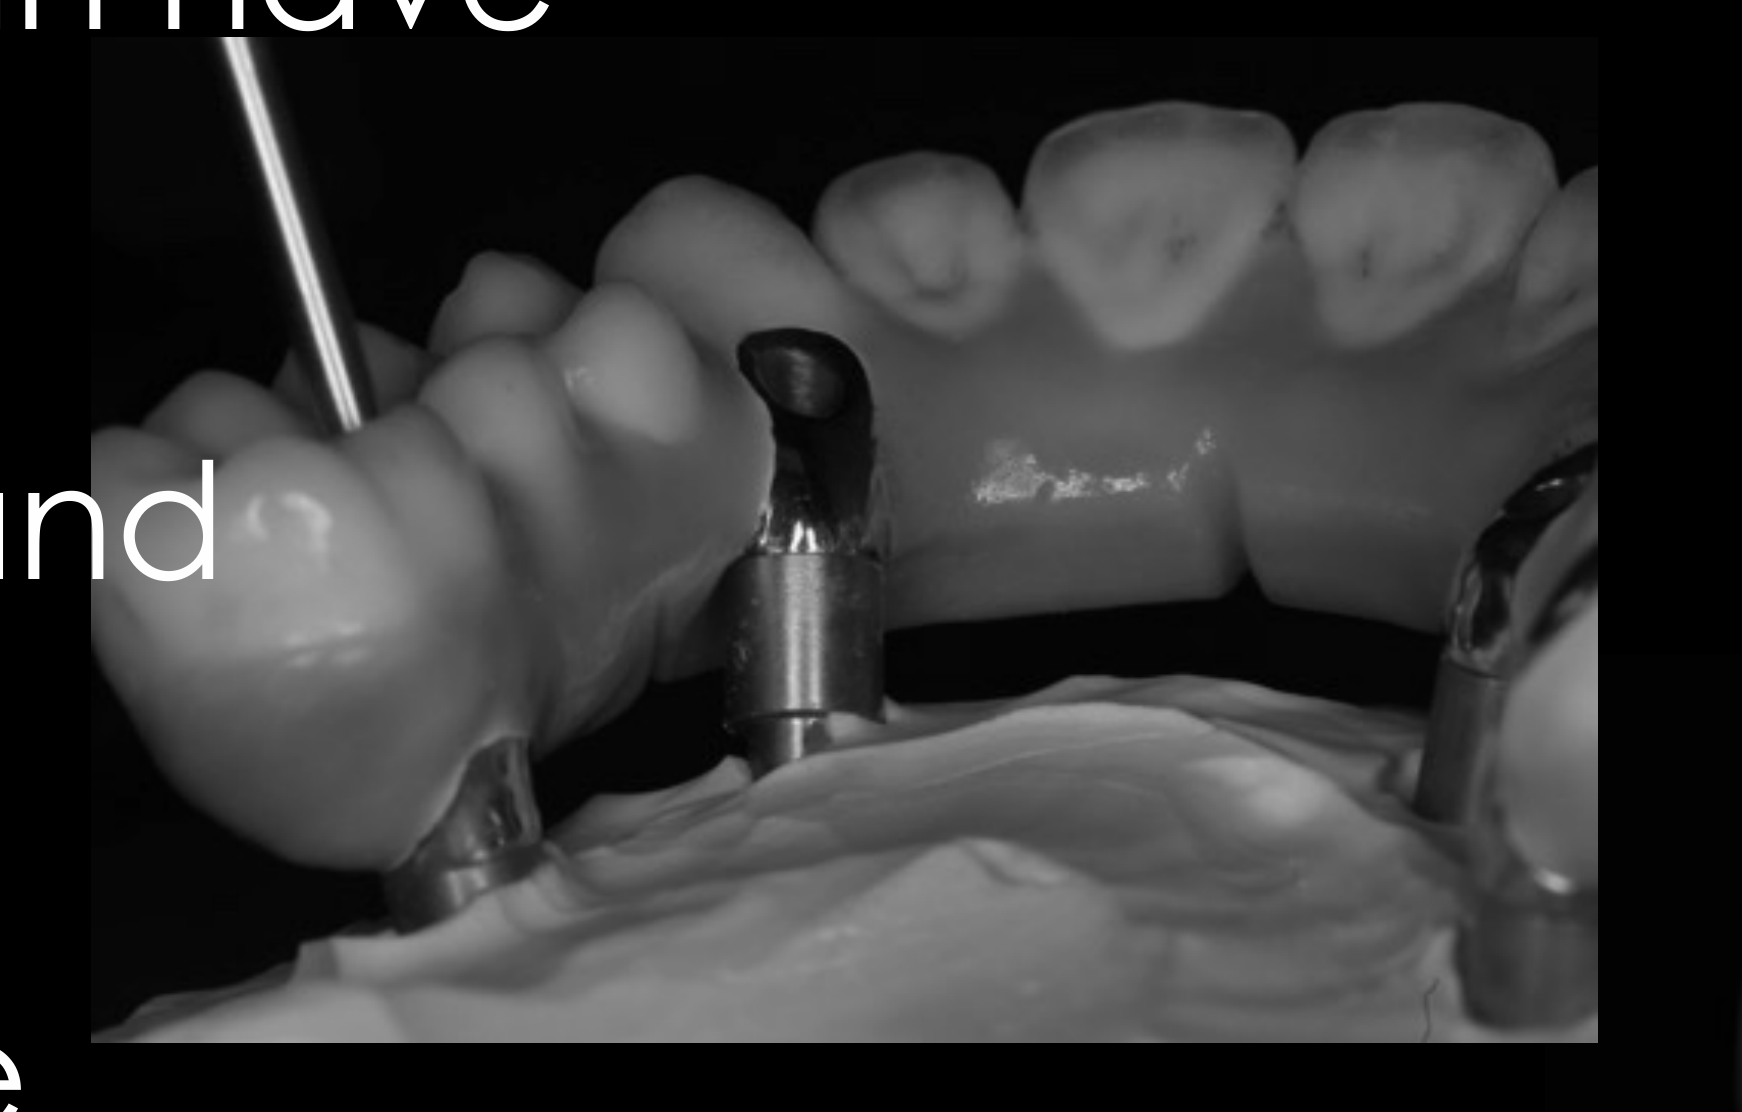
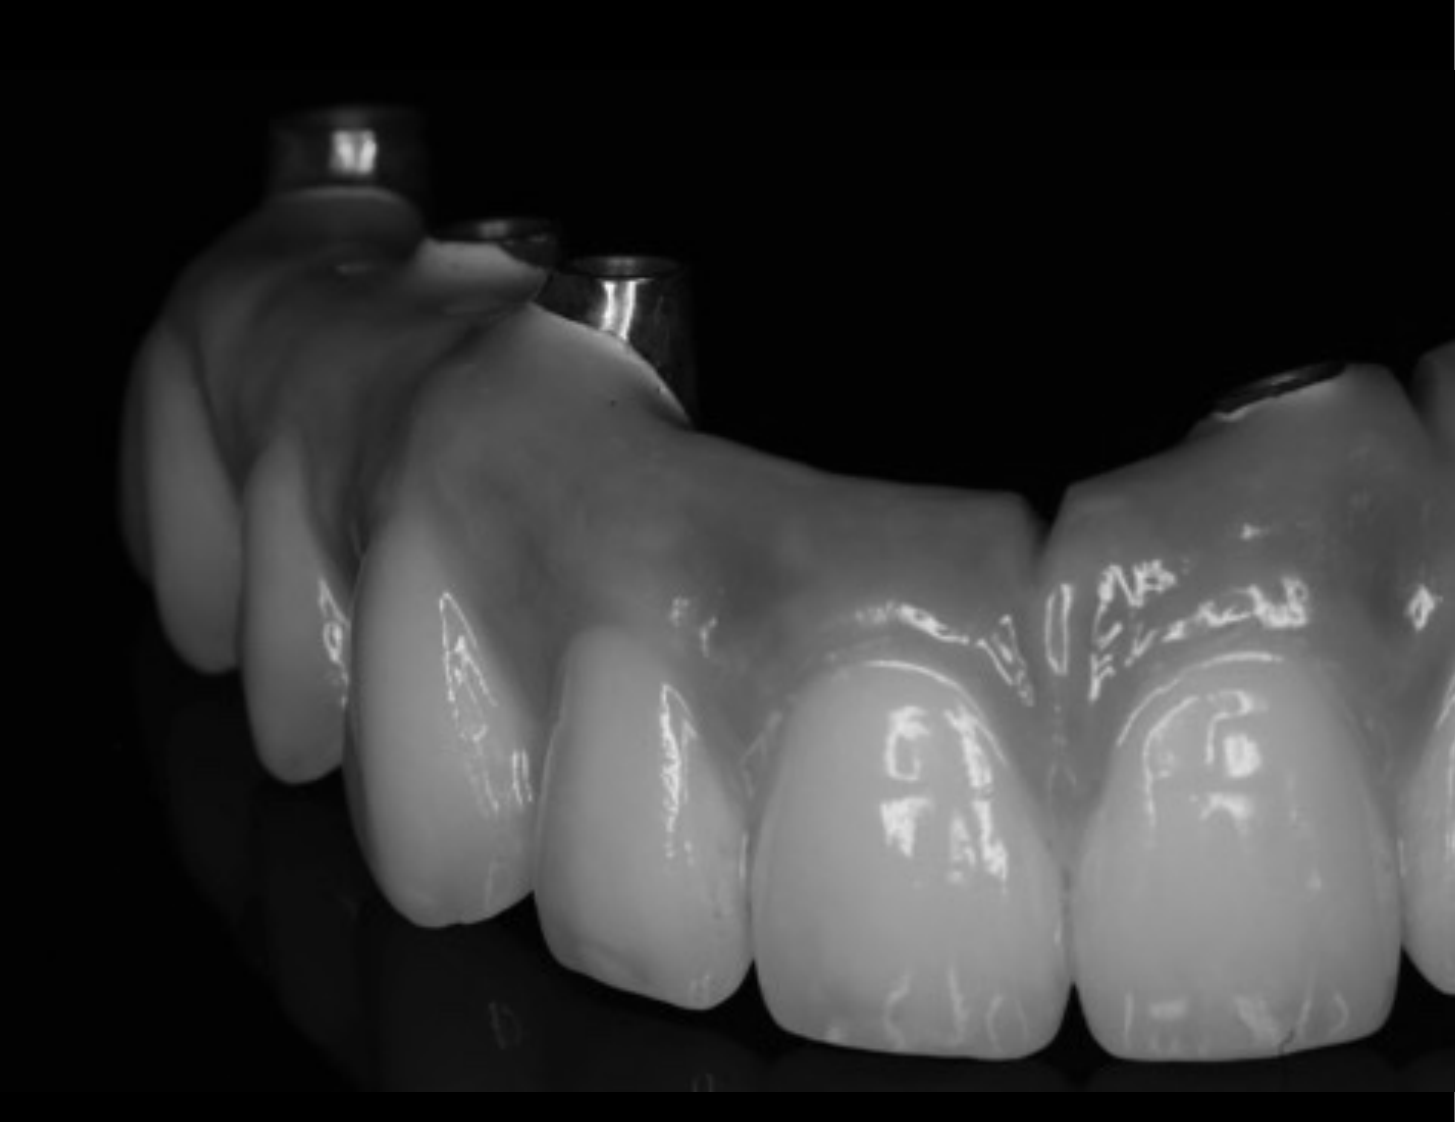
PFM – CrCo Framework79
- CAD/CAM framework: low cost, can have reasonable fit
- Maintenance: low, but expensive and difficult to fix
- Gingival replacement:
- Composite (marginal staining)
- Porcelain (aesthetics getting better)
 |  |
 |
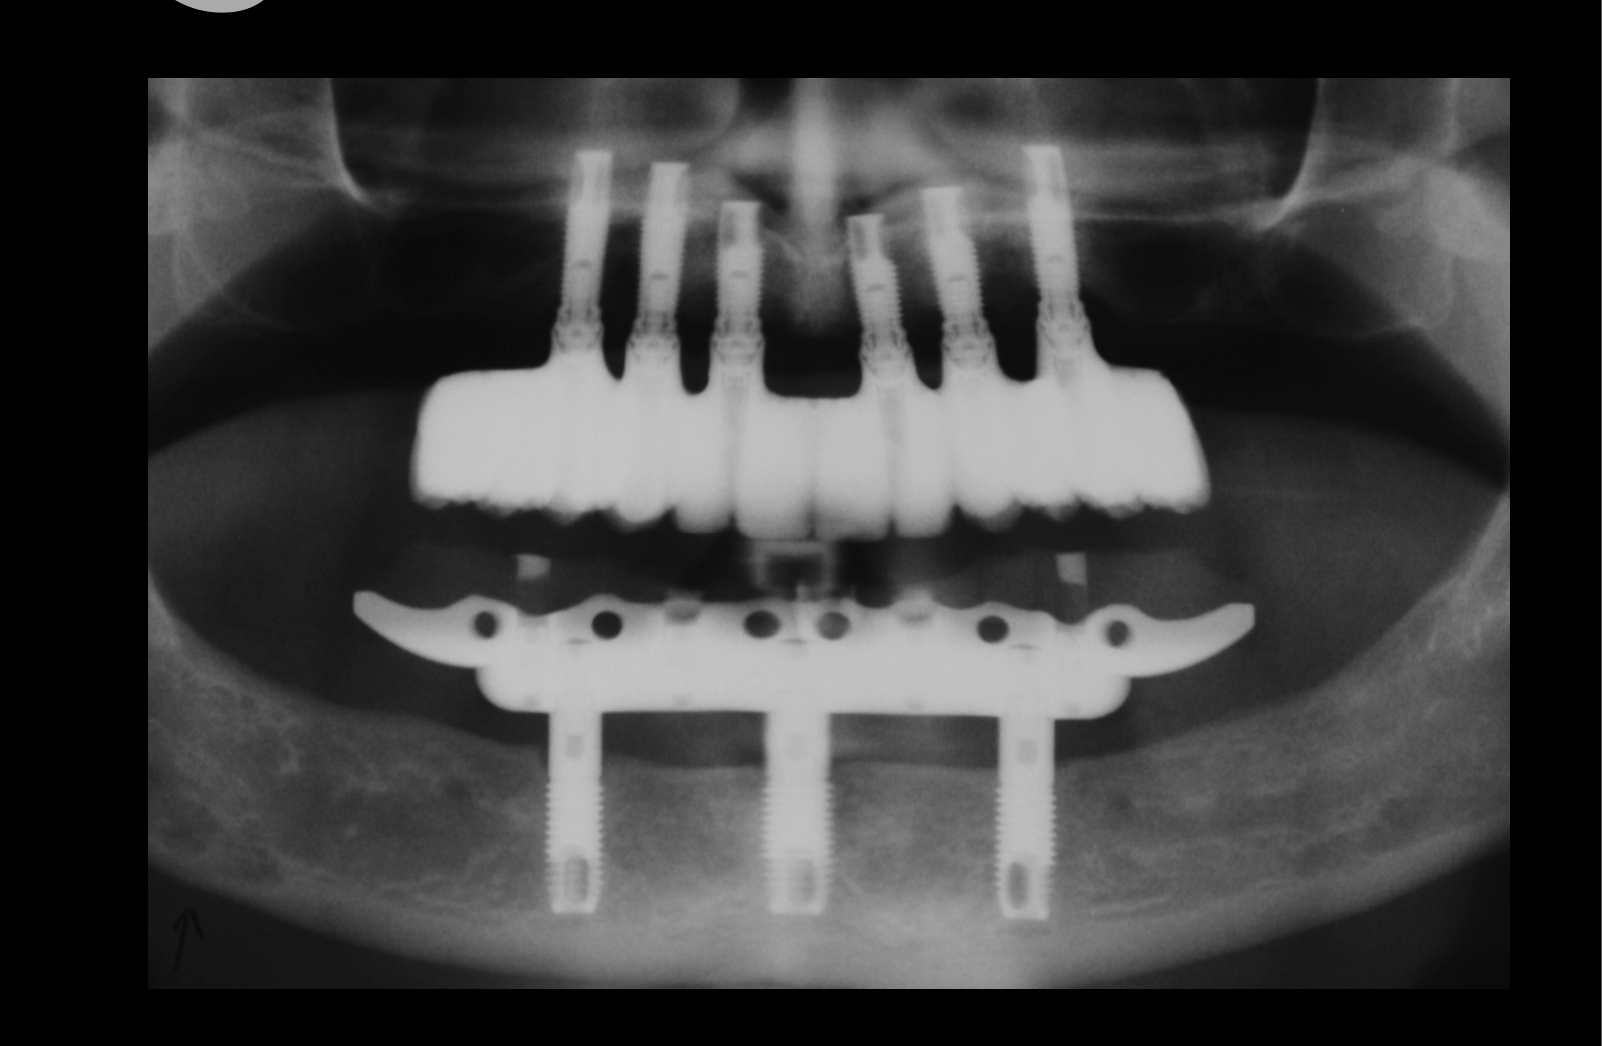
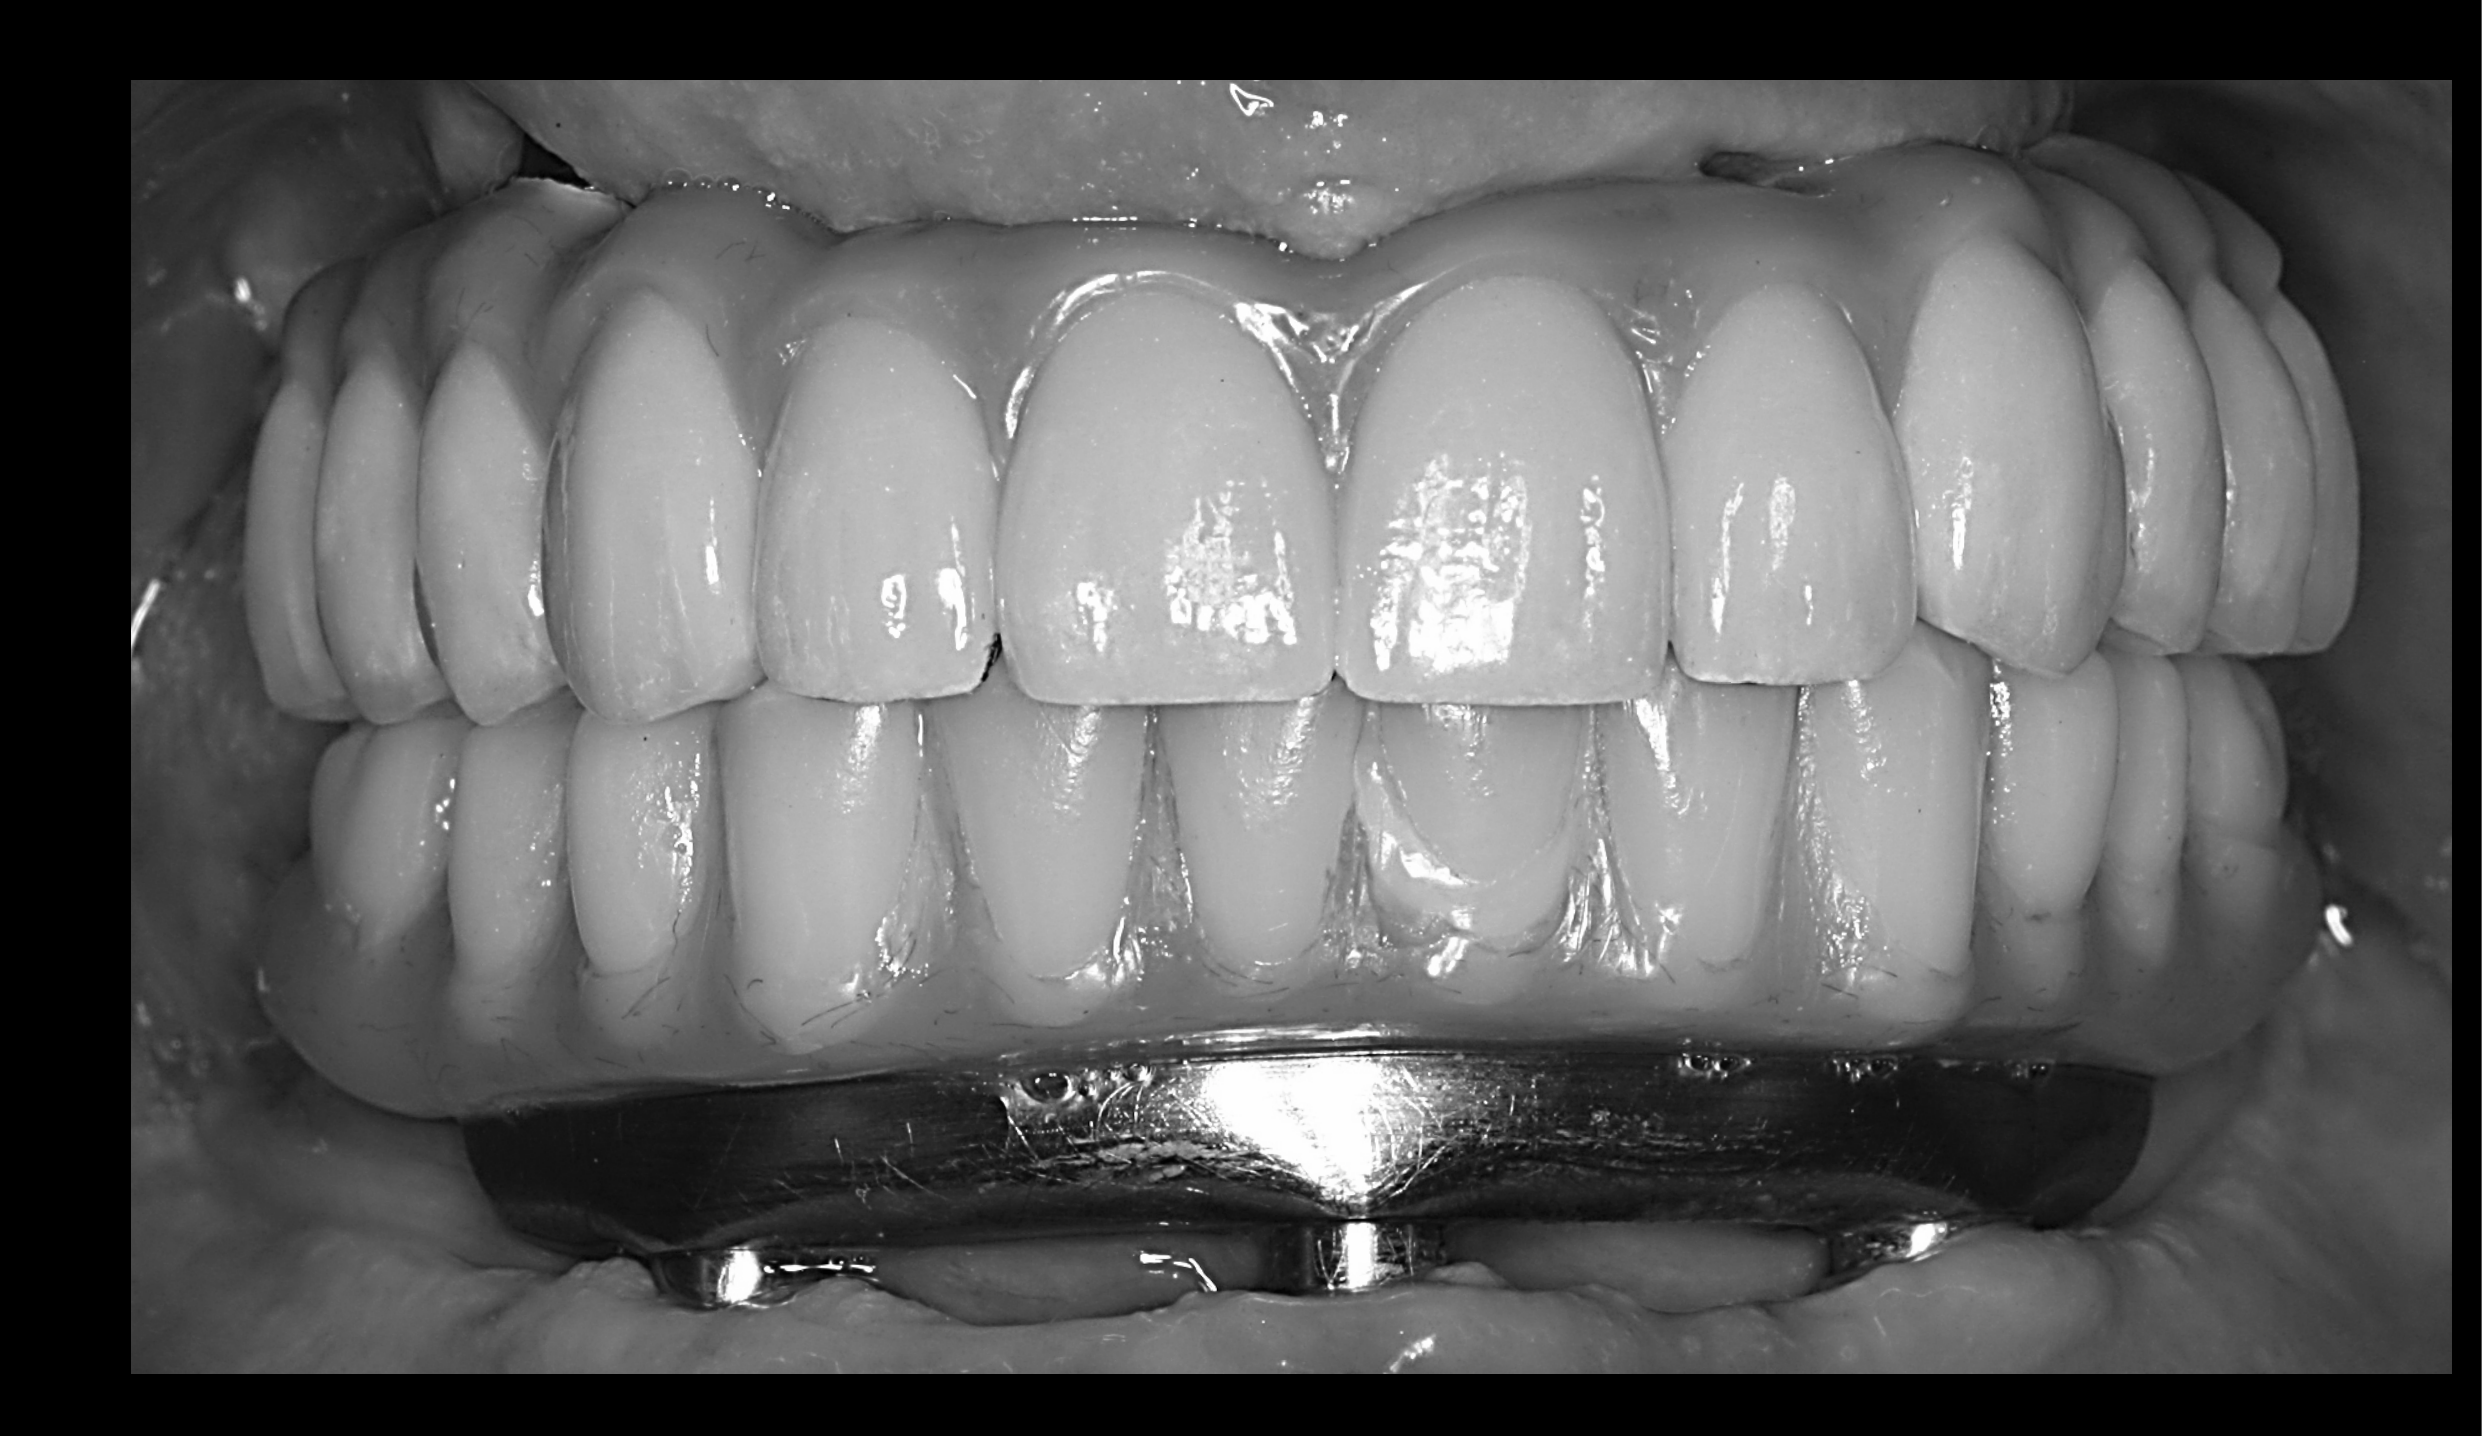
PFM – Porcelain Fused to Titanium80
- CAD/CAM Procera framework: low cost, excellent fit
- Maintenance: low, but expensive and difficult to fix
- Aesthetics of titanium porcelain: ordinary
 |  |
Flexural Strength of Dental Materials8182
| Material Type | Examples | Flexural Strength (~MPa) |
|---|---|---|
| Feldspathic | Veneering porcelain, veneers | 90 |
| Pressable ceramics | Empress, Cergo, Optimal | 150 |
| Indirect composites | Belleglass, Cristobal | 200 |
| Pressable Lithium disilicate | Empr.2, e.max | 300 |
| Glass infiltrated ceramics | In-Ceram Alum. | 400 |
| Alumina | Procera | 650 |
| (Y-TZP) Zirconia | Procera, Lava, Allzirkon | 1200 |
Flexural strength of current dental materials.
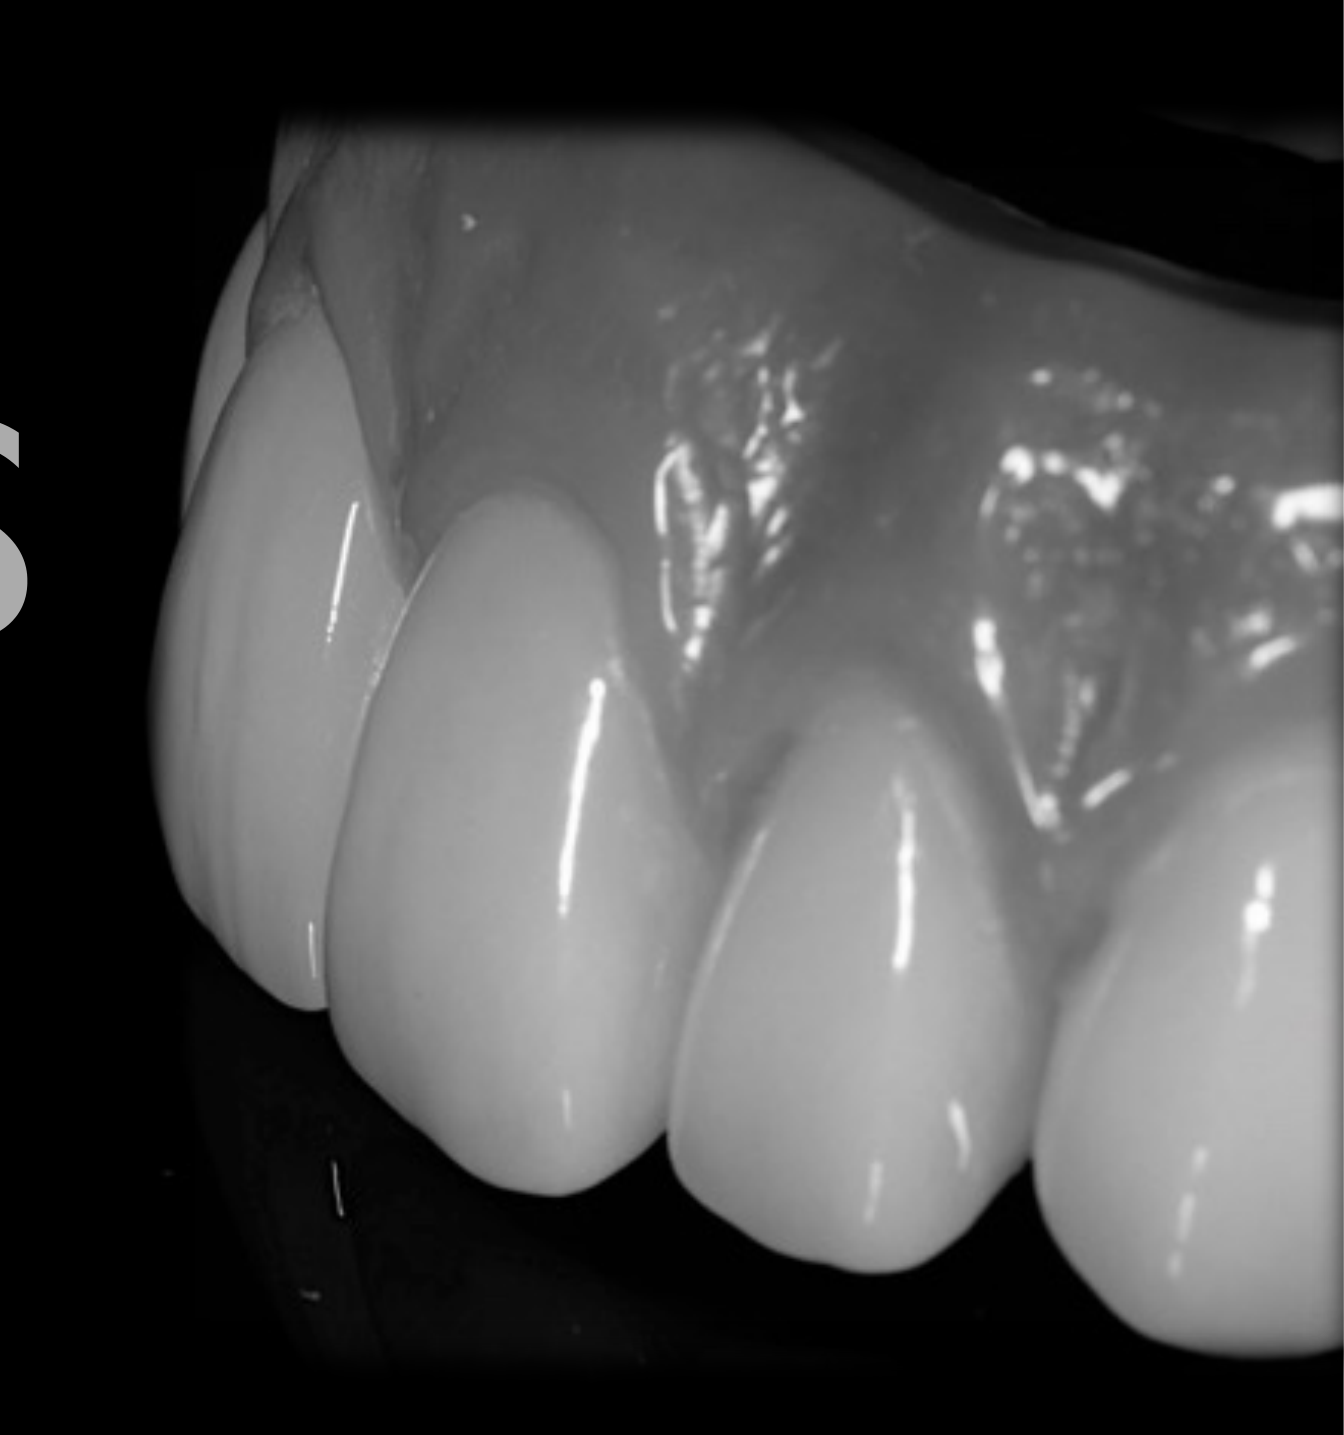
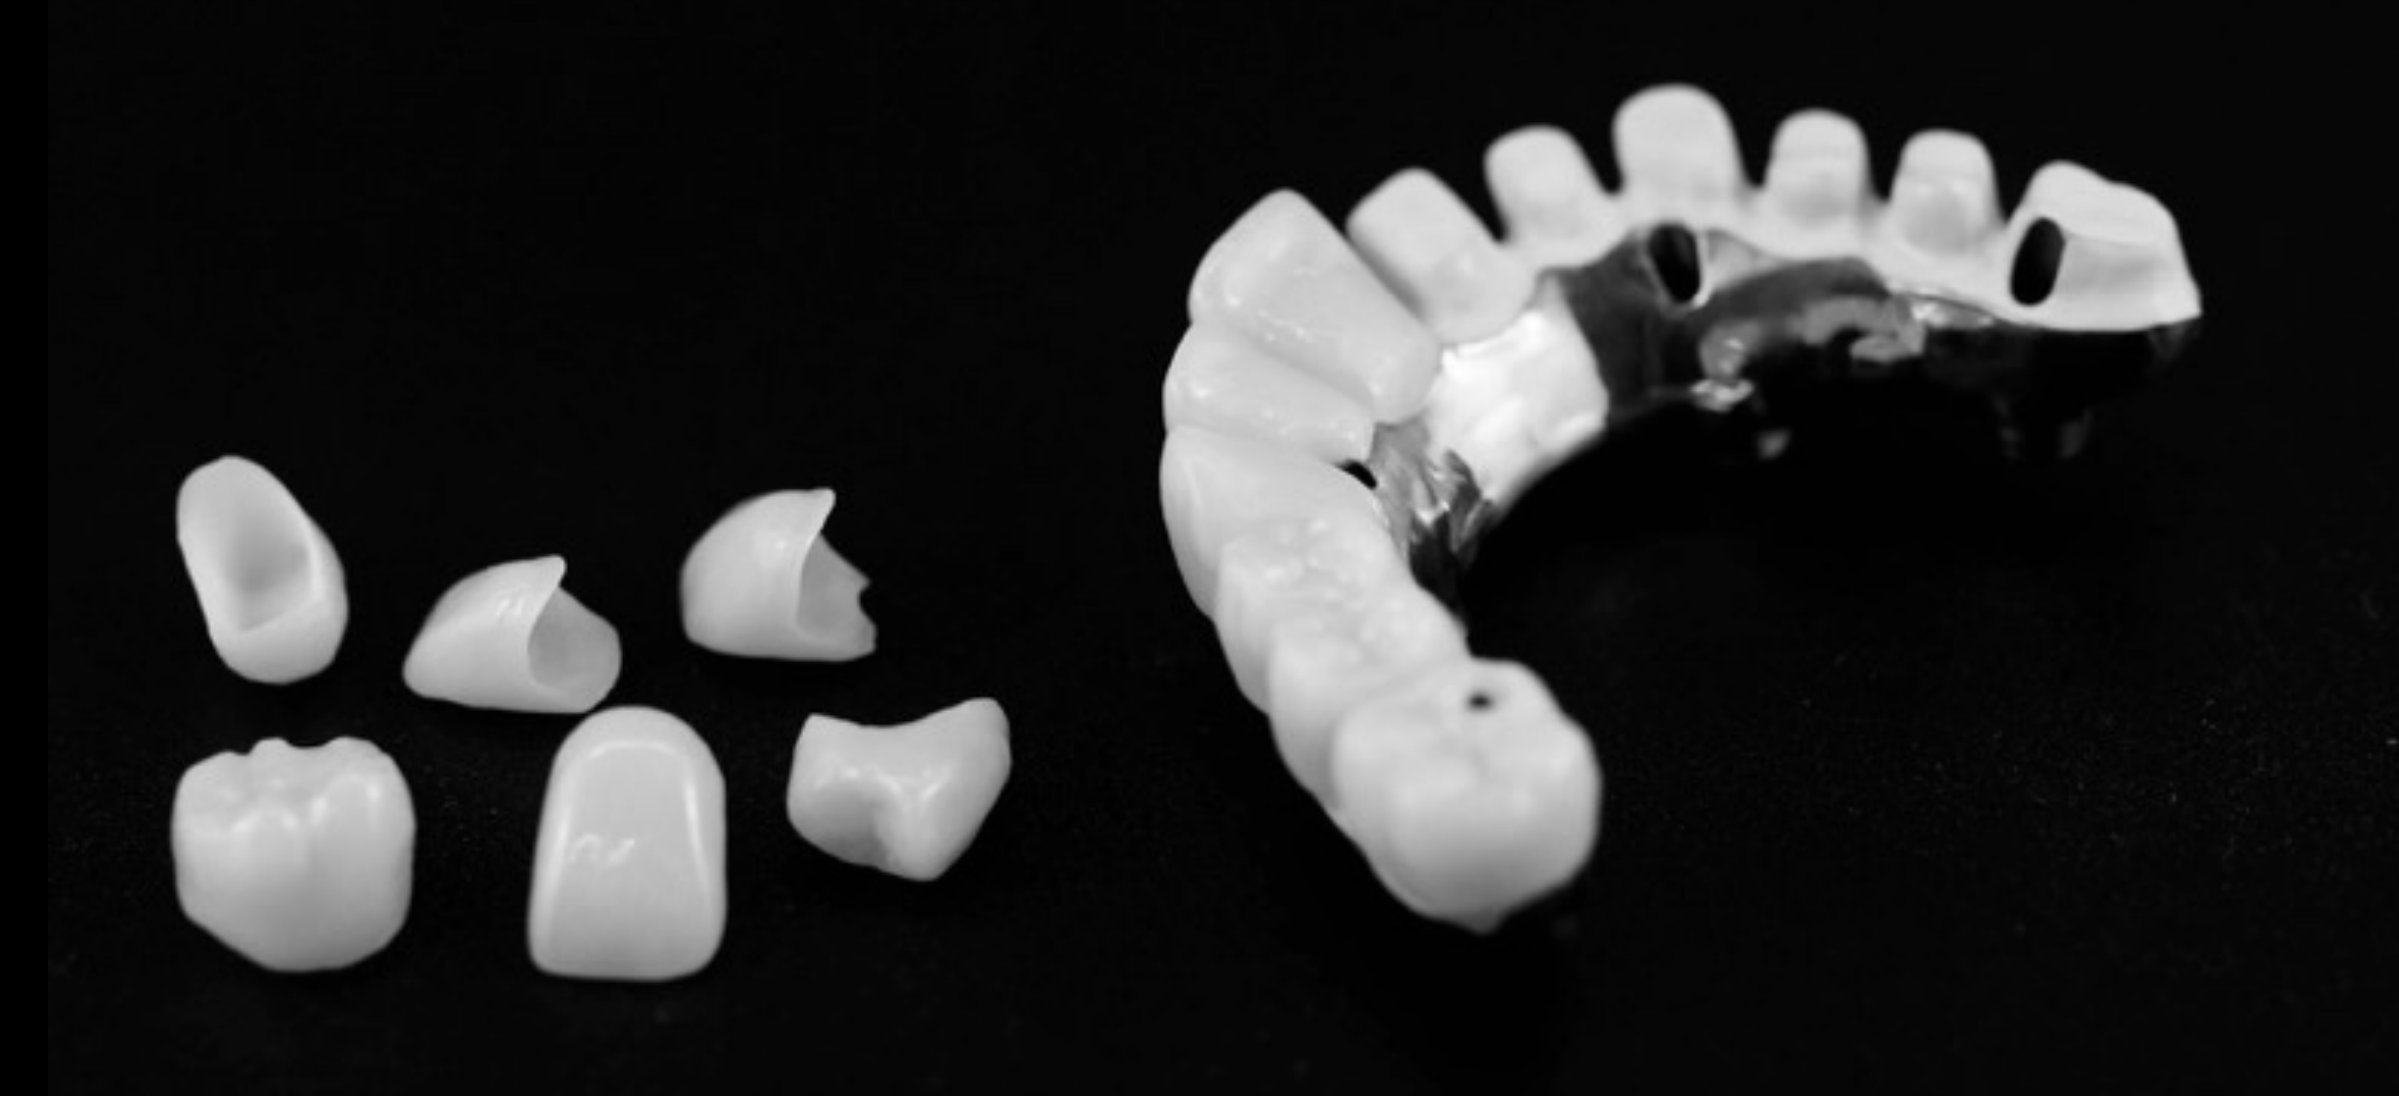
e.max Ceramic Crowns8384
- Layered anteriorly, monolithic posteriorly (300 MPa vs 90 MPa veneering porcelain)
- Need occlusal splint
- No gold component in Procera framework and no difference in cost for size of framework
- Maintenance is low and generally just replacement of one crown
- Gingival replacement: composite (marginal staining) — can be retreaded relatively easily
 |  |
Current Dental Materials85
| Material Type | Flexural Strength (~MPa) |
|---|---|
| Feldspathic (e.g., veneering porcelain, veneers) | ~90 |
| Pressable ceramics (e.g., Empress, Cergo, Optimal) | ~150 |
| Indirect composites (e.g., Belleglass, Cristobal) | ~200 |
| Pressable lithium disilicate (e.g., Empr.2, e.max) | ~300 |
| Glass infiltrated ceramics (e.g., In-Ceram Alum.) | ~400 |
| Alumina (Procera) | ~650 |
| (Y-TZP) Zirconia (e.g., Procera, Lava, Allzirkon) | ~1200 |
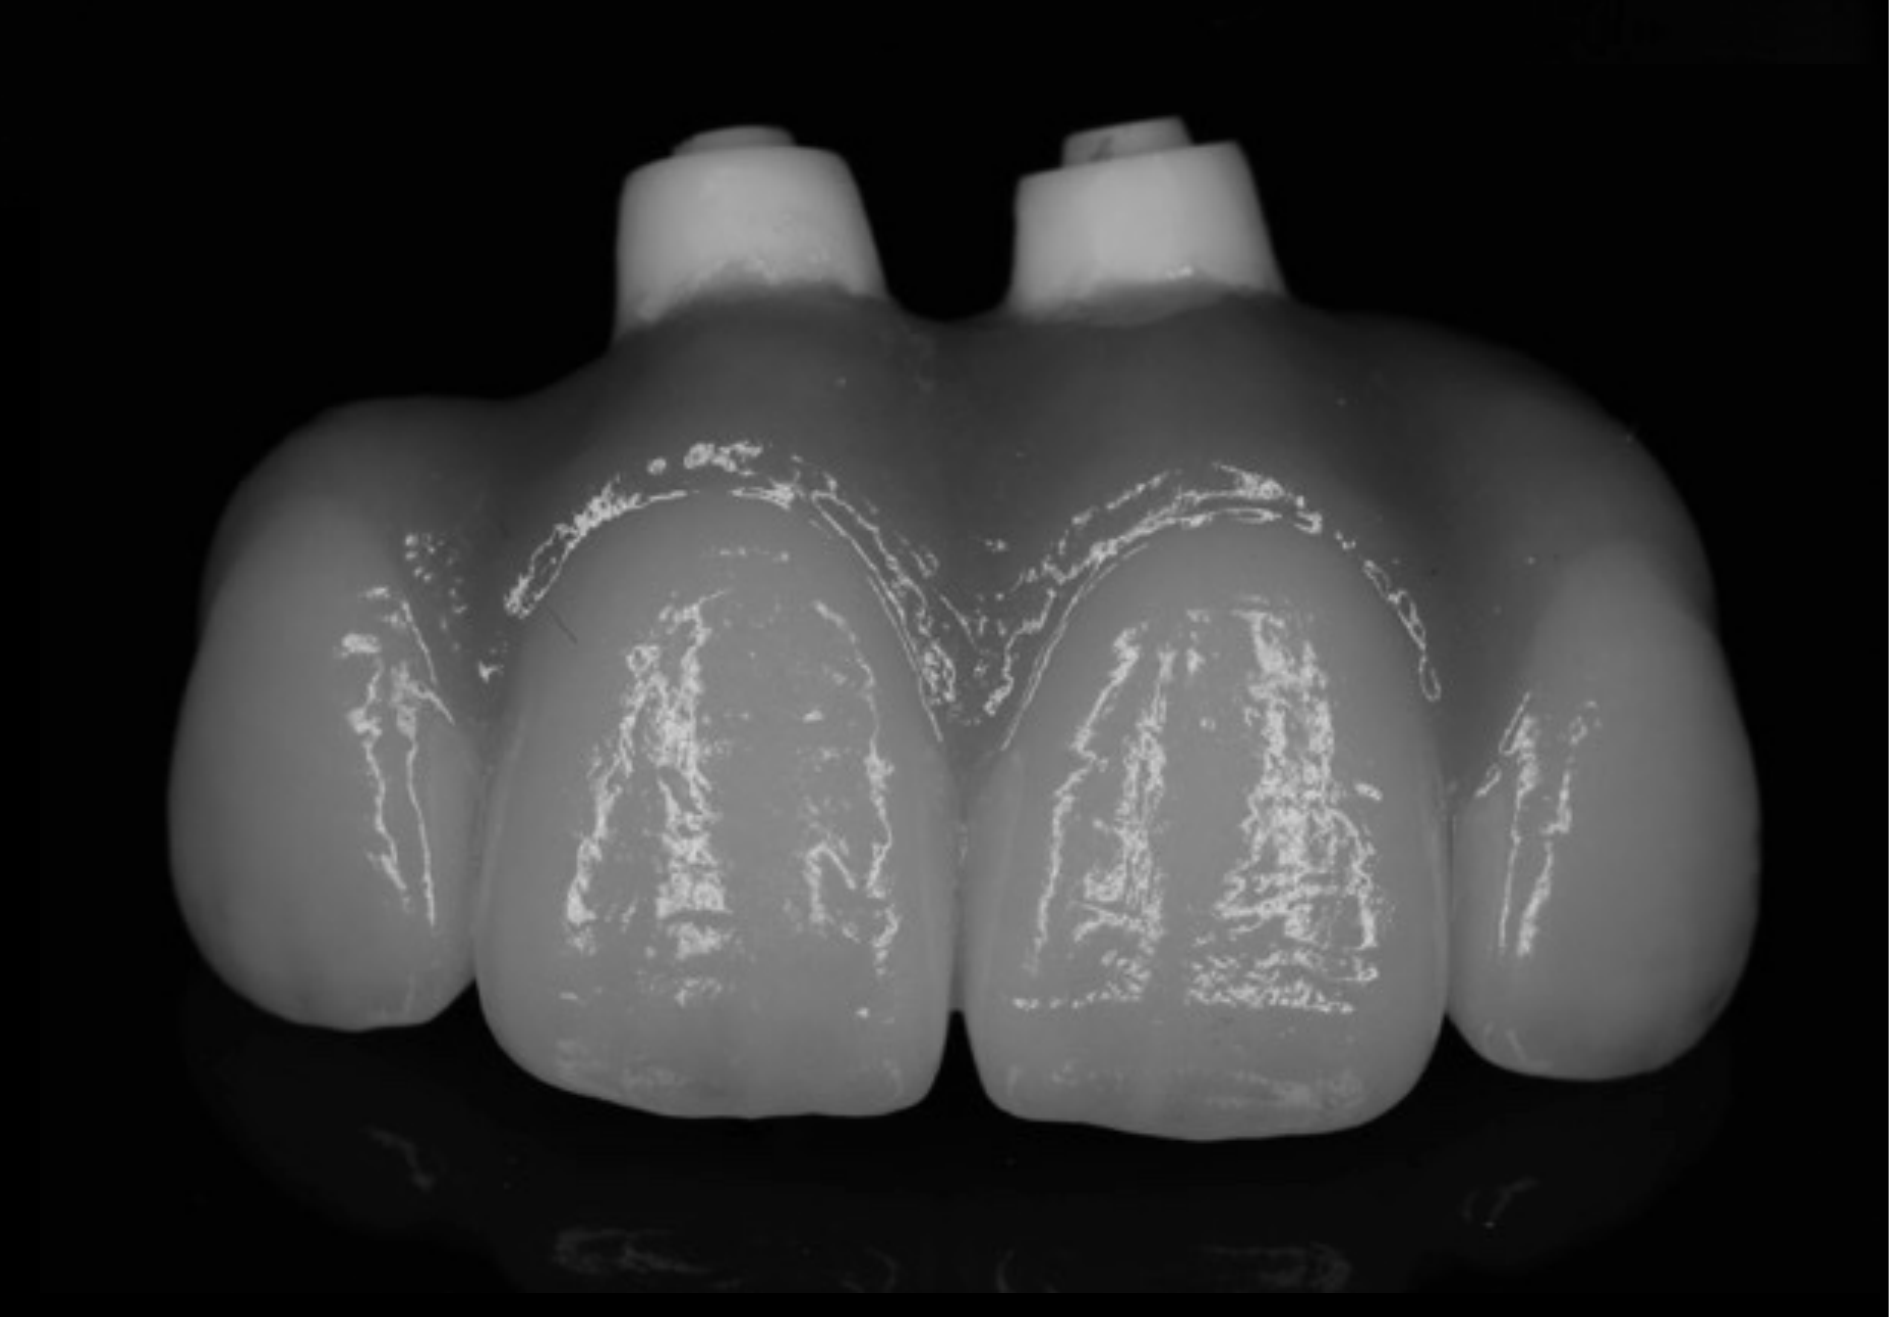
Full Zirconia868788
- Massive downside if framework fractures
- Industrial fabrication essential
- Need highly experienced technician → Need occlusal splint
- Attention to detail
- More long-term clinical research required
Titanium CAD/CAM framework / Stained monolithic zirconia segments
Maintenance Protocol and Preferences
Maintenance Protocol
Follow-Up Schedule89
- Weekly for first 4 weeks, then every 6 weeks until 6 months
- Then every 3–6 months according to need
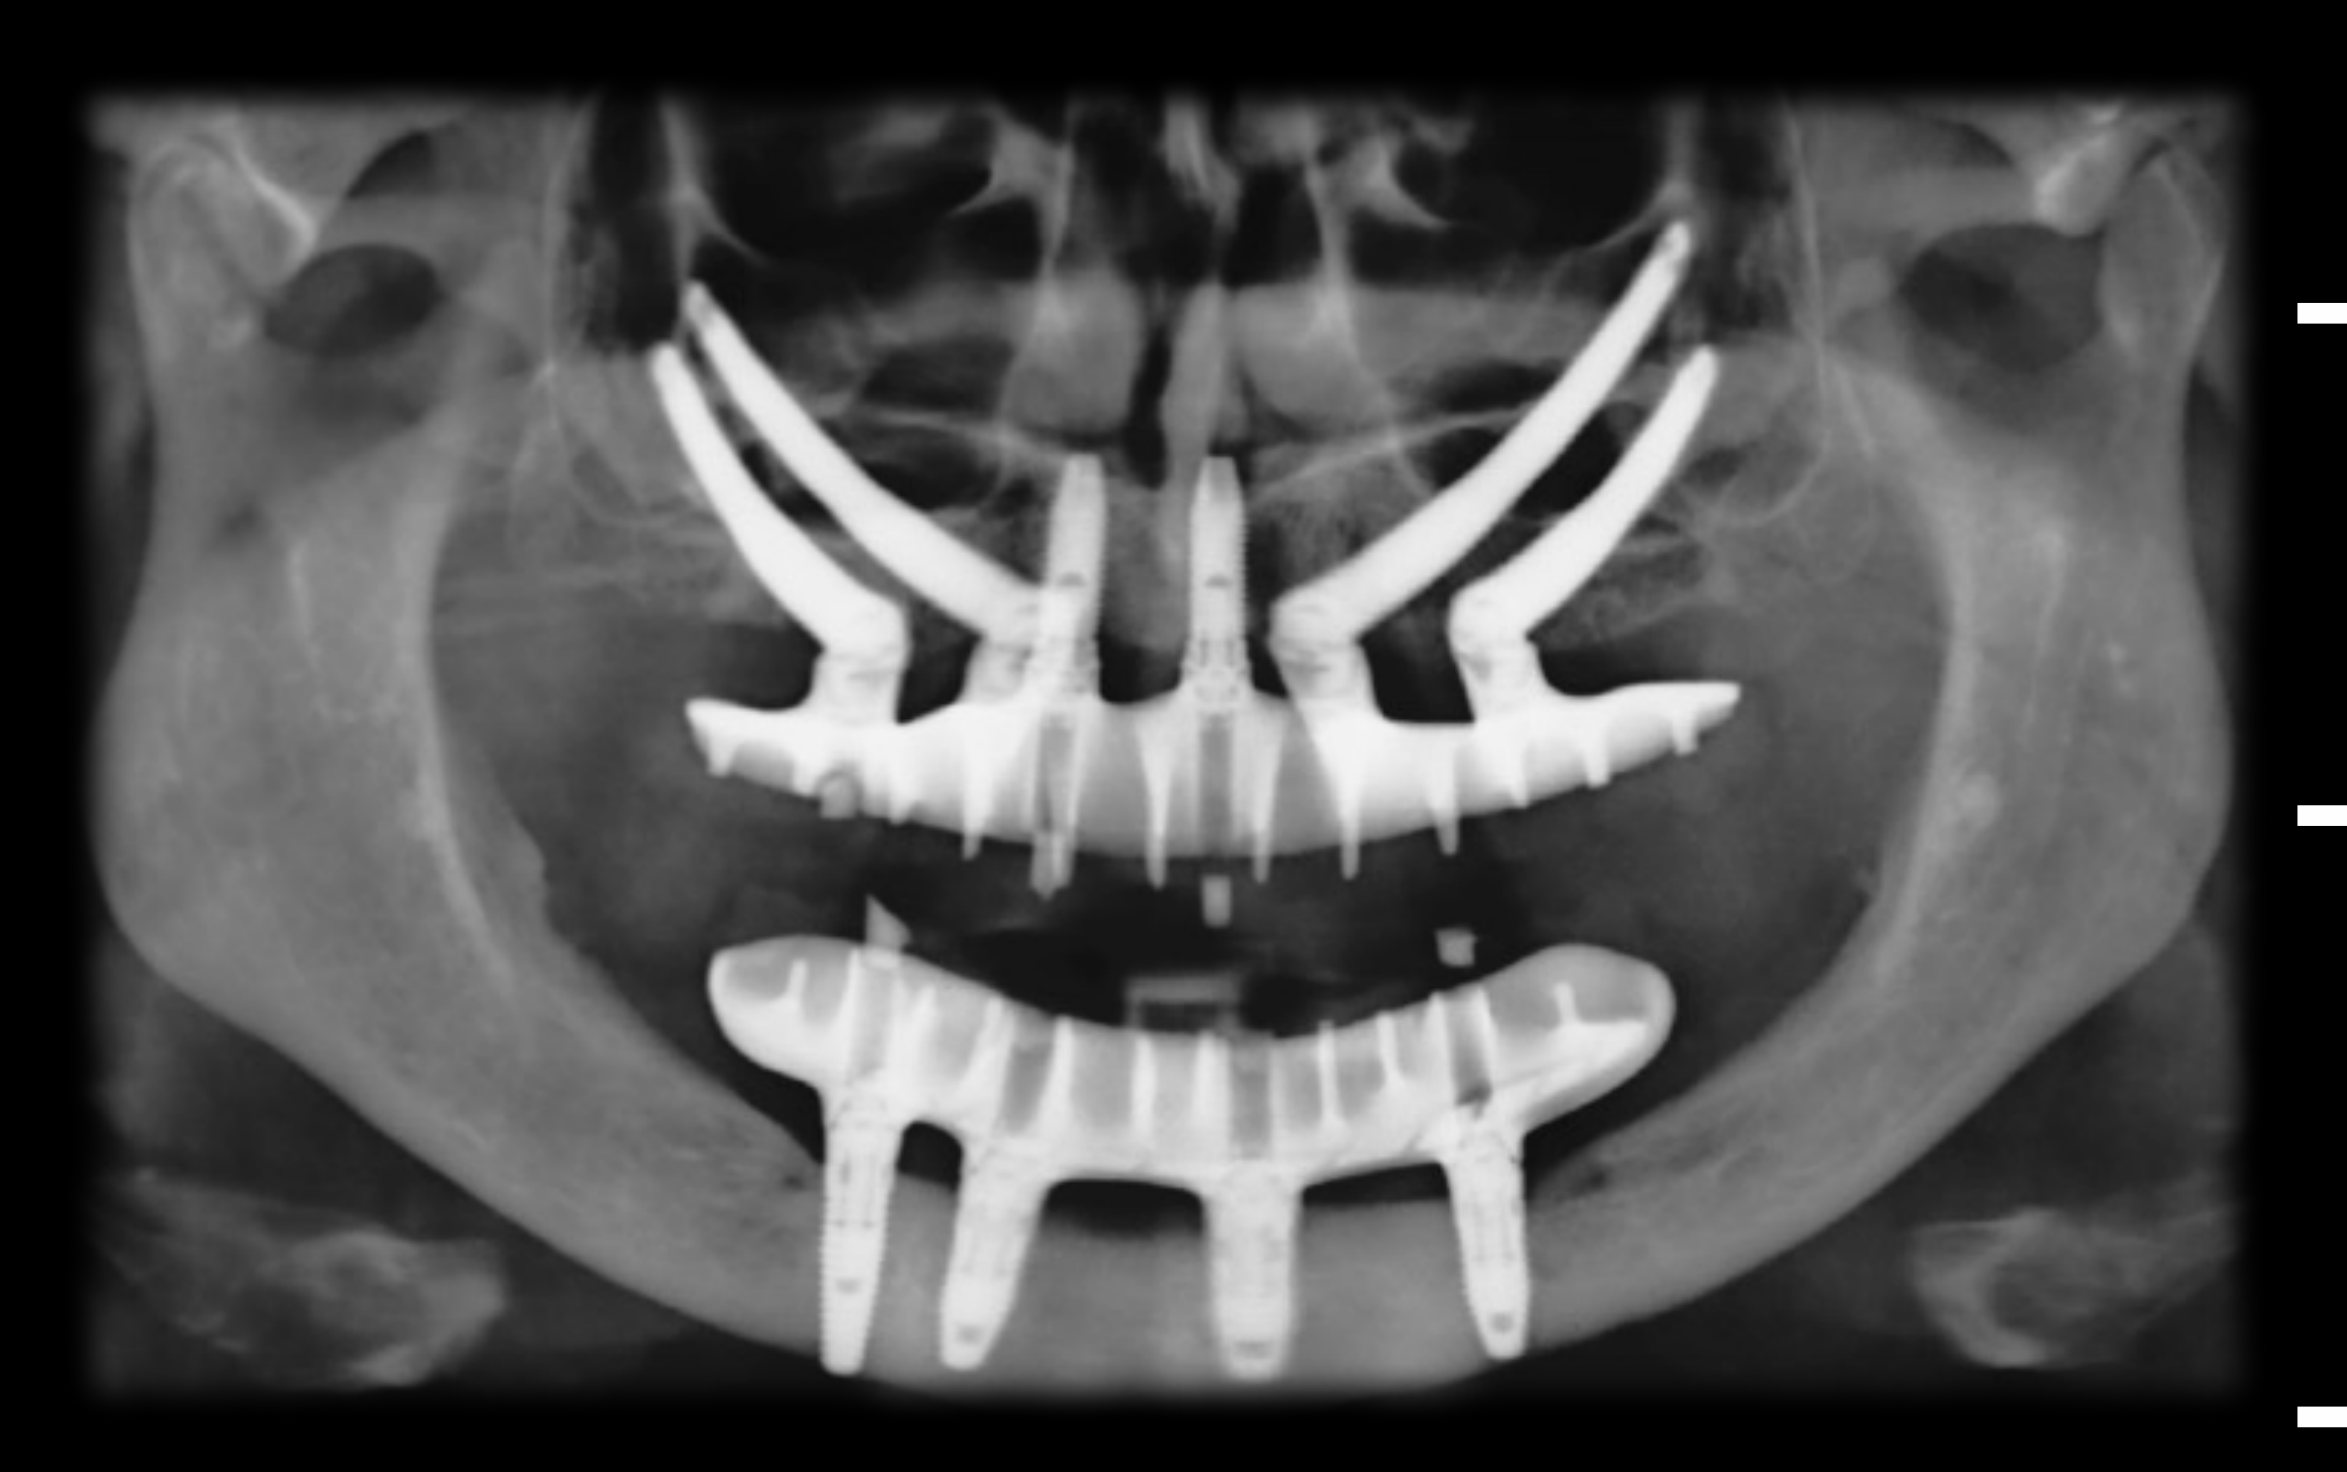
Radiographic Protocol
- OPG radiographs at bridge placement, 6 months, then yearly for 5 years
- Then every 2–3 years depending on history
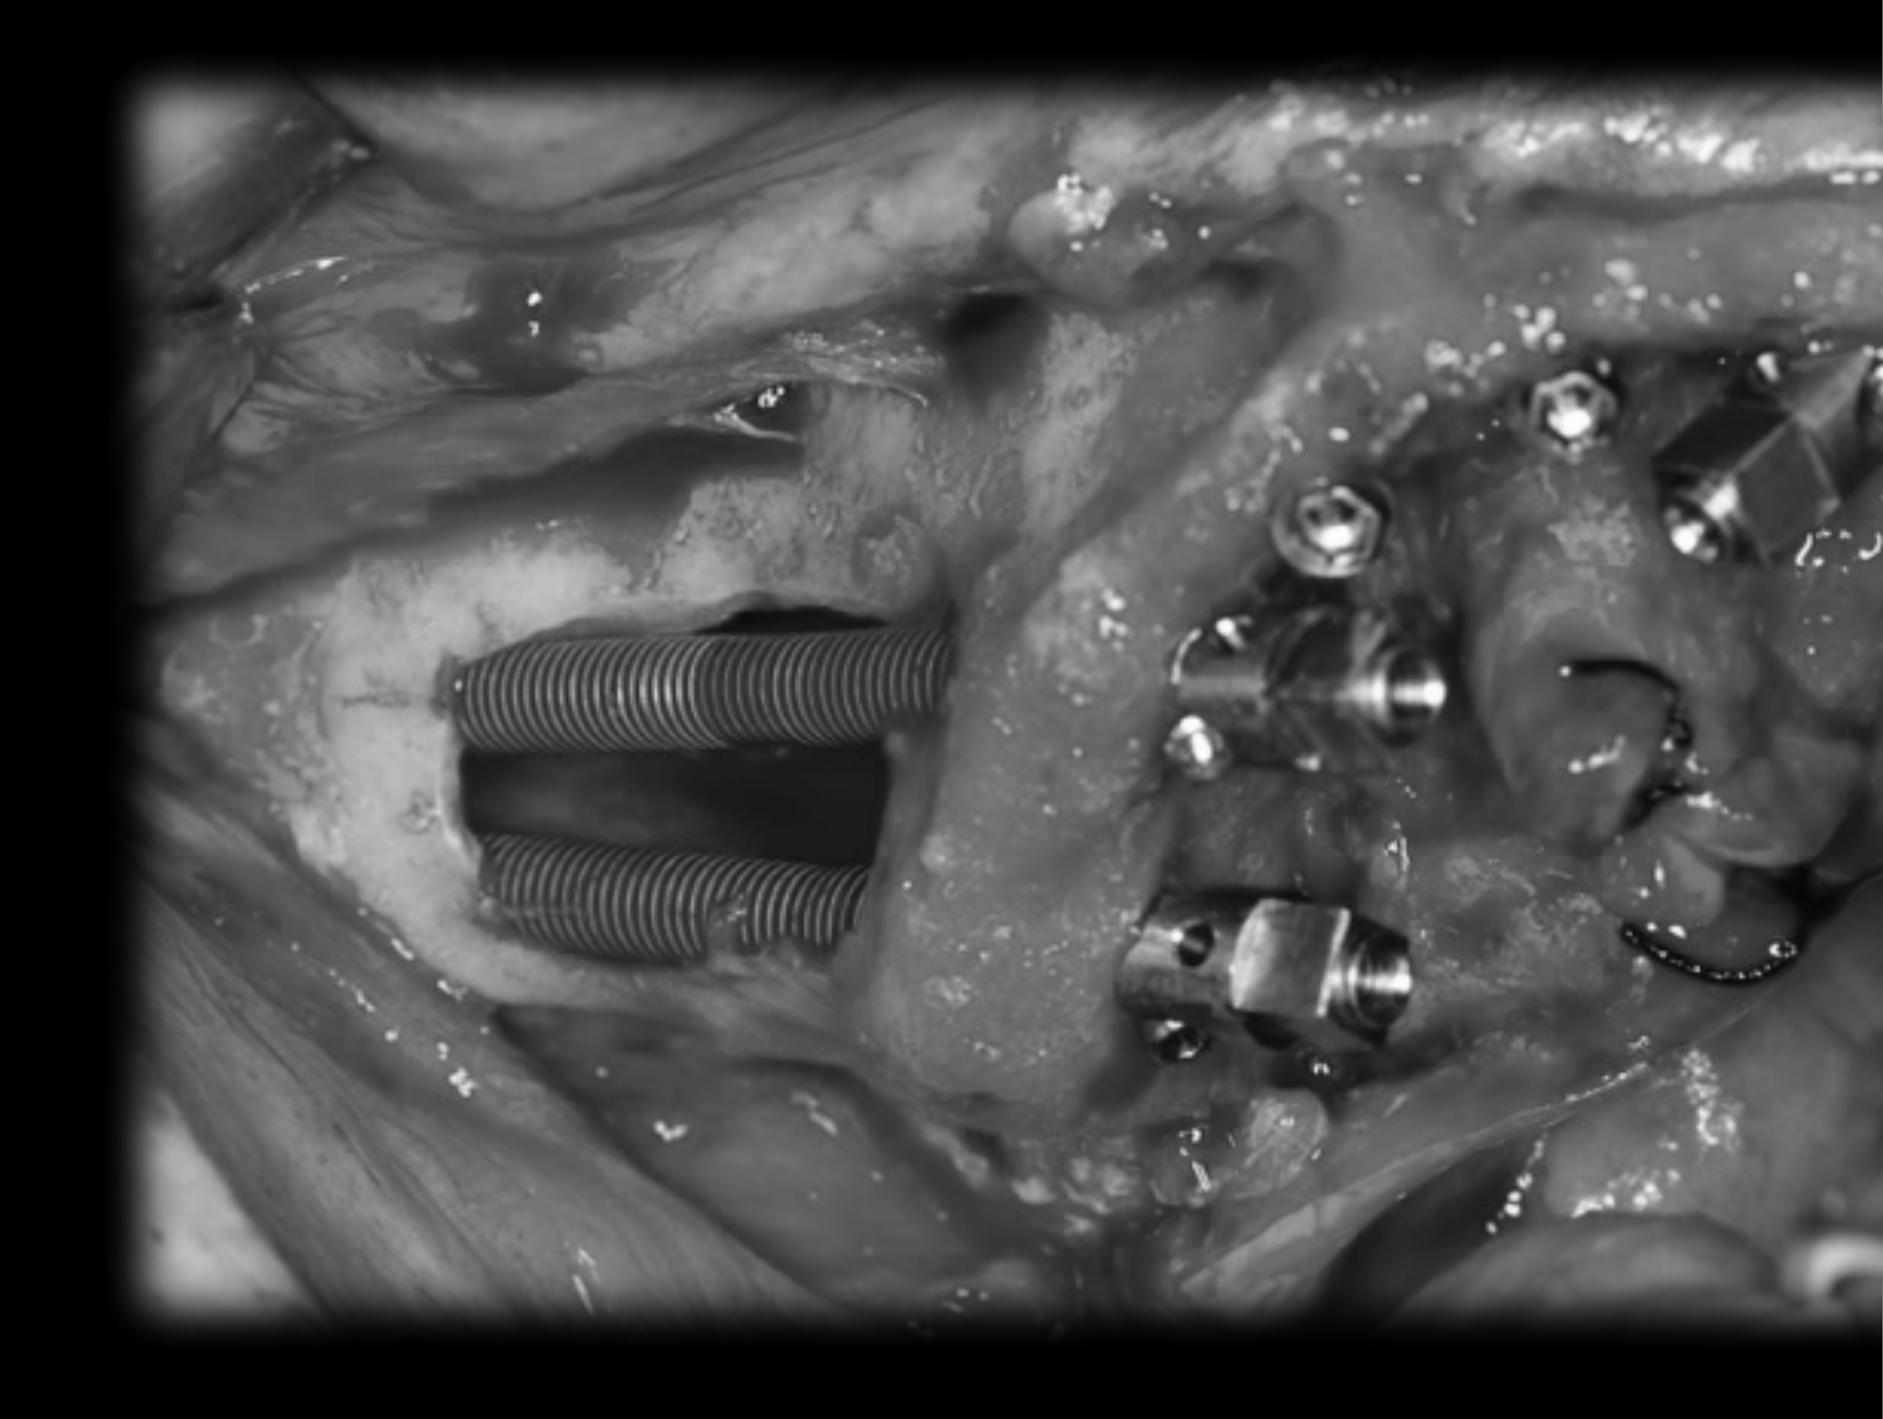
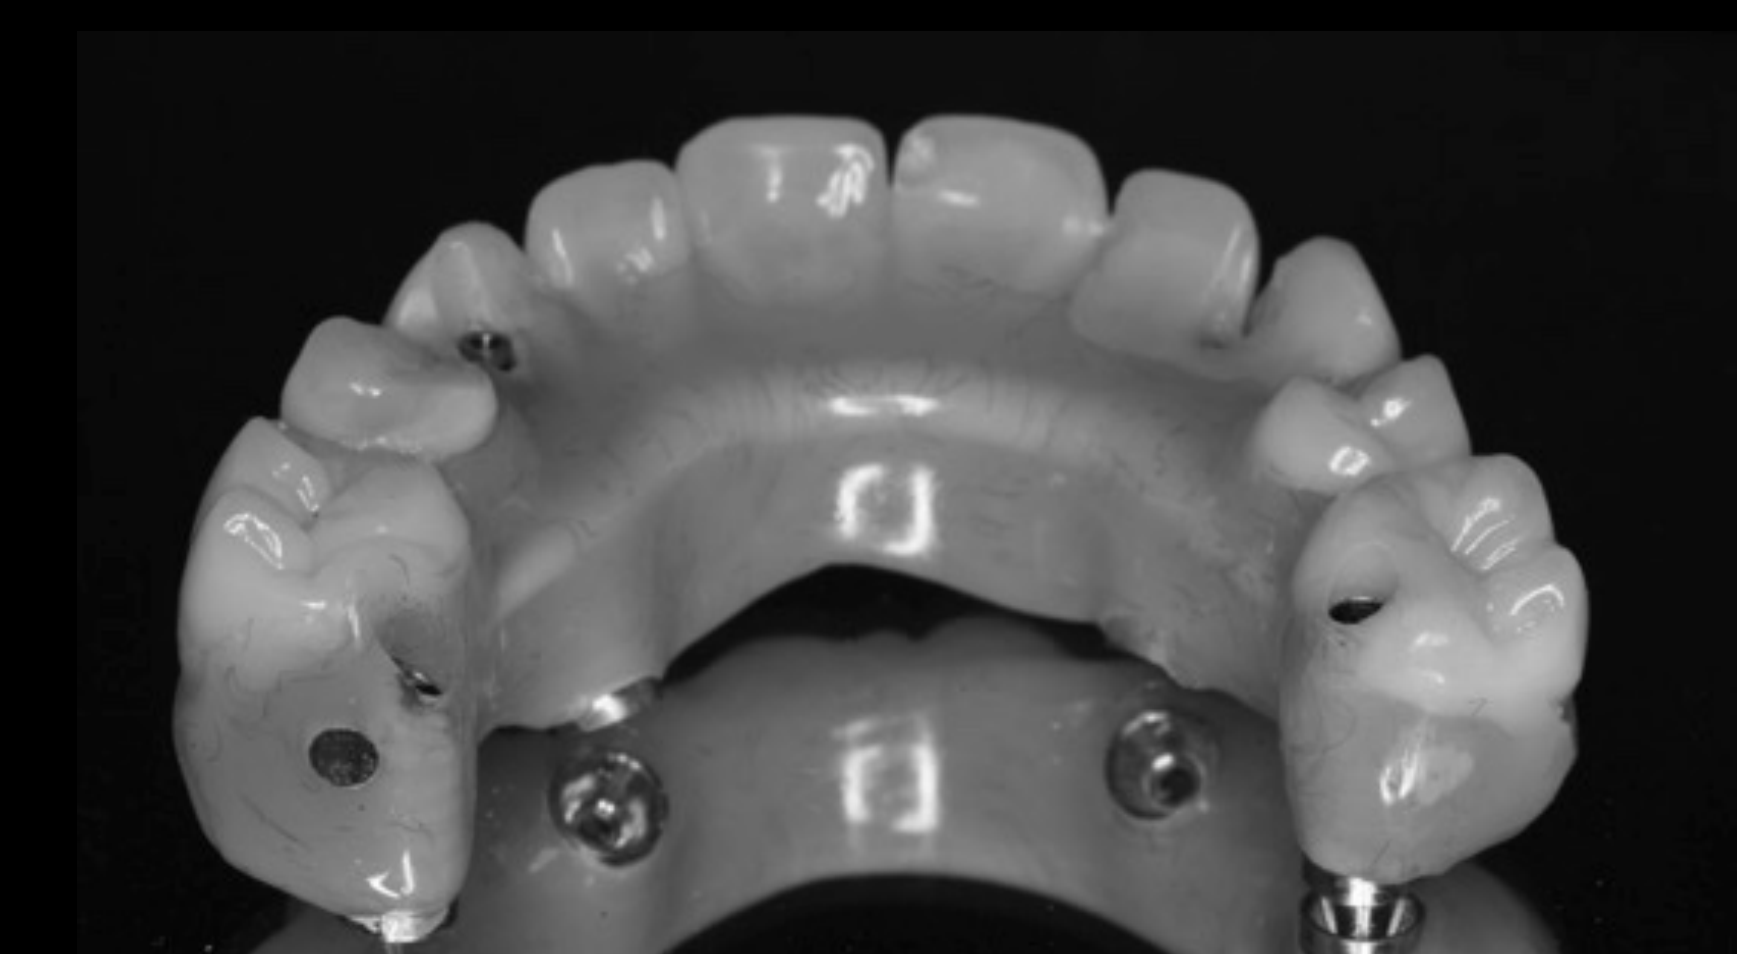
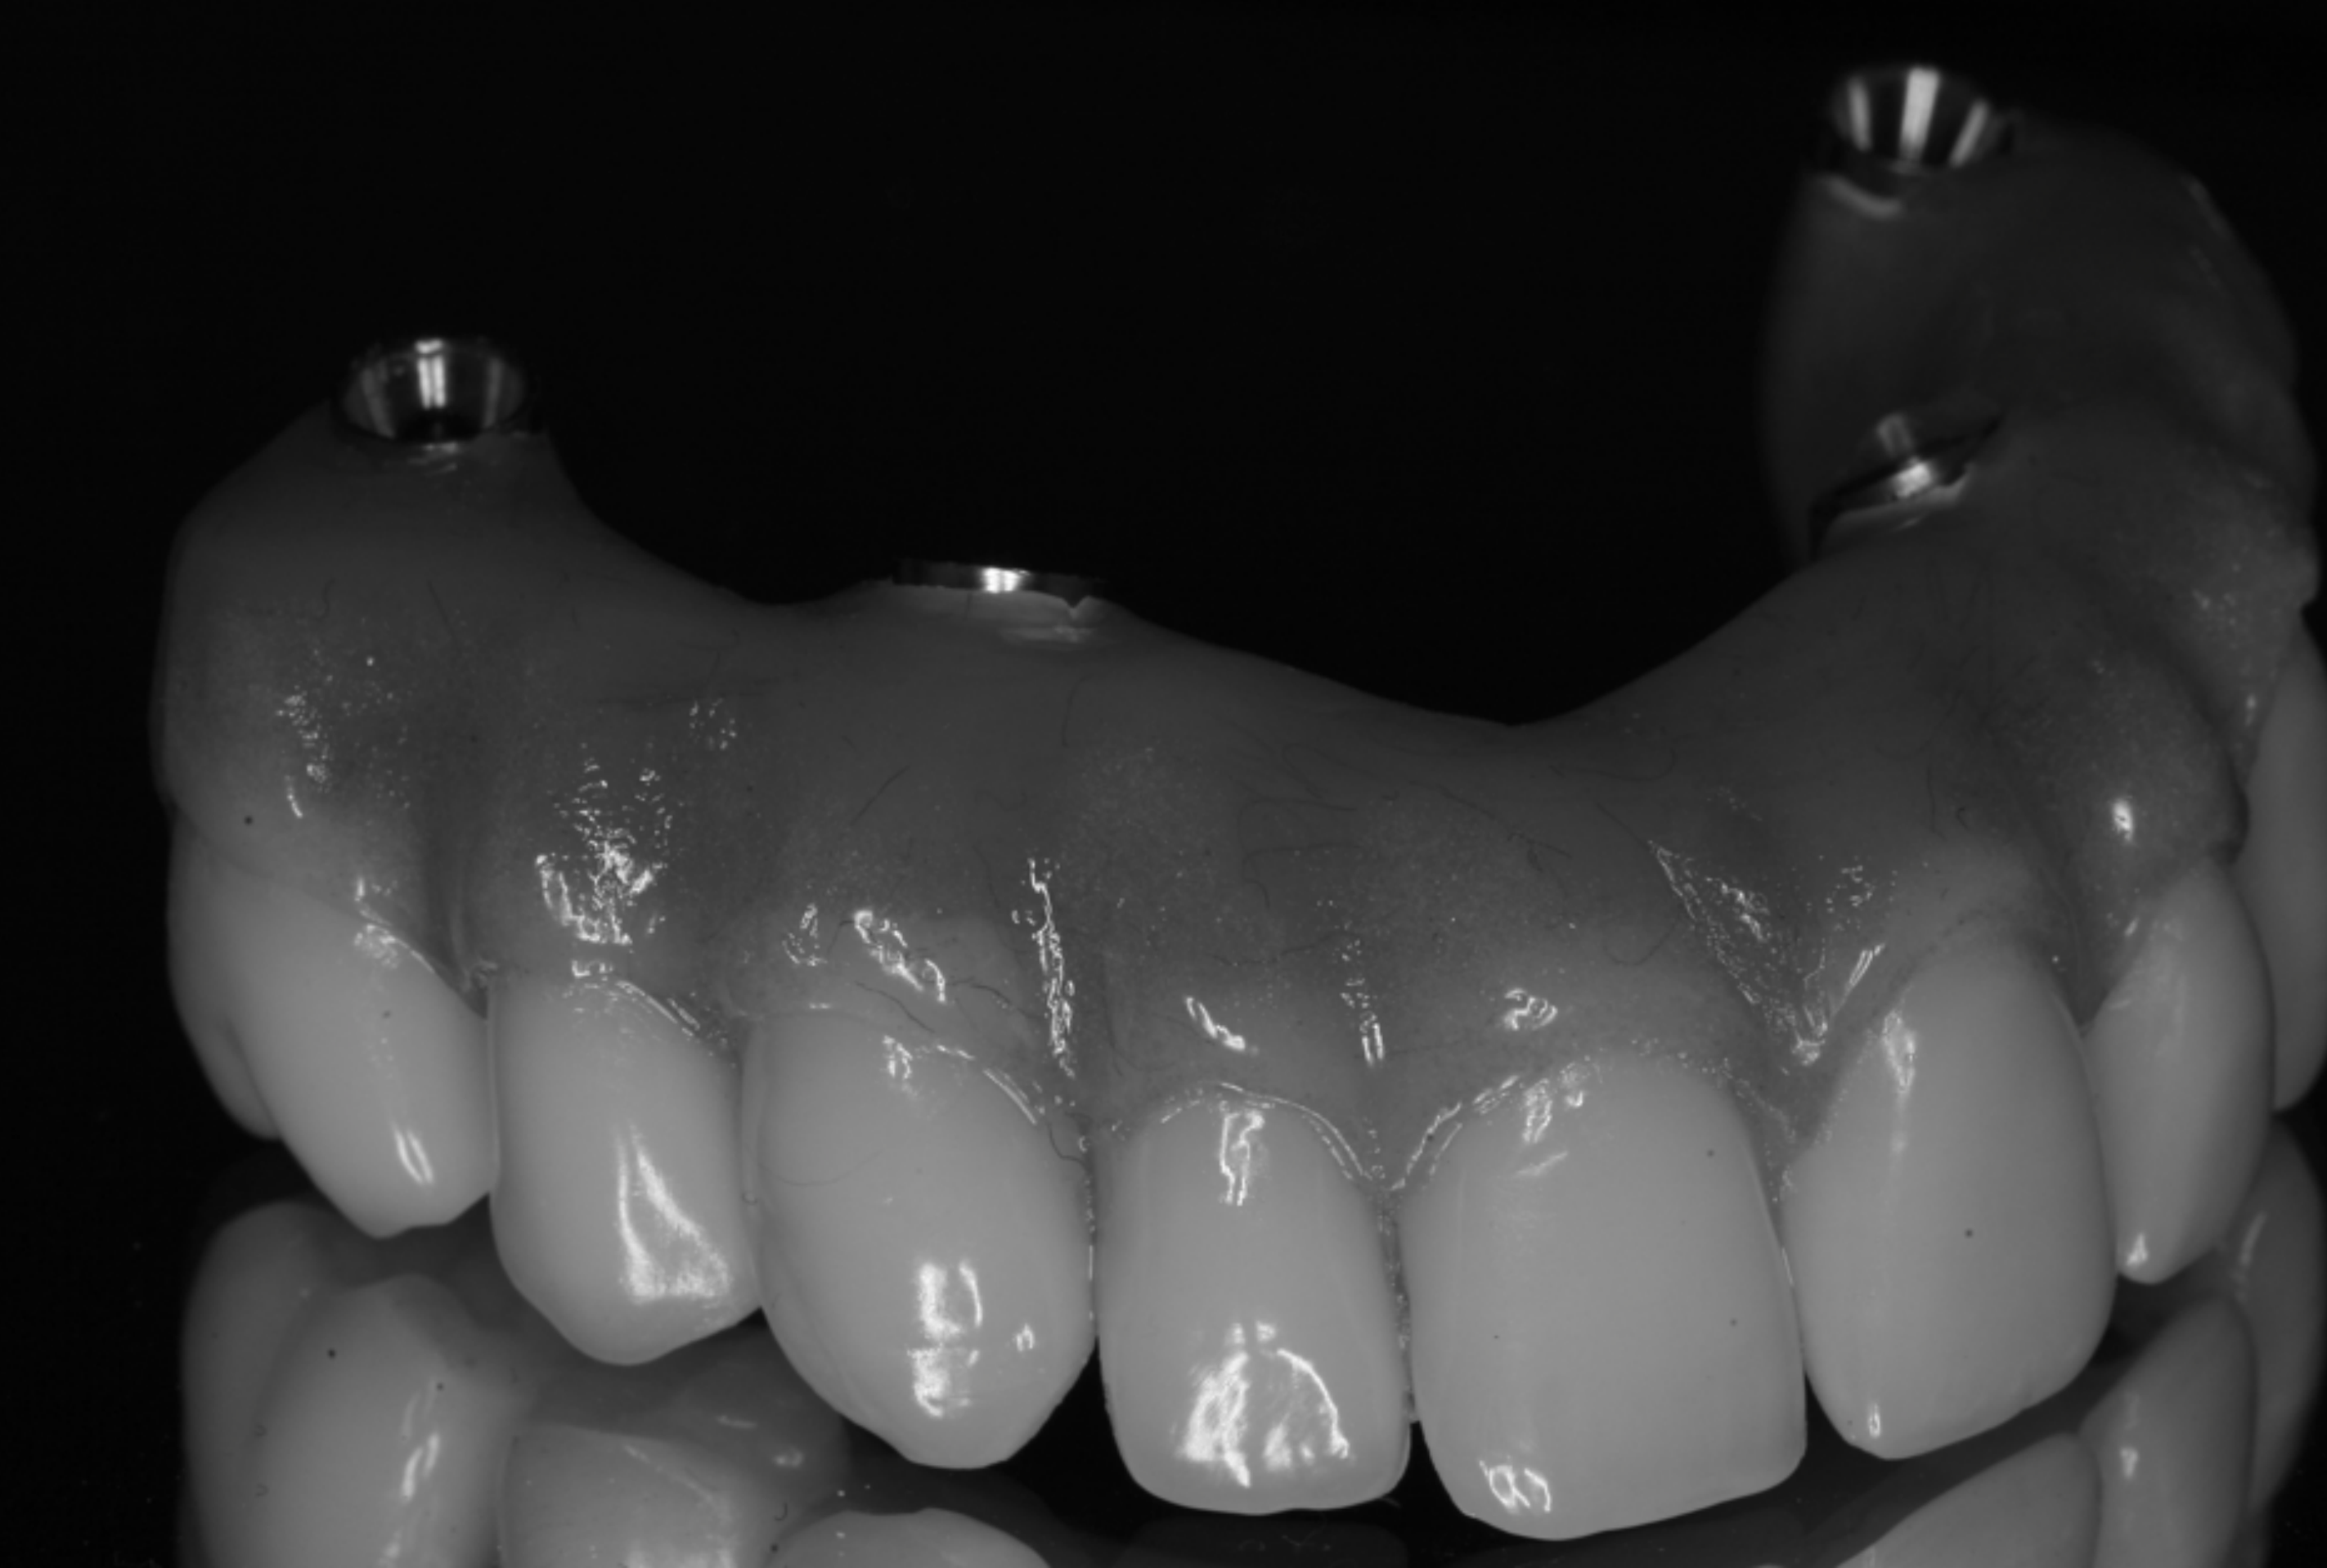
Our Preferences909192
-
No pre-implant grafting
-
Utilize available native bone
-
Immediate loading
-
Rigid prosthesis
-
Cross arch splinting
Prosthetic replacement of soft tissue and facial support
Patient and Clinician Benefits
Patient Benefits93
- Optimal comfort
- Less invasive surgery
- Less pain and swelling
- Reduced chairtime
Cost Saving
- Much earlier return to work and social life
Fast Treatment
- Immediate function
Clinician Benefits94
- Increased predictability & safety
- Reduction in interim management
- Predictable prosthetic outcome
Closing
Thank you!95
Affiliations
- Associated Brånemark Osseointegration Center, Perth, Australia
- The University of Western Australia
Contact Information
- Email: glenliddelow@gmail.com
- Website: www.branemarkcentre.com.au
Footnotes
-
Original PDF page 1: No obsidian-L7 Dental School Maxilla fixed notes, p.1 ↩
-
Original PDF page 2: No obsidian-L7 Dental School Maxilla fixed notes, p.2 ↩
-
Original PDF page 4: No obsidian-L7 Dental School Maxilla fixed notes, p.4 ↩
-
Original PDF page 5: No obsidian-L7 Dental School Maxilla fixed notes, p.5 ↩
-
Original PDF page 3: No obsidian-L7 Dental School Maxilla fixed notes, p.3 ↩
-
Original PDF page 6: No obsidian-L7 Dental School Maxilla fixed notes, p.6 ↩
-
Original PDF page 7: No obsidian-L7 Dental School Maxilla fixed notes, p.7 ↩
-
Original PDF page 8: No obsidian-L7 Dental School Maxilla fixed notes, p.8 ↩
-
Original PDF page 9: No obsidian-L7 Dental School Maxilla fixed notes, p.9 ↩
-
Original PDF page 11: No obsidian-L7 Dental School Maxilla fixed notes, p.11 ↩
-
Original PDF page 10: No obsidian-L7 Dental School Maxilla fixed notes, p.10 ↩
-
Original PDF page 12: No obsidian-L7 Dental School Maxilla fixed notes, p.12 ↩
-
Original PDF page 13: No obsidian-L7 Dental School Maxilla fixed notes, p.13 ↩
-
Original PDF page 14: No obsidian-L7 Dental School Maxilla fixed notes, p.14 ↩
-
Original PDF page 16: No obsidian-L7 Dental School Maxilla fixed notes, p.16 ↩
-
Original PDF page 15: No obsidian-L7 Dental School Maxilla fixed notes, p.15 ↩
-
Original PDF page 17: No obsidian-L7 Dental School Maxilla fixed notes, p.17 ↩
-
Original PDF page 18: No obsidian-L7 Dental School Maxilla fixed notes, p.18 ↩
-
Original PDF page 19: No obsidian-L7 Dental School Maxilla fixed notes, p.19 ↩
-
Original PDF page 20: No obsidian-L7 Dental School Maxilla fixed notes, p.20 ↩
-
Original PDF page 21: No obsidian-L7 Dental School Maxilla fixed notes, p.21 ↩
-
Original PDF page 22: No obsidian-L7 Dental School Maxilla fixed notes, p.22 ↩
-
Original PDF page 23: No obsidian-L7 Dental School Maxilla fixed notes, p.23 ↩
-
Original PDF page 24: No obsidian-L7 Dental School Maxilla fixed notes, p.24 ↩
-
Original PDF page 25: No obsidian-L7 Dental School Maxilla fixed notes, p.25 ↩
-
Original PDF page 27: No obsidian-L7 Dental School Maxilla fixed notes, p.27 ↩
-
Original PDF page 26: No obsidian-L7 Dental School Maxilla fixed notes, p.26 ↩
-
Original PDF page 28: No obsidian-L7 Dental School Maxilla fixed notes, p.28 ↩
-
Original PDF page 29: No obsidian-L7 Dental School Maxilla fixed notes, p.29 ↩
-
Original PDF page 30: No obsidian-L7 Dental School Maxilla fixed notes, p.30 ↩
-
Original PDF page 31: No obsidian-L7 Dental School Maxilla fixed notes, p.31 ↩
-
Original PDF page 32: No obsidian-L7 Dental School Maxilla fixed notes, p.32 ↩
-
Original PDF page 33: No obsidian-L7 Dental School Maxilla fixed notes, p.33 ↩
-
Original PDF page 34: No obsidian-L7 Dental School Maxilla fixed notes, p.34 ↩
-
Original PDF page 35: No obsidian-L7 Dental School Maxilla fixed notes, p.35 ↩
-
Original PDF page 36: No obsidian-L7 Dental School Maxilla fixed notes, p.36 ↩
-
Original PDF page 37: No obsidian-L7 Dental School Maxilla fixed notes, p.37 ↩
-
Original PDF page 38: No obsidian-L7 Dental School Maxilla fixed notes, p.38 ↩
-
Original PDF page 39: No obsidian-L7 Dental School Maxilla fixed notes, p.39 ↩
-
Original PDF page 40: No obsidian-L7 Dental School Maxilla fixed notes, p.40 ↩
-
Original PDF page 41: No obsidian-L7 Dental School Maxilla fixed notes, p.41 ↩
-
Original PDF page 42: No obsidian-L7 Dental School Maxilla fixed notes, p.42 ↩
-
Original PDF page 43: No obsidian-L7 Dental School Maxilla fixed notes, p.43 ↩
-
Original PDF page 44: No obsidian-L7 Dental School Maxilla fixed notes, p.44 ↩
-
Original PDF page 45: No obsidian-L7 Dental School Maxilla fixed notes, p.45 ↩
-
Original PDF page 46: No obsidian-L7 Dental School Maxilla fixed notes, p.46 ↩
-
Original PDF page 47: No obsidian-L7 Dental School Maxilla fixed notes, p.47 ↩
-
Original PDF page 48: No obsidian-L7 Dental School Maxilla fixed notes, p.48 ↩
-
Original PDF page 49: No obsidian-L7 Dental School Maxilla fixed notes, p.49 ↩
-
Original PDF page 50: No obsidian-L7 Dental School Maxilla fixed notes, p.50 ↩
-
Original PDF page 51: No obsidian-L7 Dental School Maxilla fixed notes, p.51 ↩
-
Original PDF page 52: No obsidian-L7 Dental School Maxilla fixed notes, p.52 ↩
-
Original PDF page 53: No obsidian-L7 Dental School Maxilla fixed notes, p.53 ↩
-
Original PDF page 54: No obsidian-L7 Dental School Maxilla fixed notes, p.54 ↩
-
Original PDF page 55: No obsidian-L7 Dental School Maxilla fixed notes, p.55 ↩
-
Original PDF page 56: No obsidian-L7 Dental School Maxilla fixed notes, p.56 ↩
-
Original PDF page 57: No obsidian-L7 Dental School Maxilla fixed notes, p.57 ↩
-
Original PDF page 58: No obsidian-L7 Dental School Maxilla fixed notes, p.58 ↩
-
Original PDF page 59: No obsidian-L7 Dental School Maxilla fixed notes, p.59 ↩
-
Original PDF page 60: No obsidian-L7 Dental School Maxilla fixed notes, p.60 ↩
-
Original PDF page 61: No obsidian-L7 Dental School Maxilla fixed notes, p.61 ↩
-
Original PDF page 62: No obsidian-L7 Dental School Maxilla fixed notes, p.62 ↩
-
Original PDF page 63: No obsidian-L7 Dental School Maxilla fixed notes, p.63 ↩
-
Original PDF page 64: No obsidian-L7 Dental School Maxilla fixed notes, p.64 ↩
-
Original PDF page 65: No obsidian-L7 Dental School Maxilla fixed notes, p.65 ↩
-
Original PDF page 66: No obsidian-L7 Dental School Maxilla fixed notes, p.66 ↩
-
Original PDF page 67: No obsidian-L7 Dental School Maxilla fixed notes, p.67 ↩
-
Original PDF page 68: No obsidian-L7 Dental School Maxilla fixed notes, p.68 ↩
-
Original PDF page 69: No obsidian-L7 Dental School Maxilla fixed notes, p.69 ↩
-
Original PDF page 70: No obsidian-L7 Dental School Maxilla fixed notes, p.70 ↩
-
Original PDF page 71: No obsidian-L7 Dental School Maxilla fixed notes, p.71 ↩
-
Original PDF page 74: No obsidian-L7 Dental School Maxilla fixed notes, p.74 ↩
-
Original PDF page 72: No obsidian-L7 Dental School Maxilla fixed notes, p.72 ↩
-
Original PDF page 73: No obsidian-L7 Dental School Maxilla fixed notes, p.73 ↩
-
Original PDF page 75: No obsidian-L7 Dental School Maxilla fixed notes, p.75 ↩
-
Original PDF page 76: No obsidian-L7 Dental School Maxilla fixed notes, p.76 ↩
-
Original PDF page 77: No obsidian-L7 Dental School Maxilla fixed notes, p.77 ↩
-
Original PDF page 78: No obsidian-L7 Dental School Maxilla fixed notes, p.78 ↩
-
Original PDF page 79: No obsidian-L7 Dental School Maxilla fixed notes, p.79 ↩
-
Original PDF page 80: No obsidian-L7 Dental School Maxilla fixed notes, p.80 ↩
-
Original PDF page 81: No obsidian-L7 Dental School Maxilla fixed notes, p.81 ↩
-
Original PDF page 82: No obsidian-L7 Dental School Maxilla fixed notes, p.82 ↩
-
Original PDF page 83: No obsidian-L7 Dental School Maxilla fixed notes, p.83 ↩
-
Original PDF page 84: No obsidian-L7 Dental School Maxilla fixed notes, p.84 ↩
-
Original PDF page 85: No obsidian-L7 Dental School Maxilla fixed notes, p.85 ↩
-
Original PDF page 86: No obsidian-L7 Dental School Maxilla fixed notes, p.86 ↩
-
Original PDF page 87: No obsidian-L7 Dental School Maxilla fixed notes, p.87 ↩
-
Original PDF page 88: No obsidian-L7 Dental School Maxilla fixed notes, p.88 ↩
-
Original PDF page 89: No obsidian-L7 Dental School Maxilla fixed notes, p.89 ↩
-
Original PDF page 90: No obsidian-L7 Dental School Maxilla fixed notes, p.90 ↩
-
Original PDF page 91: No obsidian-L7 Dental School Maxilla fixed notes, p.91 ↩
-
Original PDF page 92: No obsidian-L7 Dental School Maxilla fixed notes, p.92 ↩
-
Original PDF page 93: No obsidian-L7 Dental School Maxilla fixed notes, p.93 ↩
-
Original PDF page 94: No obsidian-L7 Dental School Maxilla fixed notes, p.94 ↩
-
Original PDF page 95: No obsidian-L7 Dental School Maxilla fixed notes, p.95 ↩