Developing the Treatment Plan12
The University of Western Australia
DENT 4215 — Introduction to Clinical Dental Practice Presenter: Manorika Ratnaweera
Acknowledgement of Country
The University of Western Australia acknowledges that its campus is situated on Noongar land, and that Noongar people remain the spiritual and cultural custodians of their land, and continue to practise their values, languages, beliefs and knowledge.
Artist: Dr Richard Barry Walley OAM

Learning Outcomes and Objectives34
-
Compose and implement initial treatment plans to prepare patients for further dental treatment.
-
Develop fundamental knowledge necessary to begin creating treatment plans for patients
-
Documenting treatment plans
Introduction to Treatment Planning
Information Gathering and Diagnosis
Assessment and Data Collection5
- Patient history
- Radiographic examination
- Clinical examination
- Diagnostic aids
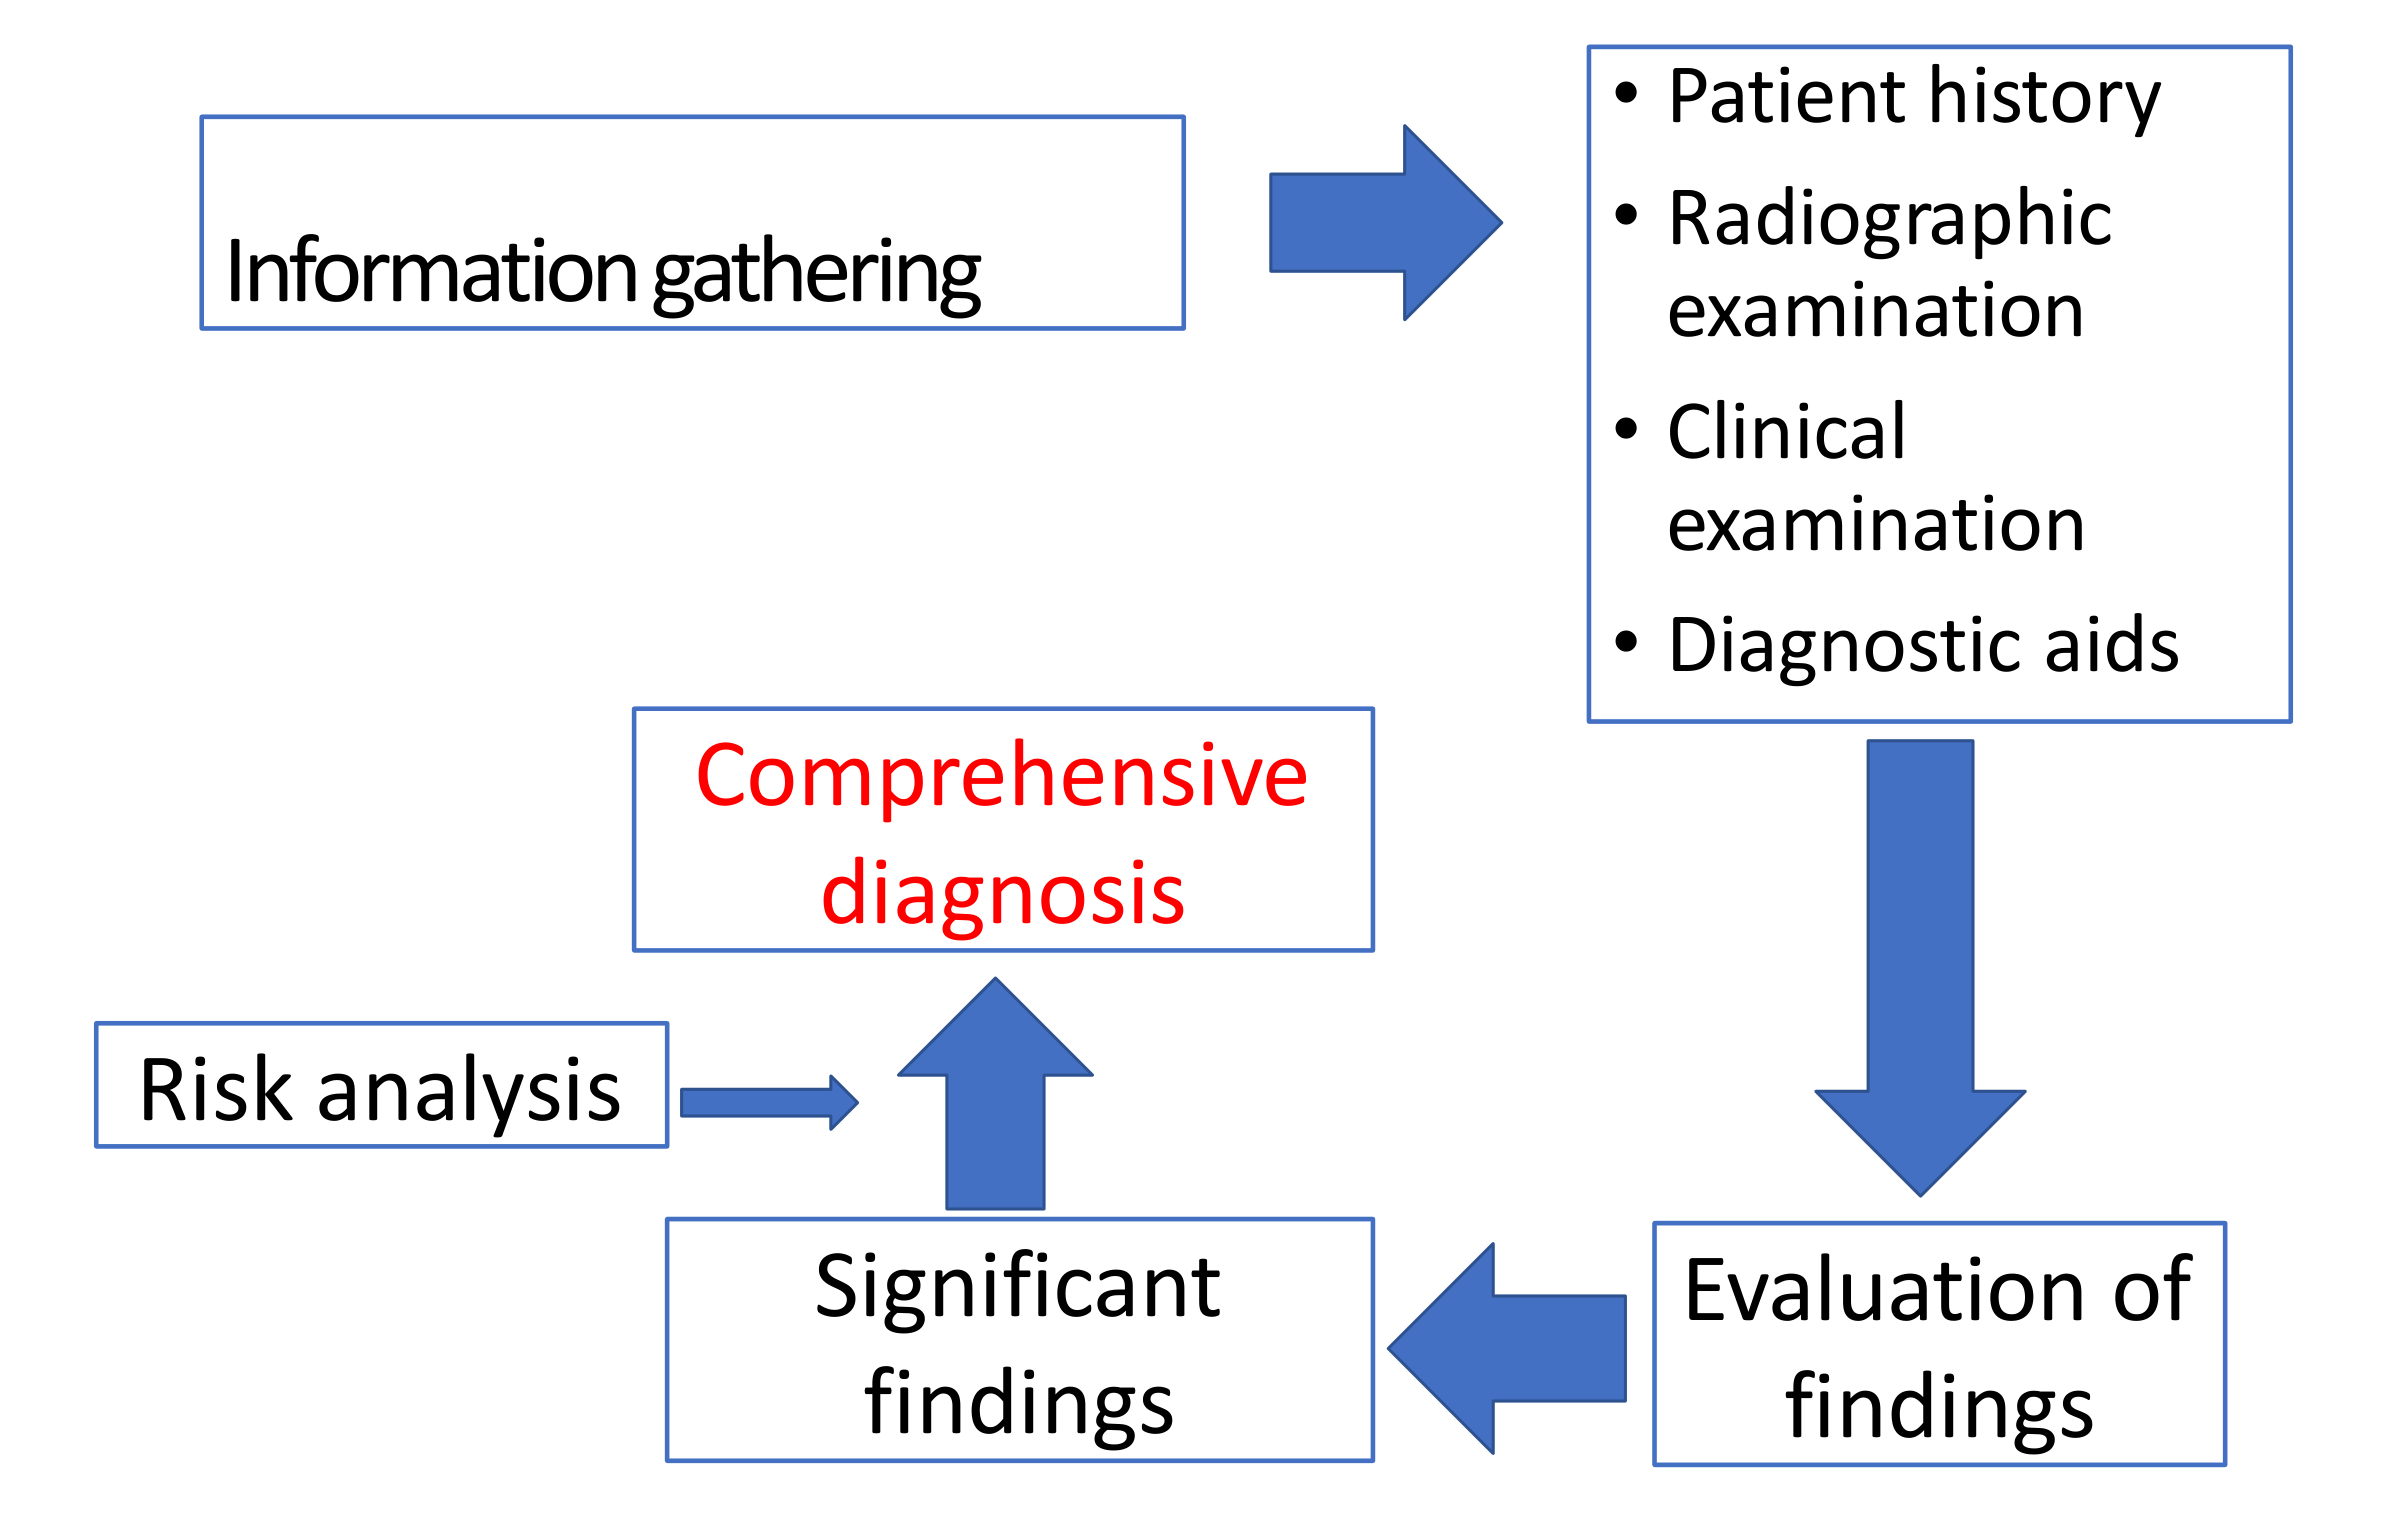
Diagnostic Evaluation
- Comprehensive diagnosis
- Risk analysis
- Significant findings
- Evaluation of findings
Diagnostic Categories6
- Definitive diagnosis: When several findings point clearly to a specific disease entity
- Differential diagnosis: When the findings suggest several possible conditions, the process of distinguishing among the list of possibilities
- Tentative diagnosis: When the diagnosis is uncertain, but it is prudent to begin some type of treatment
Treatment Objectives and the Treatment Plan
Key Components of Planning7
- Comprehensive diagnosis list
- Treatment objectives
- Patient modifiers
- Practitioner modifiers
- Treatment plan(s)
- Informed consent
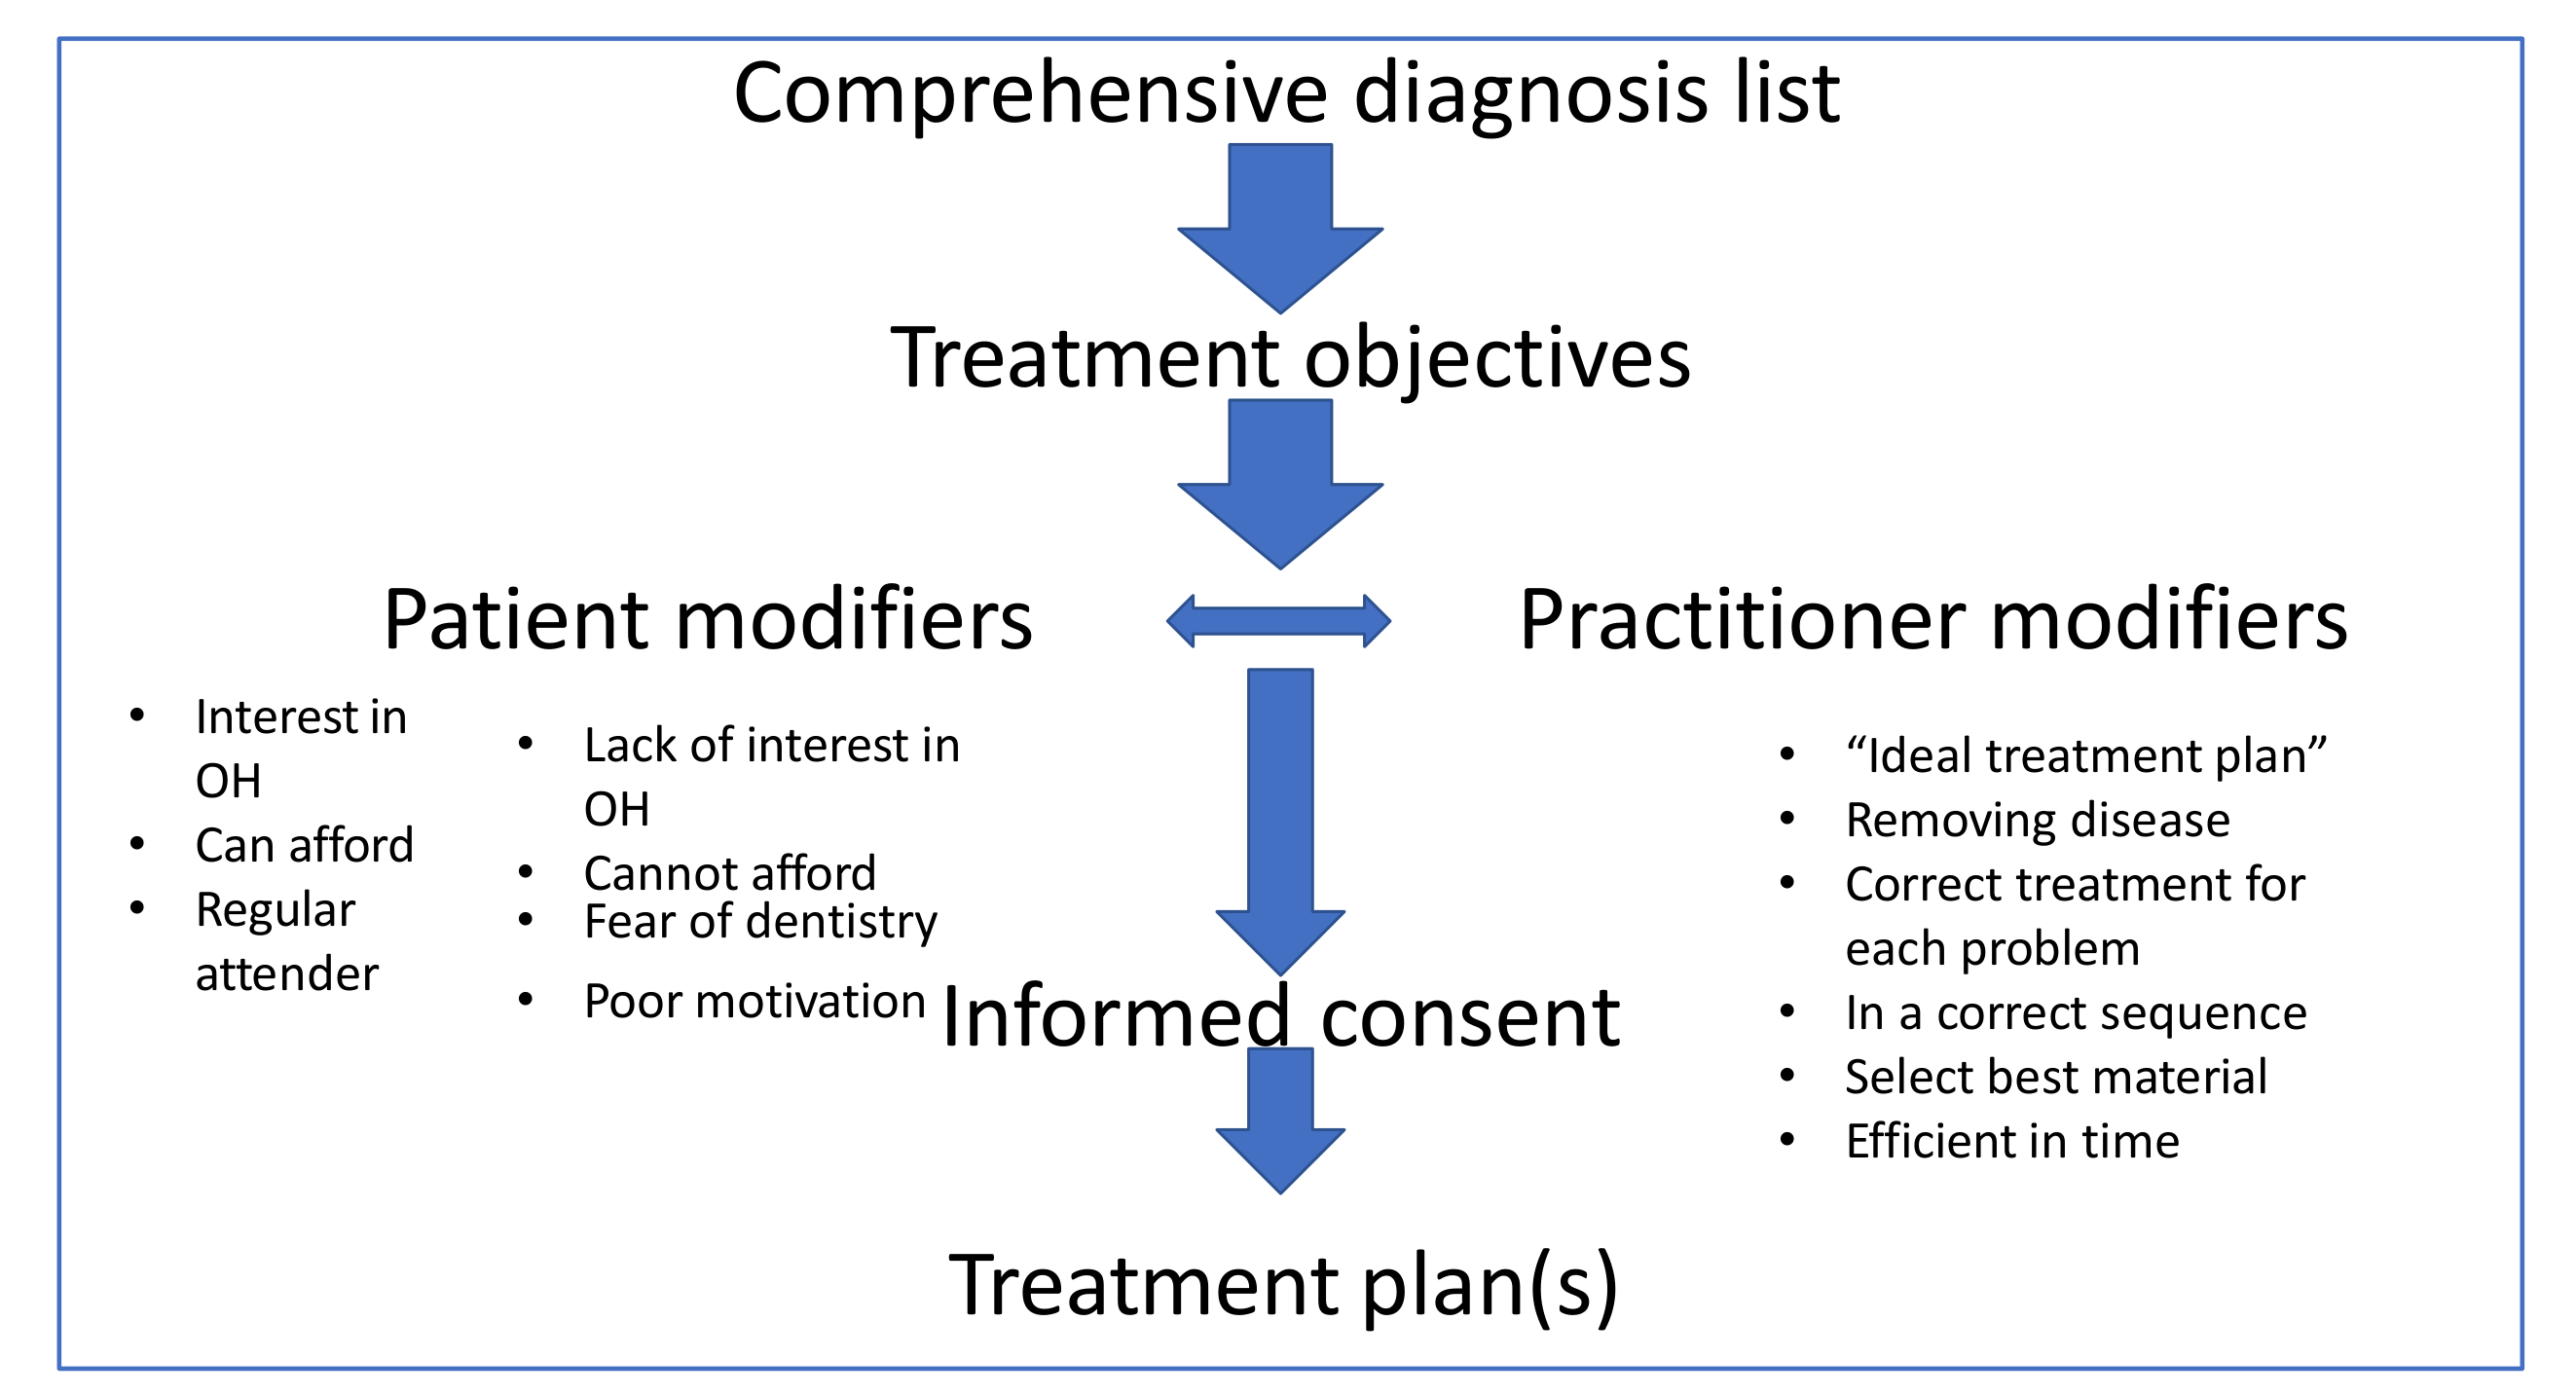
Patient Modifiers
- Interest in OH
- Can afford
- Regular attender
- Lack of interest in OH
- Cannot afford
- Fear of dentistry
- Poor motivation
Ideal Treatment Plan Goals
- Removing disease
- Correct treatment for each problem
- In a correct sequence
- Select best material
- Efficient in time
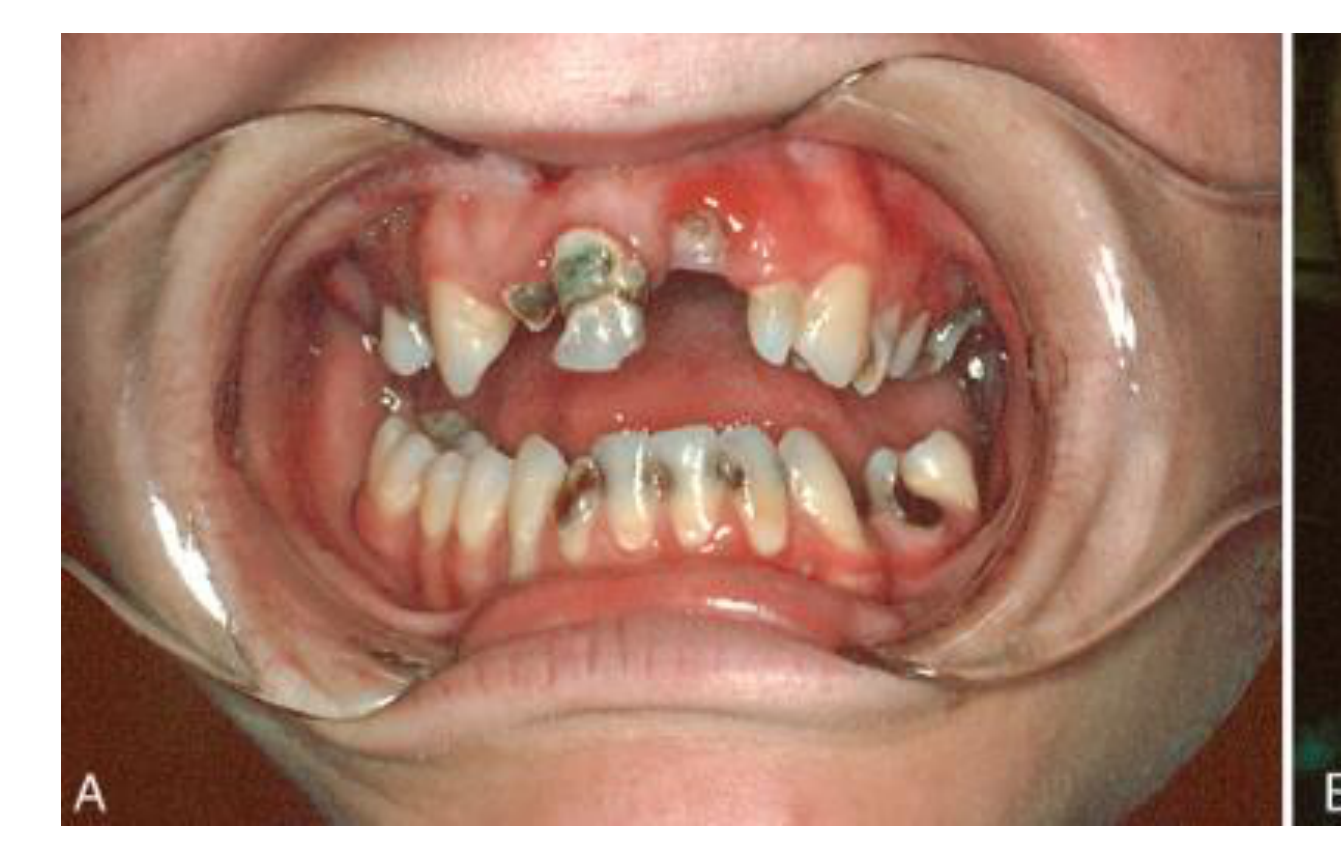
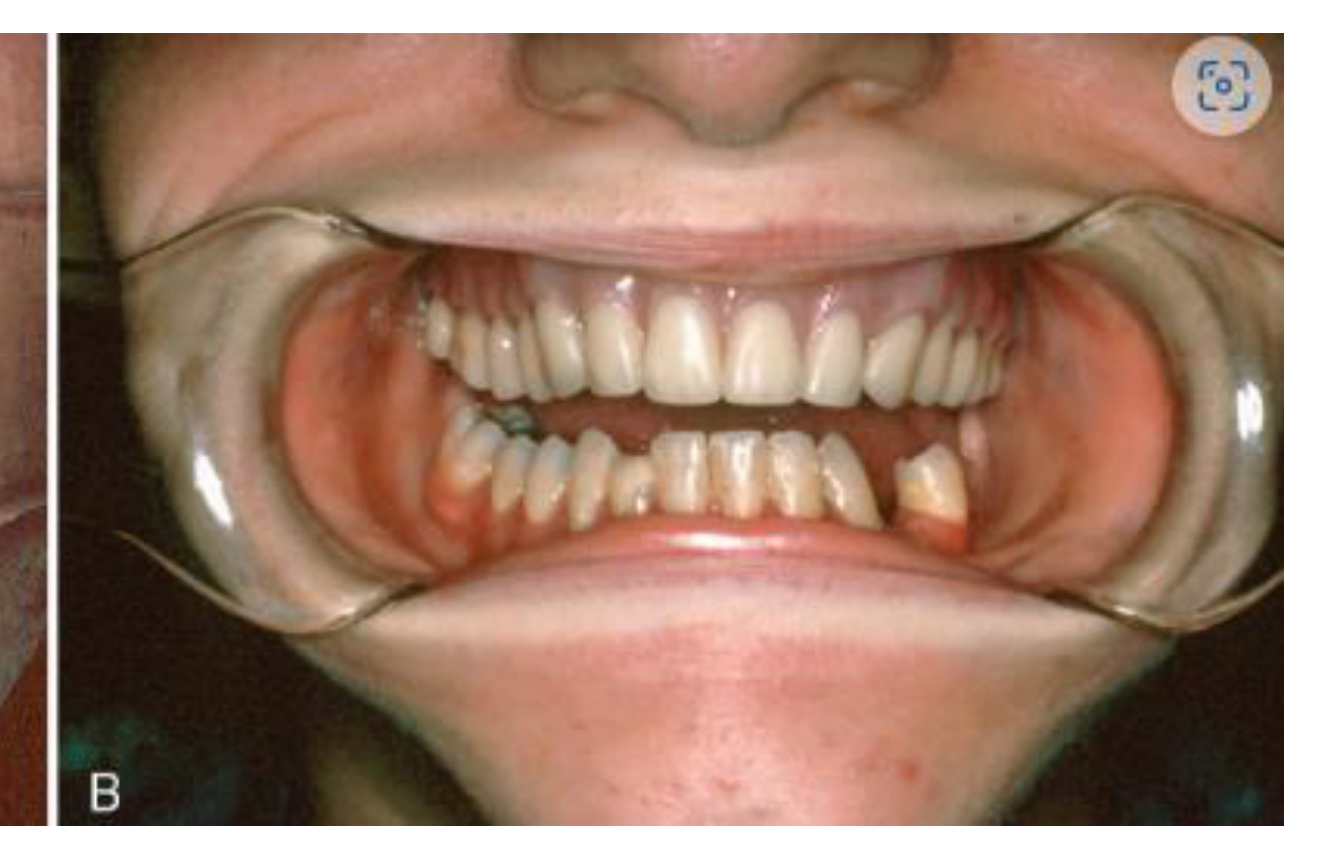
Treatment Objectives8
“…is a carefully sequenced series of services designed to eliminate or control etiological factors, repair existing damage and create a functional maintainable environment.”
Sturdevant 1995
 |  |
Core Principles9
- Created as a response to the problem list
- The schedule and sequence of the treatment
- Developing a course of action that encompasses the ramifications and sequalae of treatment to serve patients’ needs
Purpose of a Treatment Plan10
- Address patient’s problem/s
- Sequence and prioritise
- Estimates of costs
- Informed consent
- Record keeping
- Medico-Legal requirement
- Communication with other clinicians
Phases of the Treatment Plan11
- Systemic phase
- Acute phase
- Disease Control phase
- Definite phase
- Maintenance phase
Systemic Phase of Treatment Planning12
- To evaluate the severity and complexity of health issues and to assess how this may affect dental treatment
- Recognize signs and symptoms of undiagnosed conditions and refer patient to physician for evaluation
- To limit or modify dental treatment based on systemic findings
- To prevent adverse outcomes:
- Emergencies in the dental office
- To prevent serious postoperative complications in conjunction with dental treatment
Example: Antibiotic prophylaxis for high-risk dental procedures in specific medical conditions.
- The systemic phase is completed before addressing the patient’s acute complaint or other treatment needs.
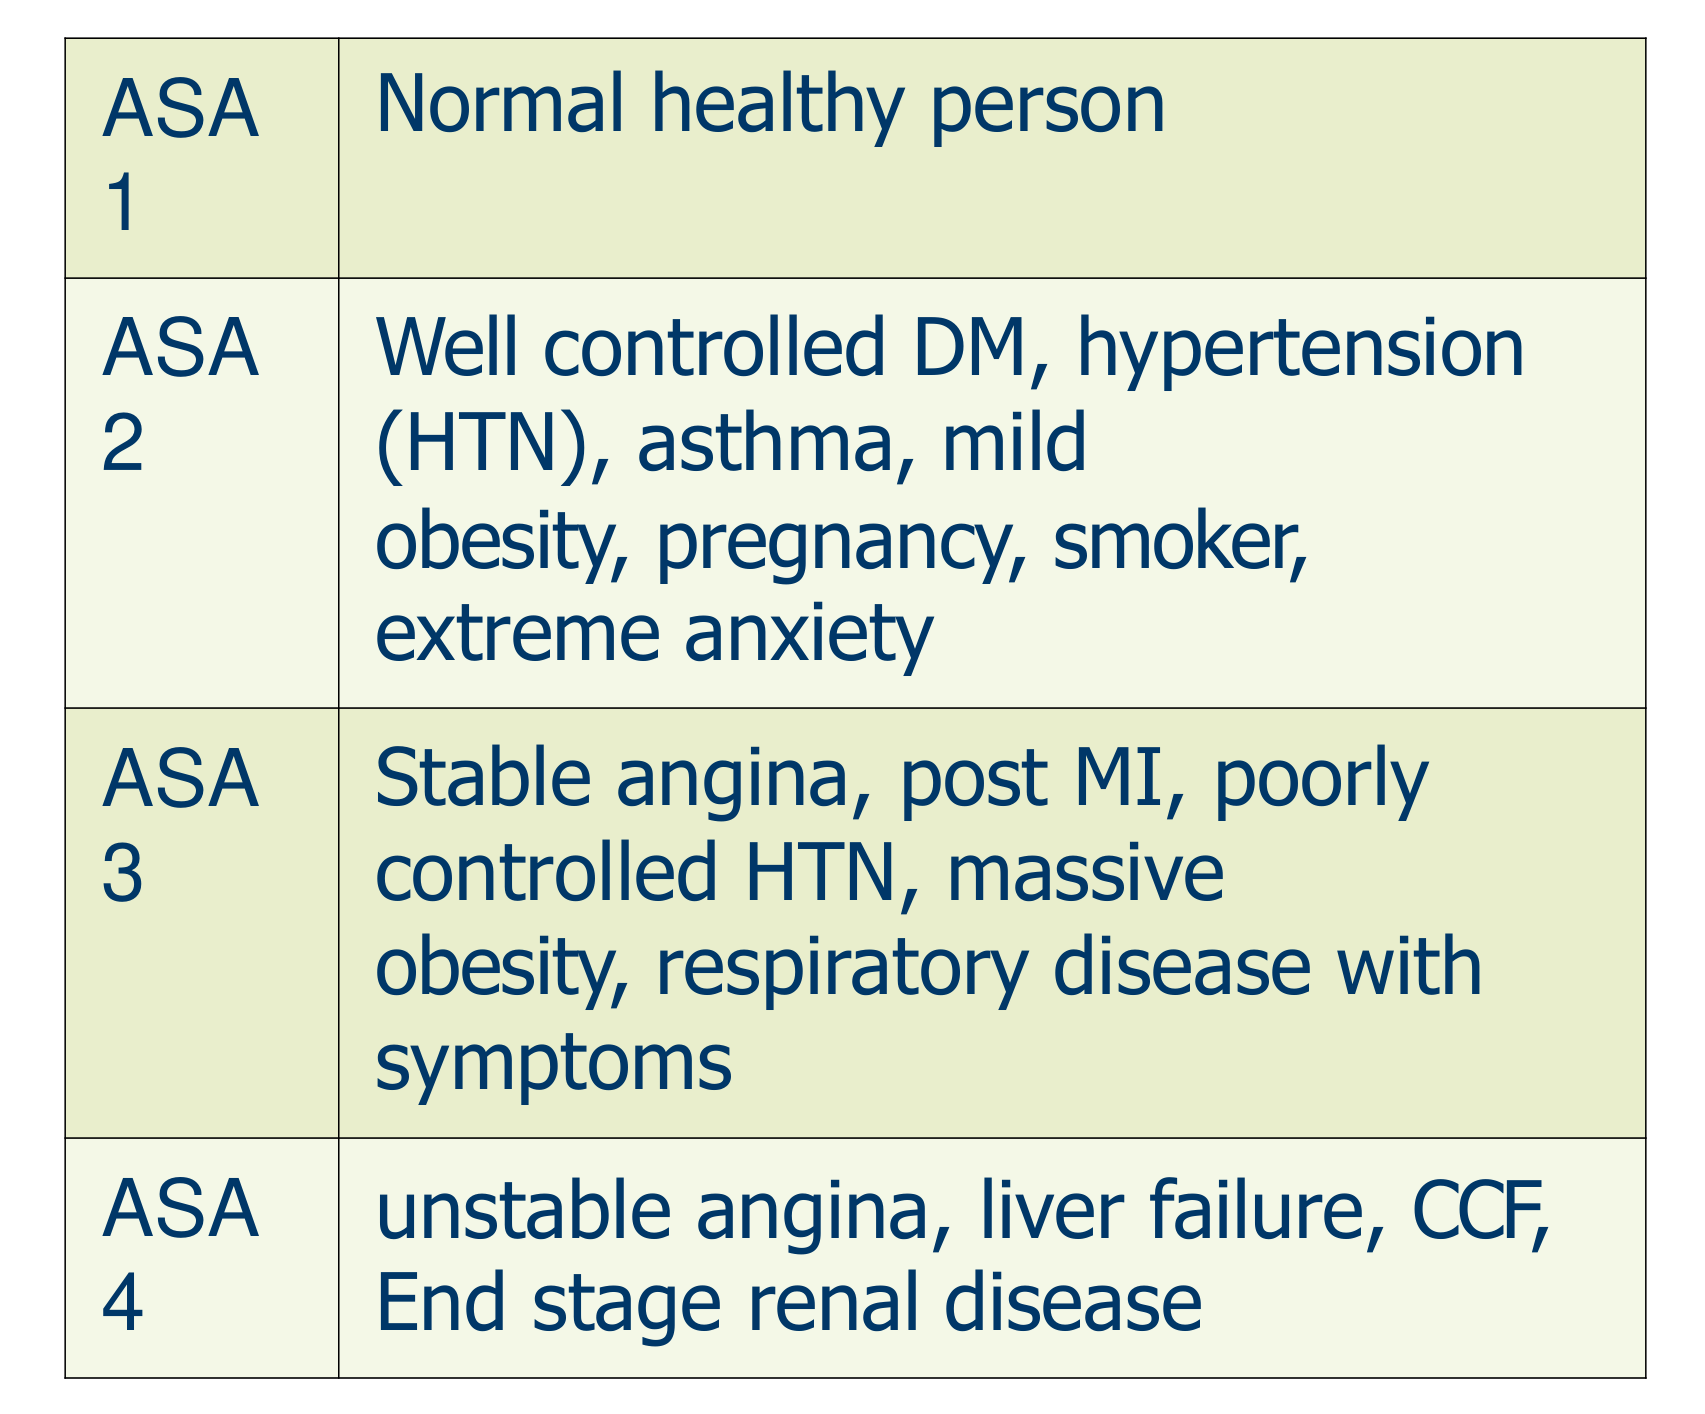
ASA Physical Status Classification13
| Classification | Description |
|---|---|
| ASA 1 | Normal healthy person |
| ASA 2 | Well-controlled DM, hypertension (HTN), asthma, mild obesity, pregnancy, smoker, extreme anxiety |
| ASA 3 | Stable angina, post-MI, poorly controlled HTN, massive obesity, respiratory disease with symptoms |
| ASA 4 | Unstable angina, liver failure, CCF, end-stage renal disease |
Limiting and Modifying Treatment14
- Postponing or limiting treatment
- Examples: Uncontrolled hypertension, INR levels, antibiotic prophylaxis, unstable angina
- Consultation with physician:
- Prescribing or altering patient medication
- Managing hypertension
- When systemic disease is suspected in the dental office
- Stress management (cardiac disease, diabetes, unstable angina, adrenal disorders)
- Positioning the patient in dental chair
Lecturer — Medication Considerations
The patient’s medical condition and medications may affect the safety and appropriateness of dental treatment.
- If a patient is taking medication and presents with a tooth that may need to be extracted for pain relief, the implications of that medication must be considered before proceeding.
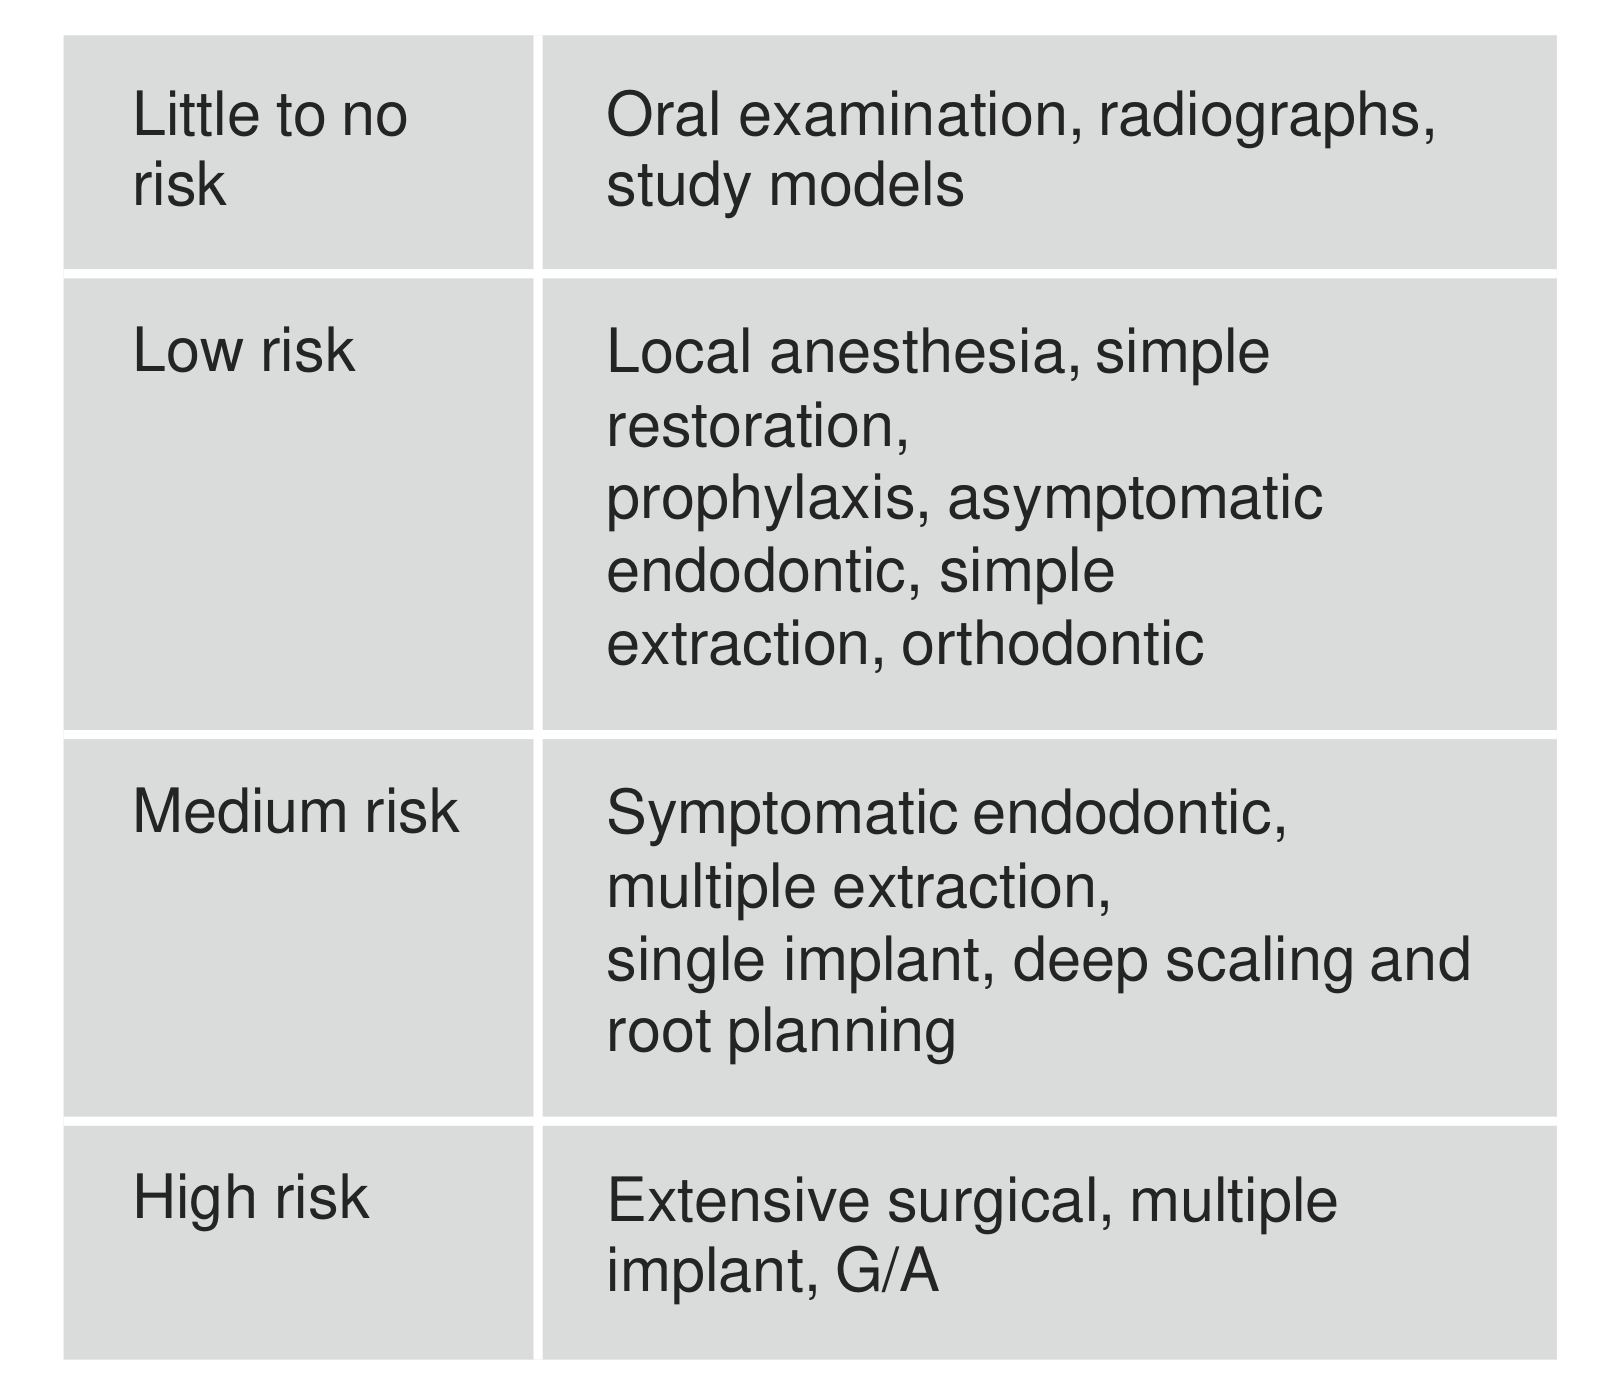
Risk Categories for Dental Procedures15
| Risk Level | Procedures |
|---|---|
| Little to no risk | Oral examination, radiographs, study models |
| Low risk | Local anesthesia, simple restoration, prophylaxis, asymptomatic endodontic, simple extraction, orthodontic |
| Medium risk | Symptomatic endodontic, multiple extraction, single implant, deep scaling and root planing |
| High risk | Extensive surgical, multiple implant, G/A |
Acute Phase of Treatment Planning
The acute phase of care incorporates diagnostic and treatment procedures aimed at solving urgent oral problems.
Patients Who May Need Acute Care16
- Those under active treatment
- On maintenance recall
- New to dental practice
- Returning to practice after being away for some length of time
Lecturer — Systemic Phase
The acute complaint must be managed, but the systemic phase must still be completed first.
- The patient’s medical condition and medications may affect management of the acute problem.
Emergency and Urgent Problems
Categorization of Problems17
-
Emergency problem: Incapacitates the patient and has the potential to become a life-threatening condition.
- Examples: Swelling, systemic infection, trauma to face or jaws
-
Urgent problem: Does not require immediate attention, but the dentist or the patient believes it should be attended to “now” or “soon”.
- Examples: Mild to moderate pain without active infection
Lecturer — Systemic Status
Acute treatment may be required to address an immediate patient concern, such as pain.
- The treatment must be considered within the context of the patient’s systemic status.
Common Acute Problems and Diagnoses
Complaint of Pain18
- Pulpal or periapical origin
- Associated with periodontal tissues:
- Periodontal abscess
- Necrotizing ulcerative gingivitis (NUG)
- Associated with tooth eruption or pericoronitis
- Associated with previous dental treatment
- Other sources of pain:
- Herpetic ulcers
- Traumatic ulcers
- Stomatitis
- Temporomandibular joint (TMJ) disorders
- Trigeminal neuralgia
- Acute sinusitis
Lecturer — Painful Tooth Management
A patient may present with a painful tooth that appears to require extraction or another immediate intervention. Before providing treatment intended to relieve the pain, the dentist must consider:
- The patient’s systemic condition.
- The medications the patient is taking.
- The possible implications of those medications for the proposed treatment.
Complaint of Swelling
- Aesthetic complaints
- Traumatic injury:
- Trauma to teeth/soft tissues
- Jawbone fractures
- Osteomyelitis
Other Forms of Oral Pathology
- Lesions that require biopsy, consultation, or referral
Treatment Planning Considerations19
- Short-term therapies within clinician competency
- Long-term implications of short-term therapies or options
- Factors influencing treatment decisions:
- Professional factors
- Patient factors and modifiers
- Combination factors
Consent, Referral and Deferral in Acute Care
Acquiring Consent for Acute Care20
Informed consent for an acute care treatment plan requires that the patient must be fully aware of:
- The diagnosis
- All reasonable treatment options
- Risks and benefits of each option
- Nature of the recommended treatment
- Costs of that treatment—present and future
Indications for Referral or Deferral21
- The problem or the offending tooth cannot be identified.
- The patient has a compromising systemic condition that precludes treatment at this time.
- The patient has an active infection.
- The patient is unwilling or unable to provide consent to treatment.
In some situations, it is not only prudent but also preferable to prescribe medications rather than initiate treatment.
Disease Control Phase of Treatment Planning22
Objectives23
- Eradicate active disease and infection
- Arrest occlusal, functional, and esthetic deterioration
- Address, control, or eliminate causes and risk factors for future disease
The disease control phase is indicated in a patient with high risk factors for that particular disease.
- Also called the Stabilisation phase
- Not necessary when:
- Oral disease is controlled
- Oral disease will be eliminated during definitive treatment
- Includes plans for:
- Management of active disease or infection
- Stabilization of disease/teeth status prior to definitive reconstruction
- Modification or elimination of risk factors that predispose the patient to the development of recurrent oral disease
Sequencing the Disease Control Phase24
-
Address the patient’s chief complaint as early in the plan as possible
-
Sequence by priority: Preferably treat the most severe and urgent needs first (e.g., provisional or protective restorations)
-
Sequence by quadrant or sextant
-
Integrate periodontal therapy into the disease control phase plan
-
Keep definitive phase options open with minimalist treatment in the disease control phase
- Generally, only those procedures necessary to arrest deterioration and prevent further infection should be undertaken in the disease control phase.
-
The patient’s overall condition should be assessed before deciding which problem to address first, so the chief complaint may not always determine the first treatment.
Structure of the Disease Control Phase25
- Education
- Aetiology, prevention, and home treatment for dental conditions
- Patient roles and responsibilities
- Oral hygiene product education and advice (type, technique, frequency)
- Smoking cessation (ask, assess, assist)
- Chemotherapeutics
- NSPT (Non-Surgical Periodontal Therapy)
- Plaque control
- Debridement and prophylaxis
- Manage risk factors
- Review, with referral to a periodontist if required
- Caries management
- Remineralisation therapy
- Defective restorations
- Extraction/referral
Lecturer — Periodontal Referral
Periodontal treatment may already have been completed if the patient was referred after that phase.
- Periodontal treatment may still need to be provided as part of the current patient’s disease control plan.
Caries Management System
Basic Caries Control Protocol26
- Caries activity tests, diagnosis, and risk assessment
- Oral prophylaxis
- Oral self-care instructions and coaching
- Saliva substitutes and stimulation
- Remineralisation (in-clinic and home care)
- Chemotherapeutics
- Diet and nutrition analysis
- Food diary: assess frequency and duration of exposure to acids and sucrose
- Restore carious lesions
- Sealants on susceptible pits and fissures
- Reassessment
Lecturer — Carious Lesions
A large carious cavity may take priority over other conditions depending on the severity and extent of disease.
- A provisional protective restoration may be used before periodontal treatment or other procedures when necessary.
Oral Disease Risk Status27
- Caries risk: CAMBRA
- Periodontal risk: http://www.perio-tools.com/PRA/en/index.asp
- Oral cancer risk: Oral Mucosal Malignancies, Contemporary Oral Medicine. 2018:1249–1436.
- Tooth wear risk: BEWE (http://www.erosivetoothwear.co.uk/page/knowledge_base)
Re-Evaluation Phase28
Also referred to as the Holding phase.
- The period between the control and definitive phases that allows for the resolution of inflammation and time for healing.
- Home care habits are reinforced, motivation for further treatment is assessed, and initial treatment and pulpal responses are re-evaluated before definitive care begins.
Lecturer — Re-Evaluation Examples
Re-evaluation determines whether treatment has been effective before progressing to definitive care.
- After endodontic treatment, an appropriate period may be allowed before obturation or subsequent treatment.
- After periodontal treatment, probing depths are reassessed to determine whether they have reduced and whether treatment has worked.
Lecturer — Denture Planning
When planning a denture, the dentist must first determine whether it will be tooth supported, tissue supported, or mixed tooth and tissue supported.
- This decision depends on whether the patient’s dentition is stable and whether additional tooth loss is likely.
- The appropriate denture type should be considered in light of the expected future condition and its associated costs.
- The patient should receive an estimate and a general explanation of the proposed approach; detailed design features such as rest seats can wait until the final design is established.
Definitive Phase of Treatment29
The definitive phase serves as the core of the treatment plan.
Before engaging in definitive phase treatment, the practitioner should affirm that:
- Disease is controlled.
- All reasonable definitive phase treatment options and costs have been evaluated and discussed with the patient.
- Informed consent is obtained with the patient.
Lecturer — Treatment Options
Treatment options should not be introduced for the first time after treatment has begun.
- For a tooth with a large restoration, the possibility of a crown should be discussed during treatment planning, even if repairing the existing restoration is also considered.
Common Definitive Phase Treatments30
- Periodontal therapy (surgical / other)
- Orthodontic treatment
- Restorative dentistry
- Multi-surface restorations / indirect restorations
- Occlusal assessment and treatment
- Esthetical procedures
- Endodontic procedures (elective)
- Extractions (third molar) and pre-prosthetic procedures
- Prosthodontics assessment and treatment
- Replacement of missing teeth
- Indication for the need of a crown, bridge, implant, or dentures
- Denture assessment and treatment
- Specialist care
Shared Decision Making and Prognosis
- Involve patient/parent in decision making
- Clinicians’ role to determine reasonable and feasible treatment options
Professional Considerations31
- Diagnosis
- Prognosis: Prediction or estimation of the likelihood of a favorable outcome for a disease (could be: Excellent, Good, Favorable, Unfavorable, Poor)
- Likelihood of remineralisation
- Caries risk status
- Disease control phases
- Cost and patient expectations
- Materials, outcomes, and implications
Referral to Specialists32
Orthodontic Treatment33
-
Dentist role to identify if referral for orthodontic assessment is required
-
Usually elective treatment for aesthetics or function
-
Common indications for referral:
- Malocclusions
- Impacted teeth
- Anterior open bite
- Skeletal abnormalities
-
Referral for orthodontic assessment by an orthodontist
-
Periodontist: Dentists should be able to identify if referral to a periodontist is required
-
Prosthodontist: Fixed prosthodontics, removable prosthodontics, implants
-
Paedodontist: Dentists should be able to identify if referral to a paedodontist is required
-
Special care dentist: Dentists should be able to identify if referral to a specialist is required
-
Other specialists
Maintenance Phase34
- The long-term success or failure of the plan depends on it.
- Prevention of future problems is the guiding principle of the maintenance phase, and it is the responsibility of the entire dental team.
- Made on an individual basis.
- Established at the conclusion of the disease control phase and definitive phases of treatment.
- Can be modified as needed.
Rationale and Benefits of Maintenance
Purpose of Maintenance Phase35
- Ensure long-term oral health
- Optimum function
- Favorable esthetics for the patient
- Maintain stable clinical attachment levels
Lang, N. P., & Tonetti, M. S. (2003).
Lecturer — Maintenance Importance
Maintenance is essential for preserving the results of treatment. If maintenance is neglected, the treatment may fail to provide lasting benefit, and the patient may return in a condition similar to that at the initial visit.
Benefits of Maintenance Phase
- Address issues that remain unresolved after the definitive phase of treatment
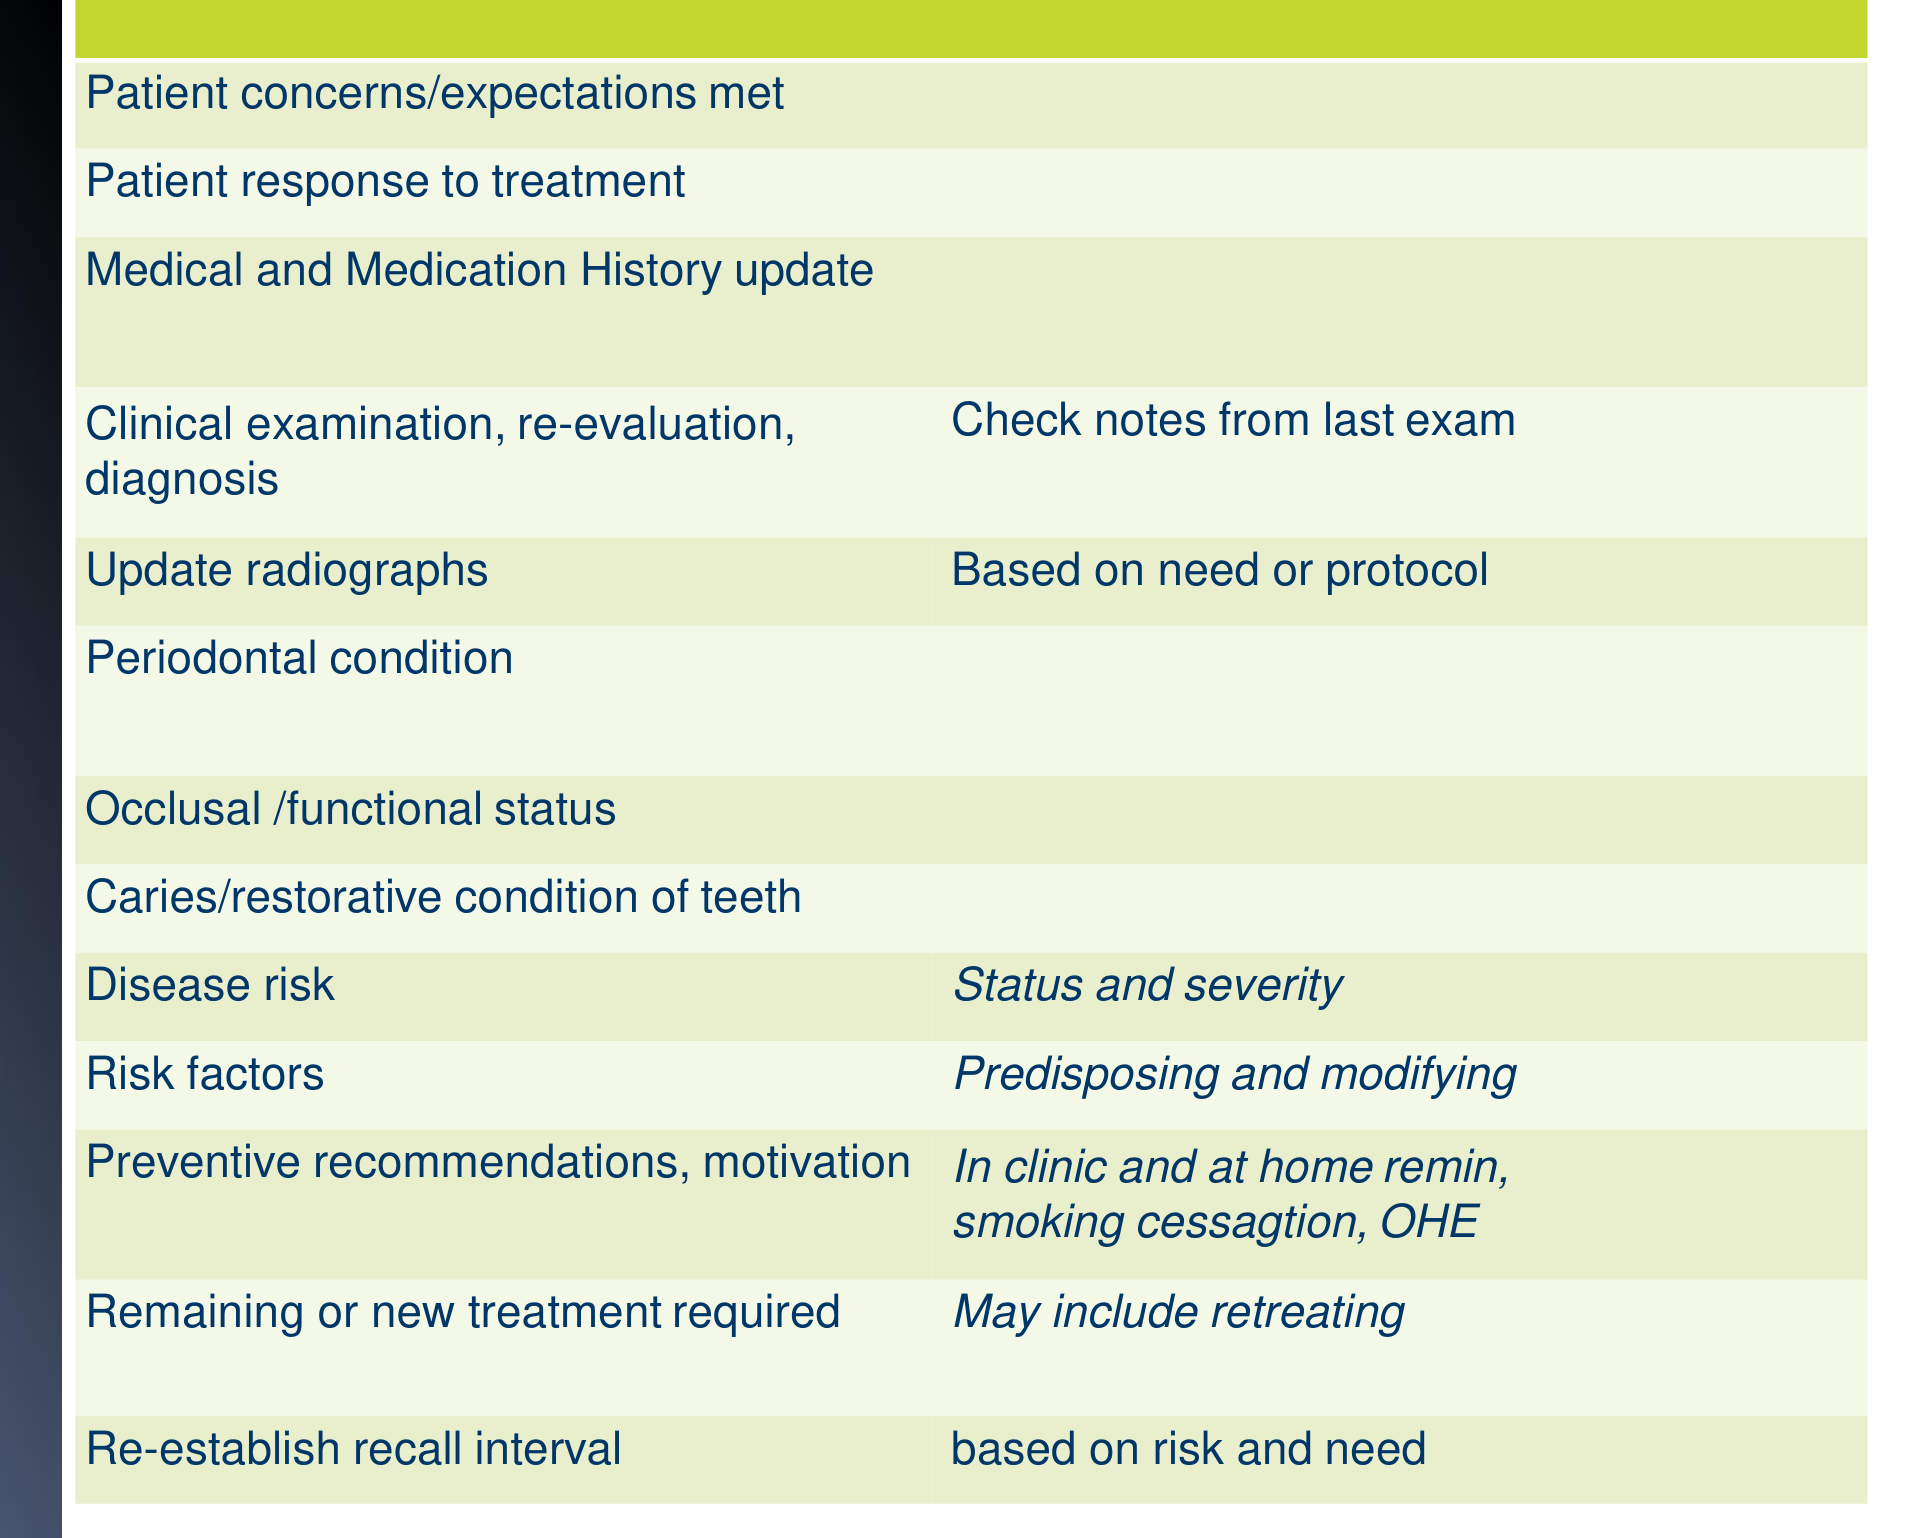
Maintenance Visit Assessment36
| Assessment Component | Details / Notes |
|---|---|
| Patient concerns/expectations met | |
| Patient response to treatment | |
| Medical and medication history update | |
| Clinical examination, re-evaluation, diagnosis | Check notes from last exam |
| Update radiographs | Based on need or protocol |
| Periodontal condition | |
| Occlusal / functional status | |
| Caries / restorative condition of teeth | |
| Disease risk | Status and severity |
| Risk factors | Predisposing and modifying |
| Preventive recommendations, motivation | In clinic and at-home remineralization, smoking cessation, OHE |
| Remaining or new treatment required | May include retreating |
| Re-establish recall interval | Based on risk and need |
Treatment Plan Outcomes37
- Patient + clinician = disease is controlled, dentition is functional, stable, and of acceptable aesthetics
- Specific tangible results of treatment
- Closely linked to:
- Risk assessment
- Prognosis determination
Lecturer — Continued Maintenance
The success of treatment depends on continued maintenance after the active treatment phases have been completed. Without maintenance, the patient’s oral condition may deteriorate and the benefits of the completed treatment may be lost.
Summary of Treatment Planning38

I. Systemic Treatment39
- Consultation with patient’s healthcare provider
- Premedication
- Stress and fear management
- Special positioning of the patient
- Any necessary treatment considerations for systemic disease
Lecturer — Systemic Assessment
Complete the systemic assessment before addressing the acute complaint. Identify medical conditions and medication-related considerations, and postpone or limit treatment when necessary.
- Consult the patient’s physician regarding medication changes or prescribing.
- Use stress-management and medical-emergency prevention strategies.
- Be prepared to manage an emergency and position the patient according to the patient’s condition.
II. Acute Treatment40
- Emergency treatment for pain or infection
- Treatment of the urgent chief complaint when possible
Lecturer — Acute Treatment
Address acute problems only after considering the patient’s systemic status. Consider the implications of the patient’s medications before treatment.
III. Disease Control41
- Caries removal to determine restorability of questionable teeth
- Extraction of hopeless or problematic teeth
- Possible provisional replacement of teeth
- Periodontal disease control
- Oral hygiene instruction
- Initial therapy:
- Scaling and root planning, prophylaxis
- Controlling other contributing factors:
- Replace defective restorations, remove caries
- Reduce or eliminate parafunctional habits, smoking
- Caries control
- Caries risk assessment
- Provisional (temporary) restorations
- Definitive restorations (i.e., amalgam, composite, glass ionomers)
- Replace or repair defective restorations
- Endodontic therapy for pathologic pulpal or periapical conditions
- Stabilization of teeth with provisional or foundation restorations
- Posttreatment assessment
IV. Definitive Treatment42
- Advanced periodontal therapy
- Stabilize occlusion (vertical dimension of occlusion, anterior guidance, and plane of occlusion)
- Orthodontic and/or orthognathic surgical treatment
- Occlusal adjustment
- Esthetic dentistry (i.e., tooth whitening, esthetic restorations)
- Definitive restoration of individual teeth (direct/indirect)
- For endodontically treated teeth
- For key teeth
- Other teeth
- Elective extraction of asymptomatic teeth
- Replacement of missing teeth
- Fixed partial dentures, implants
- Removable partial dentures
- Complete dentures
- Posttreatment assessment
Lecturer — Disease Control Goals
Disease control should stabilize the patient and arrest occlusal, functional, and aesthetic deterioration. Treatment should control or eliminate causes and risk factors for future disease, with sequencing according to priority.
- Re-evaluate the patient’s response before proceeding to definitive treatment.
Lecturer — Definitive Treatment Planning
Definitive treatment begins after disease control and stabilization. Discuss treatment options and costs, and provide informed consent before treatment.
- Present appropriate alternatives, such as restoration repair or crown treatment.
- For dentures, determine whether support will be tooth-based, tissue-based, or mixed.
- Consider the stability of the dentition and possible future tooth loss.
- Provide the patient with a general estimate and explanation of the planned treatment.
“I NEVER TRUSTED A MAN WHO WEARS A MASK.” — Coleman
V. Maintenance Therapy43
- Periodic visits
Lecturer — Maintenance Goals
Maintenance therapy is intended to maintain long-term oral health, preserve optimum function and favourable aesthetics, and maintain stable clinical attachment levels. It should prevent the patient from returning to a condition similar to that at the initial visit.
“First, let’s get you nice and numb for this procedure.”
No dental care and treatment even when provided by a clinically competent dentist, however excellent in a technical sense, has any real value unless it serves the best interest of the patient…
References44
Stefanac, S. & Nesbit, S. (2024). Diagnosis and Treatment Planning in Dentistry (4th Ed.). Mosby Elsevier.
Audio Appendix
Additional Audio Content
The following sections from the lecture audio did not correspond to any heading in the main document.
Objectives
The disease control phase was identified as one of the most important parts of treatment planning. It may also be understood as the stabilization phase, because its purpose is to stabilize the patient before definitive treatment.
Its objectives include:
- Detecting active disease and infection.
- Managing active disease and infection.
- Arresting occlusal, functional, and aesthetic deterioration.
- Controlling or eliminating causes and risk factors for future disease.
- Incorporating prevention into treatment.
- Modifying risk factors according to the patient’s risk status.
- Stabilizing the patient before proceeding to definitive treatment.
The two main concerns emphasized were active disease and infection, together with the additional measures required to prevent further deterioration.
Case Study: Chief Complaint Compared with Other Findings
A patient may present with a specific complaint, such as needing a crown. During assessment, the dentist may also identify a carious cavity on another tooth.
The treatment sequence must then be considered carefully:
- The dentist should not automatically treat only the tooth identified in the chief complaint.
- The severity and size of the other carious lesion must be compared with the need for the crown.
- The most urgent or severe problem may need to be addressed first.
- The appropriate sequence depends on the patient’s overall disease status and treatment priorities.
Risk Management in the Dental Office
The dental team should be prepared to prevent and manage medical emergencies in the dental office. This includes knowing:
- How to reduce the risk of an emergency occurring.
- How to respond if an emergency occurs.
- How to manage the patient according to the patient’s condition.
- How to position the patient appropriately.
Sequencing Periodontal Therapy and Prosthetic Treatment
Periodontal disease is chronic and may require considerable time to complete all phases of treatment. Treatment planning should therefore remain practical and efficient.
For a patient who needs both periodontal treatment and a denture:
- Periodontal treatment may be started as part of the disease control phase.
- Impressions for the denture may be initiated while periodontal treatment is continuing, when appropriate.
- This avoids unnecessarily delaying the prosthetic phase until all periodontal treatment has been completed.
- The patient’s caries and other restorative needs must also be considered before finalizing the prosthetic treatment.
- More complex situations, such as collapse of occlusal vertical dimension or other complicated spaces, require separate consideration.
Footnotes
-
Original PDF page 1: w2.3 Developing the Treatmentplan, p.1 ↩
-
Original PDF page 2: w2.3 Developing the Treatmentplan, p.2 ↩
-
Original PDF page 3: w2.3 Developing the Treatmentplan, p.3 ↩
-
Original PDF page 4: w2.3 Developing the Treatmentplan, p.4 ↩
-
Original PDF page 5: w2.3 Developing the Treatmentplan, p.5 ↩
-
Original PDF page 6: w2.3 Developing the Treatmentplan, p.6 ↩
-
Original PDF page 7: w2.3 Developing the Treatmentplan, p.7 ↩
-
Original PDF page 8: w2.3 Developing the Treatmentplan, p.8 ↩
-
Original PDF page 9: w2.3 Developing the Treatmentplan, p.9 ↩
-
Original PDF page 10: w2.3 Developing the Treatmentplan, p.10 ↩
-
Original PDF page 11: w2.3 Developing the Treatmentplan, p.11 ↩
-
Original PDF page 12: w2.3 Developing the Treatmentplan, p.12 ↩
-
Original PDF page 13: w2.3 Developing the Treatmentplan, p.13 ↩
-
Original PDF page 14: w2.3 Developing the Treatmentplan, p.14 ↩
-
Original PDF page 15: w2.3 Developing the Treatmentplan, p.15 ↩
-
Original PDF page 16: w2.3 Developing the Treatmentplan, p.16 ↩
-
Original PDF page 17: w2.3 Developing the Treatmentplan, p.17 ↩
-
Original PDF page 18: w2.3 Developing the Treatmentplan, p.18 ↩
-
Original PDF page 19: w2.3 Developing the Treatmentplan, p.19 ↩
-
Original PDF page 20: w2.3 Developing the Treatmentplan, p.20 ↩
-
Original PDF page 21: w2.3 Developing the Treatmentplan, p.21 ↩
-
Original PDF page 23: w2.3 Developing the Treatmentplan, p.23 ↩
-
Original PDF page 22: w2.3 Developing the Treatmentplan, p.22 ↩
-
Original PDF page 24: w2.3 Developing the Treatmentplan, p.24 ↩
-
Original PDF page 25: w2.3 Developing the Treatmentplan, p.25 ↩
-
Original PDF page 26: w2.3 Developing the Treatmentplan, p.26 ↩
-
Original PDF page 27: w2.3 Developing the Treatmentplan, p.27 ↩
-
Original PDF page 28: w2.3 Developing the Treatmentplan, p.28 ↩
-
Original PDF page 29: w2.3 Developing the Treatmentplan, p.29 ↩
-
Original PDF page 30: w2.3 Developing the Treatmentplan, p.30 ↩
-
Original PDF page 31: w2.3 Developing the Treatmentplan, p.31 ↩
-
Original PDF page 33: w2.3 Developing the Treatmentplan, p.33 ↩
-
Original PDF page 32: w2.3 Developing the Treatmentplan, p.32 ↩
-
Original PDF page 34: w2.3 Developing the Treatmentplan, p.34 ↩
-
Original PDF page 35: w2.3 Developing the Treatmentplan, p.35 ↩
-
Original PDF page 36: w2.3 Developing the Treatmentplan, p.36 ↩
-
Original PDF page 37: w2.3 Developing the Treatmentplan, p.37 ↩
-
Original PDF page 43: w2.3 Developing the Treatmentplan, p.43 ↩
-
Original PDF page 38: w2.3 Developing the Treatmentplan, p.38 ↩
-
Original PDF page 39: w2.3 Developing the Treatmentplan, p.39 ↩
-
Original PDF page 40: w2.3 Developing the Treatmentplan, p.40 ↩
-
Original PDF page 41: w2.3 Developing the Treatmentplan, p.41 ↩
-
Original PDF page 42: w2.3 Developing the Treatmentplan, p.42 ↩
-
Original PDF page 44: w2.3 Developing the Treatmentplan, p.44 ↩