The Special Needs Patient in Orthodontics12
Dr Daniel Fernandes — Orthodontics
University of Western Australia, School of Dentistry
The University of Western Australia — Faculty of Medicine and Dentistry
- Rationale for treating disabled patients
- Who is prepared to treat them?
- Preparing the child for treatment
- Drawing up a general treatment direction
- Choosing the suitable management modality
- Adapting traditional orthodontics to the Special Needs Patient
- The ethical dilemma revisited
Becker, A. and Chaushu, S. (2004). Australian Society of Orthodontics Meeting.
Rationale For Treating Disabled Patients3
- Dental disability
- Medically necessary care
- Persons with special care needs
Dental caries, periodontal disease, and other oral conditions if left untreated can limit substantially a child’s development and an individual’s participation in life activities.
Lecturer — Orthodontic Challenges
Orthodontic treatment can create additional difficulties for patients with special needs and can affect quality of life.
- Patients may be unable to clean their teeth independently or adequately, and brackets and arch wires can make oral hygiene more difficult.
- Some patients cannot follow commands or maintain stable muscle activity during procedures, making bracket bonding impossible when cooperation cannot be controlled.
- The treatment challenge involves both managing the patient’s condition and managing parental expectations.
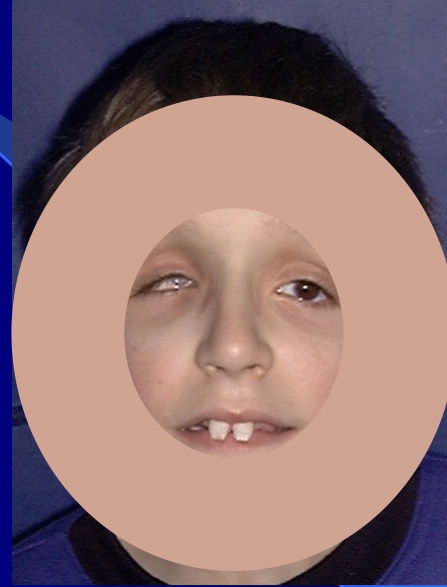
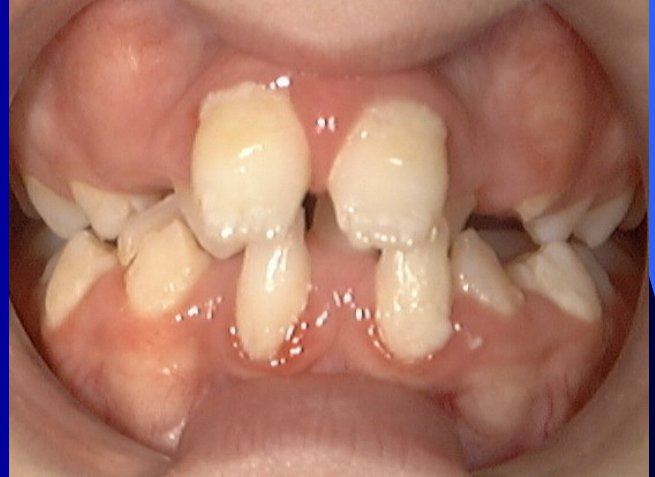
Definition Of Dental Disability45
A person should be considered to have a dental disability if they have pain, infection, or a lack of a functional dentition:
- Restricts nutritional intake adequate for growth and energy needs.
- Delays or otherwise alters growth and development; or
- Inhibits participation in life activities
 |  |
Definition Of Medically Necessary Care6789
Medically necessary care is the reasonable and appropriate diagnostic, preventive and treatment services and follow-up care (including supplies, appliances and devices) as determined by qualified, appropriate health care providers in treating any condition, disease, injury or congenital or developmental malformation.
Medically necessary care includes all health care services that directly support the delivery of dental/oral health care that in the judgment of the attending dentist, are necessary for the provision of optimal quality therapeutic and preventive oral care to the patients with medical, physical or behavioral conditions.
(cont.)
These services include, but are not limited to, sedation, general anesthesia and utilization of surgical facilities.
Dental care is medically necessary for the purpose of preventing, controlling and eliminating orofacial infection, pain and disease and correcting facial disfiguration or dysfunction.
Lecturer — Limited Orthodontic Treatment
Special needs patients may be eligible for treatment because of their condition and because they have a health card, but treatment objectives must remain realistic and simplified. The orthodontist should aim for the most stable condition possible rather than assuming that the result achievable in a patient without special needs can be reproduced.
- Orthodontic participation may be limited to serial extraction, managing eruption during mixed dentition, or removing obstructions to eruption.
- Other limited objectives include providing space for permanent teeth, limited maxillary expansion, and a limited amount of alignment and leveling.
Definition Of Persons With Special Health Care Needs101112
Persons are considered to have special care needs if they have a physical, developmental, mental, sensory, behavioral, cognitive, or emotional impairment or limiting condition that requires medical management, health care intervention, and/or use of specialized services or programs.
The condition may be developmental or acquired and may cause limitations in performing daily self-maintenance activities or substantial limitations in a major life activity.
Health care for special needs patients is beyond that considered routine and requires specialized knowledge, increased awareness and attention and accommodation.
Lecturer — Treatment Limitations
Special needs patients may have limitations involving oral hygiene, muscular balance, tongue posture, drooling, the gag reflex, uncontrollable movements, the ability to remain still, behaviour, and cooperation. These limitations influence whether orthodontic treatment can be safely delivered and whether the result can be maintained.
Who Is Prepared To Treat Them13
- Australian Dental Association
- Ask for a dentist skilled/experienced in treating disabled patients
- Pediatric Dentist or General Dentist or Special Needs Dentist (Specialist) — Daniel Sundaresan in WA
- Usually within a Public Institution/Facility
- Advice Disability Services
Lecturer — Treatment Team
Treatment generally requires close cooperation between the orthodontist and a paediatric dentist experienced in treating special needs patients. The paediatric dentist may be needed for impressions, caries treatment, restorations, extractions, behaviour management, and preparation for orthodontic procedures.
- Treatment should be multidisciplinary, with the orthodontist and paediatric dentist planning and working together.
- Parents or carers are essential members of the treatment team and may need to assist with oral hygiene, appliance cleaning, behaviour management, attendance, cooperation, and support throughout treatment.
- The team must determine whether the patient can cooperate, whether the parents understand the limitations, whether sedation or general anaesthesia is required, and whether the proposed treatment is justified by its likely benefit.
Literature Review
Jackson, E. F. (1967). Orthodontics and the retarded child, American Journal of Orthodontics, 53, 596-605.
Jackson 1967 Orthodontics And The Retarded Child1415
As early as 1967, Jackson suggested methods for orthodontic treatment for patients with learning disabilities.
Jackson, E. F. (1967). Orthodontics and the retarded child, American Journal of Orthodontics, 53, 596-605.
Lecturer — Treatment Limits
The central dilemma is how far orthodontic treatment should proceed when disability-related limitations are substantial.
- The key question is not only whether the occlusion requires treatment, but whether treatment can be performed and maintained.
Ackerman And Wiltshire 1994 The Occlusal Status Of Disabled Children161718
Ackerman, A. and Wiltshire W. A. (1994). The occlusal status of disabled children, Journal of the Dental Association of South Africa, 49, 447-51.
The occlusal status of children of six schools for the handicapped was determined using the occlusal index (O.I.) of Summers.
The study showed 75% required treatment. 10.5% had good occlusions and 15% had slight malocclusions where treatment was not considered essential.
The study indicated that 40.6% of children were interested in receiving orthodontic treatment, but only 0.5% were planning to seek it.
Lecturer — Retention and Relapse
Treatment need does not mean that treatment can be performed in every patient, and retention is particularly difficult when serious limitations affect muscles and occlusal balance.
- Approximately 50% relapse was described as a usual expectation.
- Despite relapse, parents were often happy with the results when expectations had been explained realistically.
Becker And Shapira 1996 Orthodontics For The Handicapped Child1920
Becker, A., and Shapira, J. (1996). Orthodontics for the handicapped child, European Journal of Orthodontics, 18, 55-67.
In 1996 Becker and Shapira presented guidelines for the orthodontic treatment of the handicapped child. They discussed therapeutic modalities new and old that could be utilized in the treatment of the malocclusion of handicapped children.
Basic Patient Requirements2122
Four basic requirements an orthodontic patient must demonstrate:
- Motivation
- Oral hygiene
- Behaviour management
- Manual dexterity
In the context of these patients the parents or carers can supplement the requirements.
- Cooperation with cleaning and treatment
- Oral hygiene is a major concern after brackets and wires are placed
- At least 50% relapse should be considered when planning treatment Becker, A., and Shapira, J. (1996). Orthodontics for the handicapped child, European Journal of Orthodontics, 18, 55-67.
General treatment principles still apply:
- Clinical examination
- Diagnostic records
- Prioritized problem list
- Treatment objectives
- Treatment plan
Lecturer — Simplified Objectives
Treatment objectives should be limited to what the patient can tolerate and what can realistically be maintained.
- The usual focus is a realistic and stable improvement rather than ideal intercuspation.
- Headgear and other extraoral devices may be impossible when cooperation difficulties prevent their use.
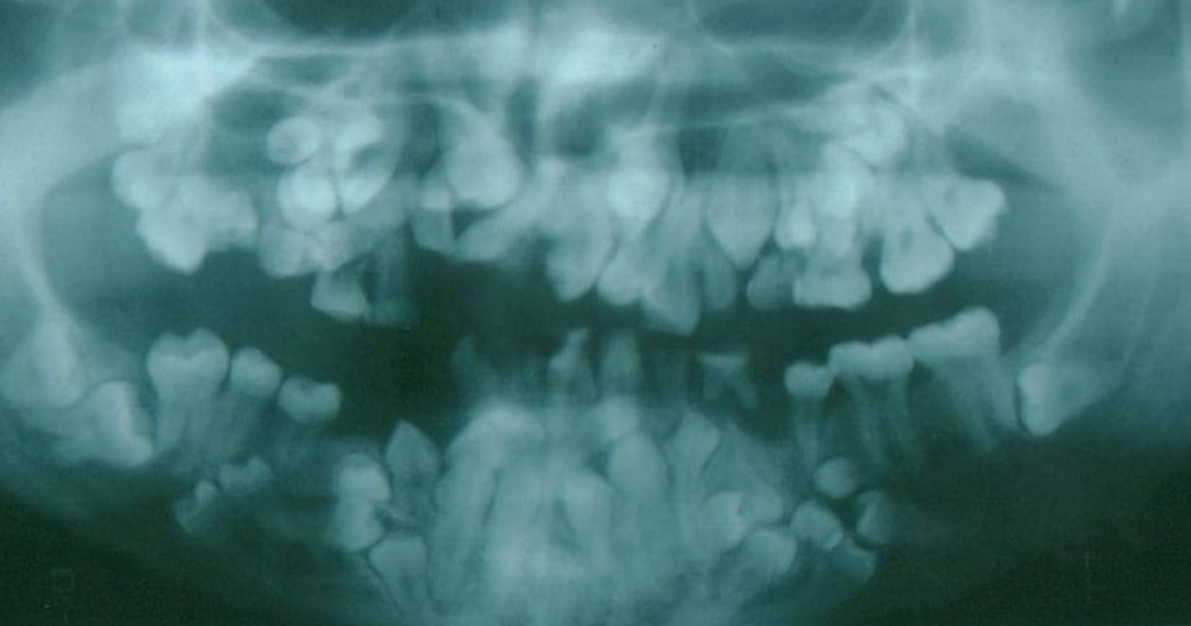
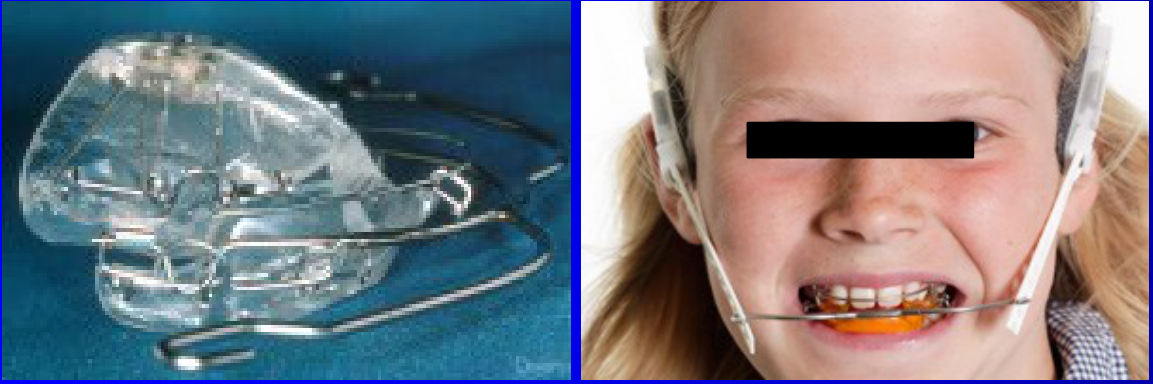
- A monoblock functional appliance may be considered when growth control is required, to control the relationship between the jaws as a unit.
The Role Of The Parent Or Carer23
The role of the parent or carer includes:
- Oral hygiene
- Caries prevention prophylaxis (diet control, fluoride application, etc.)
- Appliance care
Becker, A., and Shapira, J. (1996). Orthodontics for the handicapped child, European Journal of Orthodontics, 18, 55-67.
The Role Of The Orthodontist2425262728
- There is the need to aim for realistic treatment goals, which must be adapted to the individual patient’s needs and capabilities (Willard and Nowak, 1981).
Becker, A., and Shapira, J. (1996). Orthodontics for the handicapped child, European Journal of Orthodontics, 18, 55-67.
-
It is advisable to use a simplified appliance design to make activation independent of the patient (Becker 1993).
-
Conscious sedation is a pharmacologically induced state of relaxation in which the patient remains conscious, but with significant alteration of mood and co-operativeness throughout the dental treatment. This has played an increasingly important part in the orthodontic treatment of handicapped children.
-
Strategic extractions that will allow spontaneous corrective movements of adjacent teeth. This will often minimize the need for and extent of mechanotherapy.
-
The use of en bloc (all of the teeth moved as a unit) extra-oral removable appliances for growth modification (full-time). Where the parents cooperate with this appliance, the results may be truly dramatic.
Lecturer — Practical Treatment Goals
The orthodontist should avoid making treatment more difficult than necessary and must consider whether braces are appropriate at all.
- Common limited aims include removing obstructions to eruption, providing space for permanent teeth, closing spaces where possible, correcting a posterior crossbite when feasible, and achieving limited alignment and leveling.
- Strategic extraction may assist eruption during mixed dentition; when the permanent tooth has approximately two-thirds root development or more, the corresponding deciduous tooth may be removed and eruption observed.
- Ideal intercuspation may be inappropriate when muscle activity and function are unbalanced.

Chadwick And Asher-McDade 1997 Management Of Profound Learning Disability2930
S. M. Chadwick and C. Asher-McDade (1997). The orthodontic management of patients with profound learning disability, British Journal of Orthodontics, 24, 117-125.
- Patient selection
- Treatment planning
- Clinical management
Coordination With General Anesthesia31
Due to the need to provide routine dental care for many of these patients under general anesthetic (GA), close coordination of these procedures with orthodontic treatment is recommended. This increases the GA time, but otherwise would not place the patient under any additional risk.
S. M. Chadwick and C. Asher-McDade (1997). The orthodontic management of patients with profound learning disability, British Journal of Orthodontics, 24, 117-125.
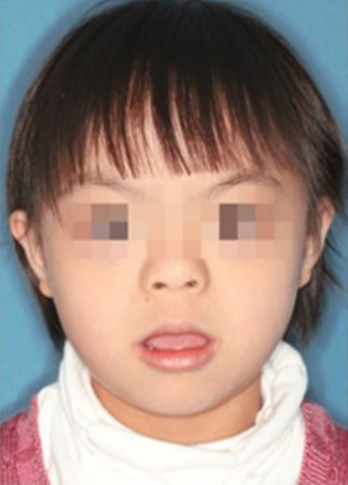 | 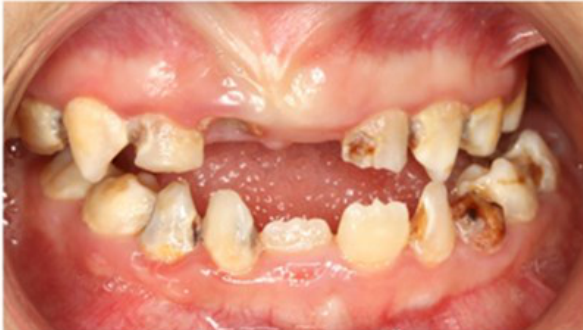 |
Ethical Questions In Elective Treatment32333435
Elective procedures on patients with a learning disability raise moral and ethical questions.
S. M. Chadwick and C. Asher-McDade (1997). The orthodontic management of patients with profound learning disability, British Journal of Orthodontics, 24, 117-125.
There may be considerable pressure from parents/carers for some form of treatment to improve the patient’s “quality of life.” The risks of orthodontic treatment must be carefully explained to allow the parents/carers to provide informed consent.
Lecturer — Elective Treatment Burden
Orthodontic treatment may be elective even when the patient’s general dental care is necessary.
- The expected improvement must be weighed against the burden of treatment, sedation, or general anaesthesia.
- Treatment should not be undertaken simply because parents want the best possible result if the patient cannot tolerate or maintain it.
- In some situations, limited dental care and eruption management are more appropriate than comprehensive orthodontics.
Elective procedures for patients with learning disability are not limited to dental treatment. Similar ethical and moral questions have been raised concerning elective surgery for patients with Downs Syndrome in order to improve their speech and appearance.
Following orthodontic treatment for patients with learning disabilities, an improvement in the parent-child relationship has been reported, but an improvement in “quality of life” or social acceptability is difficult to quantify, particularly if the patients themselves are not able to express their feelings.
Chaushu And Becker 2000 Behaviour Management Needs36373839
Chaushu, S. and Becker A. (2000). Behaviour management needs for the children with disabilities, European Journal of Orthodontics, 22, 143-149.
This investigation studied the modes of behaviour management used in the orthodontic treatment of disabled children, and the preferred criteria.
Five specific factors, frequently seen in disabled children — gag reflex, drooling, uncontrollable movements, inability to remain still, and the need for additional procedures — were graded and a scoring system was devised to include these factors within the assessment.
The scoring system may be used to evaluate new patients and to assist in a choice of the selection of an appropriate behavioral management mode.
Lecturer — Behaviour Over Time
Behaviour may improve with patience and repeated exposure.
- A patient who initially requires sedation may later tolerate regular appointments without sedation.
Becker Shapira And Chaushu 2000 Motivation Expectation And Satisfaction40414243444546
Becker A., Shapira J. and Chaushu, S. (2000). Orthodontic treatment for disabled children: motivation, expectation, and satisfaction. European Journal of Orthodontics, 22, 225-8.
This study was designed to measure motivation for and expectation of proposed orthodontic treatment for disabled children, and to examine the level of satisfaction with the results of this treatment, in the eyes of the parents. A two-part questionnaire was sent to the parents of treated disabled children.
Becker A., Shapira J. and Chaushu, S. (2000). Orthodontic treatment for disabled children: motivation, expectation, and satisfaction. European Journal of Orthodontics, 22, 151-158.
The parents expected improvement in the child’s appearance with a concomitant improvement in his/her social acceptance.
These expectations from the treatment were found to be exaggerated,
with only a minority of the parents claiming a marked improvement in their child’s everyday functioning, or a significant social improvement.
Nevertheless most of the parents were satisfied with treatment,
and reported that 17 of the children themselves, who were aware of a change, considered it an improvement. A majority of the children understood the reasons for treatment, in the most general of terms.
With only one exception, the parents stated that they would repeat the procedure, given the same set of circumstances, and all of them would recommend it for other disabled children.
It may be concluded that even though orthodontic treatment in this group of patients does not yield the desired social influence, the individual benefits from the treatment are worthwhile.
Lecturer — Realistic Expectations
Satisfaction depends substantially on realistic expectations and an understanding of the difficulty of treatment.
- Parents may remain satisfied despite relapse and may be willing to repeat complicated procedures despite frustration, time requirements, and the possibility that treatment cannot be completed as planned.
Chaushu Zeltser And Becker 2000 Safe Banding Under General Anesthesia47484950
Chaushu, S., Zeltser R. and Becker A. (2000). Safe orthodontic banding for children with disabilities during general anesthesia, European Journal of Orthodontics, 22, 225-8.
General anesthesia (GA) may be employed to overcome management difficulties in the orthodontic treatment of disabled children.
This report introduces the application of rubber dam as a useful aid for a high quality bonding and as an effective safeguard in bonding of brackets.
This report introduces the application of rubber dam as a useful aid for a high quality bonding and as an effective safeguard in bonding of brackets in (GA), in the handicapped in particular.
Additional procedures, such as extractions or exposure of impacted teeth may be carried out only after removal of the rubber dam, but before archwire placement, wherever possible.

Chaushu Gozal And Becker 2002 Intravenous Sedation515253545556
Chaushu, S., Gozal, D. and Becker A. (2002). Intravenous sedation: an adjunct to enable orthodontic treatment for children with disabilities, European Journal of Orthodontics, 24, 81-89.
Intravenous (IV) sedation has become established as an important and preferred alternative to general anesthesia (GA), in order to overcome difficulties in patient management encountered in the delivery of routine dental treatment of the disabled.
The study describes the use of IV sedation to enable the performance of certain complex orthodontic and surgical procedures, which require strict control of the oral environment for prolonged periods.
The use of IV sedation provided a satisfactory management modality in these patients, who had previously been referred for GA.
The parents reported complete satisfaction and general agreement that the same modality would again be welcomed.
IV sedation significantly reduces the use of GA and makes treatment more readily available to a larger number of disabled patients.
Lecturer — Choosing Sedation
The appropriate level of management depends on the patient’s cooperation and the procedure being performed.
- Options range from regular treatment without sedation, through sedation and intravenous sedation, to general anaesthesia.
- Sedation should not automatically be used to provide comprehensive orthodontics when a limited treatment plan would provide an adequate benefit.
The Ethical Dilemma Revisited57
First Do No Harm58
Lecturer — Treatment Burden
The treatment must not create a greater burden than its expected benefit.
- Brackets and wires may make oral hygiene twice as difficult for patients who already cannot clean adequately.
- Appliances create additional risks when the patient cannot maintain hygiene, remain still, or cooperate with instructions.
- Muscle imbalance may make the result unstable.
- The orthodontist must avoid treatment that is likely to cause harm, cannot be maintained, or cannot be completed.
Medically Necessary Treatment
Medically necessary care is the reasonable and appropriate diagnostic, preventive and treatment services (including supplies, appliances and devices) and follow-up care as determined by qualified, appropriate health care providers in treating any condition, disease, injury or congenital or developmental malformation.
Lecturer — Treatment Priorities
Dental treatment may be more urgent than comprehensive orthodontic correction, so existing dental problems must be addressed before orthodontic treatment.
- Consider caries, periodontal conditions, infection, and eruption problems first.
- General dental treatment may need to be completed before orthodontic treatment begins.
- Appropriate care may include treating caries, performing extractions, managing eruption, correcting a posterior crossbite, or providing limited space or alignment.
- The objective is treatment that is medically and dentally justified for the individual patient.
Dentally
Dental care is medically necessary for the purpose of preventing, controlling and eliminating orofacial infection, pain and disease and correcting facial disfiguration or dysfunction.
Lecturer — Practical Orthodontic Goals
Orthodontic treatment may improve quality of life, but the treatment required from the patient must be balanced against what the orthodontist can deliver.
- Practical objectives may include maxillary expansion, limited alignment and leveling, removal of retained primary teeth, and follow-up of the transition from primary to permanent dentition.
- Erupted permanent teeth should be maintained in the most stable position possible.
- Stable ideal intercuspation may not be achievable, but a compromised result with significant relapse may still be a major improvement over the initial condition.
Case Studies
Case Study Phoebe59606162
Case moved — see Case: Phoebe, clinical photographs and radiographs
DR PETER READMAN BDSc (Hons) MDS, FACD Pediatric Dentist
2 November 2004
353 Canning Highway Bicton WA 6157 Tel: (08) 9339 8200 Fax (08) 9339 8211
Unit 2, 187 Scarborough Beach Road Mount Hawthorn WA 6010 Tel (08) 9441 3922 Fax (08) 9443 6199
MOBILE: 0417 910 122
Dr Mike Razza Booragoon Orthodontics Suite 4 Gateways Building BOORAGOON 6154
Dear Mike,
RE: Phoebe [REDACTED] PO Box [REDACTED] BROOME 6725
DOB: 21 MAR 1992 Our ref: [REDACTED]
I would like to update your records in regard to Phoebe’s recent dental treatment while visiting Perth in the past few days. As you are aware, Phoebe is one of your Broome patients who was referred for extraction of her retained and partially ankylosed primary molars. During this opportunity under general anaesthesia, impressions were taken for a rapid maxillary expansion appliance (RME) which was fitted on Monday 1 November 2004.
Dental Treatment Provided Under General Anaesthesia — 20th October 200463
- EUA
- Intraoral Radiographic examination
- Scale, prophylaxis and fluoride treatment
- 7 x Dental extractions of retained primary teeth (teeth 55, 53, 63, 65, 75, 84, 85)
- 5 x Fissure sealants (teeth 16, 26, 37, 46, 47)
- Impressions for study models
- Impressions for RME
The RME was then inserted on Monday 1 November 2004 at Southbank Clinic under sedation. Post insert instructions were also given with the RME key and further discussed with Phoebe’s father ([REDACTED]).

Fees Charged for Orthodontic Treatment
Mike, the fees which I charged in regards to her orthodontic treatment so far are:
- Study Models ($90)
- Impressions/cementation/insert of RME ($280)
I would therefore be grateful if you could charge Phoebe independently in regards to the fabrication of the RME and other orthodontic costs. I have tried to keep this quite reasonable on my behalf so as not to complicate the cost of orthodontic treatment. Please find enclosed in this correspondence study models and Lab fee document.
Mike, should you require any further information please contact the Bicton Rooms in regards to Phoebe’s management.
Kind regards,
[Signature]
Dr Peter Readman
Case Study Nicholas6465666768
Case moved — see Case: Nicholas, panoramic radiographs and orthodontic management
Case Study Patrick6970717273747576
Case moved — see Case: Orthodontic treatment of a patient with Down syndrome
Case Study Nathan777879808182838485
Conclusion8687
- Rationale for treating disabled patients
- Who is prepared to treat them?
- Preparing the child for treatment
- Drawing up a general treatment direction
- Choosing the suitable management modality
- Adapting traditional orthodontics to the Special Needs Patient
- The ethical dilemma revisited
Becker, A. and Chaushu, S. (2004) Australian Society of Orthodontics Meeting.
At the end of this course you DO NOT have the didactic knowledge or clinical skills to treat comprehensive orthodontic cases.
Lecturer — Realistic Objectives
Treatment of special needs patients requires realistic objectives from the beginning, with the ethical dilemma reconsidered for every patient.
- Assess whether the patient can cooperate, whether the parents can collaborate, and whether oral hygiene can be maintained.
- Consider whether sedation or general anaesthesia is justified and whether the expected result can be retained.
- Common objectives include maxillary expansion, minimum alignment and leveling, follow-up during the transition from primary to permanent dentition, removing retained primary teeth, and providing space for permanent teeth.
- Bond braces only when the patient can tolerate them, aiming for the minimum effective treatment rather than an ideal result that places excessive demands on the patient.
- Parents must understand that relapse is likely and that the final result may be compromised.
- Even when most of the result cannot be retained, a limited result can represent a major improvement in the patient’s condition and quality of life.
Clinical Cases
Case: Phoebe, clinical photographs and radiographs
Question
Scenario: A patient with developmental learning disorders presents for orthodontic evaluation with a moderate to severe skeletal malocclusion.
What’s shown: Clinical photographs show a concave profile and a very flat midface. Intraoral photographs reveal a bilateral posterior crossbite, a posterior open bite, lack of space for the canines, and retained primary teeth in the lower arch. Radiographs show developing premolars.
Consider: How to assess the developing permanent teeth and determine the appropriate orthodontic intervention given the patient’s skeletal discrepancies and special needs.
Answer
Observations:
- Concave profile and flat midface.
- Bilateral posterior crossbite and posterior open bite.
- Lack of space for canine eruption and retained primary teeth in the lower arch.
- Radiographs indicate the premolars have approximately two-thirds of their roots formed.
Reasoning: Since the permanent premolars have at least two-thirds root formation, the retained deciduous teeth can be extracted to allow for eruption and future space closure. Due to muscle imbalance affecting the maxilla, posterior maxillary expansion is indicated. However, correcting the sagittal skeletal relationship is not feasible.
Outcome: Under general anesthesia, the patient had seven retained primary teeth extracted, received five fissure sealants, and had impressions taken for a rapid maxillary expander (RME). The RME was fitted and maintained for six months, longer than the typical three months. The parents assisted with hygiene, and over time, the patient’s behavior improved, allowing for regular appointments without sedation. Treatment in this phase was limited to the RME and monitoring the transition to the permanent dentition.
Takeaway: For special needs patients with severe skeletal discrepancies, treatment goals must be realistic and adapted to the patient’s capabilities, focusing on functional improvements like maxillary expansion and eruption management rather than ideal skeletal correction.
From the lecture slides
- Female
- Developmental learning disorder
- Moderate to severe skeletal malocclusion
Phoebe
Phoebe
R L
Phoebe — Clinical Course
Phoebe had a concave profile, a very flat midface, bilateral posterior crossbite, posterior open bite, insufficient canine space, and late retention in the lower arch.
- Radiographic assessment showed that the premolar roots were approximately two-thirds developed, supporting removal of the deciduous teeth followed by observation of permanent eruption.
- A paediatric dental specialist treated caries and restorations under sedation and took impressions for study models and the maxillary expander.
- Expansion was maintained for at least six months rather than the usual three months, with parental help maintaining hygiene around the expander.
- After expansion, Phoebe attended regular private-practice appointments without sedation, and her behaviour and cooperation improved with time and patience.
- Treatment was limited to rapid maxillary expansion and follow-up of the transition to the permanent dentition; the result reflected what was possible within her limitations rather than a comprehensive orthodontic correction.
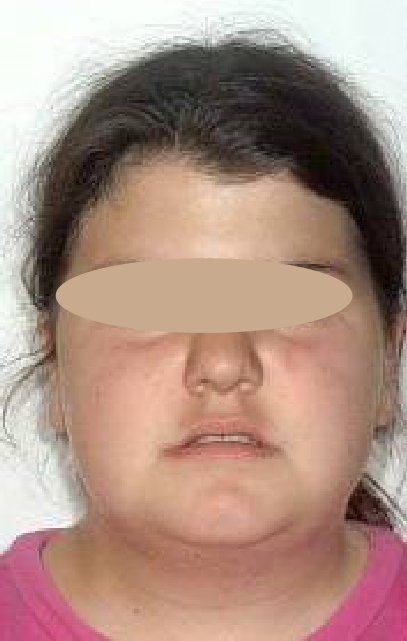 | 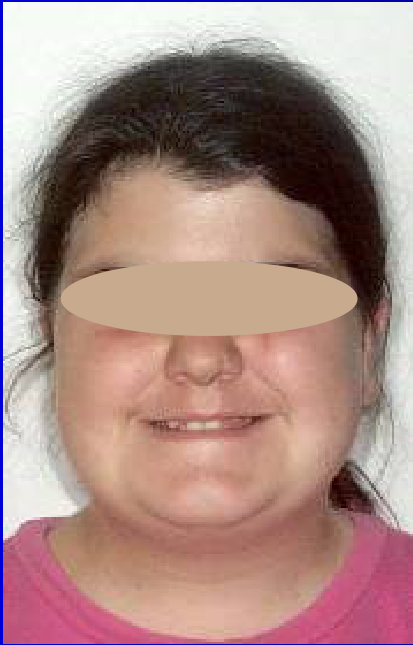 | 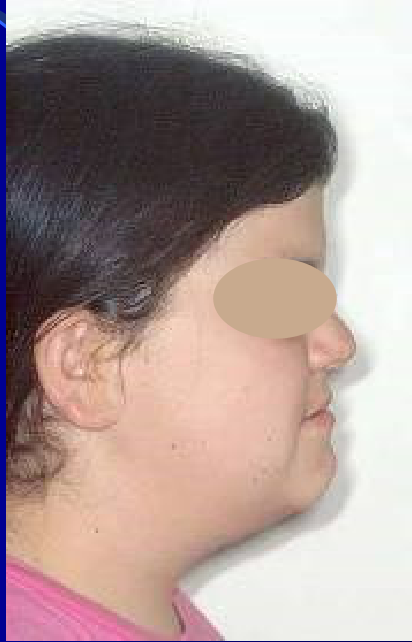 |
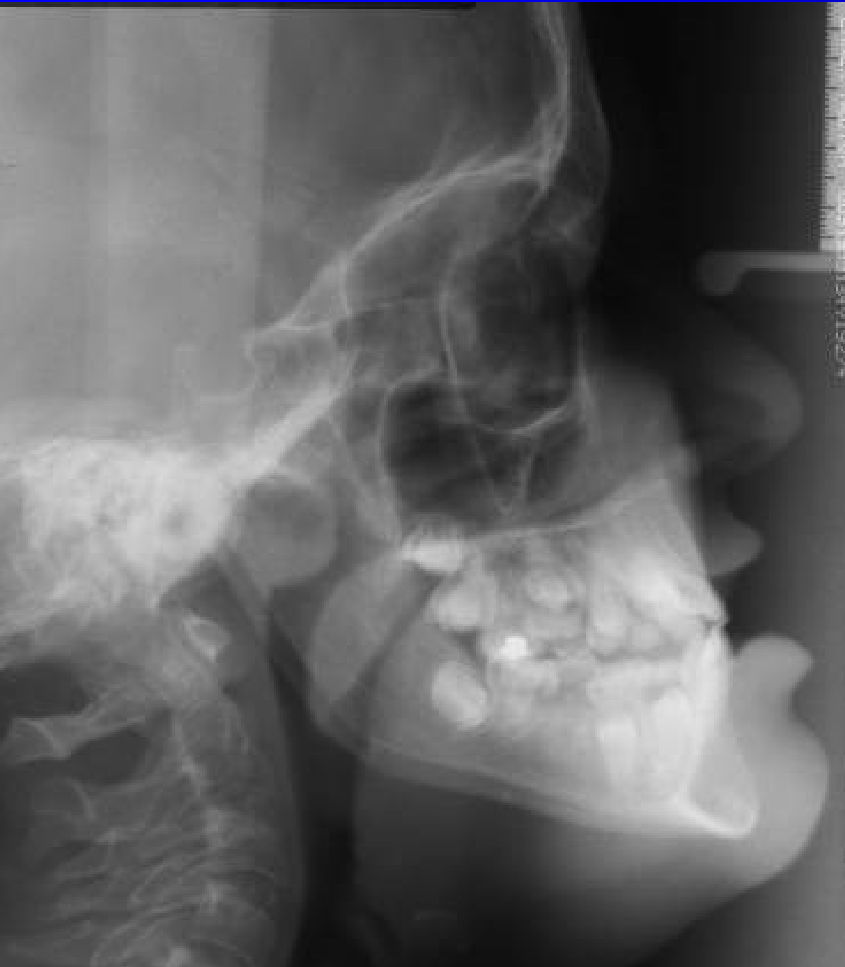 | 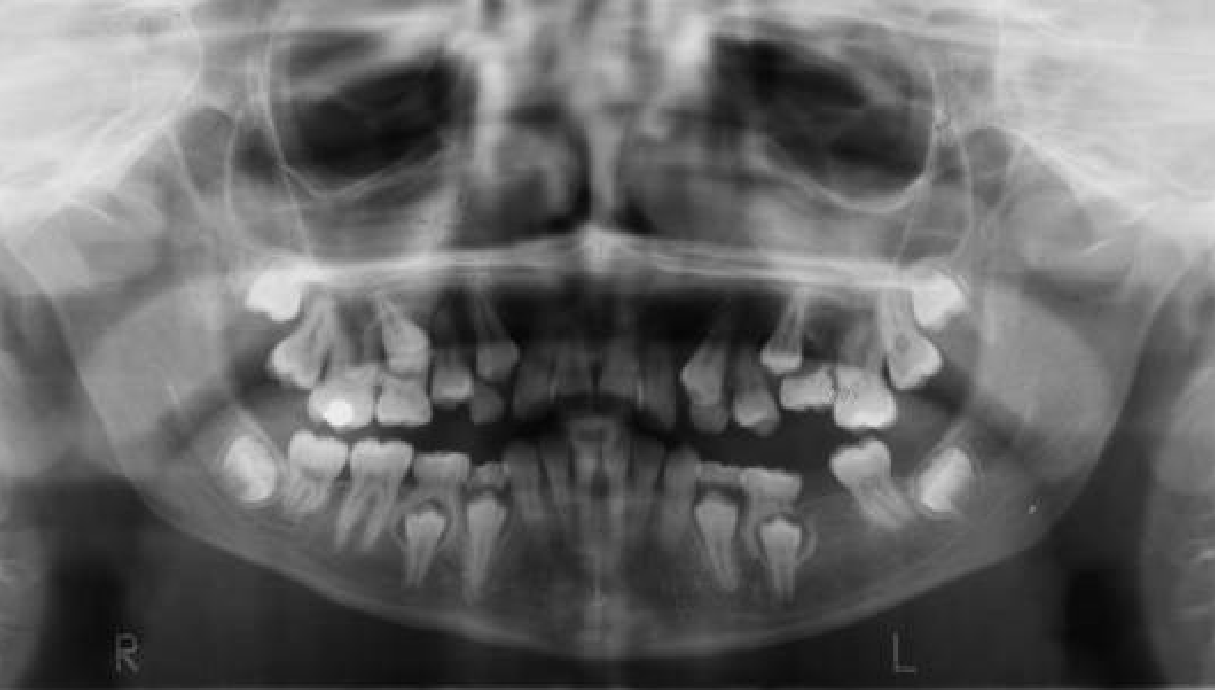 |
- GA — Diagnostic records, restorations, fit bands for rapid maxillary expansion appliance and impression for appliance fabrication.
- GA — insertion of RME
- Maintained expansion longer than average
- No sedation required to remove appliance
Case: Nicholas, clinical presentation
Question
Scenario: A patient with Down syndrome presents with moderate to severe dental malocclusion and multiple missing teeth.
What’s shown: The patient exhibits an absence of lower incisors and multiple missing teeth, which are common findings in Down syndrome.
Consider: How to manage the missing teeth and establish a functional occlusion for this patient.
Answer
Observations:
- Absence of lower incisors and multiple missing teeth.
- Moderate to severe dental malocclusion.
Reasoning: The treatment approach involves closing the spaces created by the missing teeth and reshaping the canines to function as lateral incisors. Canine guidance is achieved from the first premolars (lecturer: “from the fours”).
Outcome: Initial treatment required sedation for the extraction of deciduous teeth and necessary dental restorations, followed by a reassessment.
Takeaway: In patients with Down syndrome and congenitally missing teeth, orthodontic management can include space closure and reshaping existing teeth to establish functional guidance, often requiring sedation for initial procedures.
Case: Nicholas, panoramic radiographs and orthodontic management
Question
Scenario: Nicholas, a patient with Down syndrome, presents with multiple missing teeth and requires dental and orthodontic management.
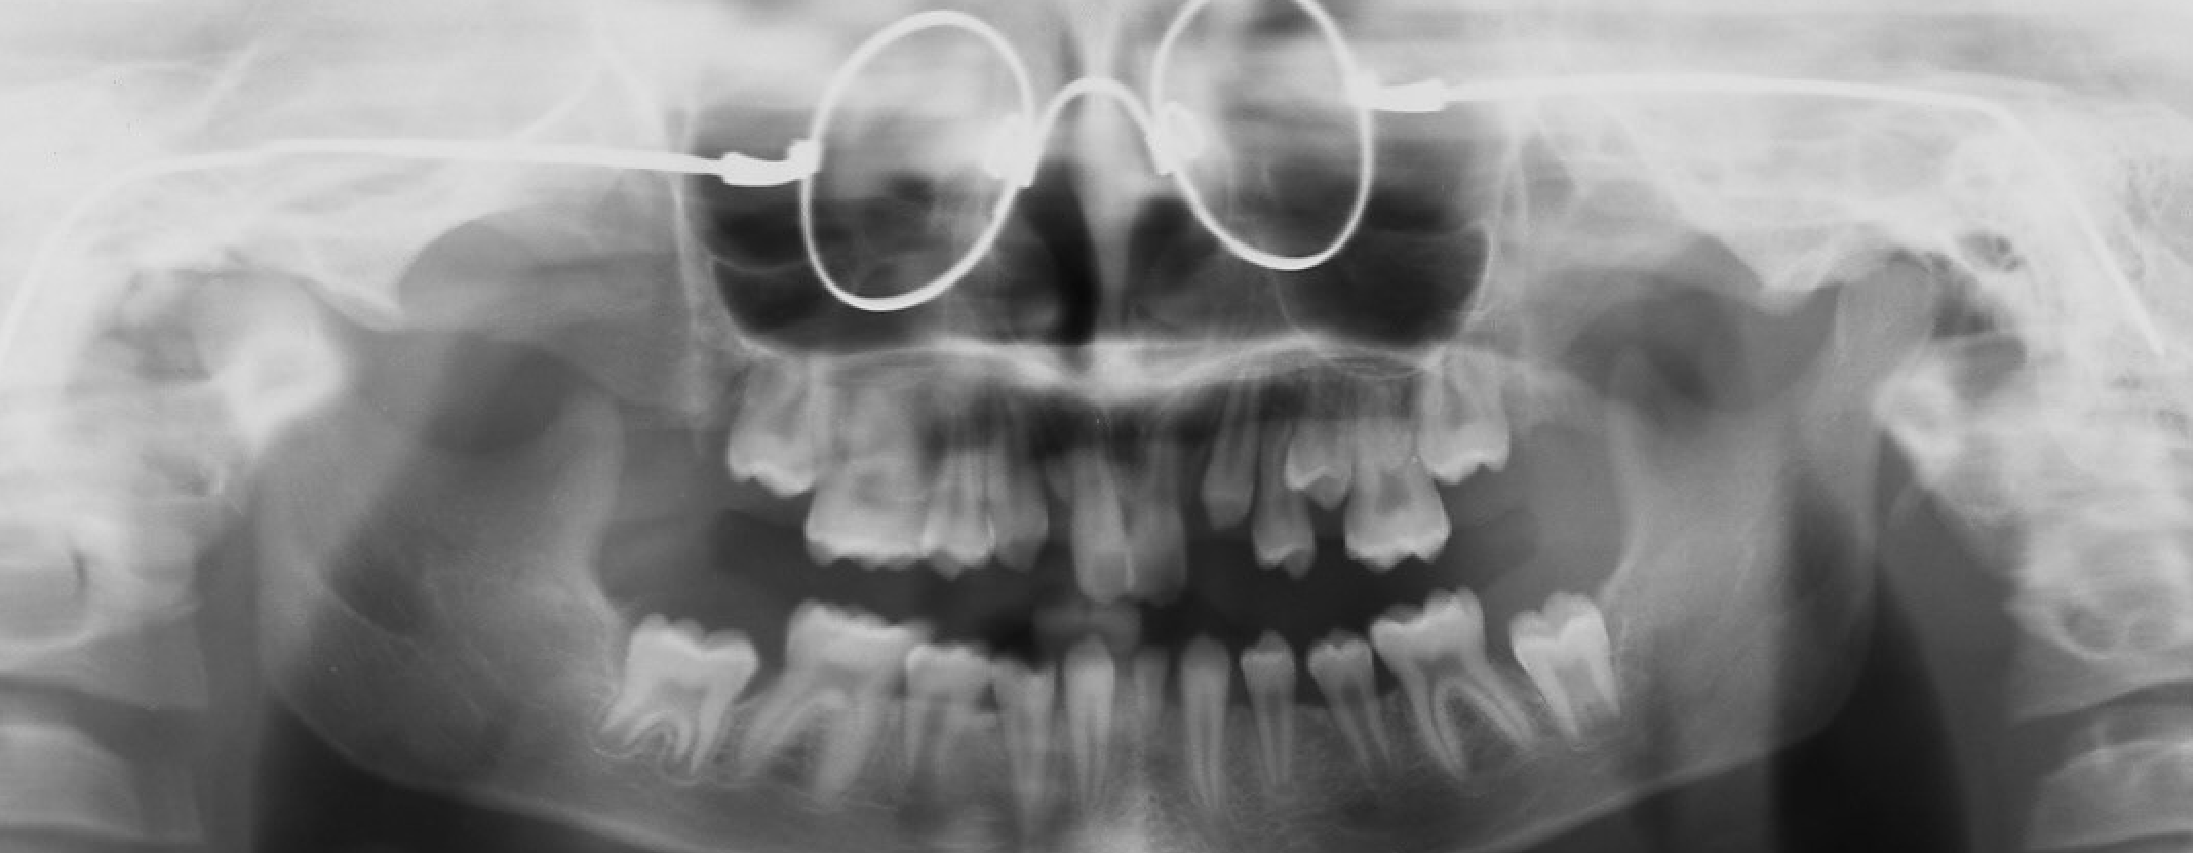
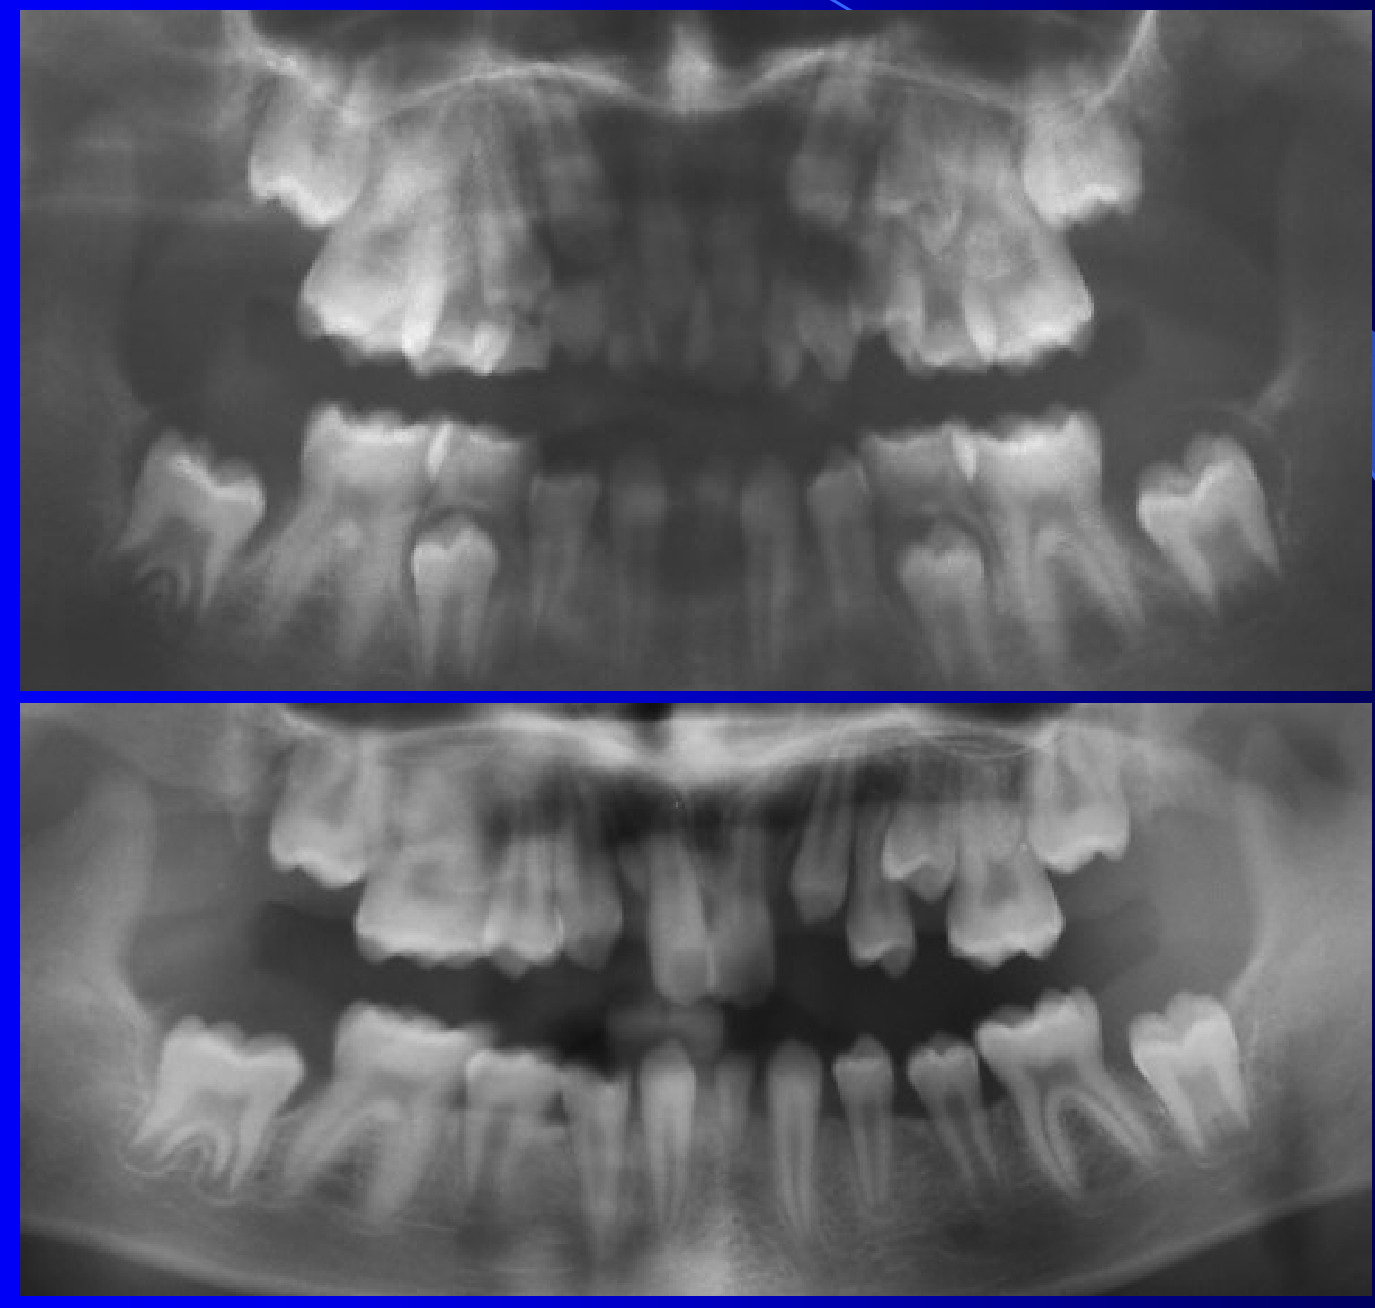
What’s shown: Panoramic radiographs displaying the dentition, highlighting missing lower incisors and upper lateral incisors, retained primary teeth, and the development of permanent canines.
Consider: How should the missing teeth and the transition from primary to permanent dentition be managed in this patient?
Answer
Observations:
- Multiple missing teeth, including lower incisors and upper lateral incisors.
- Retention of primary teeth.
- Spontaneous eruption of permanent teeth, aided by extractions of retained primary teeth when more than two-thirds of the root is developed.
Reasoning:
- Absence of lower incisors is common in Down syndrome. The plan is to close spaces and reshape the canines to act as lateral incisors, achieving canine guidance from the first premolars (lecturer: “from the fours”).
- Finishing in a Class III relationship is acceptable, provided a proper relationship between the upper and lower first molars is achieved.
- Transverse relationships must be monitored, as maxillary expansion is often needed.
- Orthodontic treatment is primarily limited to following the transition from primary to permanent dentition.
Outcome:
- Initial treatment under sedation for deciduous tooth extractions and restorations.
- Assistance with spontaneous eruption of teeth through extractions.
- Future restorative build-ups and reshaping of canines as necessary.
Takeaway:
- For patients with Down syndrome and multiple missing teeth, orthodontic treatment is largely limited to monitoring the dentition transition, closing spaces, and using restorative build-ups to reshape canines to substitute for missing incisors.
From the lecture slides
- Down Syndrome
- Moderate to severe dental malocclusion
- Multiple missing teeth
Nicholas — Eruption Management
Nicholas was missing the lower incisors and upper lateral incisors, consistent with the pattern of missing teeth associated with Down syndrome.
- The approach was to extract retained deciduous teeth, monitor permanent eruption, close spaces where appropriate, and reshape canines to function as lateral incisors when necessary.
- Restorative build-ups and reshaping formed part of the overall treatment, and sedation was initially required for extractions and dental restorations.
- The permanent teeth erupted spontaneously with limited assistance from extractions, while the orthodontic treatment primarily monitored the transition from primary to permanent dentition.
- A Class 3 relationship was acceptable if the upper and lower first-molar relationships could be achieved; transverse relationships were monitored and maxillary expansion considered where necessary.
- GA sedation
- Deciduous teeth extraction
- Required dental restorations
- Reassess
Nicholas
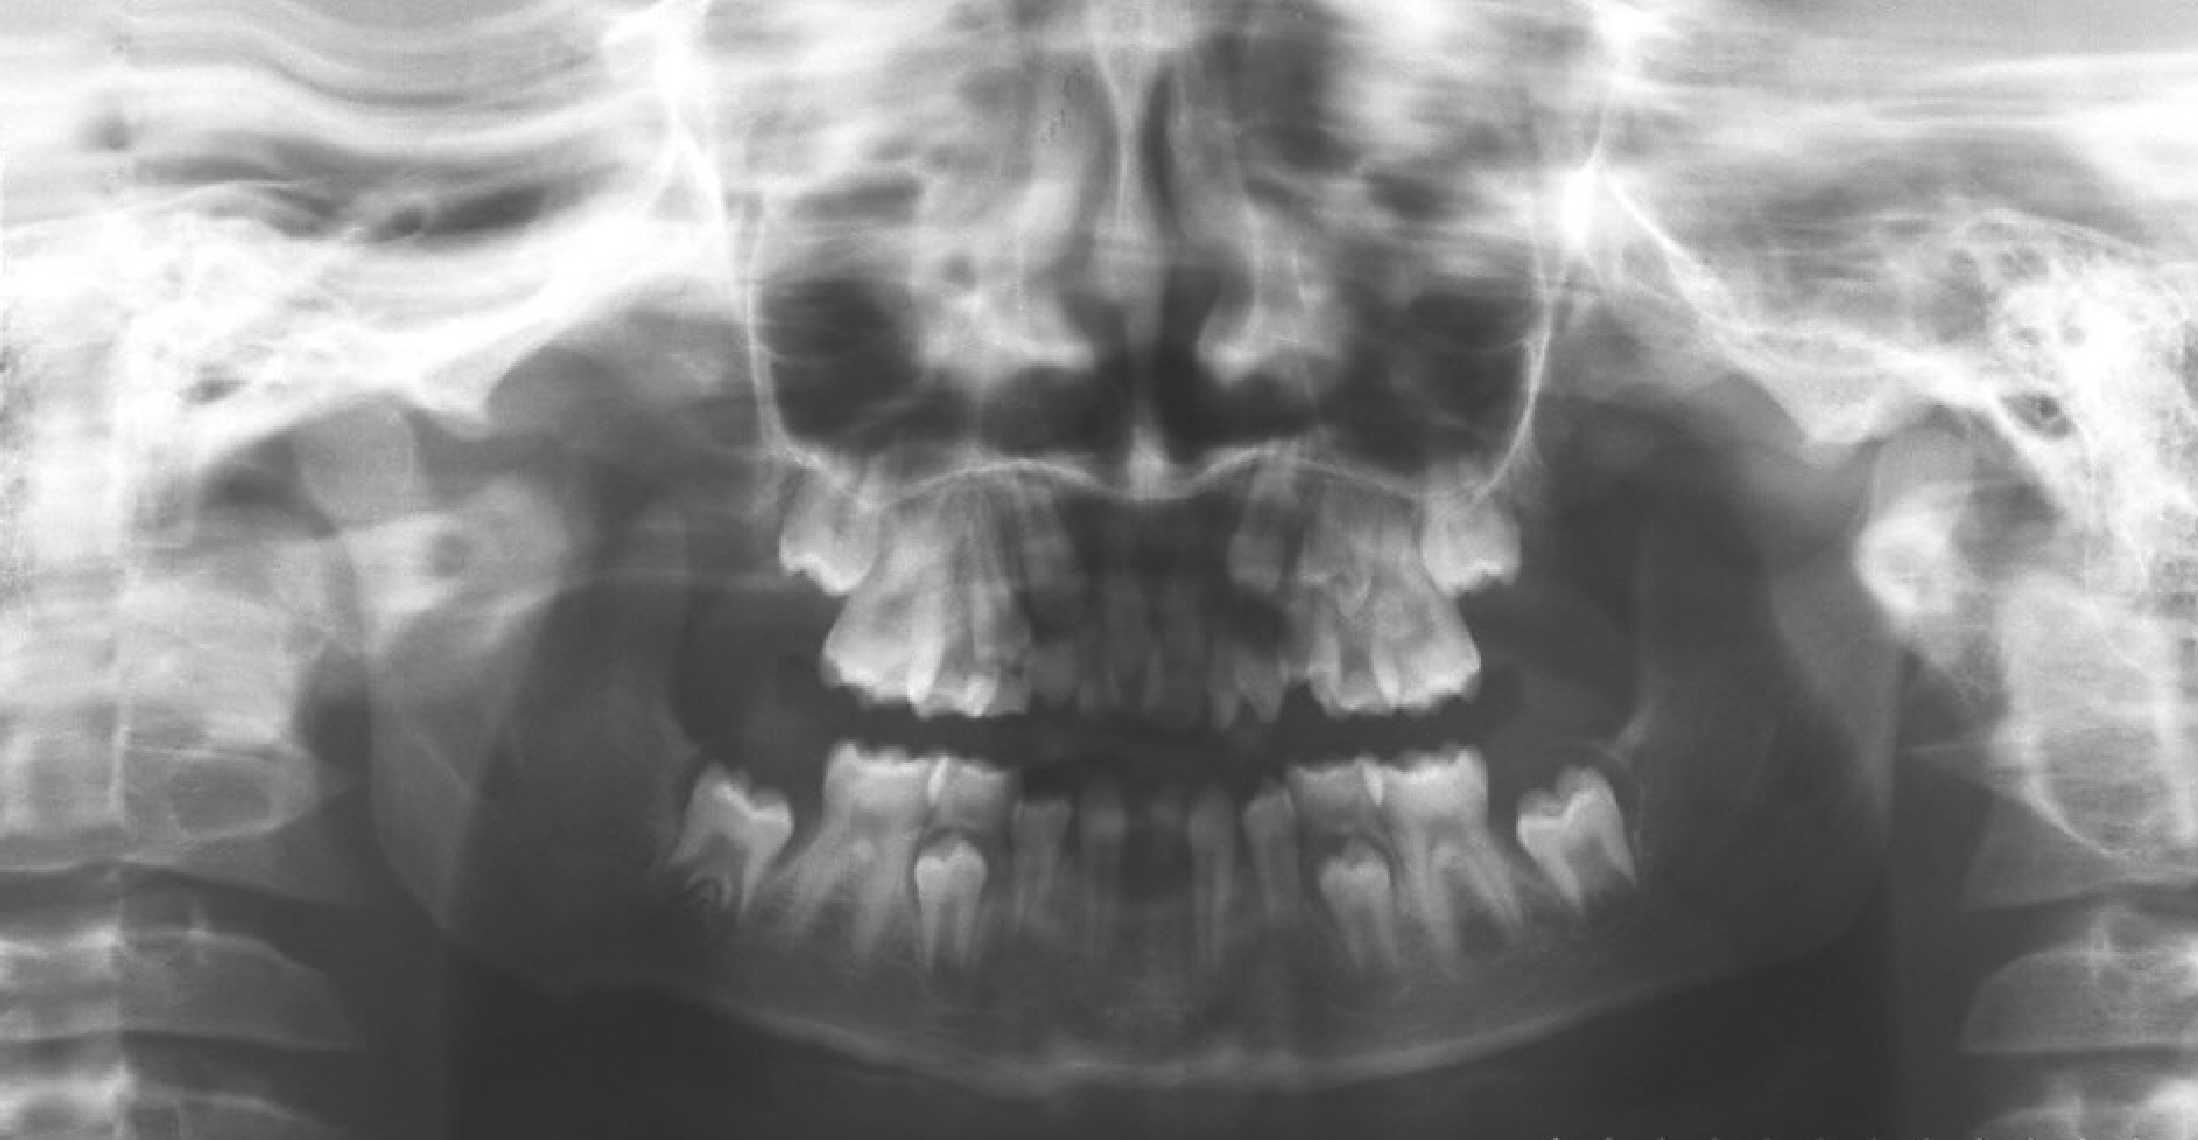
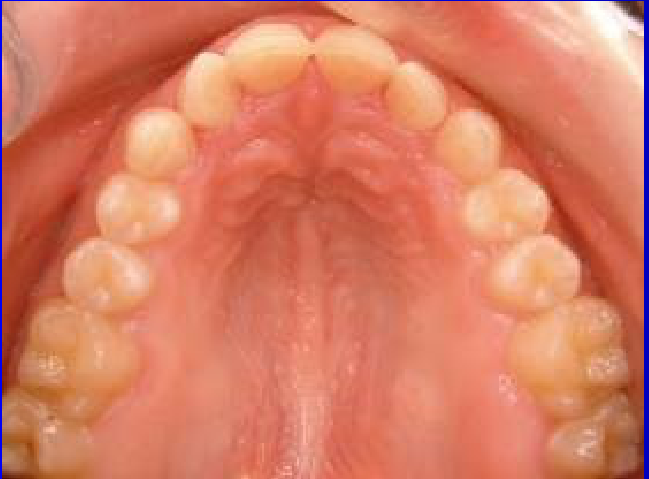
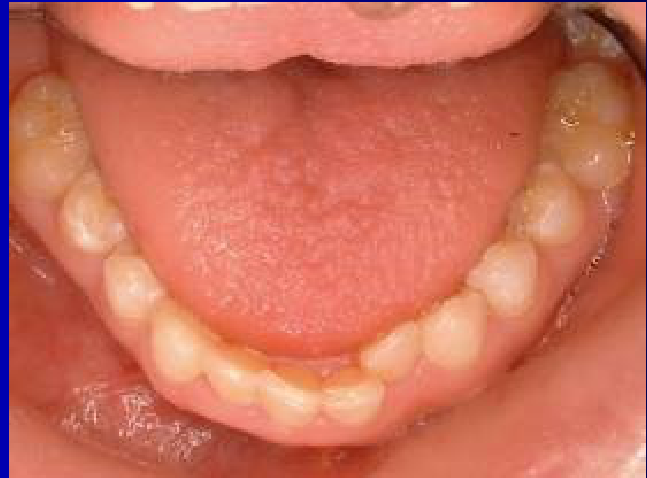
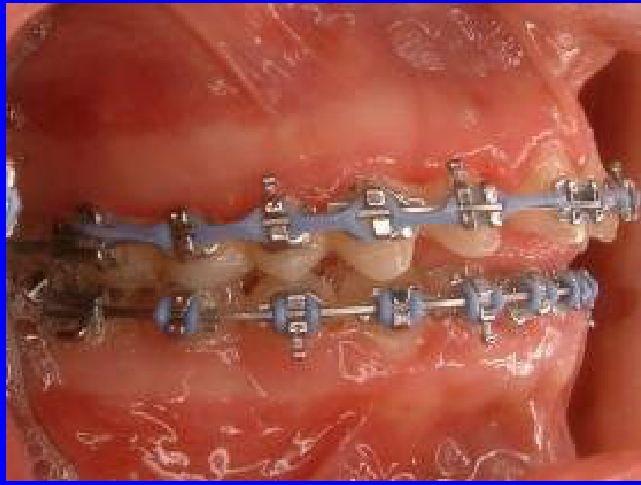
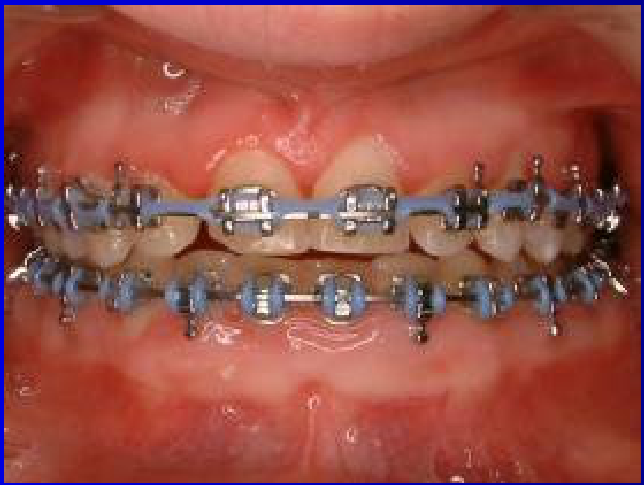
Case: Orthodontic treatment of a patient with Down syndrome
Question
Scenario: A young man with Down syndrome presents for orthodontic assessment. He has maxillary constriction, crowding, microdontia, and a skeletal Class II relationship.
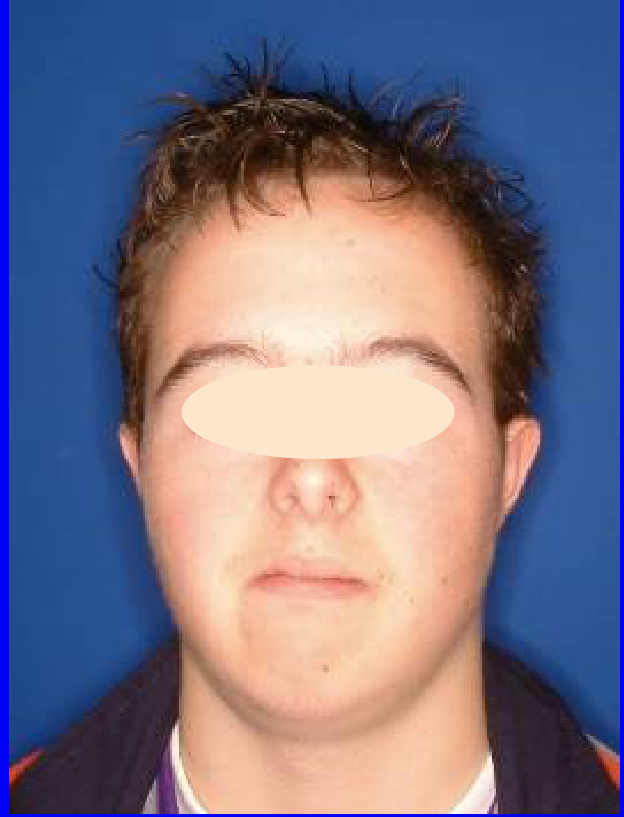
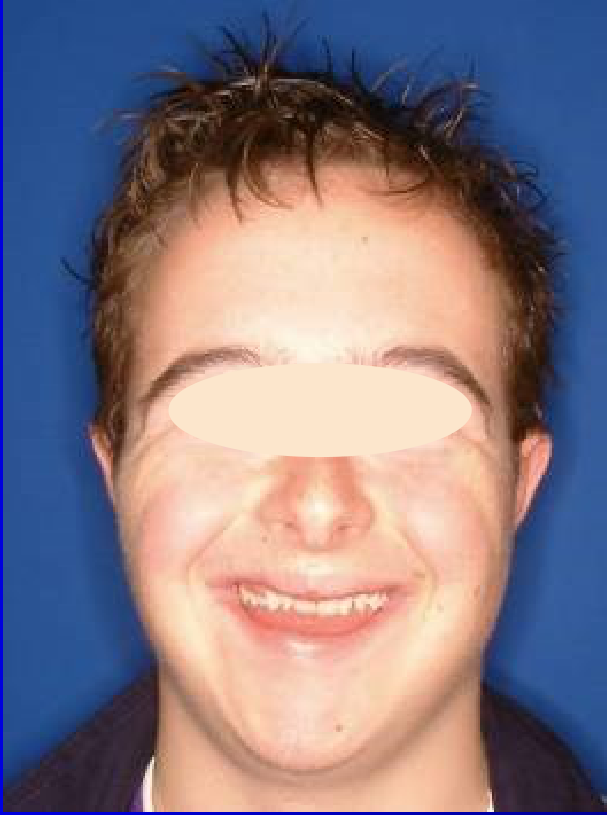
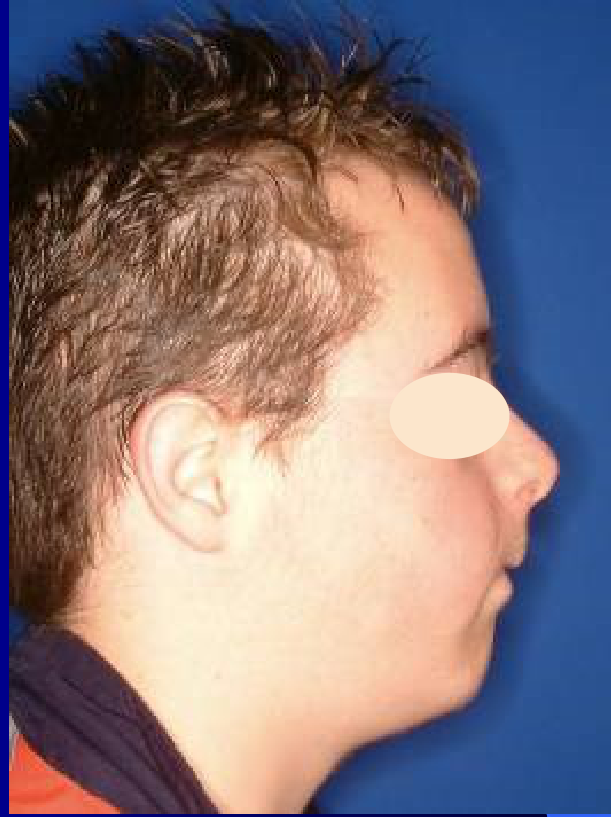
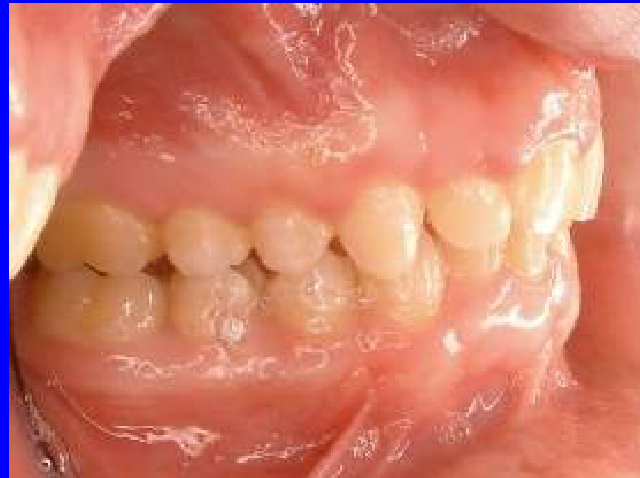
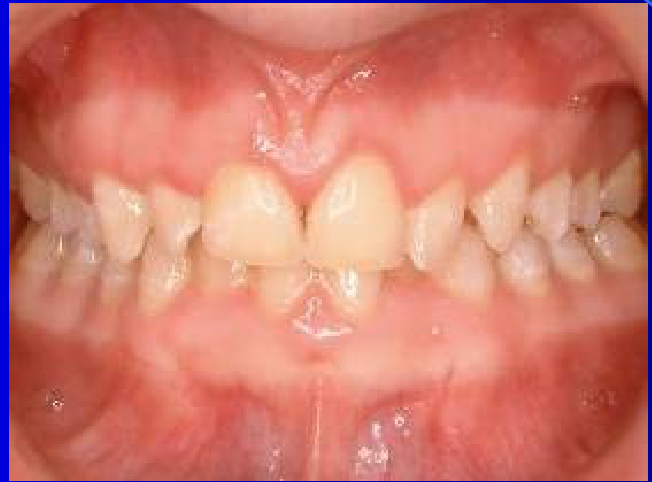
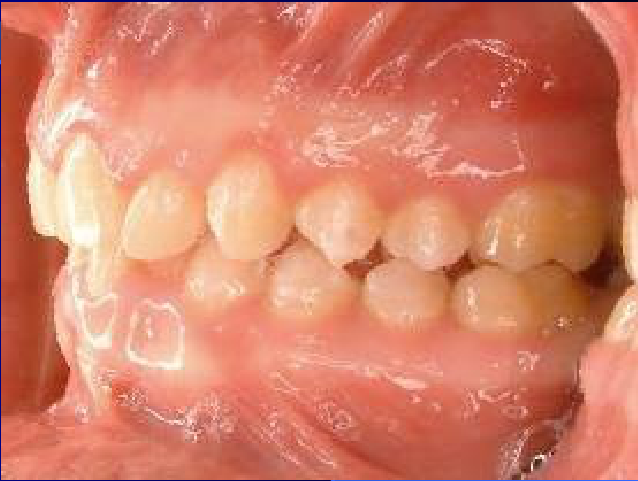
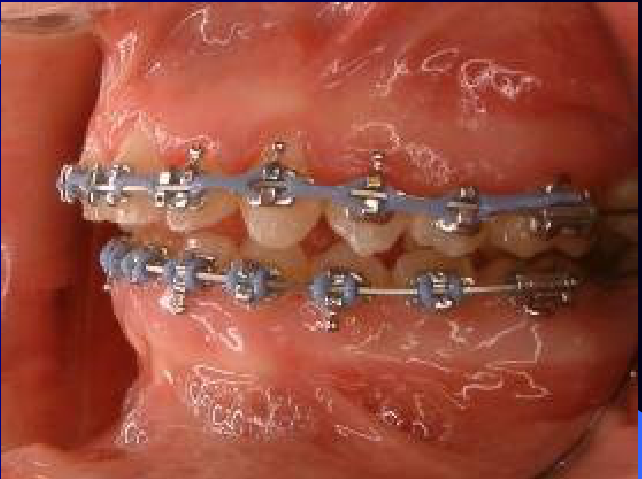
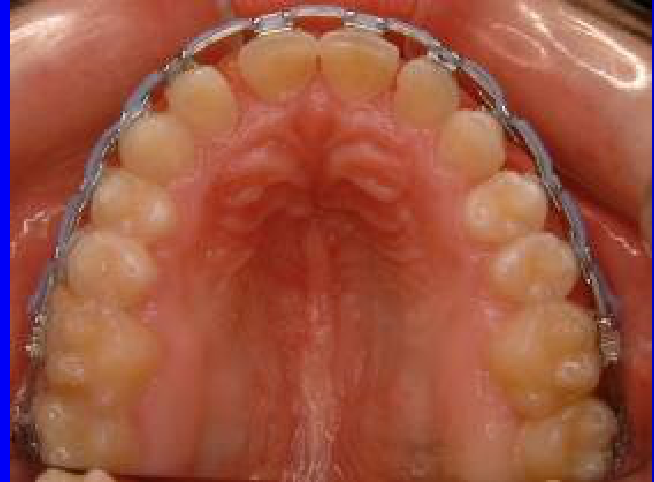
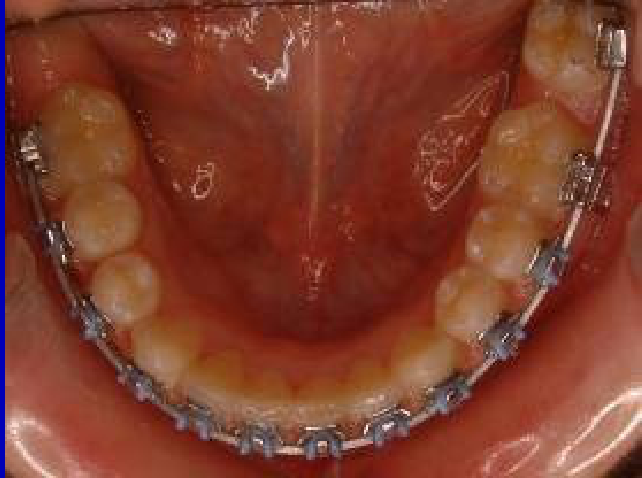
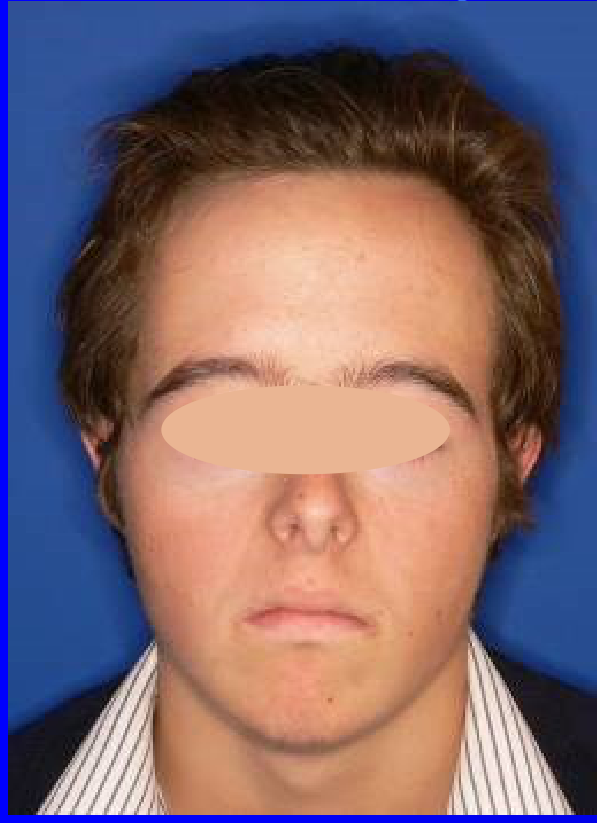
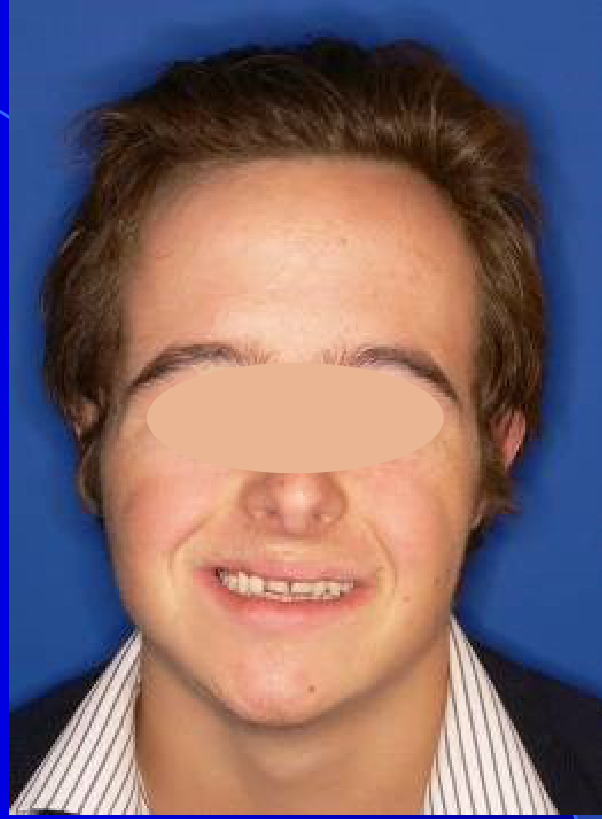
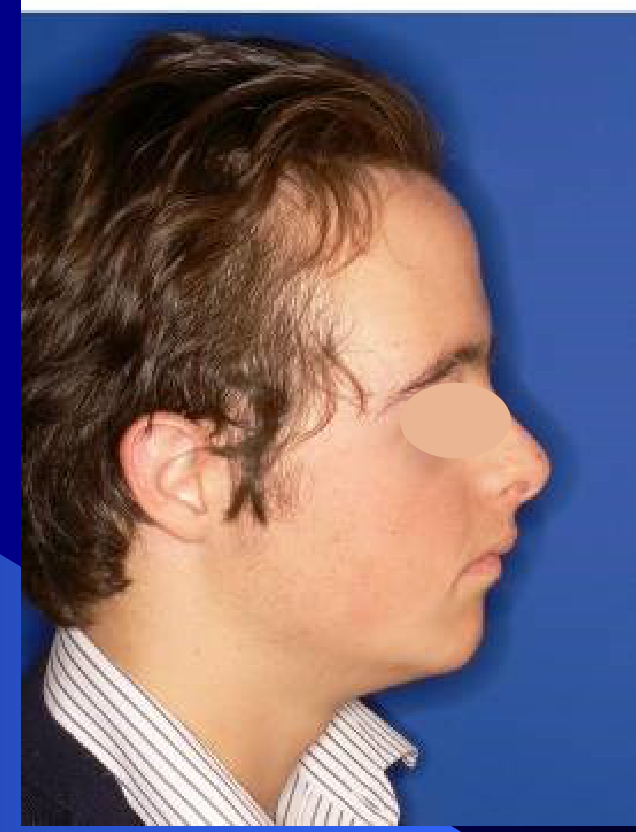
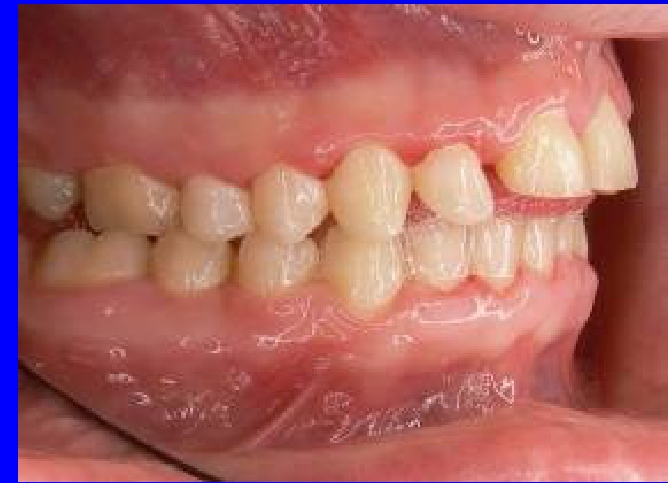
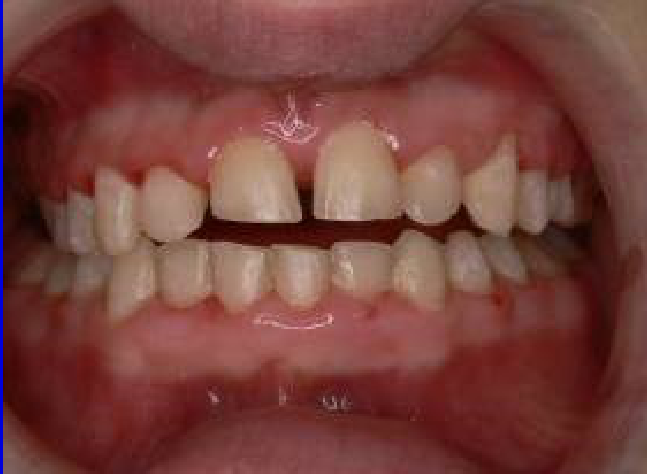
What’s shown: Clinical photographs showing a flat profile, deficient chin, and tongue interposition. Intraoral photographs show the condition following maxillary expansion, the presence of fixed orthodontic appliances, and the post-treatment profile.
Consider: Evaluate the clinical findings, the challenges posed by the patient’s soft tissue and muscular function, and the realistic goals and outcomes of orthodontic intervention in this context.
Answer
Observations:
- Maxillary constriction, crowding, microdontia, and a skeletal Class II relationship.
- Flat profile with a deficient chin and interposition of the tongue.
- Posterior crossbite present initially.
- Fixed orthodontic appliances placed; patient tolerated full fixed appliances without sedation.
- Post-treatment profile shows a more prominent chin, though a Class II profile remains.
- Significant relapse in terms of anterior open bite and spaces; patient could not tolerate the upper bar.
Reasoning: The interposition of the tongue and the imbalance between the tongue and the counter-side musculature (orbicularis oris and other functional conditions) make it impossible to retain the achievements of the treatment. The patient cannot collaborate with the use of elastics, which limits the correction of the Class II relationship and intercuspidation. The lower jaw showed some favorable vertical growth during the transition from primary to permanent dentition.
Outcome: Treatment included maxillary expansion to correct the posterior crossbite, full fixed appliances, and alignment and closure of spaces without sedation. Significant parental and family support was involved in hygiene and collaboration. Despite significant relapse in the anterior open bite and spaces, the treatment achieved a significant improvement compared to the pre-treatment condition, with a more prominent chin and corrected posterior crossbite.
Takeaway: In patients with Down syndrome and tongue interposition, orthodontic achievements are difficult to retain due to soft tissue imbalances. Treatment goals must be realistic, focusing on maxillary expansion, minimum alignment, and managing the transition, with significant parental involvement.
From the lecture slides
- Downs Syndrome
- Maxillary constriction
- Maxillary crowding
- Malalignment
- Irregular tooth form (microdontia)
- Skeletal Class II relationship
Patrick — Treatment Limits
Patrick also had retained primary teeth, tongue interposition, a flat profile, and a deficient chin.
- Maxillary expansion corrected the posterior crossbite, while crowding was managed largely by monitoring the transition from primary to permanent dentition and considering extractions where they could improve eruption and stability.
- The tongue remained a significant relapse risk, particularly for the anterior open bite, because of the imbalance between the tongue and the lip and surrounding musculature.
- Patrick tolerated a full fixed appliance, allowing some alignment and leveling, but finishing and intercuspation remained compromised; he could not tolerate an upper bar and could not cooperate consistently with elastic wear for Class 2 correction.
- No sedation was required during this phase, and substantial parental and family support assisted with hygiene and cooperation.
Patrick — post RME
- Rapid maxillary expansion
- Full-fixed appliances
- Force modules and/or elastics for Class II correction
- No sedation
- Significant parental and family support and involvement
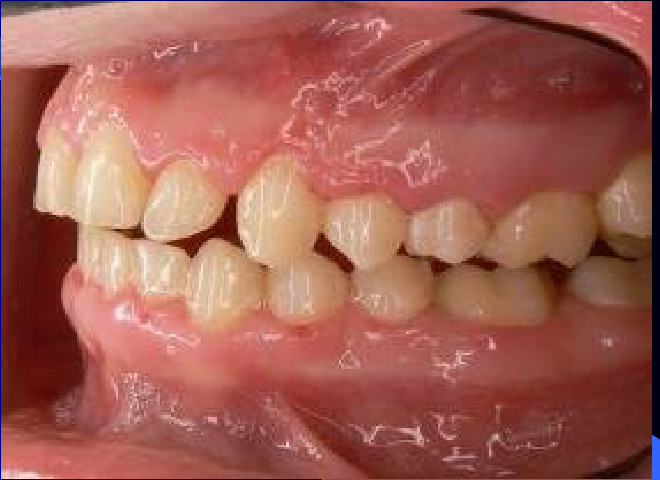
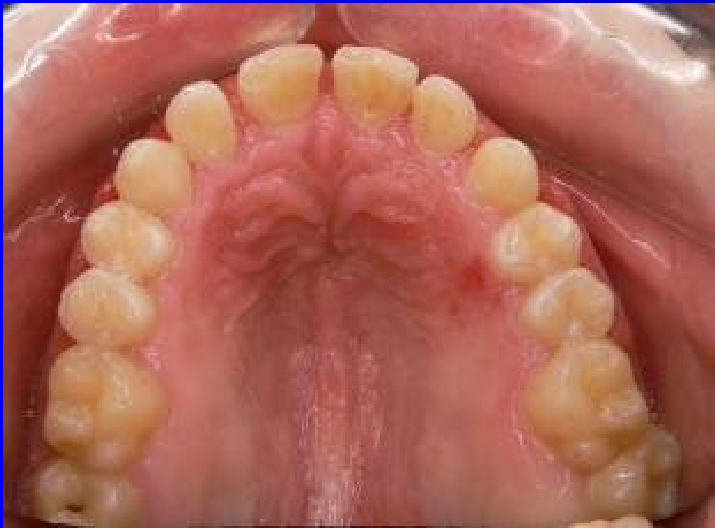
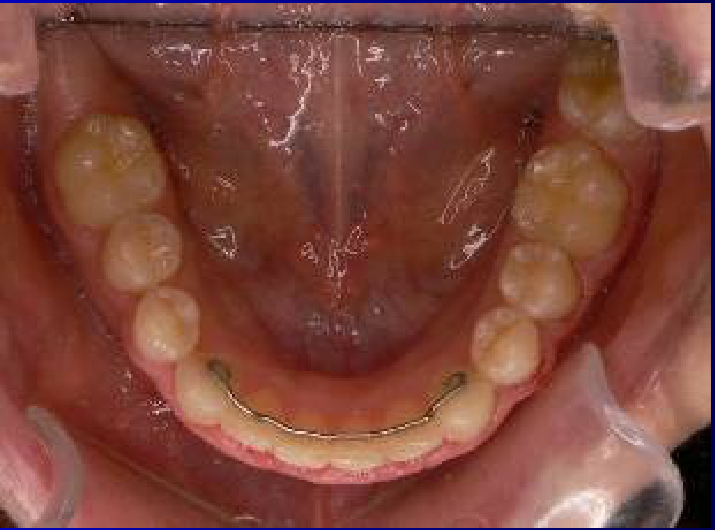
Case: Orthodontic management of a patient with a developmental disorder and visual impairment
Question
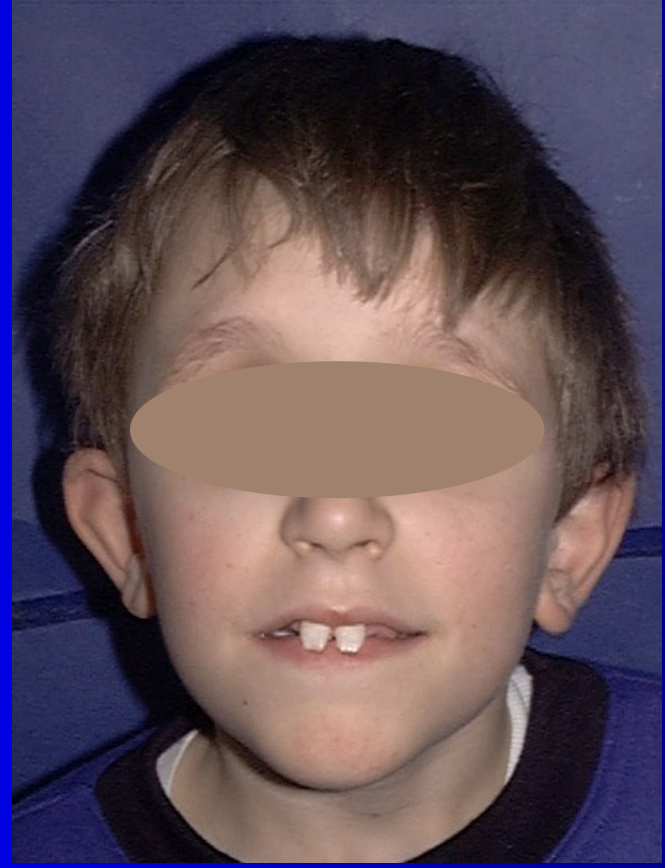
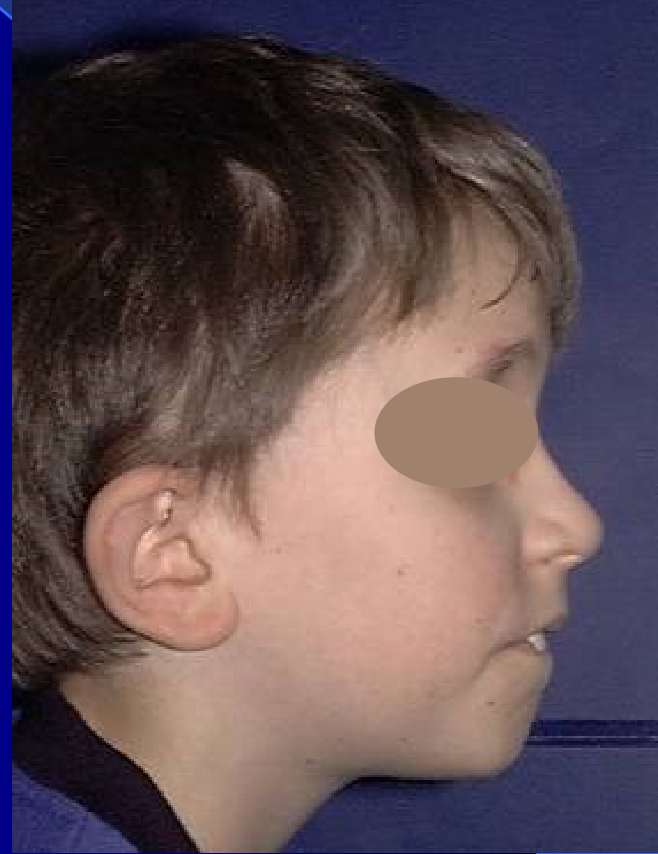
Scenario: A young boy with a developmental disorder and significant visual impairment presents with a moderate skeletal Class II malocclusion, maxillary constriction, malalignment, and irregular tooth form.
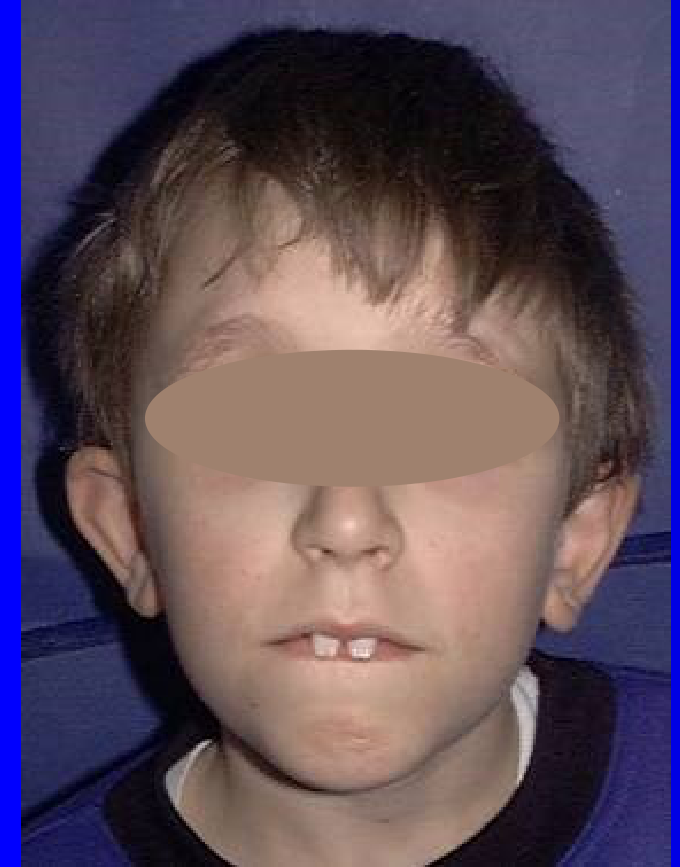
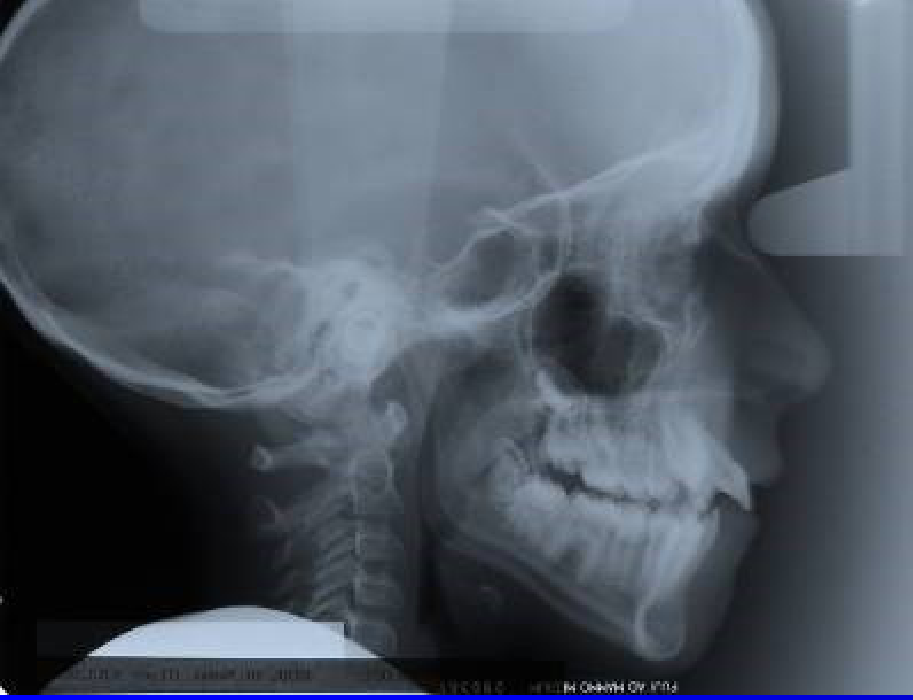
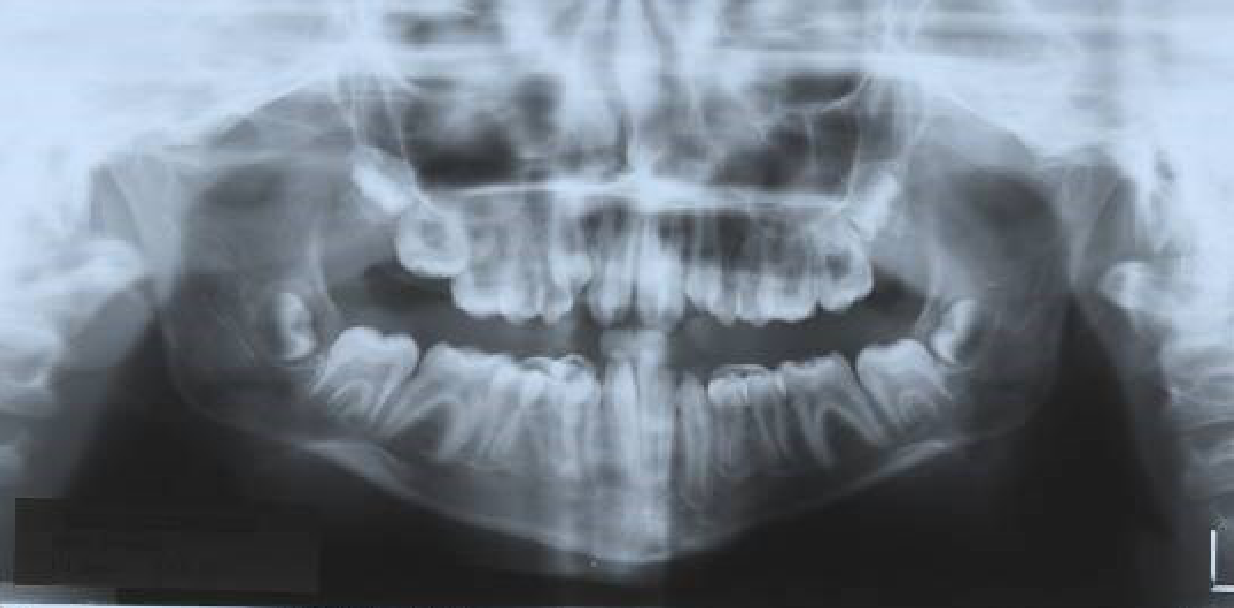
What’s shown: Clinical photographs of the face and intraoral condition. A lateral cephalometric radiograph and panoramic radiograph showing the dental and skeletal relationships. Intraoral photographs detail the misalignment, biofilm buildup, and trauma. Post-treatment photographs show the results of partial and full fixed appliances.
Consider: Analyze the radiographic and clinical findings, determine the sequence of orthodontic interventions required, and establish realistic treatment goals for a special needs patient with poor oral hygiene and severe crowding.
Answer
Observations:
- Developmental disorder, visual impairment, skeletal Class II, maxillary constriction, and irregular tooth form with incomplete crown formation of the molars.
- Lateral cephalometric radiograph shows extremely proclined upper incisors (around 35 degrees).
- Panoramic radiograph shows huge misalignment of anterior teeth with two lines of teeth (centrals forward, laterals backward).
- Intraoral examination reveals two lines of lower incisors massed outward, massive biofilm buildup, trauma, and recession and inflammation in the maxillary arch.
- Post-treatment images show partial braces on the top arch following maxillary expansion, alignment with NiTi wire, and extraction of primary teeth.
Reasoning: The extreme proclination of the upper incisors is caused by the interposition of the lower lip. The severe misalignment and two lines of teeth indicate significant crowding. Due to the imbalance of musculature and tongue posture, spontaneous correction (such as the tongue bringing laterals forward after primary extractions) will not occur, necessitating active space opening and alignment. The trauma and poor hygiene require immediate control and space provision. Step-by-step bonding (top arch then lower arch) was required due to the patient’s tolerance.
Outcome: Treatment involved rapid maxillary expansion, upper fixed appliances followed by full fixed appliances, force modules to protract the mandible, and restorations as required, all without sedation. Considerable parental involvement was necessary for home care. Following the extraction of primary teeth and alignment with NiTi wires, there was a significant improvement in trauma and alignment. Although some relapse occurred (estimated at 50%), the outcome was considered a major achievement compared to the pre-treatment condition.
Takeaway: For special needs patients with severe malocclusion and poor oral hygiene, treatment should be realistic and step-by-step, prioritizing oral hygiene control, maxillary expansion, minimum alignment, and space provision, while accepting some relapse as a success and relying heavily on parental involvement.
From the lecture slides
- Developmental disorder
- Significant visual impairment
- Moderate skeletal malocclusion Class II
- Maxillary constriction
- Malalignment
- Irregular tooth form (incomplete crown formation)
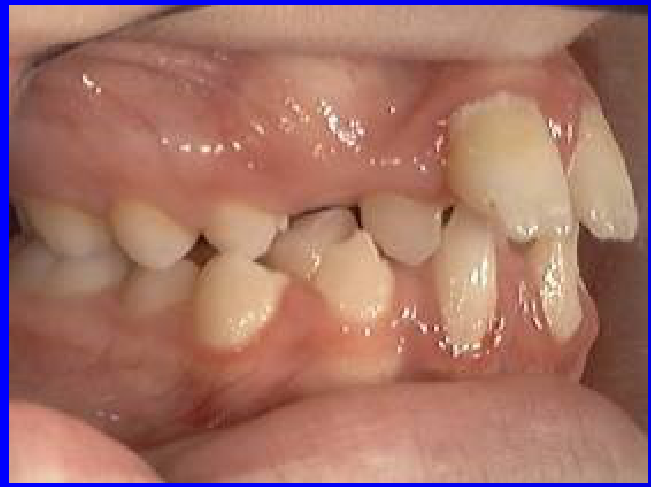
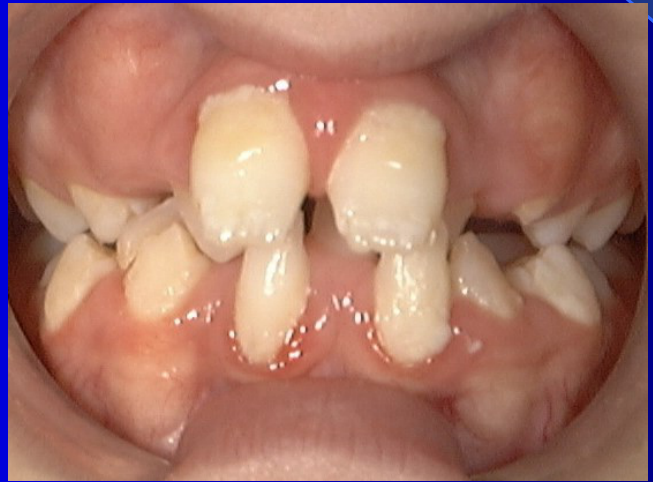
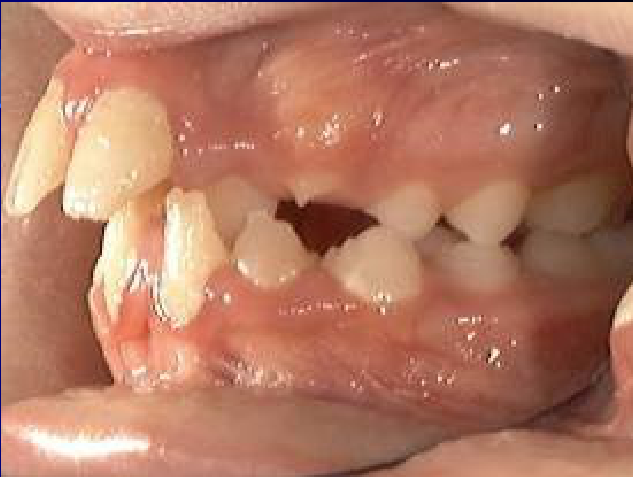
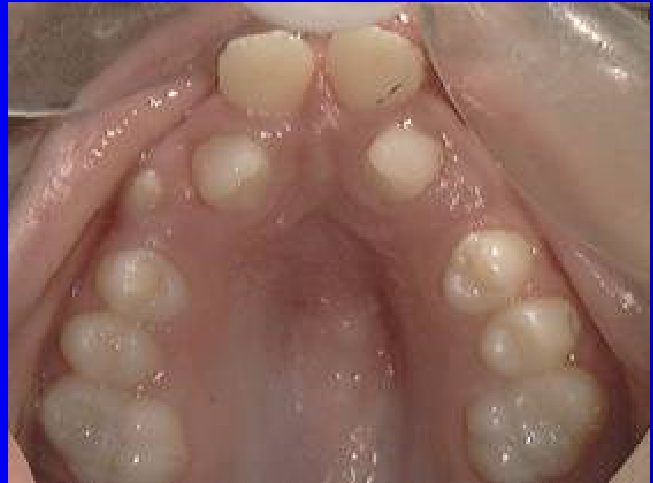
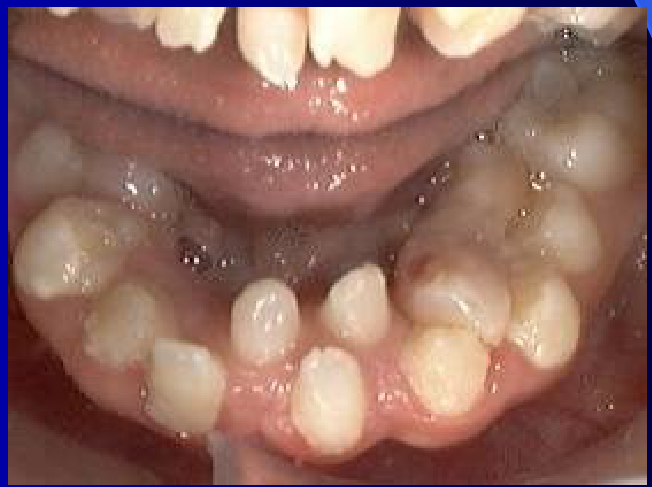
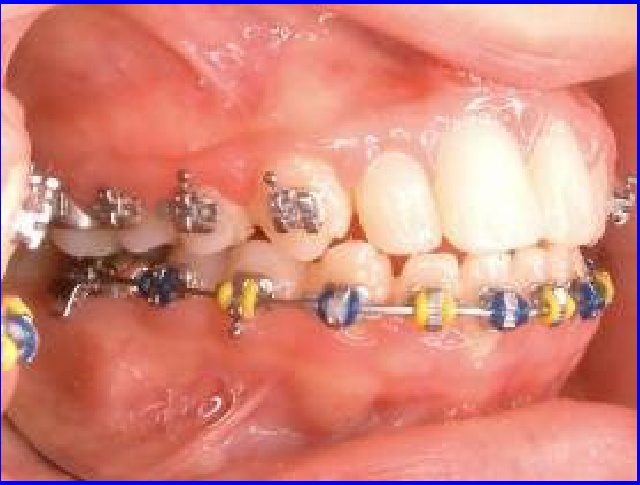
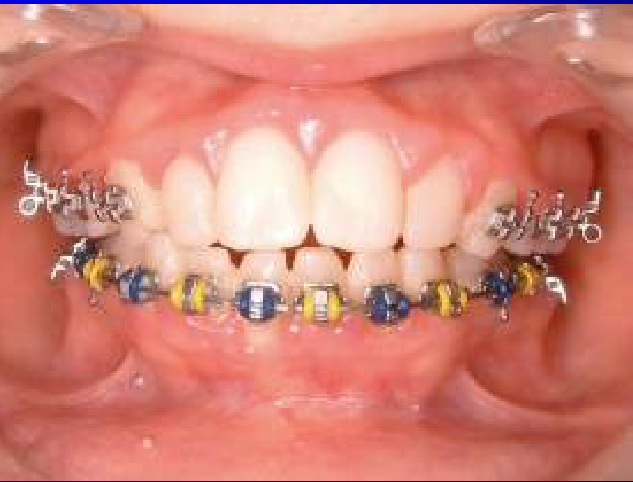
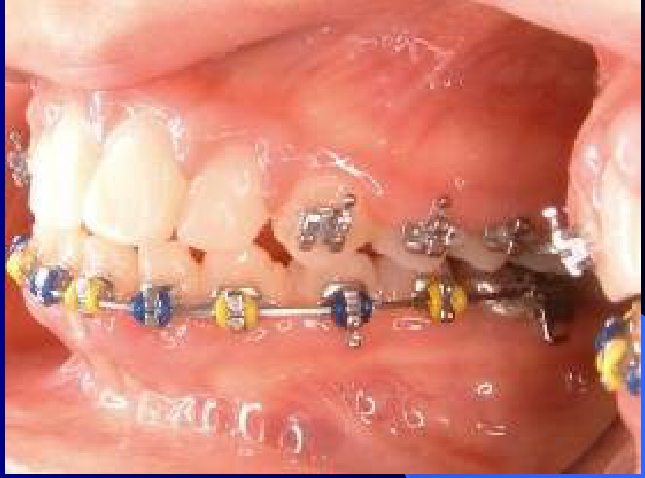
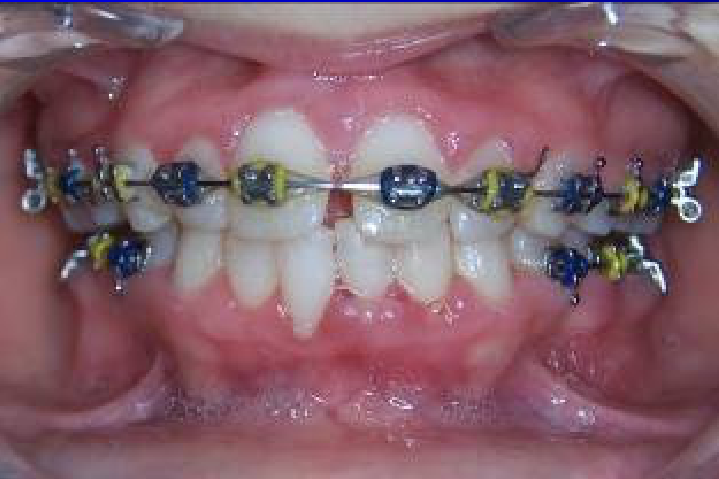
Nathan — Staged Correction
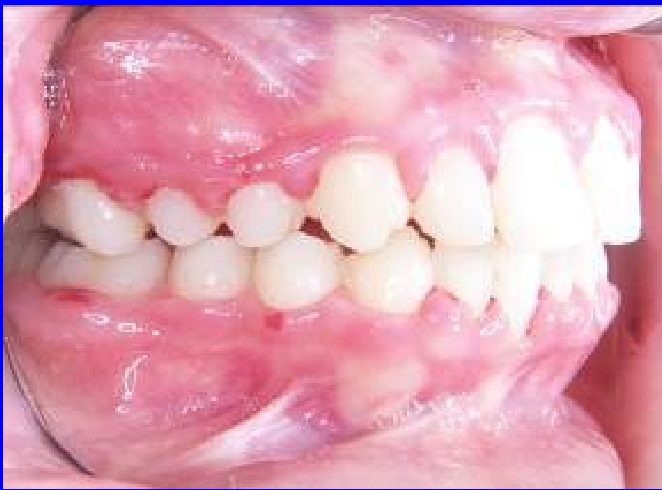
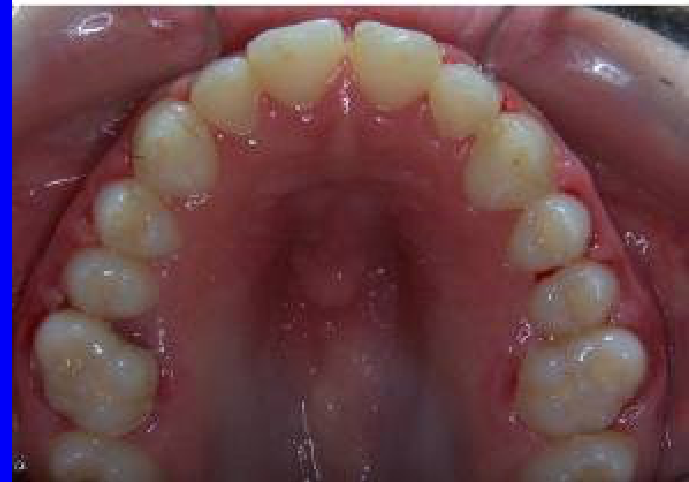
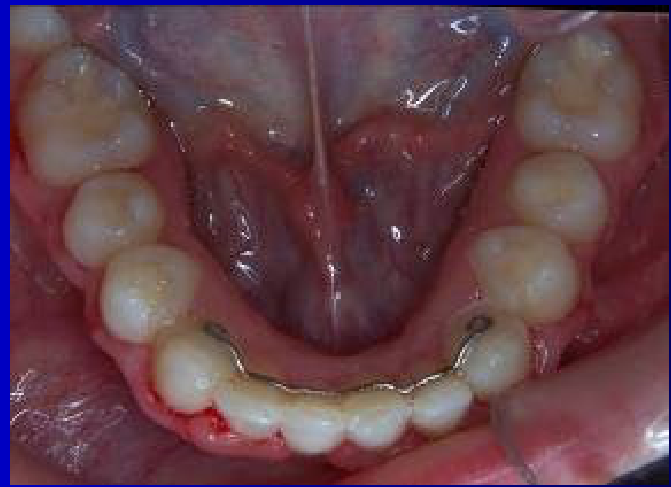
The patient referred to in the lecture as Nader had severe anterior misalignment, with central incisors positioned forward and lateral incisors positioned backward, appearing as two lines of teeth. Very proclined upper incisors, estimated at approximately 35 degrees, were also affected by lower-lip interposition.
- Substantial biofilm accumulated because the patient could not clean independently, while trauma had produced recession and inflammation.
- Treatment proceeded by controlling oral hygiene, treating caries, assessing premolar root development, extracting retained primary teeth, and expanding the maxilla to correct the posterior crossbite and create space.
- A partial upper fixed appliance was bonded in stages, followed by limited lower appliance treatment and elastics where tolerated; nickel-titanium wire was used for alignment.
- Spontaneous tongue-driven movement of the lateral incisors into the available space could not be expected because of the imbalance in musculature and tongue posture.
- The objectives were limited to maintaining posterior crossbite correction, achieving minimum intercuspation, providing some alignment, and improving trauma and the overall dental condition. Not all spaces could be closed; some relapse occurred, but the improvement was substantial compared with the original condition.
Nathan
- Rapid maxillary expansion
- Upper fixed appliances
- Full-fixed appliances
- Force modules to protract the mandible
- Restoration of the dentition as required
- No sedation required
- Considerable parental involvement in home care needs
Footnotes
-
Original PDF page 1: L6 The Special Needs Patient in Orthodontics, p.1 ↩
-
Original PDF page 2: L6 The Special Needs Patient in Orthodontics, p.2 ↩
-
Original PDF page 3: L6 The Special Needs Patient in Orthodontics, p.3 ↩
-
Original PDF page 4: L6 The Special Needs Patient in Orthodontics, p.4 ↩
-
Original PDF page 5: L6 The Special Needs Patient in Orthodontics, p.5 ↩
-
Original PDF page 6: L6 The Special Needs Patient in Orthodontics, p.6 ↩
-
Original PDF page 7: L6 The Special Needs Patient in Orthodontics, p.7 ↩
-
Original PDF page 8: L6 The Special Needs Patient in Orthodontics, p.8 ↩
-
Original PDF page 9: L6 The Special Needs Patient in Orthodontics, p.9 ↩
-
Original PDF page 10: L6 The Special Needs Patient in Orthodontics, p.10 ↩
-
Original PDF page 11: L6 The Special Needs Patient in Orthodontics, p.11 ↩
-
Original PDF page 12: L6 The Special Needs Patient in Orthodontics, p.12 ↩
-
Original PDF page 13: L6 The Special Needs Patient in Orthodontics, p.13 ↩
-
Original PDF page 14: L6 The Special Needs Patient in Orthodontics, p.14 ↩
-
Original PDF page 15: L6 The Special Needs Patient in Orthodontics, p.15 ↩
-
Original PDF page 16: L6 The Special Needs Patient in Orthodontics, p.16 ↩
-
Original PDF page 17: L6 The Special Needs Patient in Orthodontics, p.17 ↩
-
Original PDF page 18: L6 The Special Needs Patient in Orthodontics, p.18 ↩
-
Original PDF page 19: L6 The Special Needs Patient in Orthodontics, p.19 ↩
-
Original PDF page 20: L6 The Special Needs Patient in Orthodontics, p.20 ↩
-
Original PDF page 21: L6 The Special Needs Patient in Orthodontics, p.21 ↩
-
Original PDF page 22: L6 The Special Needs Patient in Orthodontics, p.22 ↩
-
Original PDF page 23: L6 The Special Needs Patient in Orthodontics, p.23 ↩
-
Original PDF page 24: L6 The Special Needs Patient in Orthodontics, p.24 ↩
-
Original PDF page 25: L6 The Special Needs Patient in Orthodontics, p.25 ↩
-
Original PDF page 26: L6 The Special Needs Patient in Orthodontics, p.26 ↩
-
Original PDF page 27: L6 The Special Needs Patient in Orthodontics, p.27 ↩
-
Original PDF page 28: L6 The Special Needs Patient in Orthodontics, p.28 ↩
-
Original PDF page 29: L6 The Special Needs Patient in Orthodontics, p.29 ↩
-
Original PDF page 30: L6 The Special Needs Patient in Orthodontics, p.30 ↩
-
Original PDF page 31: L6 The Special Needs Patient in Orthodontics, p.31 ↩
-
Original PDF page 32: L6 The Special Needs Patient in Orthodontics, p.32 ↩
-
Original PDF page 33: L6 The Special Needs Patient in Orthodontics, p.33 ↩
-
Original PDF page 34: L6 The Special Needs Patient in Orthodontics, p.34 ↩
-
Original PDF page 35: L6 The Special Needs Patient in Orthodontics, p.35 ↩
-
Original PDF page 36: L6 The Special Needs Patient in Orthodontics, p.36 ↩
-
Original PDF page 37: L6 The Special Needs Patient in Orthodontics, p.37 ↩
-
Original PDF page 38: L6 The Special Needs Patient in Orthodontics, p.38 ↩
-
Original PDF page 39: L6 The Special Needs Patient in Orthodontics, p.39 ↩
-
Original PDF page 40: L6 The Special Needs Patient in Orthodontics, p.40 ↩
-
Original PDF page 41: L6 The Special Needs Patient in Orthodontics, p.41 ↩
-
Original PDF page 42: L6 The Special Needs Patient in Orthodontics, p.42 ↩
-
Original PDF page 43: L6 The Special Needs Patient in Orthodontics, p.43 ↩
-
Original PDF page 44: L6 The Special Needs Patient in Orthodontics, p.44 ↩
-
Original PDF page 45: L6 The Special Needs Patient in Orthodontics, p.45 ↩
-
Original PDF page 46: L6 The Special Needs Patient in Orthodontics, p.46 ↩
-
Original PDF page 47: L6 The Special Needs Patient in Orthodontics, p.47 ↩
-
Original PDF page 48: L6 The Special Needs Patient in Orthodontics, p.48 ↩
-
Original PDF page 49: L6 The Special Needs Patient in Orthodontics, p.49 ↩
-
Original PDF page 50: L6 The Special Needs Patient in Orthodontics, p.50 ↩
-
Original PDF page 51: L6 The Special Needs Patient in Orthodontics, p.51 ↩
-
Original PDF page 52: L6 The Special Needs Patient in Orthodontics, p.52 ↩
-
Original PDF page 53: L6 The Special Needs Patient in Orthodontics, p.53 ↩
-
Original PDF page 54: L6 The Special Needs Patient in Orthodontics, p.54 ↩
-
Original PDF page 55: L6 The Special Needs Patient in Orthodontics, p.55 ↩
-
Original PDF page 56: L6 The Special Needs Patient in Orthodontics, p.56 ↩
-
Original PDF page 58: L6 The Special Needs Patient in Orthodontics, p.58 ↩
-
Original PDF page 57: L6 The Special Needs Patient in Orthodontics, p.57 ↩
-
Original PDF page 59: L6 The Special Needs Patient in Orthodontics, p.59 ↩
-
Original PDF page 60: L6 The Special Needs Patient in Orthodontics, p.60 ↩
-
Original PDF page 61: L6 The Special Needs Patient in Orthodontics, p.61 ↩
-
Original PDF page 63: L6 The Special Needs Patient in Orthodontics, p.63 ↩
-
Original PDF page 62: L6 The Special Needs Patient in Orthodontics, p.62 ↩
-
Original PDF page 64: L6 The Special Needs Patient in Orthodontics, p.64 ↩
-
Original PDF page 65: L6 The Special Needs Patient in Orthodontics, p.65 ↩
-
Original PDF page 66: L6 The Special Needs Patient in Orthodontics, p.66 ↩
-
Original PDF page 67: L6 The Special Needs Patient in Orthodontics, p.67 ↩
-
Original PDF page 68: L6 The Special Needs Patient in Orthodontics, p.68 ↩
-
Original PDF page 69: L6 The Special Needs Patient in Orthodontics, p.69 ↩
-
Original PDF page 70: L6 The Special Needs Patient in Orthodontics, p.70 ↩
-
Original PDF page 71: L6 The Special Needs Patient in Orthodontics, p.71 ↩
-
Original PDF page 72: L6 The Special Needs Patient in Orthodontics, p.72 ↩
-
Original PDF page 73: L6 The Special Needs Patient in Orthodontics, p.73 ↩
-
Original PDF page 74: L6 The Special Needs Patient in Orthodontics, p.74 ↩
-
Original PDF page 75: L6 The Special Needs Patient in Orthodontics, p.75 ↩
-
Original PDF page 76: L6 The Special Needs Patient in Orthodontics, p.76 ↩
-
Original PDF page 77: L6 The Special Needs Patient in Orthodontics, p.77 ↩
-
Original PDF page 78: L6 The Special Needs Patient in Orthodontics, p.78 ↩
-
Original PDF page 79: L6 The Special Needs Patient in Orthodontics, p.79 ↩
-
Original PDF page 80: L6 The Special Needs Patient in Orthodontics, p.80 ↩
-
Original PDF page 81: L6 The Special Needs Patient in Orthodontics, p.81 ↩
-
Original PDF page 82: L6 The Special Needs Patient in Orthodontics, p.82 ↩
-
Original PDF page 83: L6 The Special Needs Patient in Orthodontics, p.83 ↩
-
Original PDF page 84: L6 The Special Needs Patient in Orthodontics, p.84 ↩
-
Original PDF page 85: L6 The Special Needs Patient in Orthodontics, p.85 ↩
-
Original PDF page 86: L6 The Special Needs Patient in Orthodontics, p.86 ↩
-
Original PDF page 87: L6 The Special Needs Patient in Orthodontics, p.87 ↩