Natal & Neonatal Teeth1
Dr Jilen Patel BDSc (Hons) WA, DClinDent, MRACDS, FADI, FICD
Specialist Paediatric Dentist
Senior Lecturer, Clinical Dentistry
UWA Dental School
Outline2
- Definitions and nomenclature
- History
- Prevalence
- Etiology
- Clinical presentation and classification
- Histology and ultrastructure
- Complications
- Diagnosis and differential diagnosis
- Management
- Conclusion
Definitions And Nomenclature
- Natal Teeth are teeth present in the oral cavity of the infant 🔴at the time of birth (Massler and Savara, 1950)
Definitions3
-
Natal teeth are teeth present in the oral cavity of the infant at the time of birth (Massler and Savara, 1950)
-
Neonatal teeth are teeth which erupt during the neonatal period (from birth to 30 days) (Massler and Savara, 1950)
-
Early infancy teeth are teeth which erupt within one to three and a half months of life (Spouge and Feasby, 1966)
-
Precocious teeth are teeth which erupt during the third to fifth month of life (Bodenhoff and Gorlin, 1963)
-
Natal teeth are usually true primary teeth rather than supernumerary teeth; approximately 95% are primary teeth.
-
If a true primary natal tooth is lost, there will generally not be another tooth in that position until the permanent successor erupts.
Nomenclature4
- Congenital teeth
- Fetal teeth
- Infancy teeth
- Pre-deciduous teeth
- Dentitia praecox
- Dens connatalis
- Precocious dentition
(Zhu and King, 1995; Mayhall, 1967; Kates et al. 1984)
- The terms “natal teeth” and “neonatal teeth” are the main terms used, although other descriptions have also been reported.
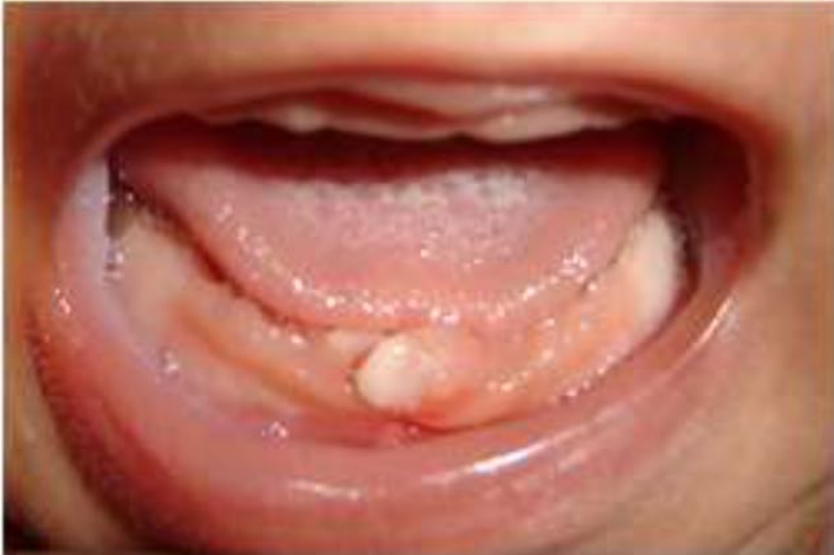
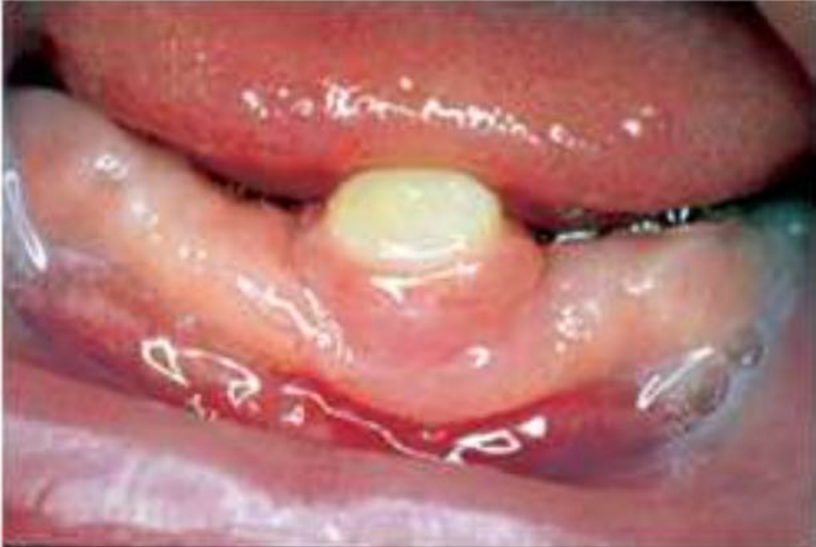
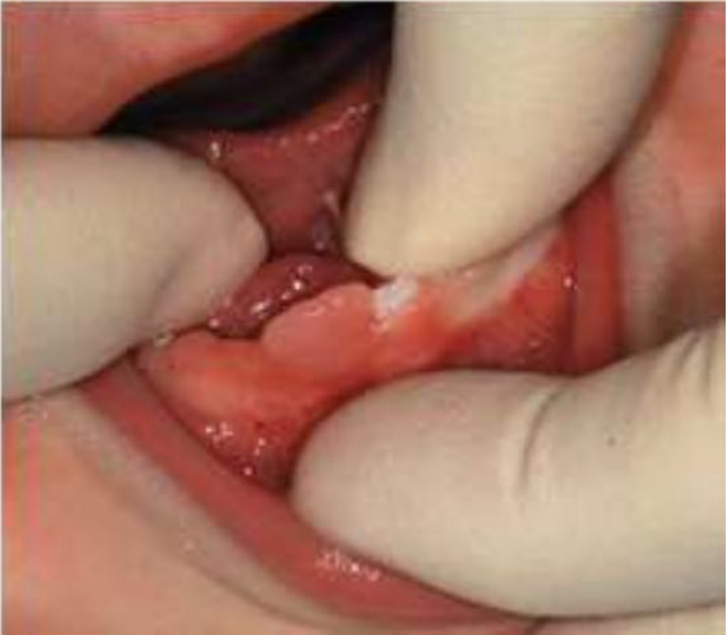
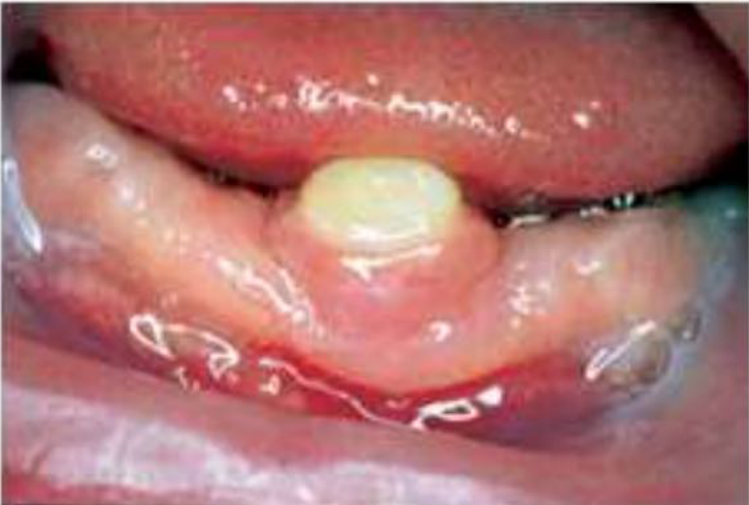
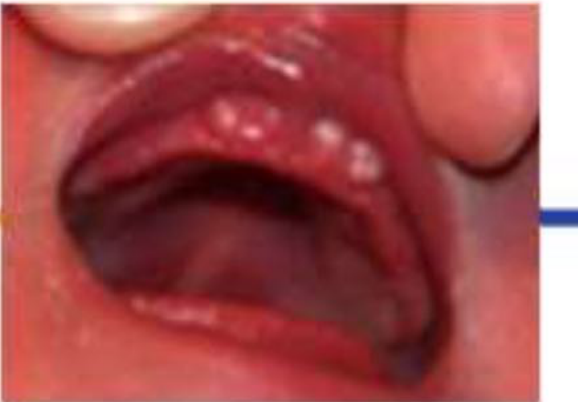
- Natal and neonatal teeth may vary considerably in structure and appearance, ranging from a relatively complete tooth crown or a thin enamel shell to only incisal edges, a partly erupted tooth, or a swelling caused by an unerupted tooth.
History5
Natal and neonatal teeth have been a subject of curiosity and study since the time it was first documented by Titus Livius, in 59 BC.
Gaius Plinius Secundus (the Elder), in 23 BC, believed that a splendid future awaited male infants with natal teeth. In females it was considered a bad sign and that they bring disaster to their community.
Diverse Superstitions6
| Region | Belief |
|---|---|
| Africa, India, Poland | monstrous and bearer of misfortune |
| China | bad omen for girls |
| England | grow up into famous soldiers |
| France & Italy | future conquerors of the worlds |
Allwright, 1958; Bodenhoff & Gorlin, 1963; Zhu & King, 1995.
Lecturer — Cultural Impact
Cultural and historical beliefs may be particularly important in some regions, including parts of East Africa and Nigeria.
- In some communities, a child born with a natal tooth may be associated with evil spirits.
- Families may attempt to hide the child, and the child may be bullied throughout childhood.
- Parents may be told to get rid of the child, despite the scientific view that a natal tooth is a natural dental finding.
- Clinicians should be aware of these cultural factors when counselling families.
Superstition
Prevalence And Incidence7
-
Natal teeth are three times more common than neonatal teeth (Rao and Mathad, 2009)
-
Natal teeth are 🔴three times more common than neonatal teeth (Rao and Mathad, 2009)
-
95% are true primary teeth; 5% are supernumerary teeth (Kates et al., 1984)
-
🔴95%: true primary teeth; 🔴5%: supernumerary teeth (Kates et al. 1984)
-
The incidence of natal and neonatal teeth has been investigated in multiple studies:
- 1:716 to 1:30,000 (Zhu and King, 1995)
- 1:2,000 to 1:3,500 (Chow, 1980)
Lecturer — Incidence Variation
The reported incidence varies according to the population studied.
- The population may consist of fit and healthy children, children with cleft lip and palate, or children with syndromes or more complex medical histories.
- More complex medical histories are associated with a greater likelihood of oral anomalies, including natal teeth.
Gender Predilection And Site Distribution
Gender Predilection8
- F > M (Zhu & King, 1995; Goncalves et al., 1998)
- F : M = 66% : 31% (Anegundi et al., 2002)
- F = M (Basavanthappa et al., 2011)
Lecturer — Gender Evidence
A gender difference has been reported in some studies, but the lecturer considered the evidence uncertain.
- Findings may depend on where the study was conducted, the sample size, and the characteristics of the population studied.
- No definite, clinically significant gender discrepancy was identified.
Site Distribution
- Mandibular incisor region (85%) — Gardina, 1961; Bodenhoff & Gorlin, 1963
- Maxillary incisors (11%) — King and Lee, 1989
- Mandibular canine (3%) — King and Lee, 1989
- Maxillary canine and molar (<1%) — King and Lee, 1989
- Multiple neonatal and natal teeth are rare (Ooshima et al., 1986)
Eruption Pattern and Assessment
Natal teeth most commonly occur in the mandibular incisor region because the mandibular incisors are usually the first teeth to erupt.
Natal teeth most commonly occur in the 🔴mandibular incisor region, corresponding to the fact that mandibular incisors are normally among the first teeth to erupt.
- The presence of an upper incisor before a lower incisor is not necessarily concerning.
- Eruption of a molar while other teeth have not erupted is atypical and should raise concern; a primary molar without other erupted teeth suggests that further assessment is needed.
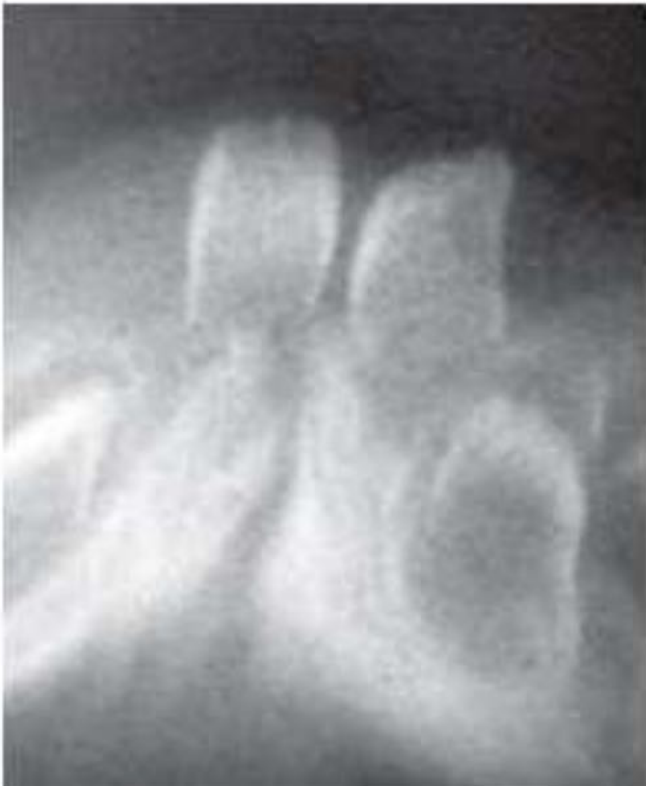
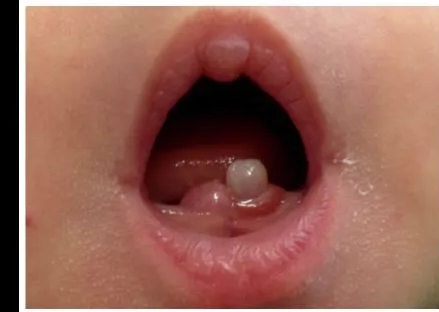
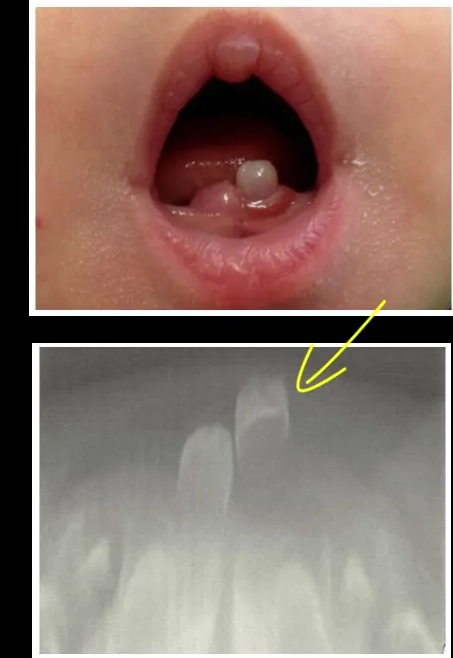
- A case report described a preterm newborn with an erupted mandibular central incisor. Radiographs identified it as the primary mandibular central incisor rather than a supernumerary tooth, and the developing underlying permanent successors were also visible.
Aetiology9
- Unknown
- Superficial position of tooth germ in alveolar bone during development (Cunha et al. 2001)
- Trauma or infection
- Osteoclastic activity within tooth germ area (bone remodelling) (Goncalves, 1998)
- Hereditary transmission of an autosomal dominant gene, with a familial trait in 8–62% of cases (Hyatt, 1965; Zhu & King, 1995)
- Certain syndromes and newborns with orofacial clefts (Motoyama et al. 1967)
Lecturer — Superficial Tooth Germ
The superficial position of the tooth germ is the most accepted explanation for natal teeth and explains their early eruption.
- It may also account for the incompletely developed root, tooth mobility, and attachment mainly to the surrounding gingival tissues.
Maternal-Related Factors10
-
dietary deficiencies (malnutrition)
- poor maternal health
- endocrine disturbances: pyelitis and hypovitaminosis during pregnancy
- excessive secretion of pituitary, thyroid or gonads
(Khatib et al. 2005; Vucicevic et al. 2007)
-
Febrile state: increased body temperature can affect the normal eruption of teeth, e.g. fever, exanthemata
(Massler & Savara, 1959; Vucicevic et al. 2007)
-
Environmental factors
- polychlorinated biphenoyls & bibenzofurans ?
(Yamaguchi et al. 1971; Gladen et al. 1990)
Lecturer — Maternal Associations
Maternal-related factors have been reported as possible associations, but the evidence generally demonstrates association rather than causation.
- Malnutrition or another maternal condition does not necessarily mean that the child will develop natal teeth.
- Findings depend on the type and design of the studies considered.
- Discoloration may be present.
- Both partial and complete eruption may occur.
- Although the teeth may occur in pairs, solitary teeth also occur.
Clinical Presentation1112
- Usually small and conical
- May resemble normal primary teeth in size and shape
- Usually have an immature appearance with poorly-developed, hypoplastic enamel and dentine
- Usually occurs in pairs
Zhu & King, 1995; Galassi et al. 2004; Ziai et al. 2005.
- May be attached to the mucosa and are occasionally covered by a pad of soft tissue
- Absent or poor root development
- Mostly mobile
Zhu & King, 1995; Galassi et al. 2004; Ziai et al. 2005.
Lecturer — Parental Concerns
Parents may describe the finding as a white object in the mouth, something flapping around, or a possible tooth or tumour.
- Parents of newborns may be especially vulnerable to anxiety about unusual oral findings.
- The appearance of a natal tooth does not by itself confirm that the finding is a tooth, since other neonatal abnormalities can produce swellings or white lesions.
 |  |
 |  |
Classification
Hebling et al. 1997
Classification - Spouge And Feasby 196613
A mature natal or neonatal tooth
- A tooth which is nearly or fully developed
- Relatively good prognosis for maintenance
The immature natal or neonatal tooth
- A tooth with incomplete or substandard structure
- Implies a poor prognosis
Lecturer — Clinical Determination
Although the classification distinguishes mature from immature teeth, the distinction may be difficult to establish clinically.
- In a neonate, it may be difficult to distinguish a solid crown from an enamel shell based only on appearance.
Classification - Hebling Et Al 19971415
Hebling et al. 1997
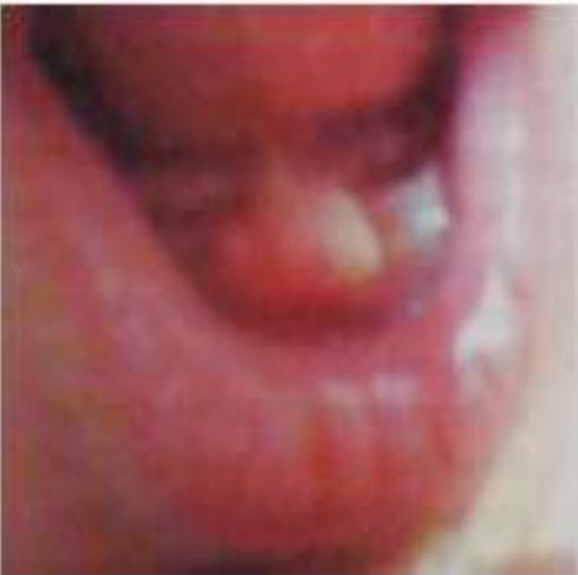
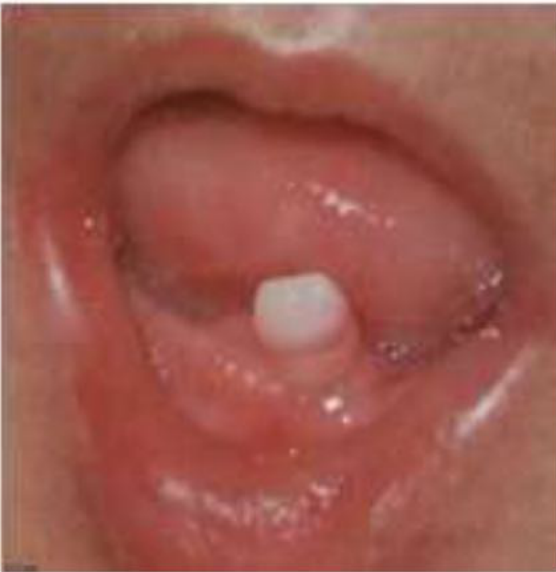
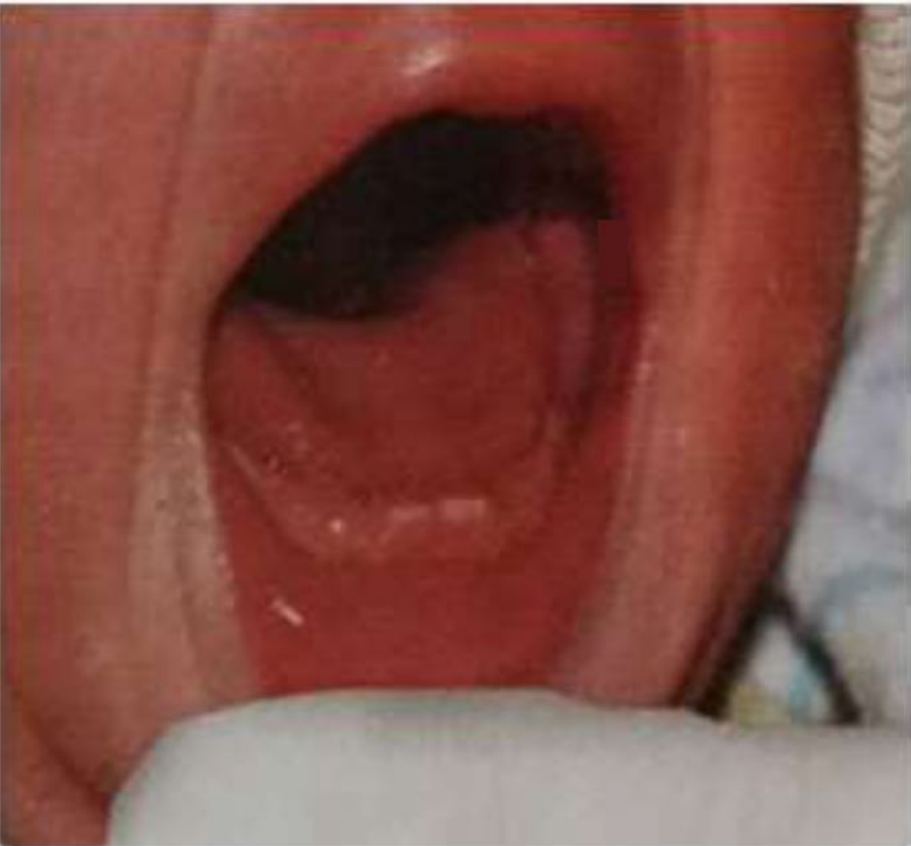
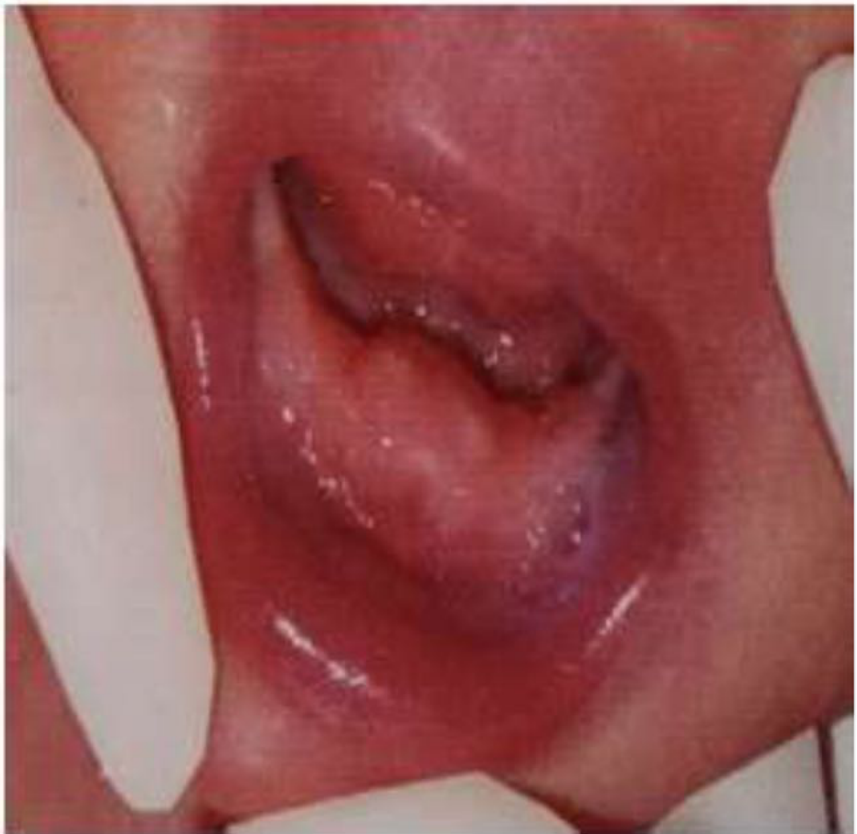
The appearance of each natal tooth in the oral cavity can be classified into four categories, given as follows, as the teeth emerge in the oral cavity:
1. Shell-shaped crown
- Poorly fixed to the alveolus by the gingival tissue
- Absence of a root
2. Solid crown
- Poorly fixed to the alveolus by the gingival tissue
- oedema of the gingival tissue
- Little or no root
- Eruption of the incisla margin
3. Eruption of the incisal margin of the crown through the gingival tissue
4. Edema of the gingival tissue with an unerupted palpable tooth
Lecturer — Morphological Variation
The Hebling classification considers morphological variations rather than providing an easily applied clinical determination of maturity.
- Natal teeth do not all have the same structure, ranging from thin shells to relatively fully developed teeth and forms consisting only of incisal edges or producing a tissue bulge while remaining unerupted.
 |  |
 |  |
Histology And Ultrastructure
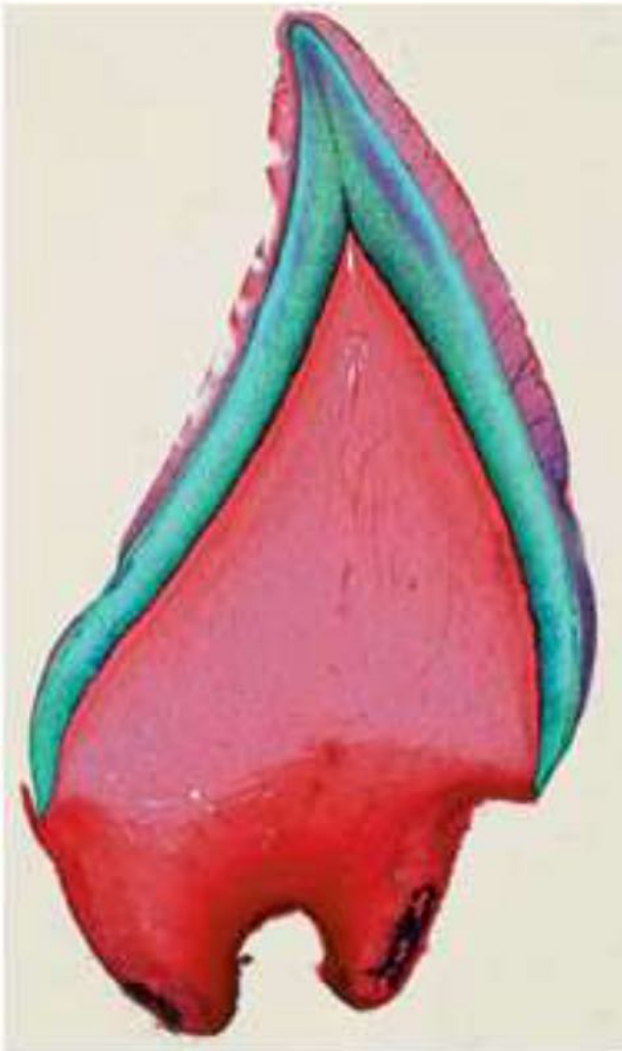
Histology1617
Enamel (Ndiokwelu et al. 2004, To 1992)
- Thin layer of enamel or absence of the enamel
- Enamel hypoplasia/hypomineralisation
Dentin (Massler & Savara, 1950; Zhu & King, 1996; Uzamis et al. 1999; Leung & Robson, 2006)
- Interglobular dentin in the coronal region
- Irregular dentin and cell inclusions in the cervical region
- Atypical dentin (due to the response to irritant stimulus from oral cavity)
Dentino-enamel junction: not scalloped
Cementum
- Lack of cementum and Hertwig’s sheath
- Acellular cementum in some cases (thinner than normal)
Pulp canal and pulp chamber (Howkins 1932, Massler & Savara 1950, Hals, 1957, Clergeau-Guerithault, 1991, Friend et al. 1991)
- Larger than normal
- Vascularised pulps along with few inflammatory cells
Roots (Massler & Savara, 1950, Allwright 1958, Leung & Robson 2006)
- Lack of root formation (despite the tooth is erupted in the oral cavity)
Structural Characteristics18
-
Enamel of the teeth exhibited hypoplastic, depressed areas, and the incisal edge of natal tooth lacked enamel (Jasmin & Clergeau-Guerithault, 1991)
-
Thickness of enamel was around 280 microns compared to up to 1200 microns in normal teeth (Uzamis et al. 1999)
-
Enamel has normal prism structure and mineralization (prism structure can be absent in the cervical part of the enamel)
-
Cervical and apical dentin is tubular
-
In developing teeth, the dentin in these regions changed to an irregularly formed hard tissue of osteodentin character (in which enclosed cells could be observed) (Masatomi et al. 1991)
-
Enamel may also be pitted and characterized by additional grooves
Lecturer — Clinical Consequences
These histological findings are primarily of academic interest, but they are clinically relevant because defective tooth structure is more susceptible to breakdown.
- Breakdown may lead to discoloration, caries, abscess formation, and infection.
- Because the pulp may be large and vascularized, enamel breakdown can create a risk of pulpal and periapical problems.
- Tooth mobility is related to early eruption and incomplete root development.
Complications19
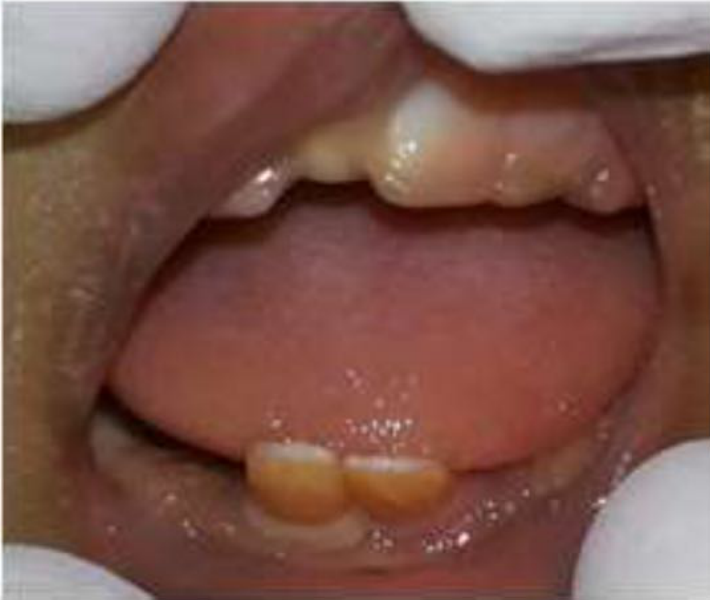
- Dysplastic enamel
- Mobility — potential risk of aspiration
- Difficulty suckling — interfere with feeding
- Traumatic injury to the baby’s tongue and/or to the maternal breast
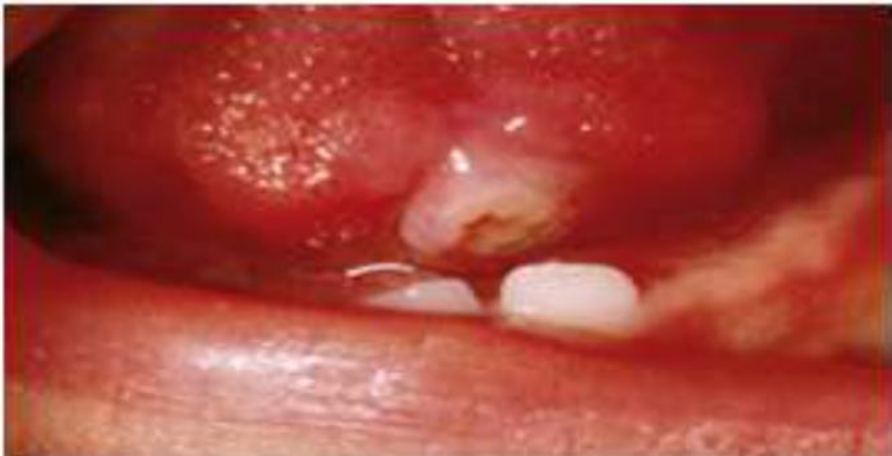
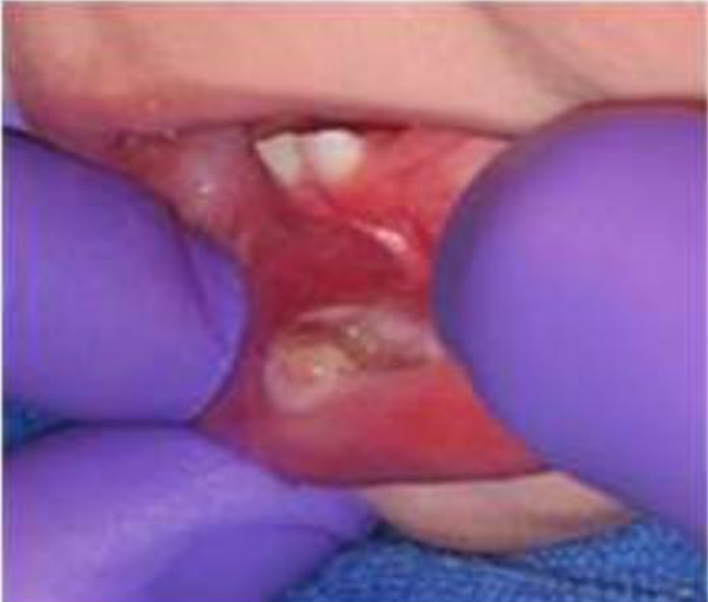
- Riga-Fede disease
 |  |
 |
Poor Quality Enamel20
-
Increased risk of caries
-
Chipping and attrition
-
Periapical abscesses
-
The tooth may become discoloured.
-
Pits, grooves, and other enamel defects may create areas susceptible to further breakdown. Allwright, 1958; Kates et al. 1984.
Mobility21
- “[Natal] teeth are loose and moveable in the early stages and there is a constant danger of the teeth becoming detached and either swallowed or aspirated, especially during nursing” (Brauer et al 1947 as cited by Massler & Savara 1950)
- No reports of inhalation of an exfoliated natal tooth (Gardiner 1961)
- “Inhalation of one of these teeth has never been reported in the literature and the danger is probably more imaginary than real” (Spouge & Feasby 1966)
Lecturer — Natal Tooth Mobility
Natal teeth may be very mobile because the root has not developed normally.
- Although mobility may appear severe, the tooth may still be attached firmly to the gingival tissues.
- Extraction may require separation of the tooth from the gingival tissues rather than simple removal from a socket.
Difficulty Feeding22
-
Presence of natal teeth may cause discomfort for the mother when the infant is suckling
- interfere with feeding
- ulceration
- laceration
(Bodenhoff & Gorlin 1963, Massler & Savara 1950)
-
Children with normal primary teeth have often been nursed up to 2-3 years of age without complication (Massler & Savara 1950)
Lecturer — Feeding Difficulty
Feeding difficulty is one of the most significant practical complications.
- Feeding may be difficult for the infant and distressing for the parent.
- Feeding is particularly difficult when the tooth causes pain or ulceration.
Riga-Fede Syndrome23
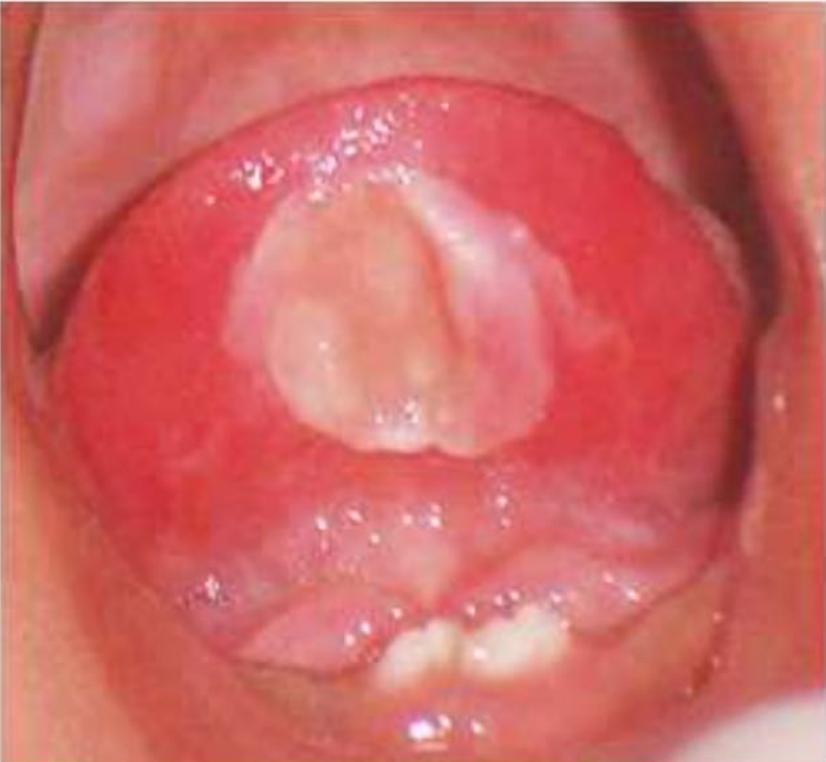
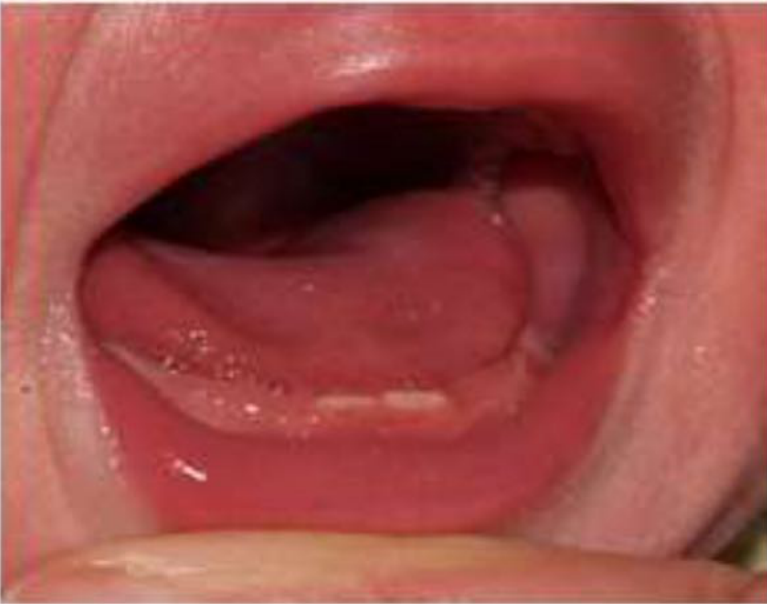
- Benign ulceration of the ventral surface of the tongue or lingual frenum caused by repetitive trauma from the sharp incisal edges of teeth (Choi et al. 2009, Bodenhoff & Gorlin, 1963)
- In infants, the tongue rests between the alveolar processes, causing the ventral surface of the tongue to rest against the incisal edges of natal teeth (Massler & Savara 1950)
- Discomfort, refusal to feed (Massler & Savara 1950)
Sublingual ulceration of a 27 day old male resulting from natal teeth (Patil and Dixit 2013)
Lecturer — Riga-Fede Terminology
The lecturer clarified that Riga-Fede is not really a disease or syndrome in the strict sense.
- The term describes the ulceration and related signs caused by the natal tooth.
- The ulceration may be severe and painful, leading the child to avoid feeding.
Associated Systemic Conditions24
- Cleft lip, palate and cyclopia (Boyd & Miles 1951, de Almeida & Gomide 1996)
- Ellis-Van Creveld (Chondroectodermal Dysplasia) (Weiss, 1955)
- Pachyonychia Congenita (Jadassohn-Lewandowsky) (Bodenhoff & Gorlin 1963, Leung 1986)
- Hallermann-Streiff (Oculomandibulodyscephaly with Hypotrichosis) (Robotta & Schafer, 2011)
- Steatocystoma Multiplex (McDonald & Reed 1976, King & Lee 1987)
- Pierre-Robin
- Pallister-Hall
- Short Rib-Polydactyly (type II)
- Wiedemann-Rautenstrauch (Neonatal Progeria)
- Pfeiffer, Ectodermal Dysplasia, Craniofacial Dysostosis
- Rubinstein-Taybi
- Sotos
- Adrenogenital
- Epidermolysis-Bullosa Simplex including Van der Woude
- Down’s Syndrome (Ndiokwelu et al. 2004)
- Walker-Warburg Syndromes (Venkatesh and Adhisivam, 2011)
Lecturer — Systemic Associations
An association does not mean that the condition causes natal teeth or that every child with the condition will have natal teeth.
- Children with cleft lip and palate may have an increased occurrence of natal teeth, but cleft lip and palate does not necessarily cause them.
- Some reported associations may reflect that a particular group of children was studied and oral anomalies were identified.
- Caries should not be treated as a feature of a syndrome: it requires bacteria, diet, a susceptible tooth, and time, which are environmental factors.
Diagnosis And Differential Diagnosis
Diagnosis25
- History
- Clinical examination
- Radiograph?
Lecturer — Clinical Assessment
Diagnosis should also consider the child’s medical history and a careful examination of the finding.
- Assess whether it appears to be a tooth, whether it is mobile, and whether it causes ulceration or interferes with feeding.
- Lift the lip fully to inspect for enamel defects, grooves, discoloration, abscesses, or other areas of breakdown, since abnormalities may be hidden by surrounding tissues.
- If the diagnosis is uncertain, referral is recommended rather than simply monitoring the finding.
Differential Diagnosis26
-
Supernumerary teeth (Zhu & King, 1995)
-
Bohn’s nodules (Leung and Robson, 2006)
-
Dental lamina cysts (gingival cyst of newborn) (Leung and Robson, 2006)
-
Inclusion cysts (Kumar et al. 2008)
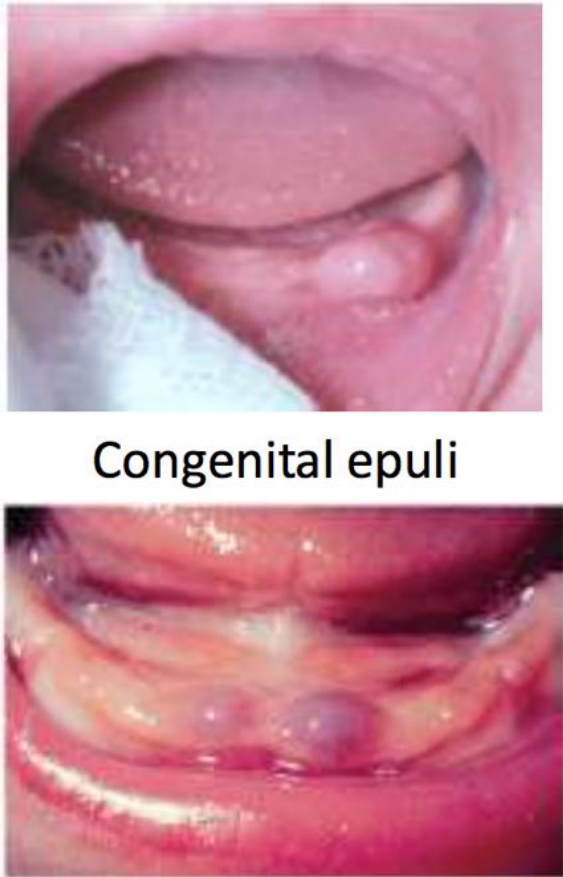
- Congenital epulis
- Odontogenic hamartomas
-
Lymphangioma of the alveolus (Leung, 1986; Leung and Robson, 2006)
-
Eruption cyst
-
Epstein pearls
-
Neuroectodermal tumour of infancy
-
Foreign bodies lodged in the gingiva
Lecturer — Newborn Oral Lesions
Bohn’s nodules are small, white, keratin-filled cysts usually found on the alveolar ridges.
- They are common, with a prevalence approaching 60%, generally require no treatment, and exfoliate on their own.
- Epstein pearls are similar lesions found on the palate along the suture line where the palatal shelves fuse.
- Because newborns may have multiple oral abnormalities, an uncertain lesion should be referred for assessment.
 |  |
Radiographs272829
What can you see?
-
When does calcification of primary incisors begin?
-
When does calcification of permanent incisors begin?
-
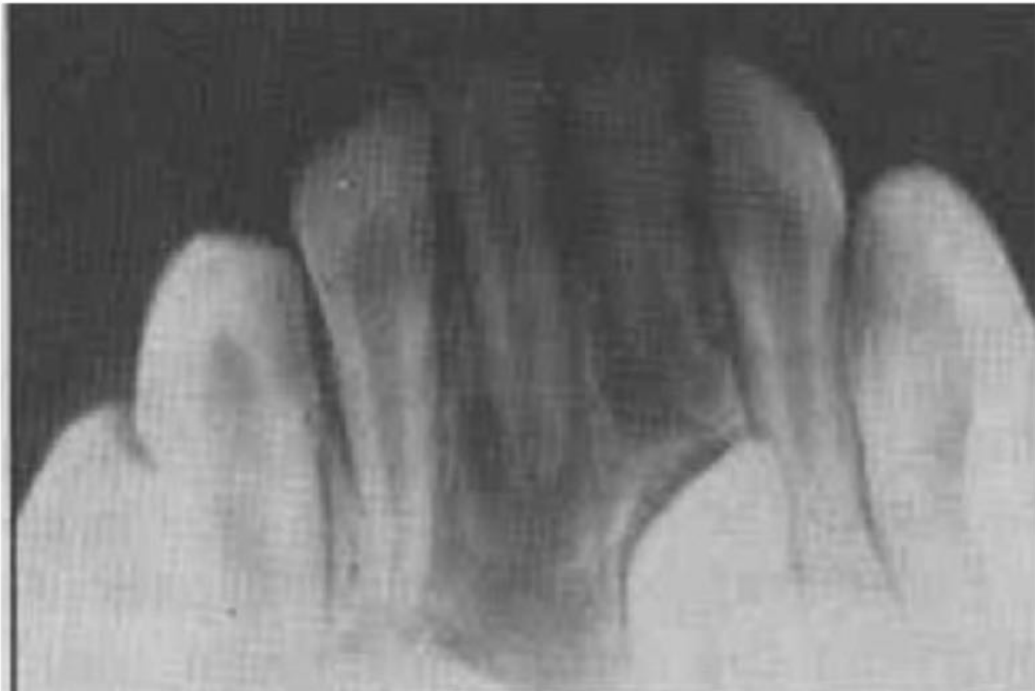
A radiographic verification of the relationship between a natal and/or neonatal tooth and adjacent structures, nearby teeth, and the presence or absence of a germ in the primary tooth area
-
Differentiate the premature eruption of a primary tooth from a supernumerary tooth
-
Provides information about root development
-
Shows tooth’s relationship to underlying structures
Lecturer — Radiograph Use
The lecturer questioned the routine diagnostic value of radiographs in neonates because a very young infant may be exposed to radiation while the permanent incisors have not yet begun to calcify.
- Radiographic findings may not change management: if ulceration or feeding problems require removal, the tooth may be removed whether or not it is supernumerary, and its status can be clarified later.
- Radiographs may be considered when the lesion does not clearly appear to be a tooth and another diagnosis is suspected.
- Routine radiographs are generally not considered necessary when the clinical diagnosis is clear; the ALARA principle requires weighing radiation risks against diagnostic benefits.
Massler & Savara 1950; Leung, 1986; Almeida et al. 1997; Cunha et al. 2001.
- ALARA principle
- Diagnostic quality of radiograph
- Risk / benefit
Lecturer — Stoma Adhesive Wafers
Stoma adhesive wafers may be a practical way to reduce trauma and allow the ulcer to heal.
- They are thin, mould to the tissues, adhere in the presence of moisture, and are biocompatible.
- The child can then be reviewed later, although access to these materials may depend on whether the clinician is working in a hospital setting.
 |  |
Management
Treatment Planning Factors30
The treatment planning of these natal or neonatal teeth depends on various factors including:
- Degree of mobility
- If the tooth is supernumerary or is part of the normal dentition
- Inconvenience during suckling
- Problems associated with breastfeeding
If the erupted tooth is diagnosed as a tooth of the normal dentition, maintenance of these teeth in the mouth is the first treatment option (Chow, 1980, Roberts, 1992).
Lecturer — Conservative Management
Conservative management is preferred when the child is feeding well and the tooth is not causing significant problems.
- Parents can be reassured that the tooth is usually a true primary tooth and may become firmer as development continues.
- Referral is generally recommended, particularly for complex cases or when extraction is being considered.
No Treatment31
- If the tooth is asymptomatic
- Breastfeeding is not impaired
(Boyd and Miles, 1951)
Application of a corticosteroid in orabase (such as kenalog) can aid in relieving the symptoms of the ulcer (Slayton, 2000; Choi et al. 2009).
Lecturer — Neonatal Topical Pastes
The lecturer did not generally recommend over-the-counter pastes such as Kenalog for neonates.
- The product may spread throughout the mouth and be ingested, creating concerns about excessive exposure or overdose.
 | 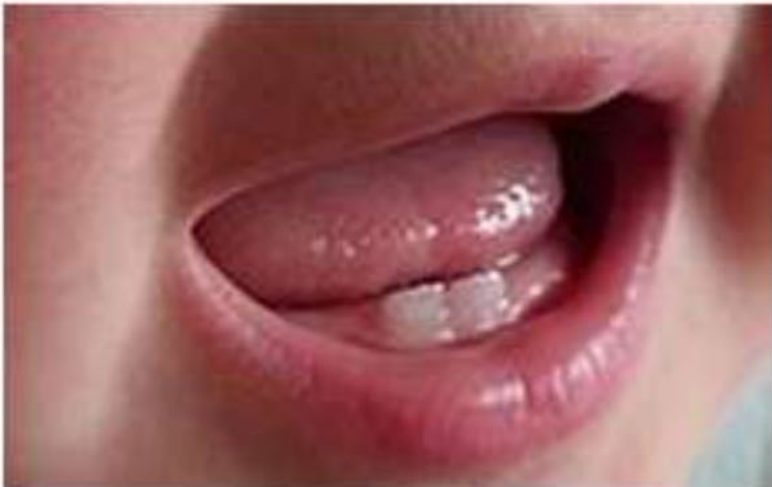 |
Grinding And Smoothing32
Smoothing of the tooth by grinding should be carried out if tooth is causing:
- Mild subgingival ulceration or mild discomfort to the mother
- Trauma to the infant’s tongue
Finishing burs, sandpaper disc, soflex disc can be used for smoothing (Allwright 1958, Choi et al 2009, Slayton 2000).
Lecturer — Smoothing Safety
Grinding or smoothing is technically difficult and potentially unsafe in a neonate.
- Risks include injury to the tongue or lip and difficulty controlling the instrument.
- A soft-flex disc should not be used casually; referral to an appropriate paediatric or hospital setting is recommended.
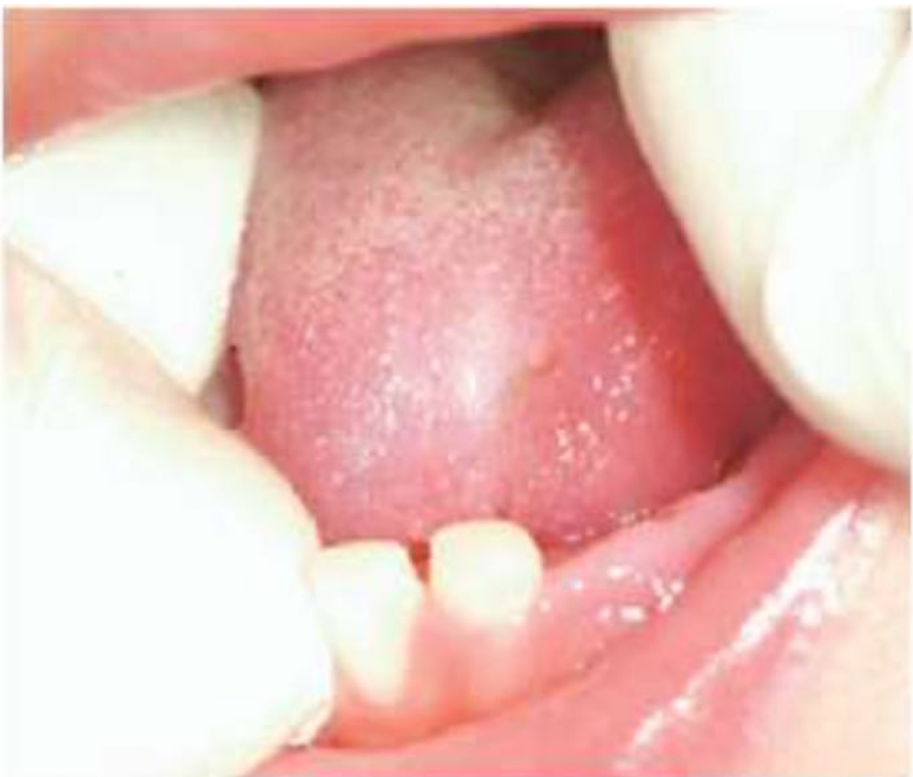
Intraoral photograph of 2-month-old girl with tongue ulcer lesion caused by neonatal tooth; intraoral photograph of the same infant, 1 month after grinding the sharp incisor edge. The lesion was resolved.
(Choi et al. 2009)
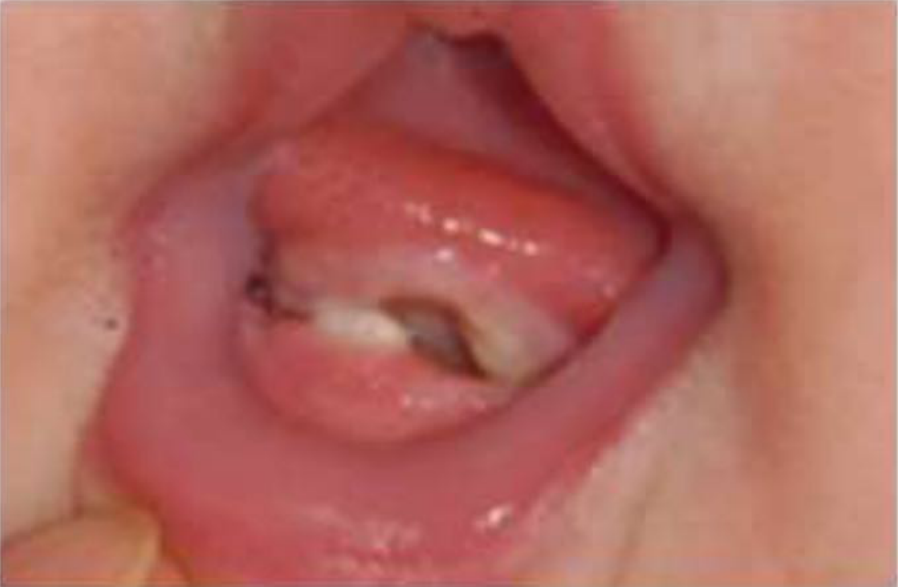 | 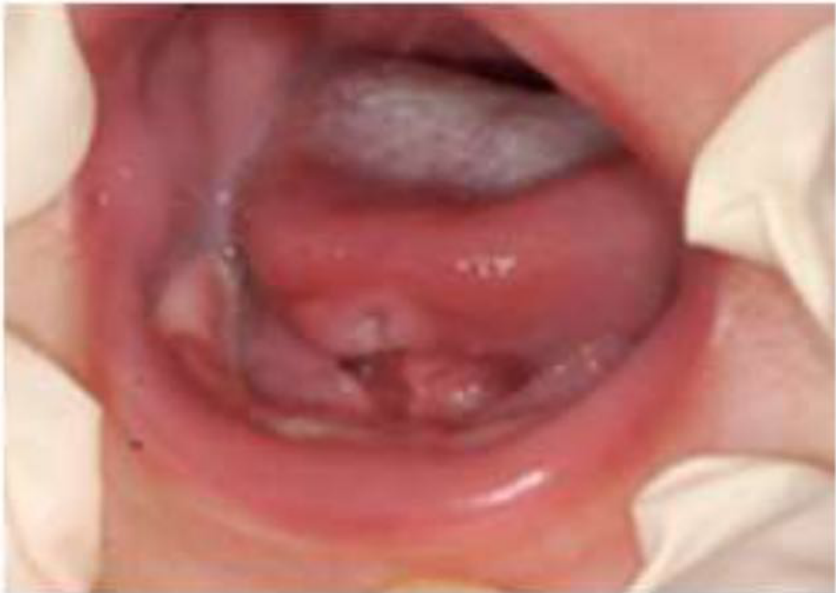 |
Coverage Options333435
- Place something over the tooth in order to reduce the trauma to the tongue and nipple
- Options are:
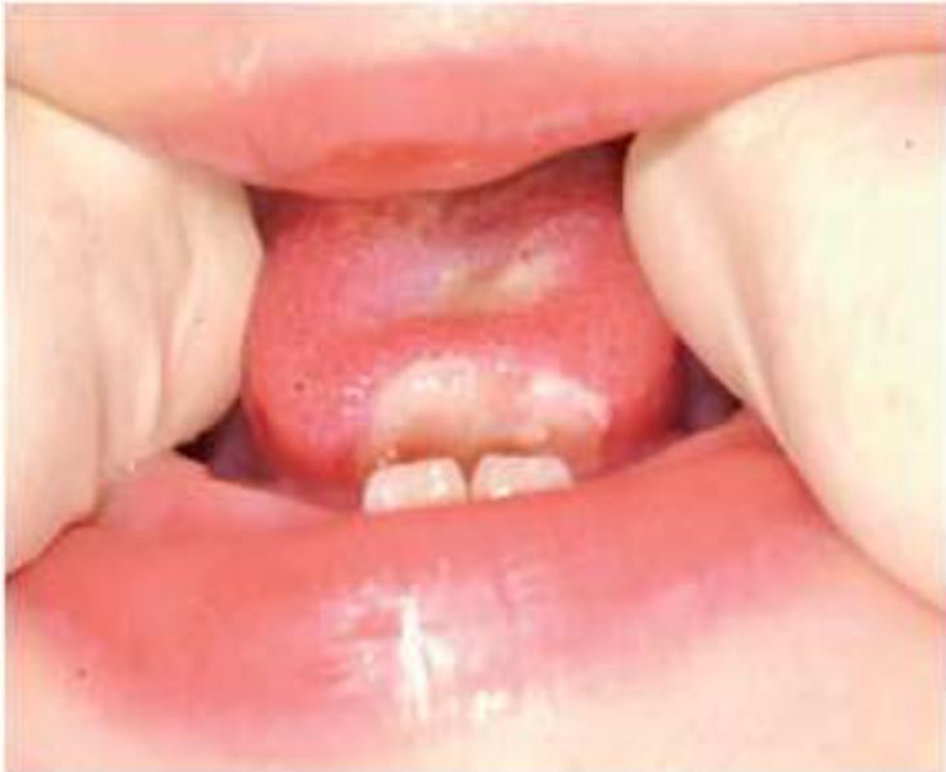
- A smooth rounded composite dome restoration (Goho, 1996; Choi et al. 2009)
- A breast feeding splint (Bjuggren, 1973)
- Stomahesive wafers (Buchannan & Jenkins, 1997)
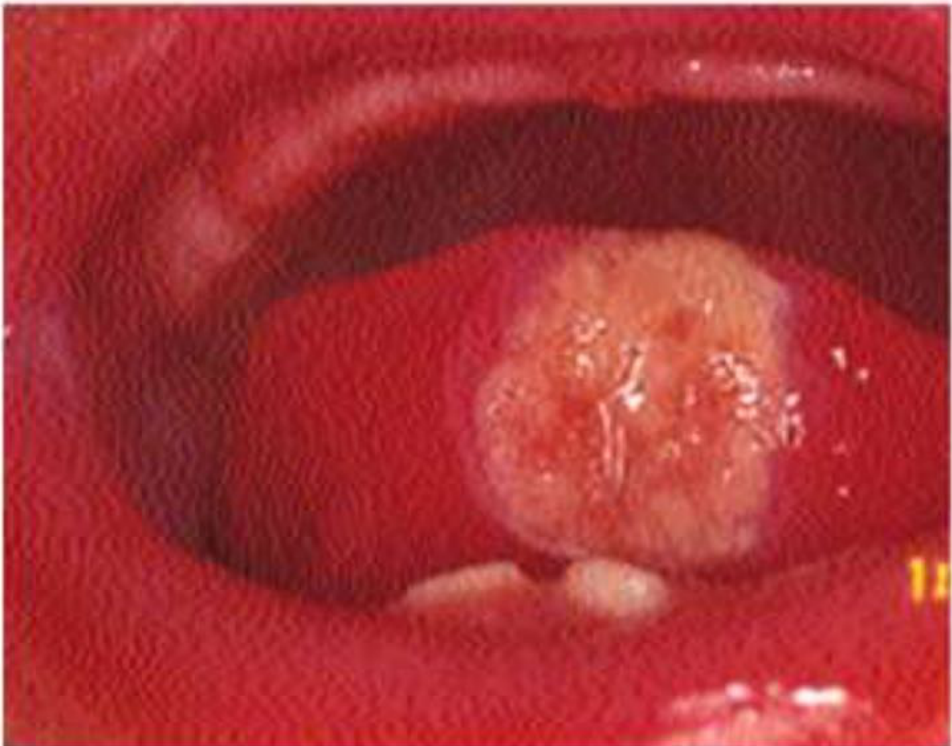
Composite build-up.
(Choi et al 2009)
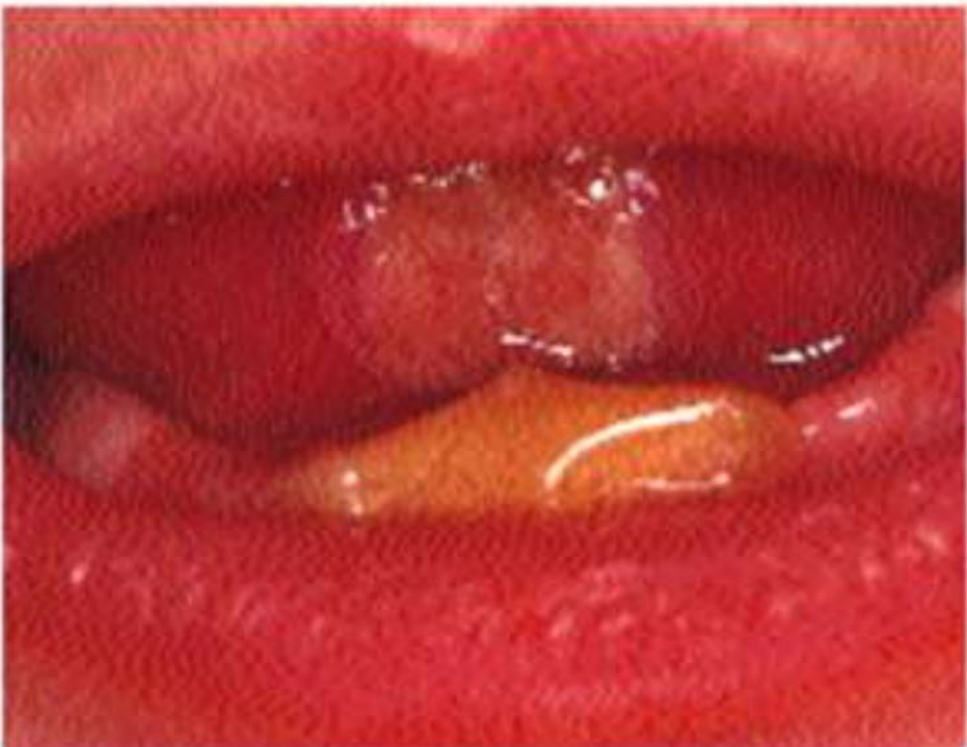
Stomahesive wafer.
(Buchanan and Jenkins, 1997)
 |  |
 |  |
Extraction - Indications3637
- Extraction is not contraindicated for any other clinical reasons (Mhaske et al. 2013)
- If the tooth is confirmed supernumerary through radiographs (Mhaske et al. 2013)
- Excessive mobility: risk of spontaneous exfoliation and consequent aspiration (Allwright, 1958; Kates et al. 1984)
- The tooth is unsuitable to retain due to severe dysplasia (Coho, 1996)
- The tooth developed an abscess or pulpal hyperplasia (Coho, 1996)
- Tooth interfering with the pre-surgical orthopaedic or surgical phase of oral cleft management (Ziai et al. 2005)
- Severe sublingual ulceration which is seriously interfering with feeding and the child is severely malnourished or dehydrated (Allwright, 1958; Slayton, 2000; Choi et al. 2009)
Natal Tooth Cases
Two cases illustrated why extraction should be reserved for carefully selected situations.
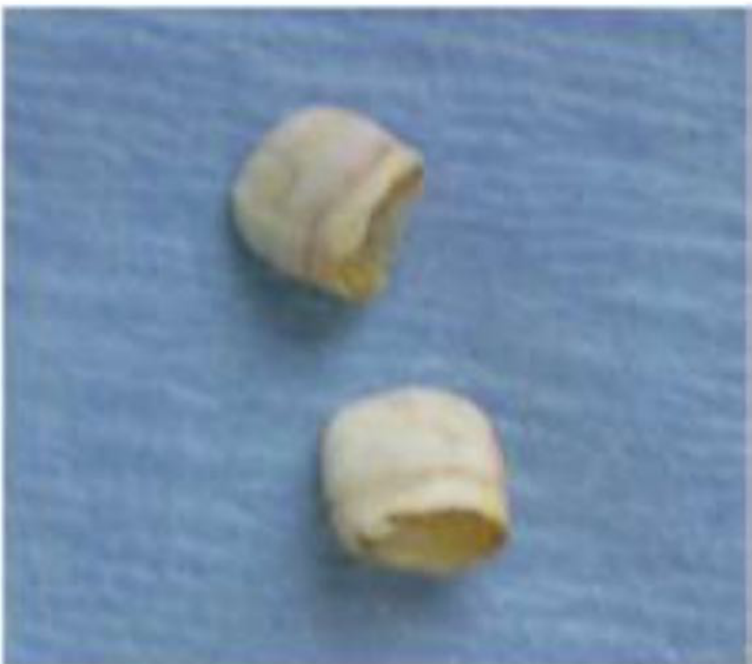
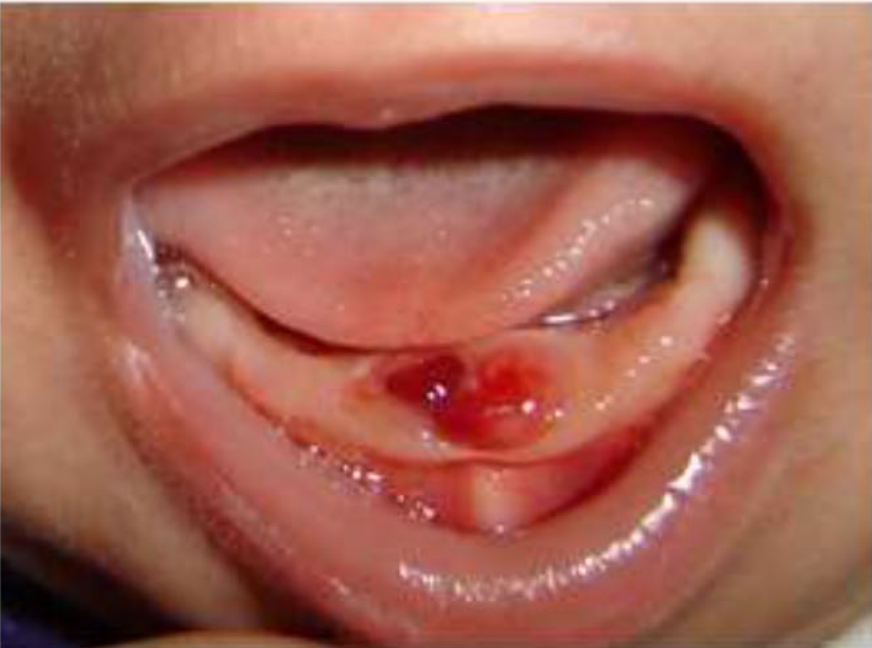
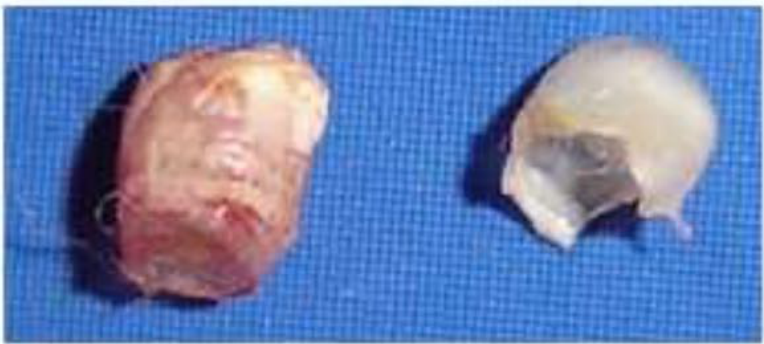
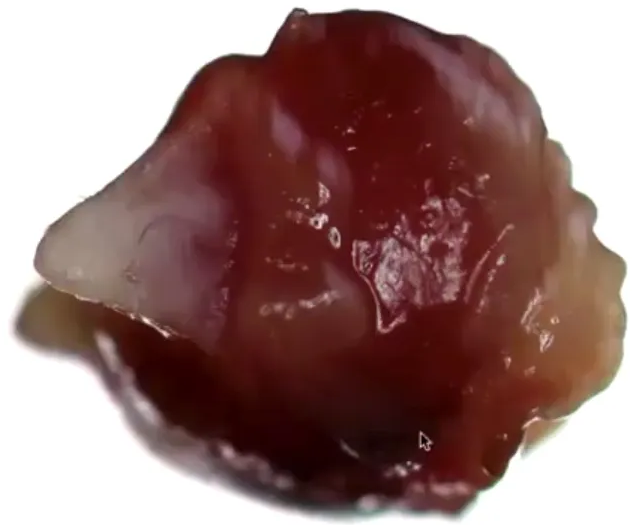
- A healthy infant had a highly mobile tooth attached by a small amount of tissue. Vitamin K status was checked, haemostasis was achieved, and the specimen included the tooth and follicular tissue. Examination showed yellow enamel, qualitative and quantitative enamel defects, and a groove extending through the entire tooth; full lip retraction was needed to identify the defect.
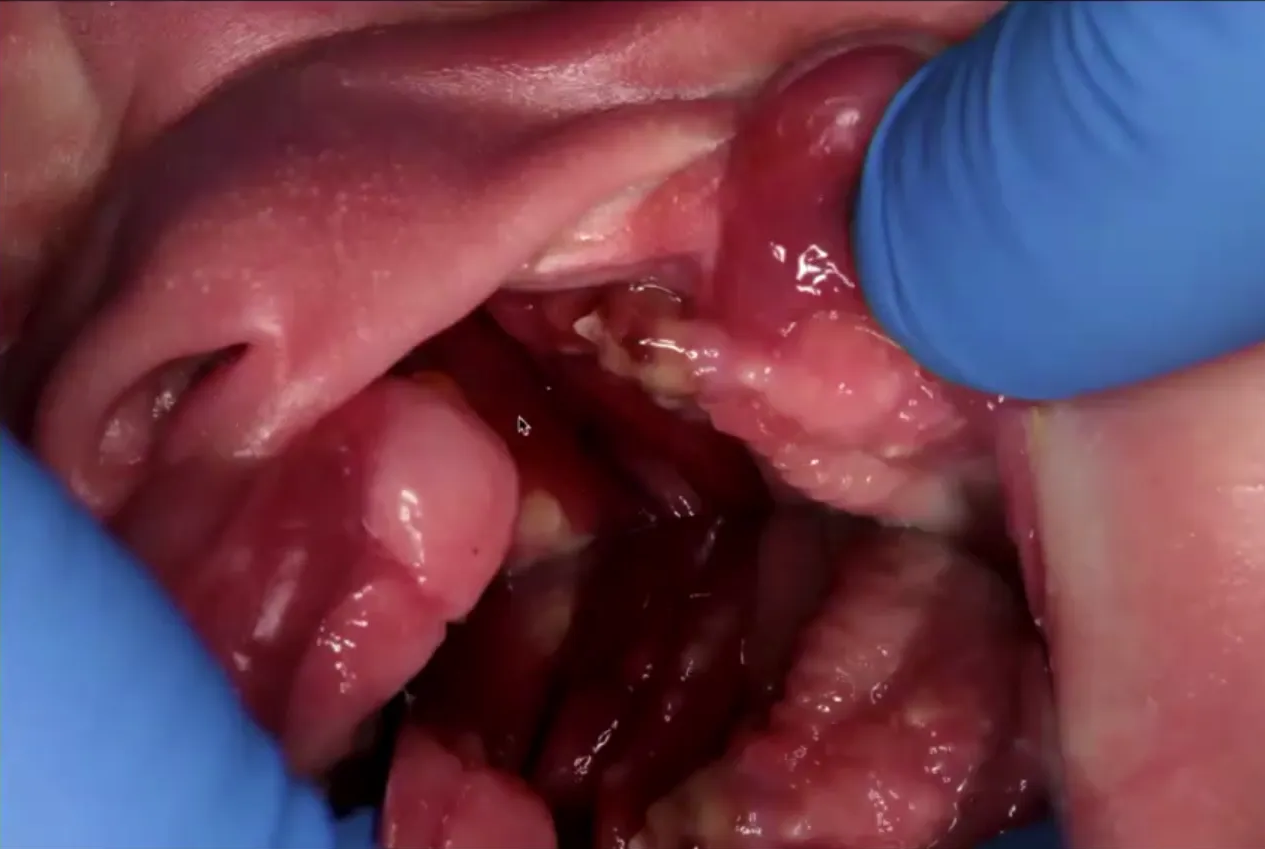
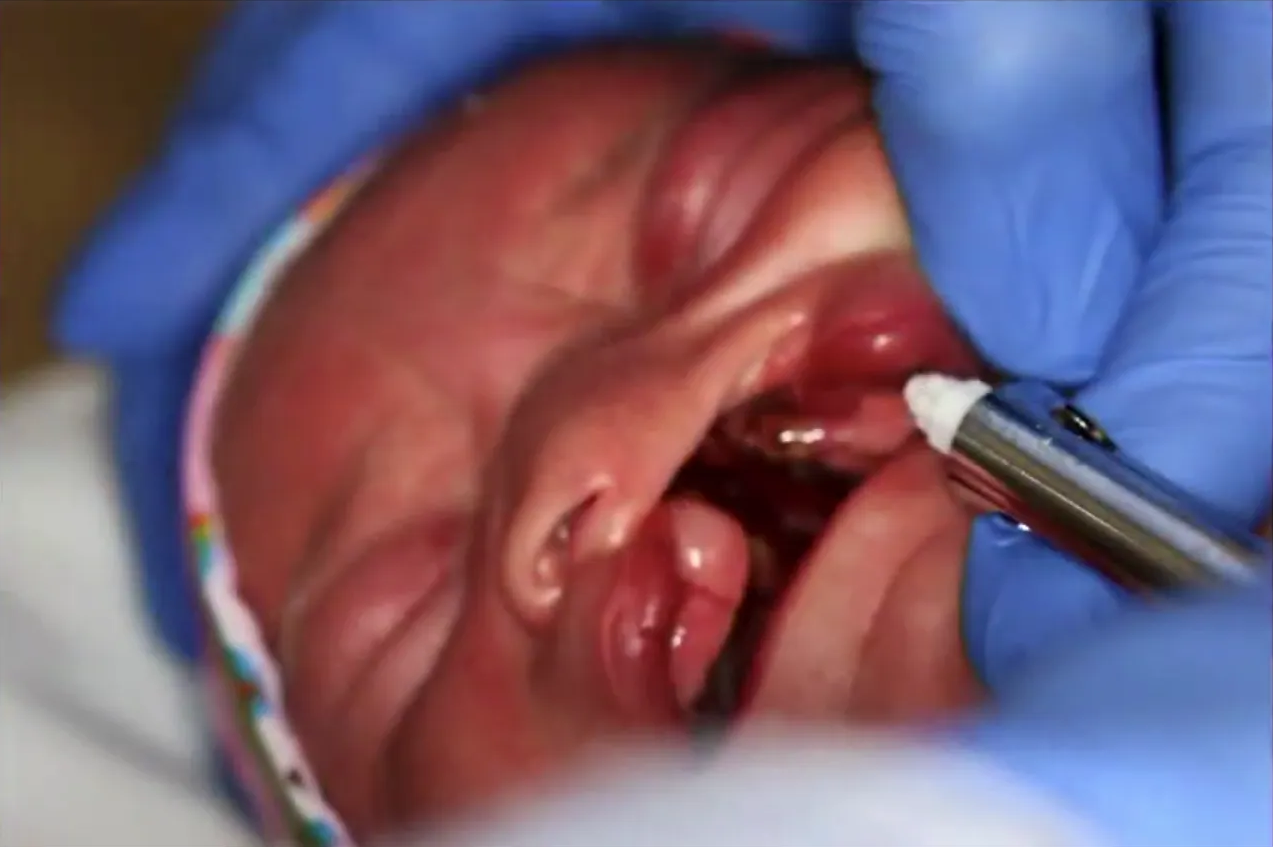
- A child with unilateral cleft lip and palate had a natal tooth in the cleft region, a feeding ulcer, and required removal in a controlled clinical setting. Local anaesthetic was delivered with a LignaJet, which provides approximately 0.2 mL per click; in a two- to three-kilogram infant, this helps control the potentially toxic lignocaine dose. In a cleft, the tooth could move into the nasal cavity, so the procedure was not generally appropriate for routine dental practice.
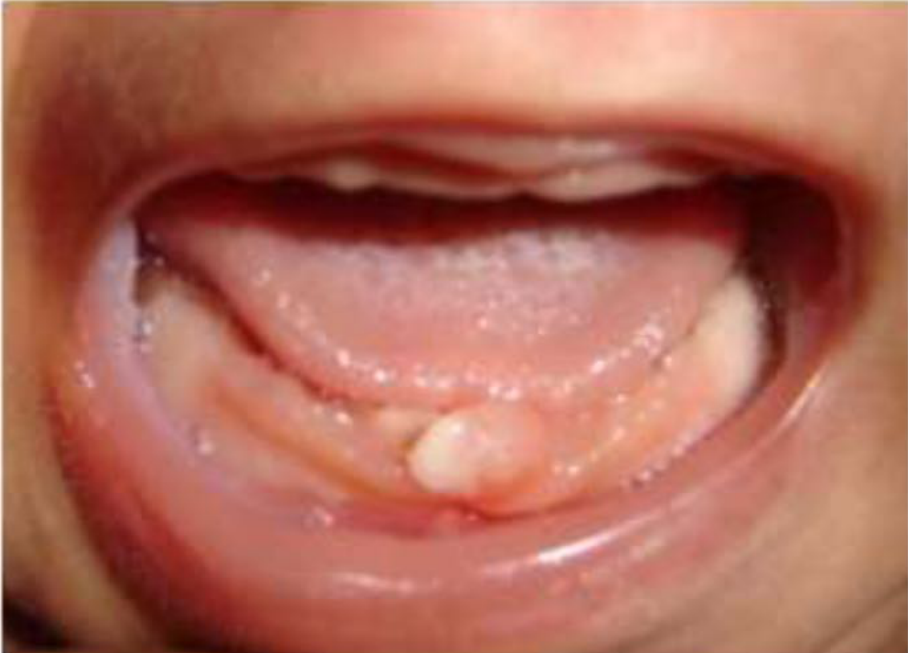
13-day-old female infant with neonatal teeth.
(Khandelwal et al. 2013)
 |  |
 |
Extraction - Precautions38
If the treatment option is extraction only, certain precautions should be taken:
- Considering the general health condition of the infant prior to extraction
- Avoiding extraction up to the 10th day of life to prevent hemorrhage
- Assessing the need to administer vitamin K before extraction (0.5–1.0 mg IM)
- Avoiding unnecessary injury to the gingiva
- Socket should be curetted following extraction to prevent continued development of the cells of the dental papilla (Leung & Robson 2006, Zhu & King 1996)
- Being alert to the risk of aspiration during removal
Lecturer — Neonatal Extraction Setting
Extraction should generally be performed in an appropriate hospital or specialist setting rather than routine general dental practice when the clinician lacks neonatal experience.
- The clinician must account for the infant’s low body weight, the small tooth, difficulty gripping it securely, bleeding and haemostasis, and the risk of slipping, aspiration, or displacement into the nasal cavity.
- The maximum safe dose of local anaesthetic must be calculated, and vitamin K administration confirmed. An intraligamentary technique such as the LignaJet may help control the volume delivered.
Extraction - Complications39
- Potential increased risk of space loss following extraction
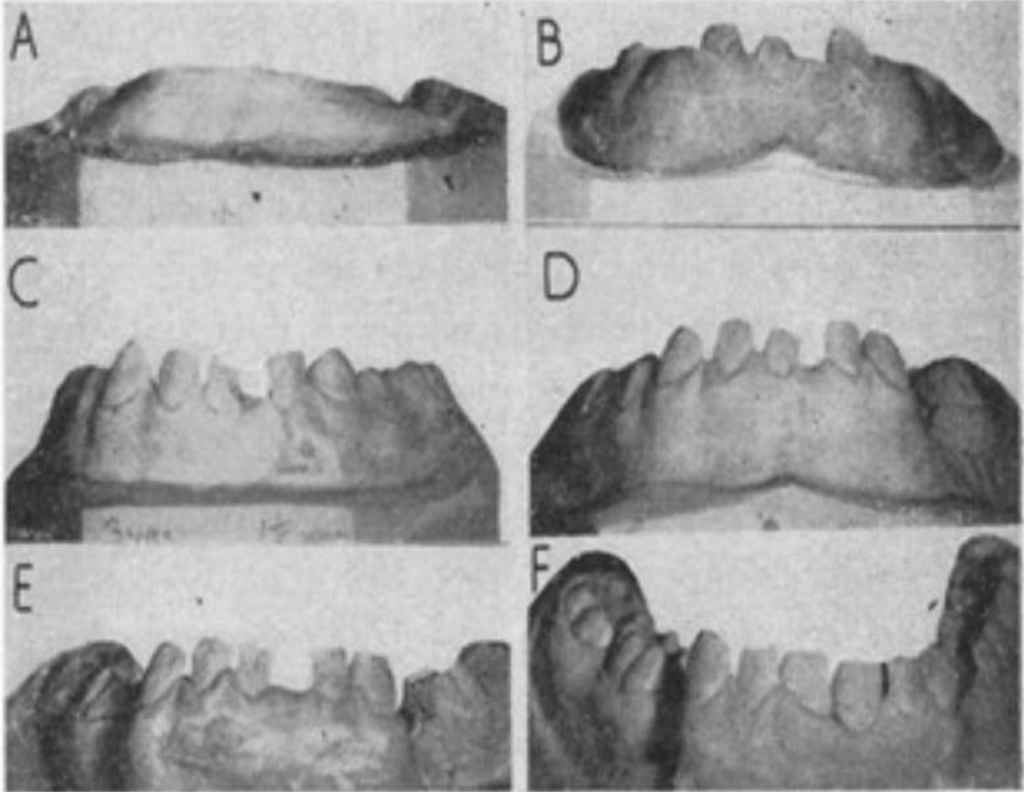
Gardiner, 1961 reported 9 cases with space loss following extraction of natal teeth, however the space was regained when the permanent teeth erupted.
Lecturer — Post Extraction Space
In the anterior region, some space lost after extraction may be regained when the permanent teeth erupt, so a space maintainer is generally not required after extraction of an anterior tooth.
- Extraction of a primary molar, such as a D or E, is more likely to result in space loss and requires greater consideration of space management.
Fig 2: Models showing the closing of incisal space (measured between B̄ and |B̄) following the loss of |Ā and also the opening of this space at 5 years. A, aged 4 months – 0 mm; B, aged 1½ years – 9 mm; C, aged 3 years – 7 mm; D, aged 5¼ years – 7.5 mm; E, aged 6½ years – 8 mm; F, aged 7½ years – 12 mm.
(Gardiner, 1961)
Clinical Cases
Case: Natal tooth in a preterm newborn, intraoral and radiographic views
Question
Scenario: A case report of a preterm newborn who presents with a tooth erupted in the oral cavity at birth.
What’s shown: Intraoral clinical photograph and a radiograph of the infant’s mouth.
Consider: Identify the erupted tooth, determine whether it is a primary or supernumerary tooth, and assess the development of adjacent and underlying teeth.

Answer
Observations:
- A tooth is visibly erupted in the anterior mandible intraorally.
- Radiographically, the erupted tooth corresponds to the primary mandibular right central incisor (71).
- The underlying permanent successors (31 and 41) are visible on the radiograph.
- The adjacent primary mandibular left central incisor (81) is also close to erupting in the area.
Reasoning: The radiograph confirms that the erupted natal tooth is the normal primary central incisor (71) rather than a supernumerary tooth, as evidenced by the presence of the underlying permanent tooth germs and the normal development of the adjacent primary tooth (81).
Takeaway: The vast majority (95%) of natal teeth are true primary teeth rather than supernumerary teeth, which can be verified radiographically by identifying the underlying permanent successor.
Case: Tongue ulceration in a 2-month-old girl, before and after grinding
Question
Scenario: A 2-month-old infant presents with a tongue ulcer lesion caused by a neonatal tooth.
What’s shown: Intraoral photographs showing the ulcer lesion before treatment, and the same infant one month after the sharp incisor edge was ground down, with the lesion resolved.
Consider: What treatment is demonstrated in the images, and what are the clinical considerations and risks associated with performing this procedure on a neonate?
Answer
Observations:
- The initial photograph shows a tongue ulcer lesion caused by a neonatal tooth.
- The follow-up photograph, taken one month later, shows the lesion has resolved after the sharp incisor edge was ground down.
Reasoning:
- Grinding down the sharp edges of the tooth can resolve the trauma and subsequent ulceration.
- However, performing this procedure on a neonate is considered risky (“dodgy”) because of the high chance of accidentally slicing the tongue or lip.
- Because of these risks, the lecturer advises against attempting this in a general practice setting and recommends referring such cases to a pediatric dentist or specialist in a metro setting.
Outcome:
- The tongue ulcer lesion resolved one month after the sharp incisor edge was ground down.
Takeaway:
- While grinding down sharp neonatal teeth can resolve associated tongue ulceration, the procedure carries a high risk of soft tissue injury in neonates and should ideally be referred to a specialist.
Case: Infant with unilateral cleft lip and palate and a natal tooth
Question
Scenario: An infant with a unilateral cleft lip and palate presents with a natal tooth and a feeding ulcer on the tongue.
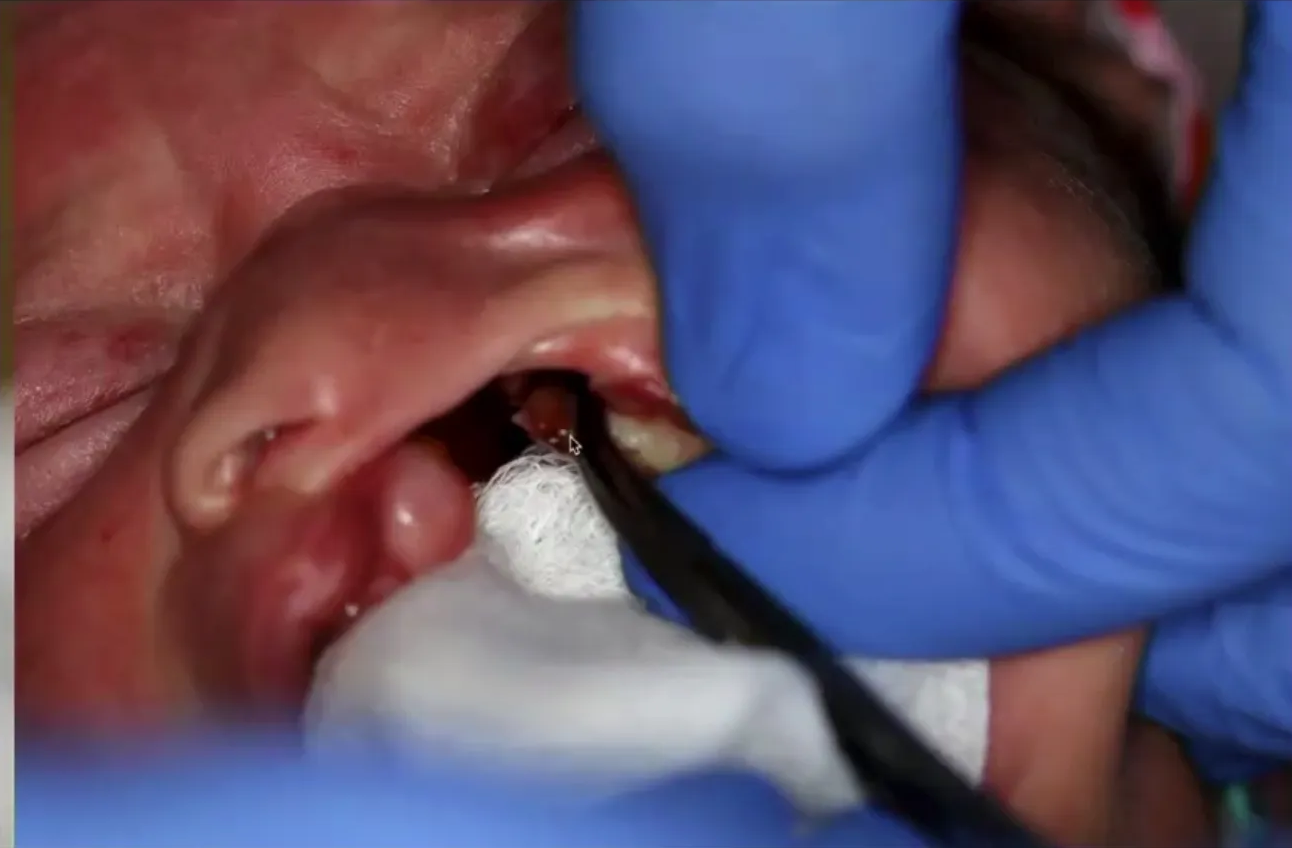
What’s shown: Clinical photographs showing the natal tooth, the cleft, the vomer, the feeding ulcer on the tongue, the administration of local anesthetic, and the post-extraction site.
Consider: How to manage the extraction of a natal tooth in a patient with a cleft lip and palate, including anesthetic considerations and surgical precautions.
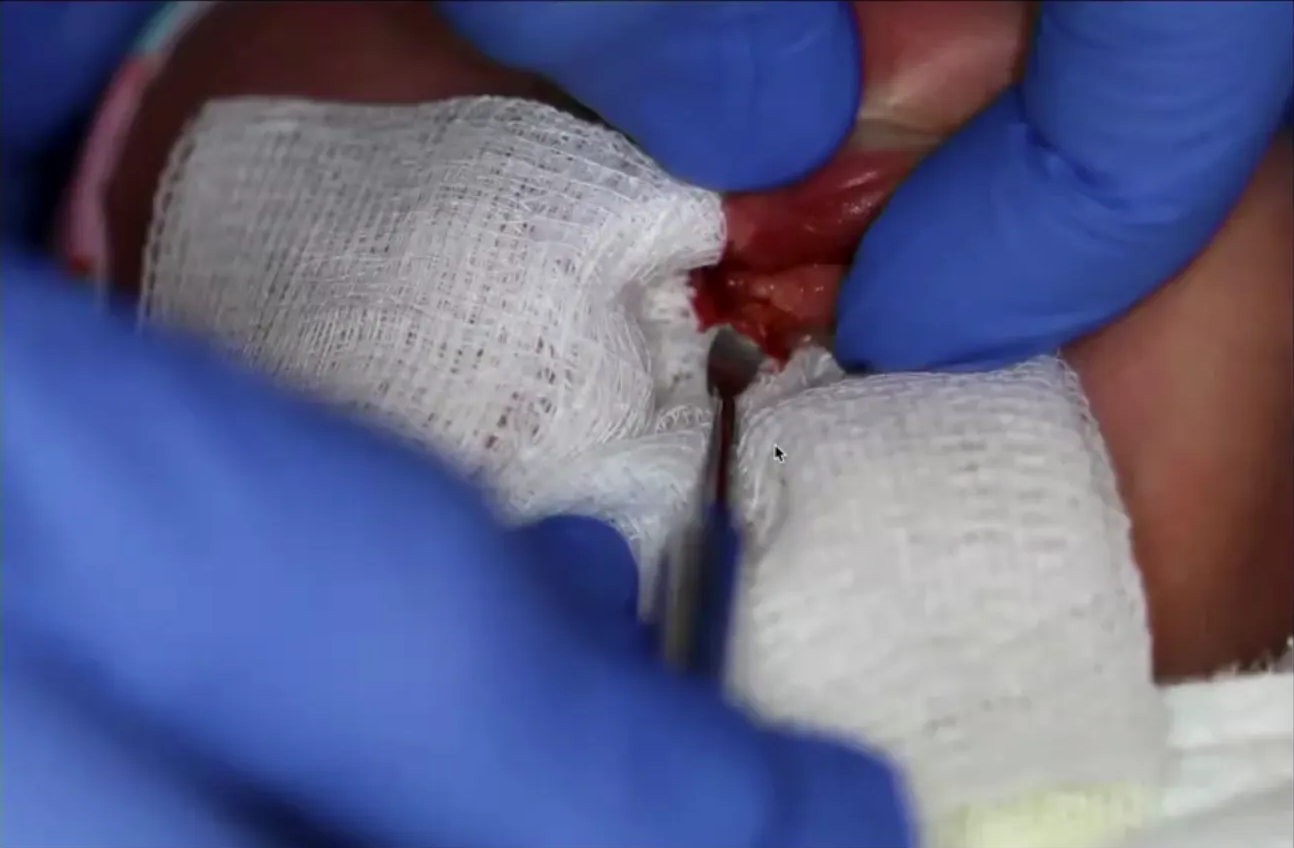
Answer
Observations:
- The infant has a unilateral cleft lip and palate with a natal tooth and a feeding ulcer on the tongue.
- Local anesthetic was administered using an intraligamentary syringe (ligna jet) delivering 0.2 ml per click to avoid toxicity.
- The tissues were blanched from the local anesthetic prior to extraction.
Reasoning: Extraction in a cleft lip and palate patient carries risks, such as the tooth or instruments entering the nasal cavity. It is crucial to curette the socket to remove the epithelial root sheath and dental papilla cells; otherwise, a root could continue to form as the child grows, requiring another extraction later.
Outcome: The tooth was extracted, and the socket was curetted to ensure complete removal of the follicle.
Takeaway: Extracting natal teeth in cleft lip and palate patients requires careful anesthetic dosing and thorough socket curettage to prevent continued root development, and is generally best referred or performed in a hospital setting due to the risks involved.
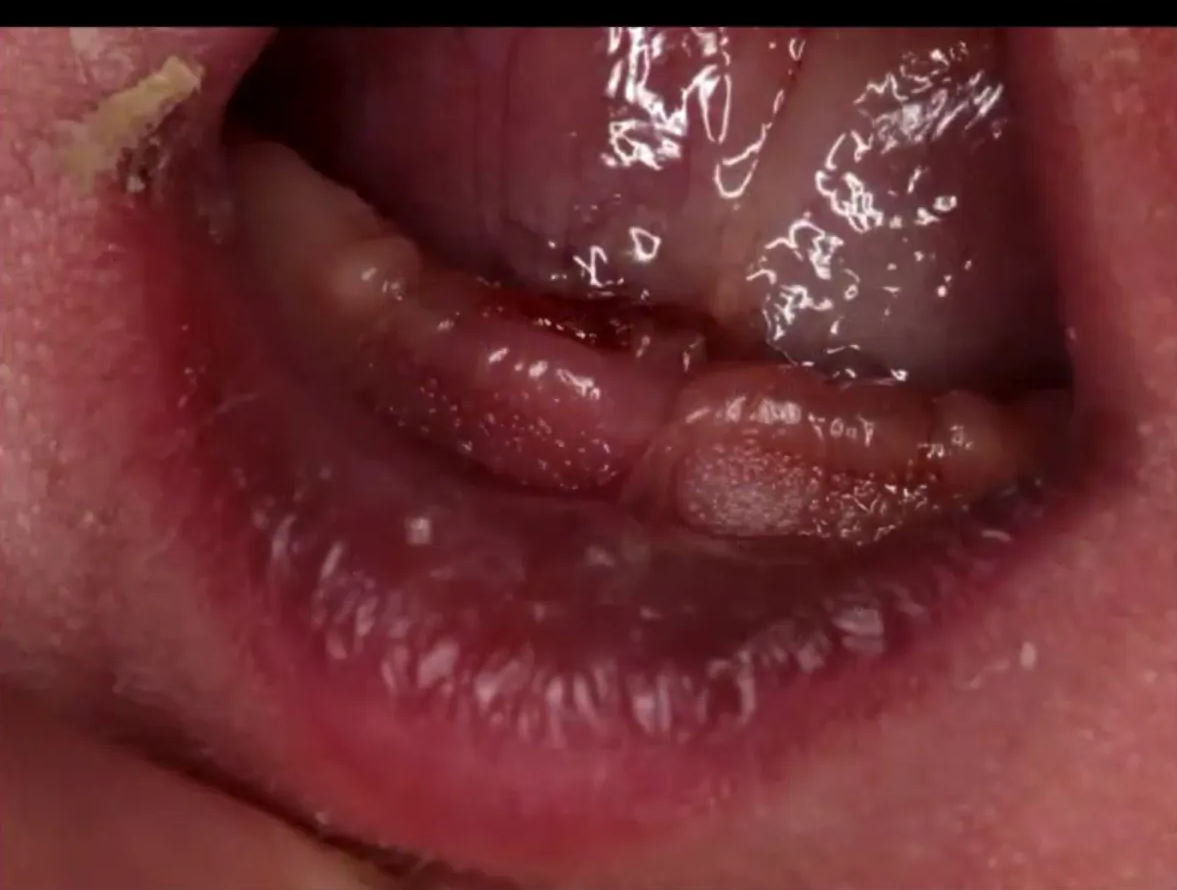
Case: Fit and healthy infant with a highly mobile floating natal tooth
Question
Scenario: A fit and healthy infant without a cleft presents with a highly mobile natal tooth that is floating on tissue.
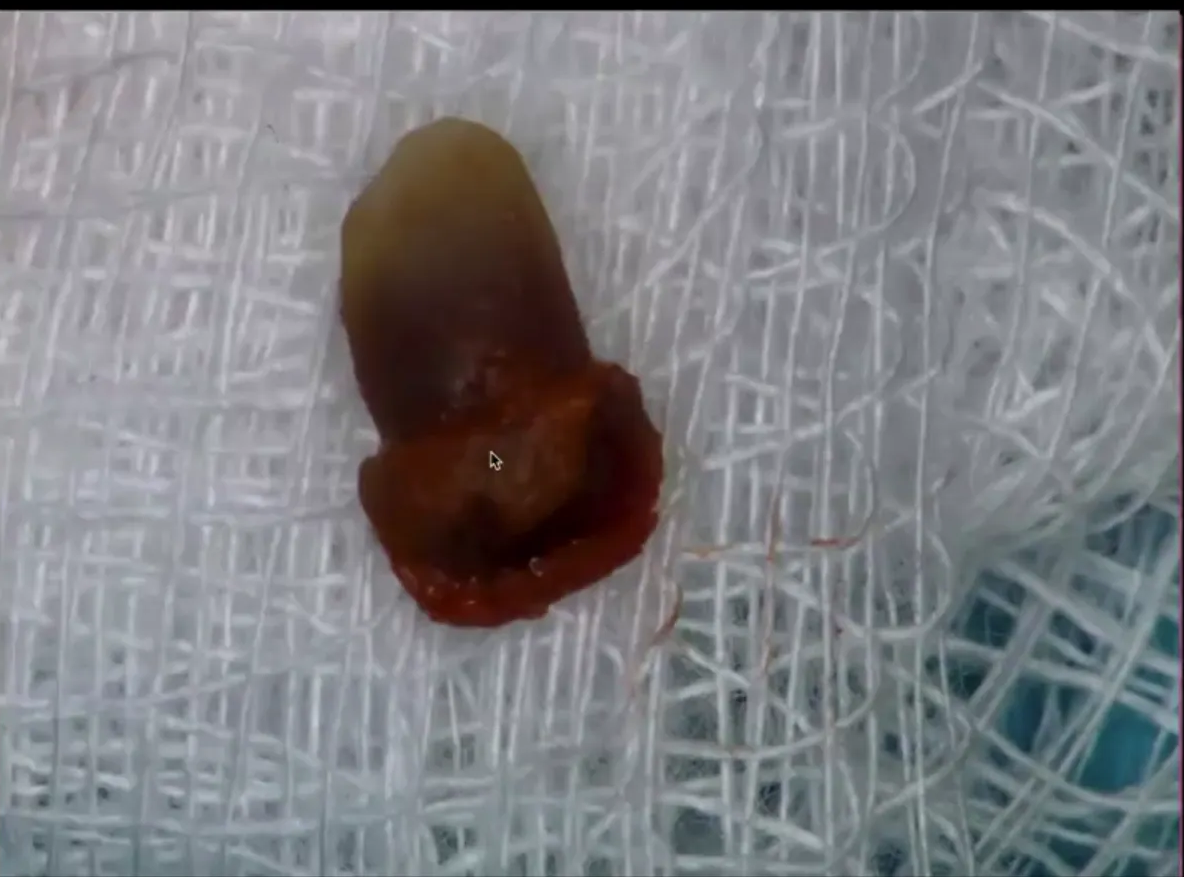
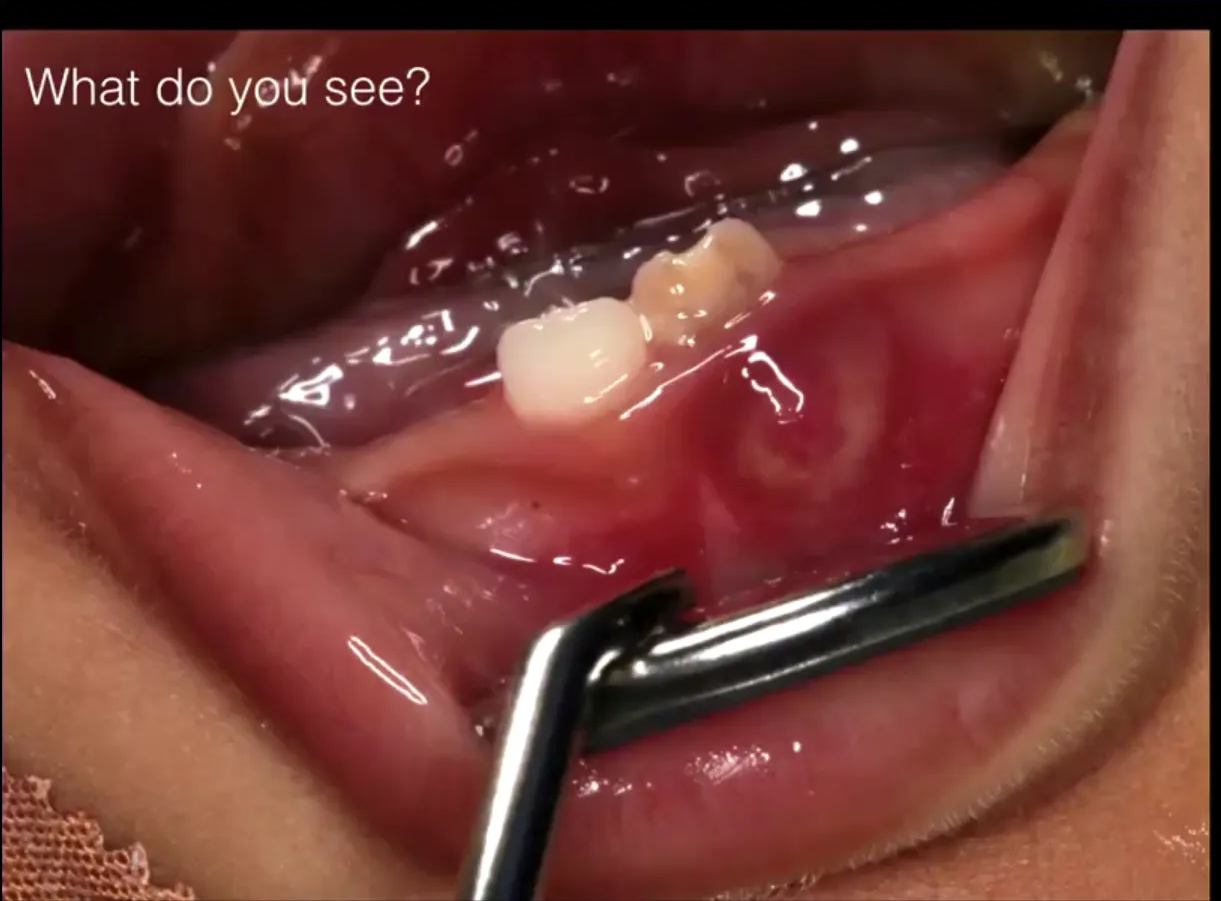
What’s shown: Clinical photographs showing the floating tooth in the alveolus, the post-extraction site with good hemostasis, and the extracted tooth and follicle.
Consider: How to assess and manage a highly mobile, floating natal tooth in a healthy infant, and what hidden defects might be present.
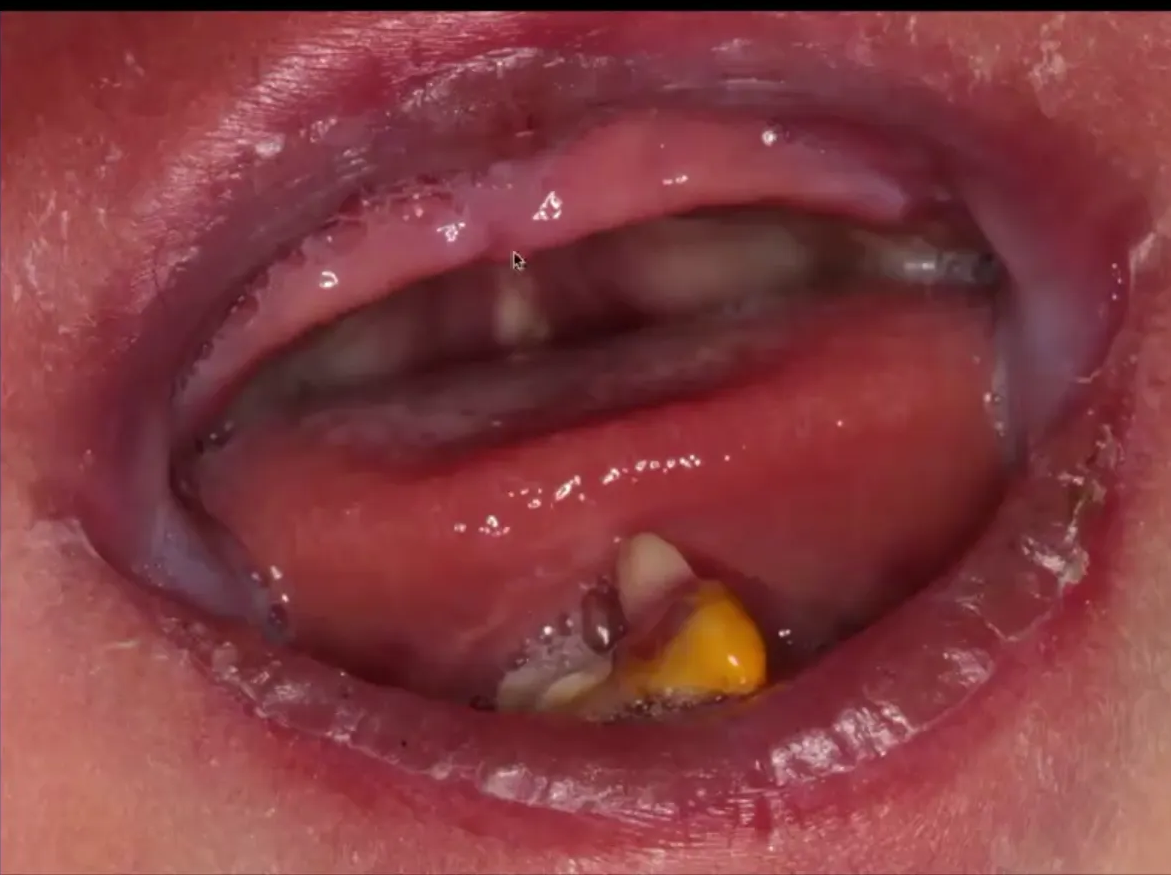
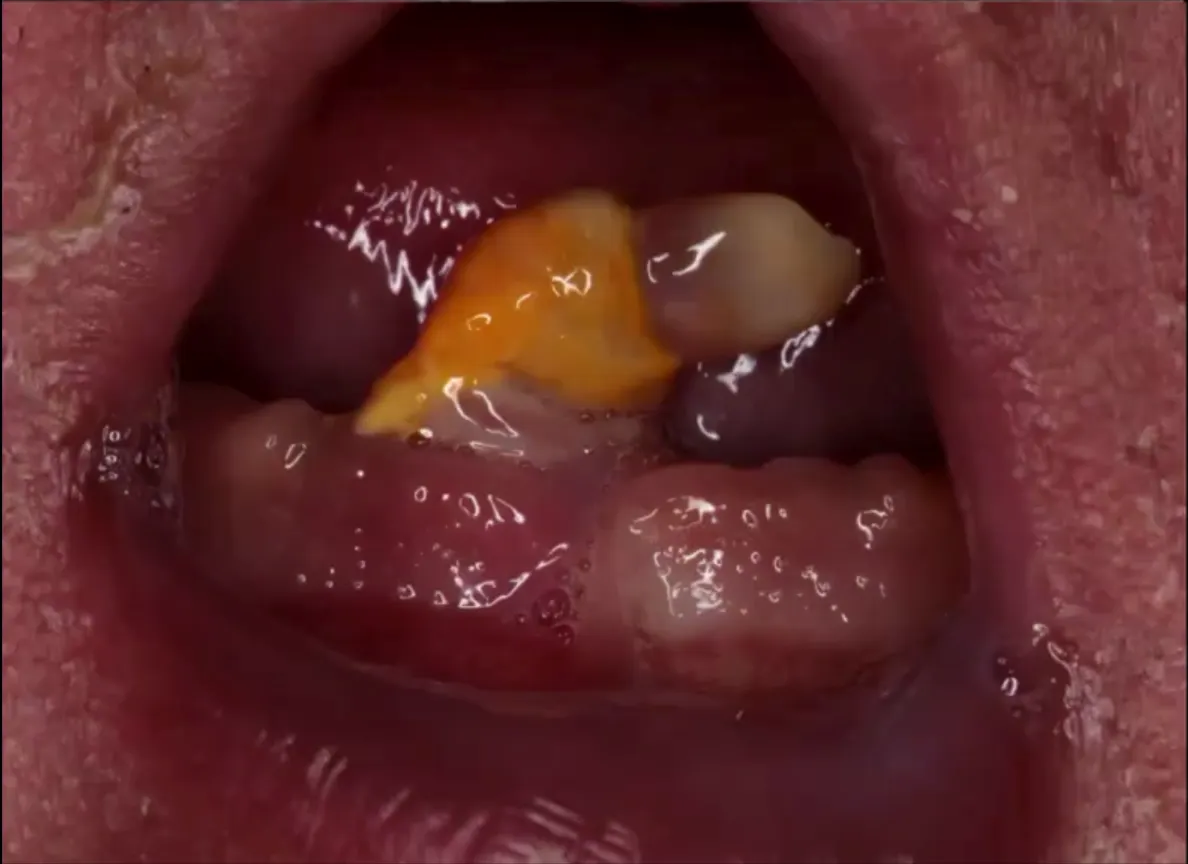
Answer
Observations:
- The tooth is extremely mobile, floating on its follicle without bony support.
- The extracted tooth shows qualitative (yellow) and quantitative enamel defects, with some breakdown.
- An abscess was present, which was only visible when the lip was fully lifted and examined closely in a knee-to-knee position.
- Upon extraction, a defect was revealed on the lingual surface: a groove running straight through the whole tooth.
Reasoning: A tooth floating on tissue will not firm up and poses a risk, necessitating extraction. Close examination, including lifting the lip, is essential to identify hidden abscesses or defects that might be missed otherwise. The presence of enamel defects and an abscess indicates severe dysplasia, which is an indication for extraction.
Outcome: The tooth and the whole follicle were extracted. Good hemostasis was achieved, and the child’s vitamin K injection status was verified.
Takeaway: Highly mobile natal teeth floating on tissue require extraction. Thorough clinical examination, including lifting the lip, is necessary to identify hidden abscesses or structural defects like grooves running through the tooth.
Footnotes
-
Original PDF page 1: L1 Natal Teeth 2020, p.1 ↩
-
Original PDF page 2: L1 Natal Teeth 2020, p.2 ↩
-
Original PDF page 3: L1 Natal Teeth 2020, p.3 ↩
-
Original PDF page 4: L1 Natal Teeth 2020, p.4 ↩
-
Original PDF page 6: L1 Natal Teeth 2020, p.6 ↩
-
Original PDF page 5: L1 Natal Teeth 2020, p.5 ↩
-
Original PDF page 7: L1 Natal Teeth 2020, p.7 ↩
-
Original PDF page 8: L1 Natal Teeth 2020, p.8 ↩
-
Original PDF page 9: L1 Natal Teeth 2020, p.9 ↩
-
Original PDF page 10: L1 Natal Teeth 2020, p.10 ↩
-
Original PDF page 11: L1 Natal Teeth 2020, p.11 ↩
-
Original PDF page 12: L1 Natal Teeth 2020, p.12 ↩
-
Original PDF page 13: L1 Natal Teeth 2020, p.13 ↩
-
Original PDF page 14: L1 Natal Teeth 2020, p.14 ↩
-
Original PDF page 15: L1 Natal Teeth 2020, p.15 ↩
-
Original PDF page 16: L1 Natal Teeth 2020, p.16 ↩
-
Original PDF page 17: L1 Natal Teeth 2020, p.17 ↩
-
Original PDF page 18: L1 Natal Teeth 2020, p.18 ↩
-
Original PDF page 19: L1 Natal Teeth 2020, p.19 ↩
-
Original PDF page 20: L1 Natal Teeth 2020, p.20 ↩
-
Original PDF page 21: L1 Natal Teeth 2020, p.21 ↩
-
Original PDF page 22: L1 Natal Teeth 2020, p.22 ↩
-
Original PDF page 23: L1 Natal Teeth 2020, p.23 ↩
-
Original PDF page 24: L1 Natal Teeth 2020, p.24 ↩
-
Original PDF page 25: L1 Natal Teeth 2020, p.25 ↩
-
Original PDF page 26: L1 Natal Teeth 2020, p.26 ↩
-
Original PDF page 27: L1 Natal Teeth 2020, p.27 ↩
-
Original PDF page 28: L1 Natal Teeth 2020, p.28 ↩
-
Original PDF page 29: L1 Natal Teeth 2020, p.29 ↩
-
Original PDF page 30: L1 Natal Teeth 2020, p.30 ↩
-
Original PDF page 31: L1 Natal Teeth 2020, p.31 ↩
-
Original PDF page 32: L1 Natal Teeth 2020, p.32 ↩
-
Original PDF page 33: L1 Natal Teeth 2020, p.33 ↩
-
Original PDF page 34: L1 Natal Teeth 2020, p.34 ↩
-
Original PDF page 35: L1 Natal Teeth 2020, p.35 ↩
-
Original PDF page 36: L1 Natal Teeth 2020, p.36 ↩
-
Original PDF page 37: L1 Natal Teeth 2020, p.37 ↩
-
Original PDF page 38: L1 Natal Teeth 2020, p.38 ↩
-
Original PDF page 39: L1 Natal Teeth 2020, p.39 ↩