Cardiovascular Disease and Dentistry1
Dr Jee-Yun Leung
Learning Outcomes
Part 12
- Review common vascular, valvular, electrical, muscular and congenital cardiac conditions and their management (e.g. hypertension, coronary artery disease, rheumatic heart disease, infective endocarditis, arrhythmias, congenital structural defects, heart failure)
- Describe potential oral findings associated with cardiac conditions
- Describe the oral manifestations and manage the risks associated with common treatments used to manage cardiac conditions
- Assess the associated risks of common dental procedures and modify dental treatment appropriately to safely provide care
Lecturer — Cardiovascular Assessment
Cardiovascular conditions should be considered through their definitions and aetiology, general manifestations, and general medical management.
- Consider the oral manifestations of these conditions.
- Include dental management and associated treatment risks.
Part 2
- Work a patient up prior to cardiac surgery
- Manage angina or an acute coronary syndrome in dental practice
Lecturer — Practical Dental Framework
Apply a practical framework to patients with cardiovascular disease in dental practice.
- Consider risk assessment and access to appropriate dental care.
- Consider the timing and setting of treatment, capacity and consent, and education and prevention.
- Plan pre-operative, peri-operative and post-operative care.
- Assess patients before cardiac surgery, including the balance between the risks and benefits of pre-operative dental treatment.
Overview of Common Cardiac Conditions3
- Hypertension
- Coronary Artery Disease
- Rheumatic Heart Disease
- Infective Endocarditis
- Arrhythmias
- Congenital Structural Defects
- Heart Failure
WHO International Classification of Diseases4
- 11 Diseases of the circulatory system
- Hypertensive diseases
- Hypotension
- Ischaemic heart diseases
- Diseases of coronary artery
- Pulmonary heart disease or diseases of pulmonary circulation
- Pericarditis
- Acute or subacute endocarditis
- Heart valve diseases
- BC20 Chronic rheumatic heart diseases, not elsewhere classified
- Diseases of the myocardium or cardiac chambers
- Cardiac arrhythmia
- Heart failure
- Diseases of arteries or arterioles
- Diseases of veins
- Disorders of lymphatic vessels or lymph nodes
- Postprocedural disorders of circulatory system
- Neoplasms of the circulatory system
- Developmental anomalies of the circulatory system
- Infections of the circulatory system
- Symptoms, signs or clinical findings of the circulatory system
- Cerebrovascular diseases
- Functional vascular disorders of the skin
- JB64.4 Diseases of the circulatory system complicating pregnancy, childbirth or the puerperium
- BE2Y Other specified diseases of the circulatory system
- BE2Z Diseases of the circulatory system, unspecified
Lecturer — WHO Classification
The WHO International Classification of Diseases provides a classification system for a broad range of diseases.
- It is revised every 10 years to maintain its currency and utility.
- The classification helps different countries and health professionals use a common language when discussing diseases.
Types of Cardiac Conditions
Vascular / Ischaemic5
- Hypertension
- Hypotension
- Ischaemic heart disease (Coronary artery disease) – angina, myocardiac infarction
- Thromboembolic complications of CVD
Valvular
- Rheumatic fever and Rheumatic heart disease
- Infective endocarditis
- Aortic and mitral valve stenosis, regurgitation and prolapse
Electrical (Dysrhythmias)
- Extrasystoles (ectopics)
- Tachycardia (including Atrial fibrillation)
- Bradycardias
Muscular (Cardiomyopathies)
- Primary – genetic/inherited, acquired
- Secondary
Congenital
- Cyanotic
- Acyanotic
Heart Failure
Lecturer — Heart Failure
Heart failure may result from the progression or complication of other cardiovascular conditions. It involves impairment of the heart’s ability to pump blood sufficiently to meet the body’s demands.
Vascular and Ischaemic Conditions6
- Hypotension
- Hypertension
- Ischaemic heart disease (Coronary artery disease) – angina, myocardial infarction
- Thromboembolic complications of CVD
Hypotension
Hypotension Definitions7
- Hypotension (chronic arterial hypotension) = systolic BP <100 mmHg
- Pre-syncope (“near-fainting”) = condition in which a patient feels syncope is imminent
- Syncope (“fainting”) = acute fall in blood pressure, resulting in transient global cerebral hypoperfusion, causing a loss of consciousness which usually leads to loss of postural tone and falling
- Vasovagal syncope = reaction to pain, or to anxiety and fear before, during or after a dental procedure
- Orthostatic hypotension = fall in blood pressure when standing up after sitting or lying down for an extended period of time in the dental chair
Orthostatic Hypotension Aetiology8
- Cardiac conditions: ability for heart to pump blood (e.g. abnormal heart rhythm, heart failure, MI)
- Autonomic nervous system: involved in returning BP to normal (e.g. Parkinson’s disease)
- Long-term bed rest (e.g. hospitalised, pregnancy)
- Low blood volume (e.g. dehydration, anaemia, injury)
- Medications (e.g. antihypertensives, antidepressants)
Lecturer — Orthostatic Physiology
Moving from lying flat to standing makes it more difficult for blood in the legs and feet to return to the heart, briefly reducing the blood available for the heart to send to the brain and other organs.
- Carotid sinus and aortic arch receptors normally detect the blood pressure change and increase the force of cardiac contraction.
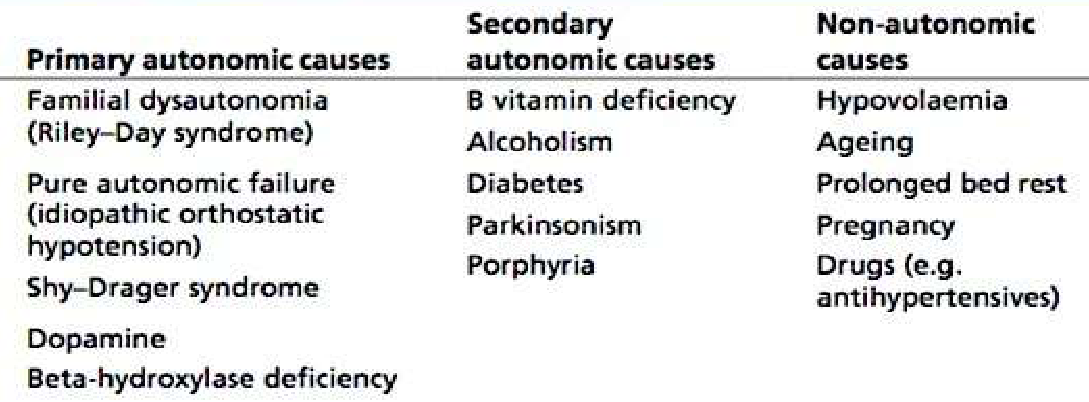
| Primary autonomic causes | Secondary autonomic causes | Non-autonomic causes |
|---|---|---|
| Familial dysautonomia (Riley–Day syndrome) | B vitamin deficiency | Hypovolaemia |
| Pure autonomic failure (idiopathic orthostatic hypotension) | Alcoholism | Ageing |
| Shy–Drager syndrome | Diabetes | Prolonged bed rest |
| Dopamine Beta-hydroxylase deficiency | Parkinsonism | Pregnancy |
| Porphyria | Drugs (e.g. antihypertensives) |
Scully C. Scully’s medical problems in dentistry. 7th ed. Edinburgh: Churchill Livingstone/Elsevier; 2014
Orthostatic Hypotension General Manifestations9
- Early symptoms: vertigo, dizziness, visual blurring, headache, syncope
- Later: tachycardia, paleness, cold extremities, sweating
Hypotension General Management
Syncope – patient with sudden loss of consciousness and tone10
-
falls to floor
-
may have brief twitching or jerking (may appear similar to an epileptic seizure, but much shorter duration)
-
Falls associated with syncope may cause secondary injury, including dental trauma Management: stop dental treatment. If the patient is in the dental chair, tilt it to be horizontal. Provide basic life support.
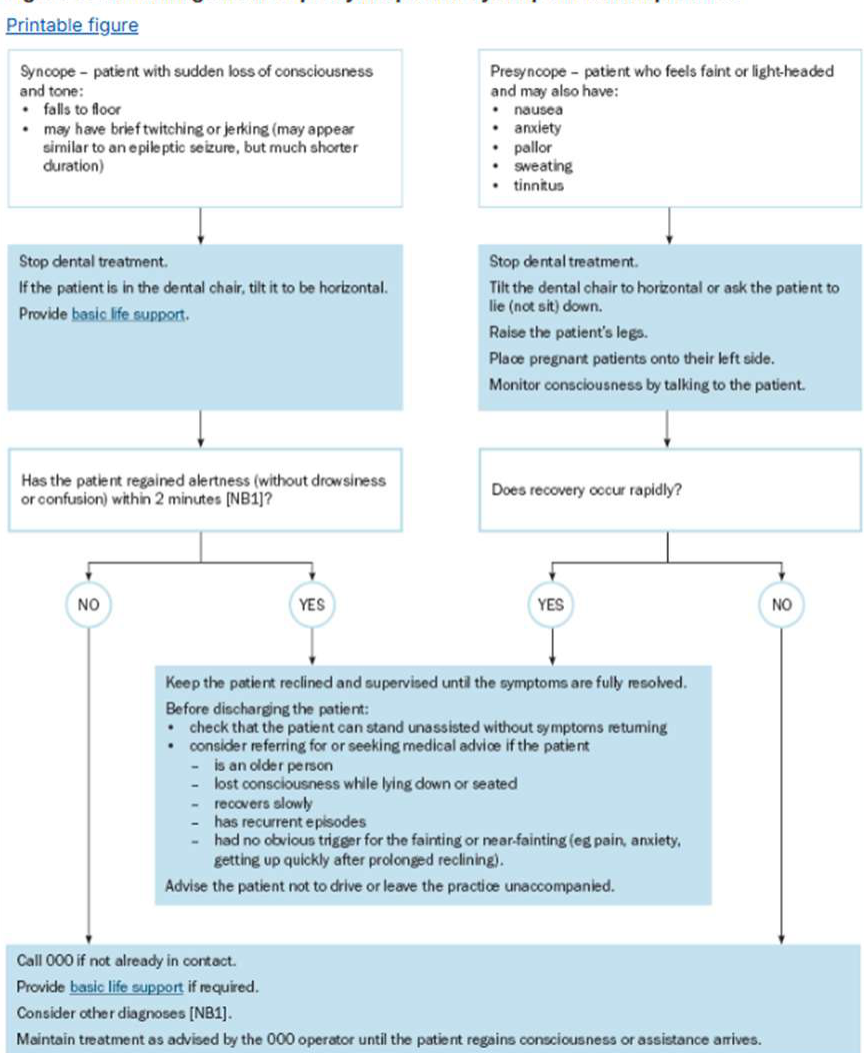
Presyncope – patient who feels faint or light-headed
May also have:
- nausea
- anxiety
- pallor
- sweating
- tinnitus
Management: stop dental treatment. Tilt the dental chair to horizontal or ask the patient to lie (not sit) down. Raise the patient’s legs. Place pregnant patients onto their left side. Monitor consciousness by talking to the patient.
Recovery Pathway
Has the patient regained alertness (without drowsiness or confusion) within 2 minutes [NB1]? Does recovery occur rapidly?
If YES: Keep the patient reclined and supervised until the symptoms are fully resolved. Before discharging the patient:
- check that the patient can stand unassisted without symptoms returning
- consider referring for or seeking medical advice if the patient
- is an older person
- lost consciousness while lying down or seated
- recovers slowly
- has recurrent episodes
- had no obvious trigger for the fainting or near-fainting (eg, pain, anxiety, getting up quickly after prolonged reclining).
- Advise the patient not to drive or leave the practice unaccompanied.
If NO: Call 000 if not already in contact. Provide basic life support if required. Consider other diagnoses [NB1]. Maintain treatment as advised by the 000 operator until the patient regains consciousness or assistance arrives.
Notes
- NB1: Many people with chest pain do not have angina or a heart attack, but anyone with acute chest pain requires rapid medical evaluation for potentially life-threatening causes. The likelihood of angina or heart attack increases with the number of suggestive features.
- NB2: Sublingual glyceryl trinitrate (GTN) dosing is a 400 microgram spray (or 300 to 600 microgram tablet) generally administered every 5 minutes to a maximum of 3 doses. Ask patients who use GTN to bring their GTN to their dental appointment so that it can be administered if chest pain occurs.
- NB3: If symptoms (pain or other features that may indicate angina) last longer than the patient’s usual angina symptoms, urgent medical evaluation of a possible heart attack or other urgent condition is required.
Hypertension
Hypertension Definition
- Essential (primary) hypertension (95%): High blood pressure for which a secondary cause cannot be found.
- Secondary hypertension (5%): Systolic BP >140 mmHg and diastolic BP >90 mmHg with an identifiable cause.
National Heart Foundation of Australia – Classification of Blood Pressure
Hypertension Definition11
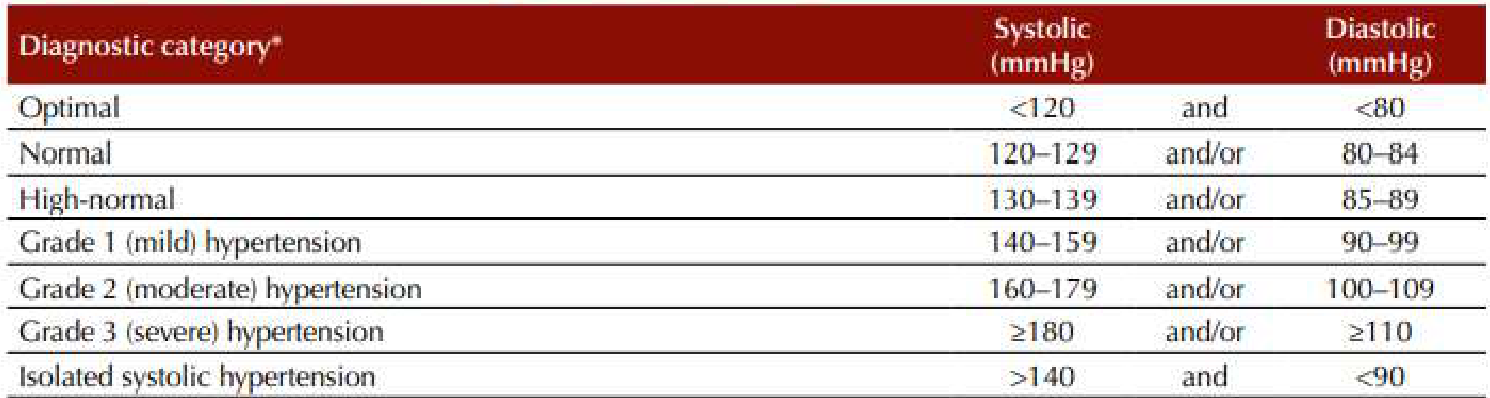
| Diagnostic category* | Systolic (mmHg) | Diastolic (mmHg) |
|---|---|---|
| Optimal | <120 and | <80 |
| Normal | 120–129 and/or | 80–84 |
| High-normal | 130–139 and/or | 85–89 |
| Grade 1 (mild) hypertension | 140–159 and/or | 90–99 |
| Grade 2 (moderate) hypertension | 160–179 and/or | 100–109 |
| Grade 3 (severe) hypertension | ≥180 and/or | ≥110 |
| Isolated systolic hypertension | >140 and | <90 |
*When a patient’s systolic and diastolic blood pressure levels fall into different categories, the higher diagnostic category and recommended actions apply.
Hypertension Aetiology12
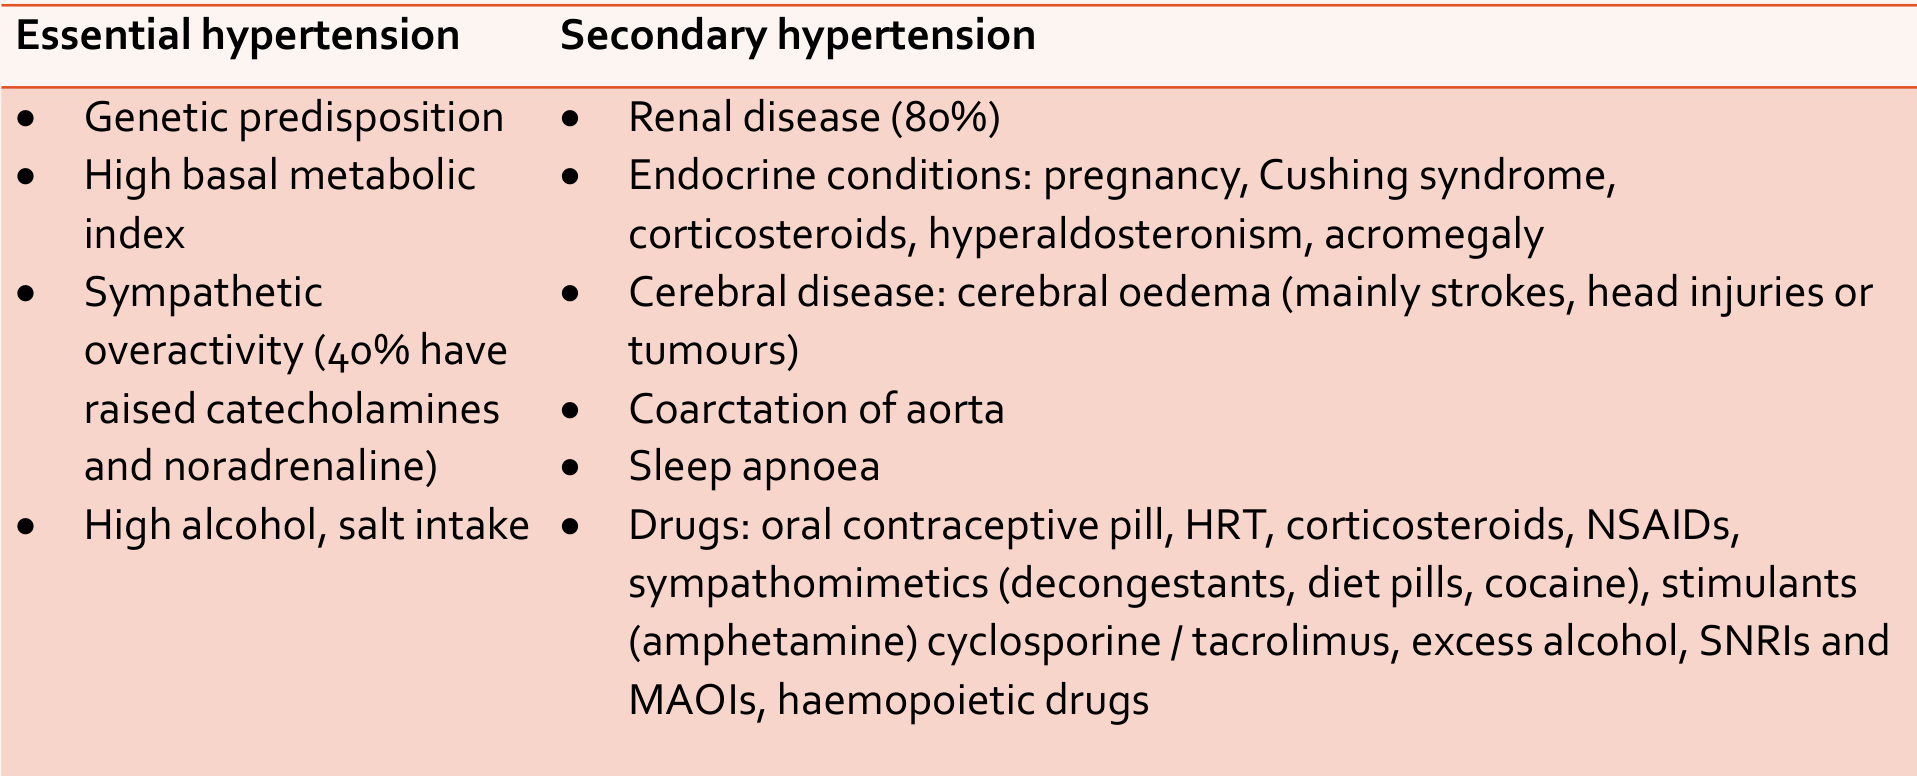
| Essential hypertension | Secondary hypertension |
|---|---|
| Genetic predisposition | Renal disease (80%) |
| High basal metabolic index | Endocrine conditions: pregnancy, Cushing syndrome, corticosteroids, hyperaldosteronism, acromegaly |
| Sympathetic overactivity (40% have raised catecholamines and noradrenaline) | Cerebral disease: cerebral oedema (mainly strokes, head injuries or tumours) |
| High alcohol, salt intake | Coarctation of aorta |
| Sleep apnoea | |
| Drugs: oral contraceptive pill, HRT, corticosteroids, NSAIDs, sympathomimetics (decongestants, diet pills, cocaine), stimulants (amphetamine), cyclosporine/tacrolimus, excess alcohol, SNRIs and MAOIs, haemopoietic drugs |
Hypertension Epidemiology
Australian Institute of Health and Welfare13
- 39% of Australians >18yo have hypertension (~7.2 million adults)
- Of adults with hypertension:
- 80–82% of those <54yo had uncontrolled hypertension
- 65% had been dispensed antihypertensive medications
- Hypertensive disease contributed to 13% of all Australian deaths in 2023
- Nearly 1 in 20 (5%) Australian women aged 15–44 giving birth had new onset hypertension in pregnancy
- 24% of ATSI adults >18yo had hypertension 2022–2023
https://www.aihw.gov.au/reports/risk-factors/hypertension/contents/summary
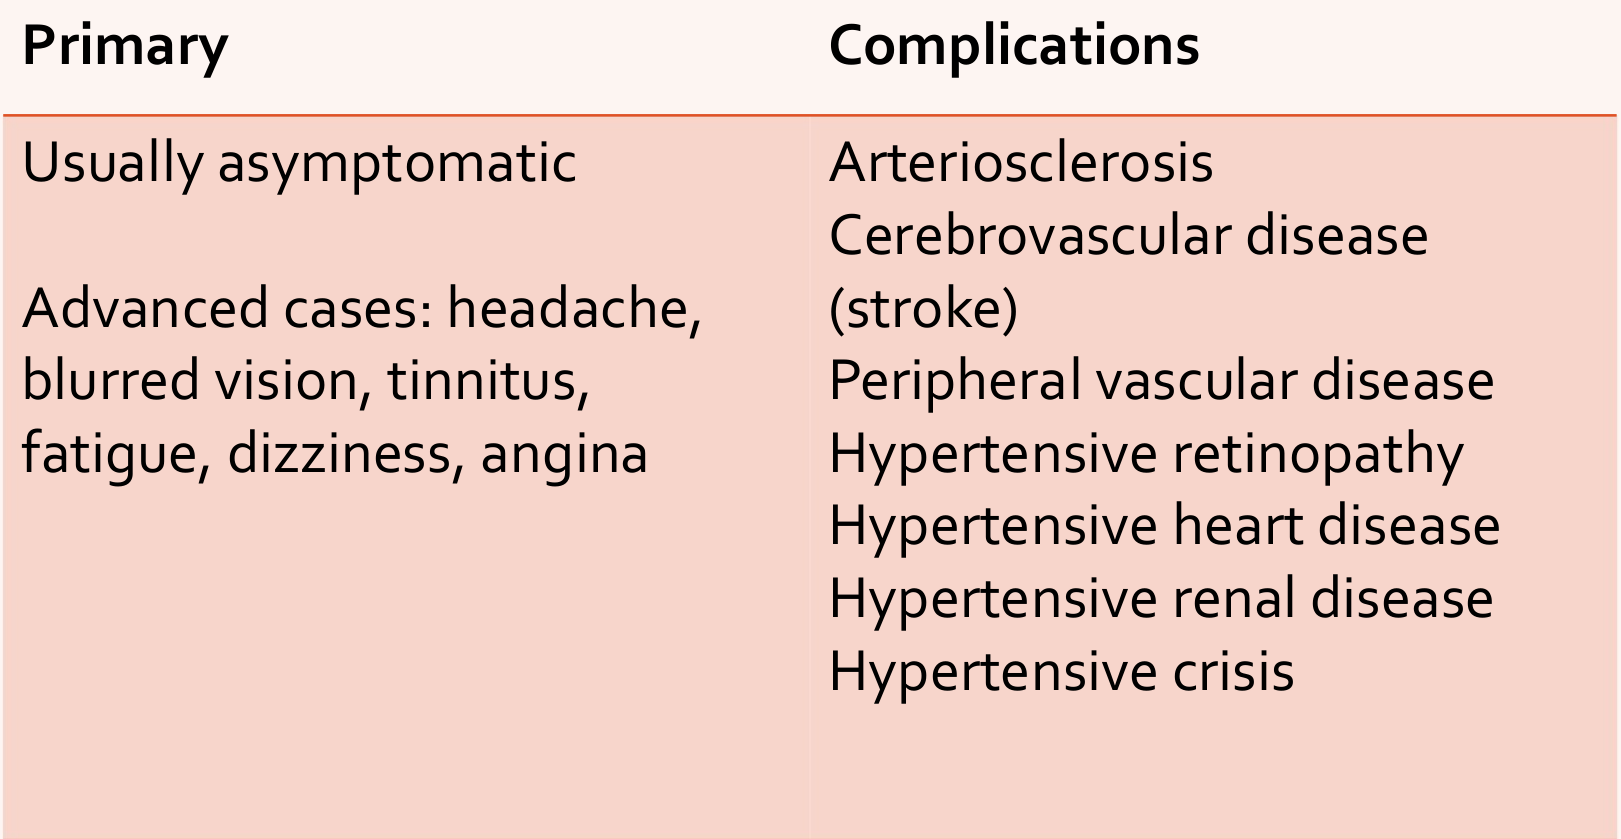
Hypertension General Manifestations14
| Primary | Complications |
|---|---|
| Usually asymptomatic | Arteriosclerosis |
| Advanced cases: headache, blurred vision, tinnitus, fatigue, dizziness, angina | Cerebrovascular disease (stroke) |
| Peripheral vascular disease | |
| Hypertensive retinopathy | |
| Hypertensive heart disease | |
| Hypertensive renal disease | |
| Hypertensive crisis |
Lecturer — Hypertension Damage
Prolonged, uncontrolled hypertension may affect myocardial structure, the coronary vasculature and the cardiac conduction system. Hypertensive renal disease results from chronic high blood pressure damaging the kidneys, while hypertensive crisis carries a high risk of complications involving blood vessels and other organs.
Hypertension General Management
- Identify and manage risk factors: physical activity, smoking cessation, weight control, diet, alcohol intake, etc.
- Assess presence/absence of organ damage
- Pharmacologic strategies: most widely used first-line ACEIs and ARBs
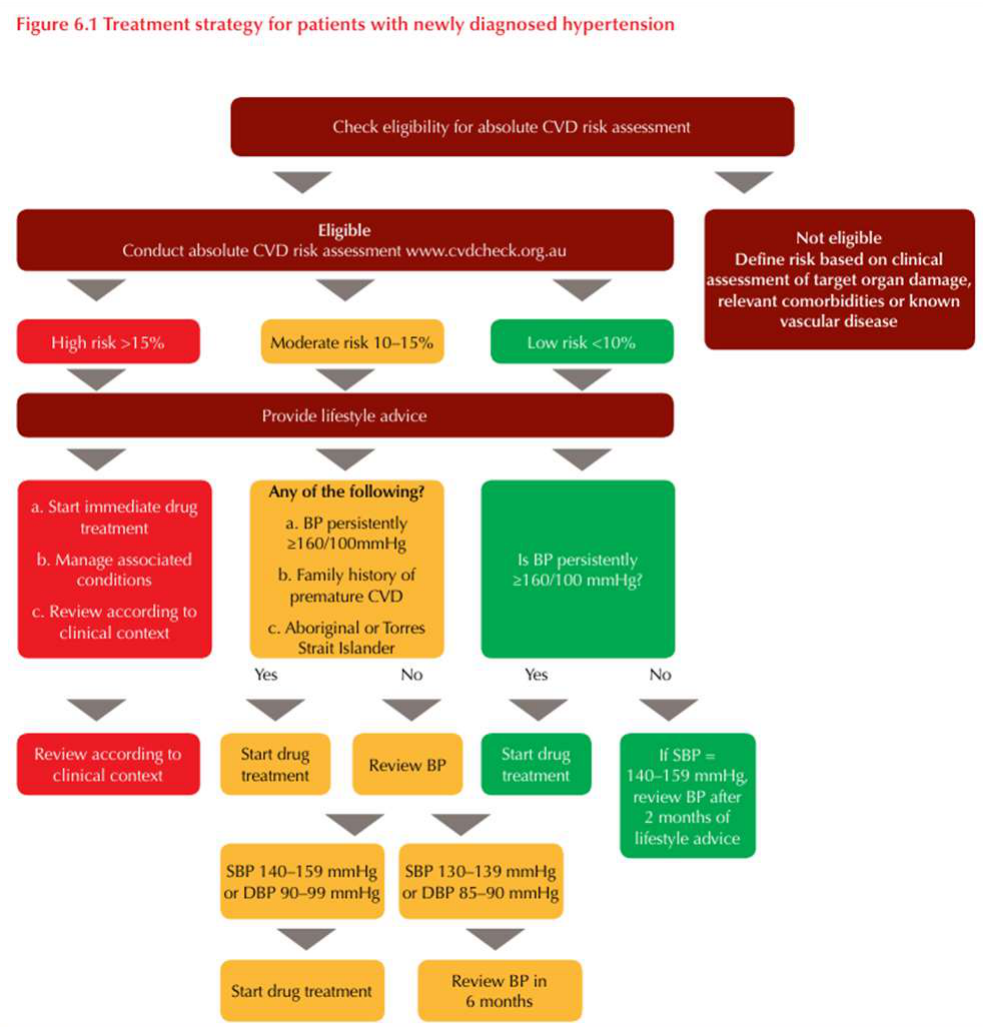
Absolute CVD Risk Assessment15
Check eligibility for absolute CVD risk assessment:
- Eligible: Conduct absolute CVD risk assessment — www.cvdcheck.org.au
- Not eligible: Define risk based on clinical assessment of target organ damage, relevant comorbidities or known vascular disease
Risk categories:
- High risk >15%
- Moderate risk 10–15%
- Low risk <10%
Treatment Pathway
Provide lifestyle advice:
- Start immediate drug treatment
- Manage associated conditions
- Review according to clinical context
Any of the following?
-
BP persistently ≥160/100 mmHg
-
Family history of premature CVD
-
Aboriginal or Torres Strait Islander
-
Yes: Start drug treatment
-
No: Review BP
Is BP persistently ≥160/100 mmHg?
-
Yes: Start drug treatment
-
No: If SBP = 140–159 mmHg, review BP after 2 months of lifestyle advice
-
SBP 140–159 mmHg or DBP 90–99 mmHg → start drug treatment
-
SBP 130–139 mmHg or DBP 85–90 mmHg → review BP in 6 months
-
Review according to clinical context
https://www.heartfoundation.org.au/for-professionals/hypertension
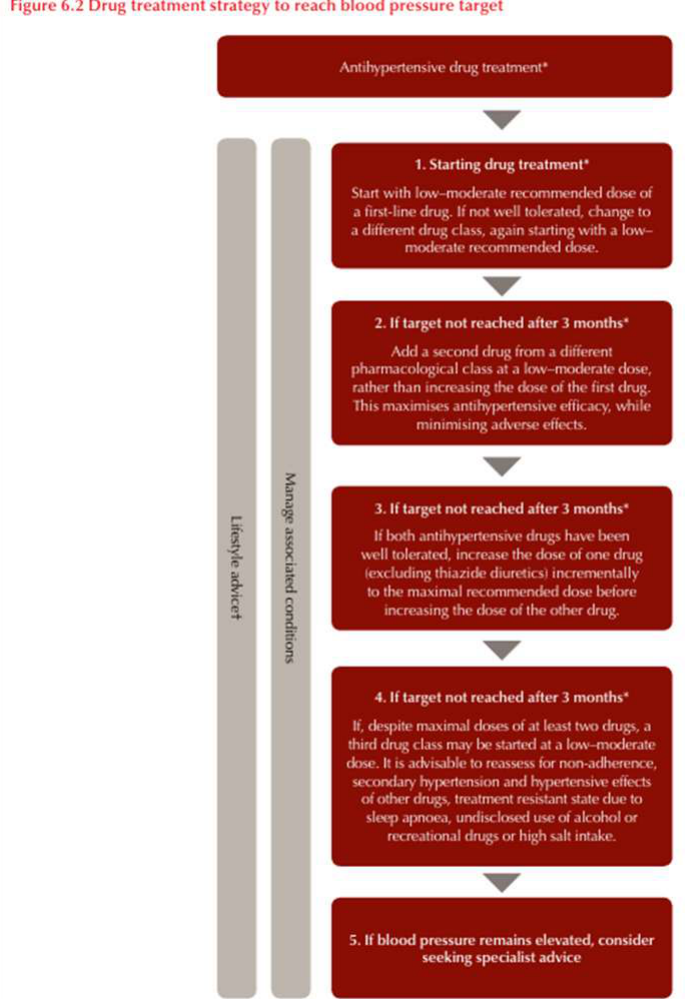
Antihypertensive Drug Treatment16
-
Starting drug treatment — Start with low-moderate recommended dose of a first-line drug. If not well tolerated, change to a different drug class, again starting with a low-moderate recommended dose.
Lifestyle advice; manage associated conditions.
-
If target not reached after 3 months — Add a second drug from a different pharmacological class at a low–moderate dose, rather than increasing the dose of the first drug. This maximises antihypertensive efficacy, while minimising adverse effects.
-
If target not reached after 3 months — If both antihypertensive drugs have been well tolerated, increase the dose of one drug (excluding thiazide diuretics) incrementally to the maximal recommended dose before increasing the dose of the other drug.
-
If target not reached after 3 months — If, despite maximal doses of at least two drugs, a third drug class may be started at a low–moderate dose. It is advisable to reassess for non-adherence, secondary hypertension and hypertensive effects of other drugs, treatment resistant state due to sleep apnoea, undisclosed use of alcohol or recreational drugs or high salt intake.
-
If blood pressure remains elevated — Consider seeking specialist advice.
Maximum effect of drug likely to be seen in 4–6 weeks. If baseline blood pressure is severely elevated earlier reviews may be considered. For steps 1–4, review every 4–6 weeks for tolerance, efficacy and adverse effects. All patients should receive lifestyle advice with follow-up based on clinical context.
 | 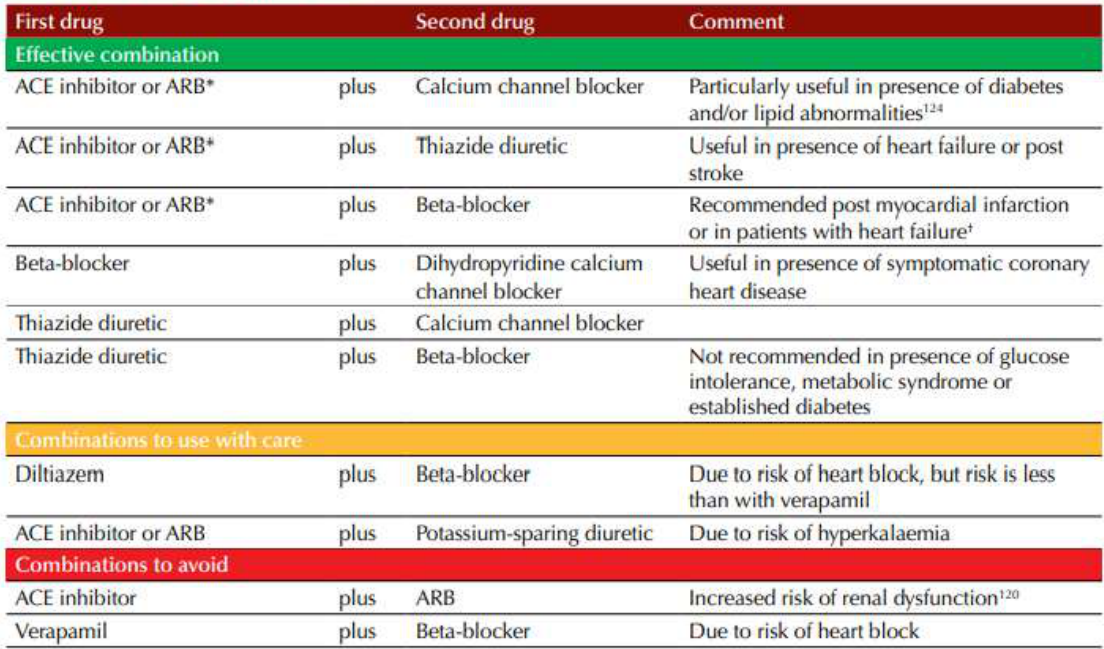 |
Drug Combinations
| First drug | Second drug | Comment |
|---|---|---|
| Effective combination | ||
| ACE inhibitor or ARB* | plus Calcium channel blocker | Particularly useful in presence of diabetes and/or lipid abnormalities |
| ACE inhibitor or ARB* | plus Thiazide diuretic | Useful in presence of heart failure or post stroke |
| ACE inhibitor or ARB* | plus Beta-blocker | Recommended post myocardial infarction or in patients with heart failure† |
| Beta-blocker | plus Dihydropyridine calcium channel blocker | Useful in presence of symptomatic coronary heart disease |
| Thiazide diuretic | plus Calcium channel blocker | |
| Thiazide diuretic | plus Beta-blocker | Not recommended in presence of glucose intolerance, metabolic syndrome or established diabetes |
| Combinations to use with care | ||
| Diltiazem | plus Beta-blocker | Due to risk of heart block, but risk is less than with verapamil |
| ACE inhibitor or ARB | plus Potassium-sparing diuretic | Due to risk of hyperkalaemia |
| Combinations to avoid | ||
| ACE inhibitor | plus ARB | Increased risk of renal dysfunction |
| Verapamil | plus Beta-blocker | Due to risk of heart block |
ACE, angiotensin-converting enzyme; ARB, angiotensin receptor blocker
- *In head-to-head trials ACE inhibitors and ARBs are equally effective in blood pressure reduction and prevention of cardiovascular events overall, however may have important differences in their efficacy, so that they are not interchangeable in some clinical conditions.
- †Carvedilol; bisoprolol (beta-1 selective antagonist); metoprolol extended release (beta-1 selective antagonist); nebivolol.
https://www.heartfoundation.org.au/for-professionals/hypertension
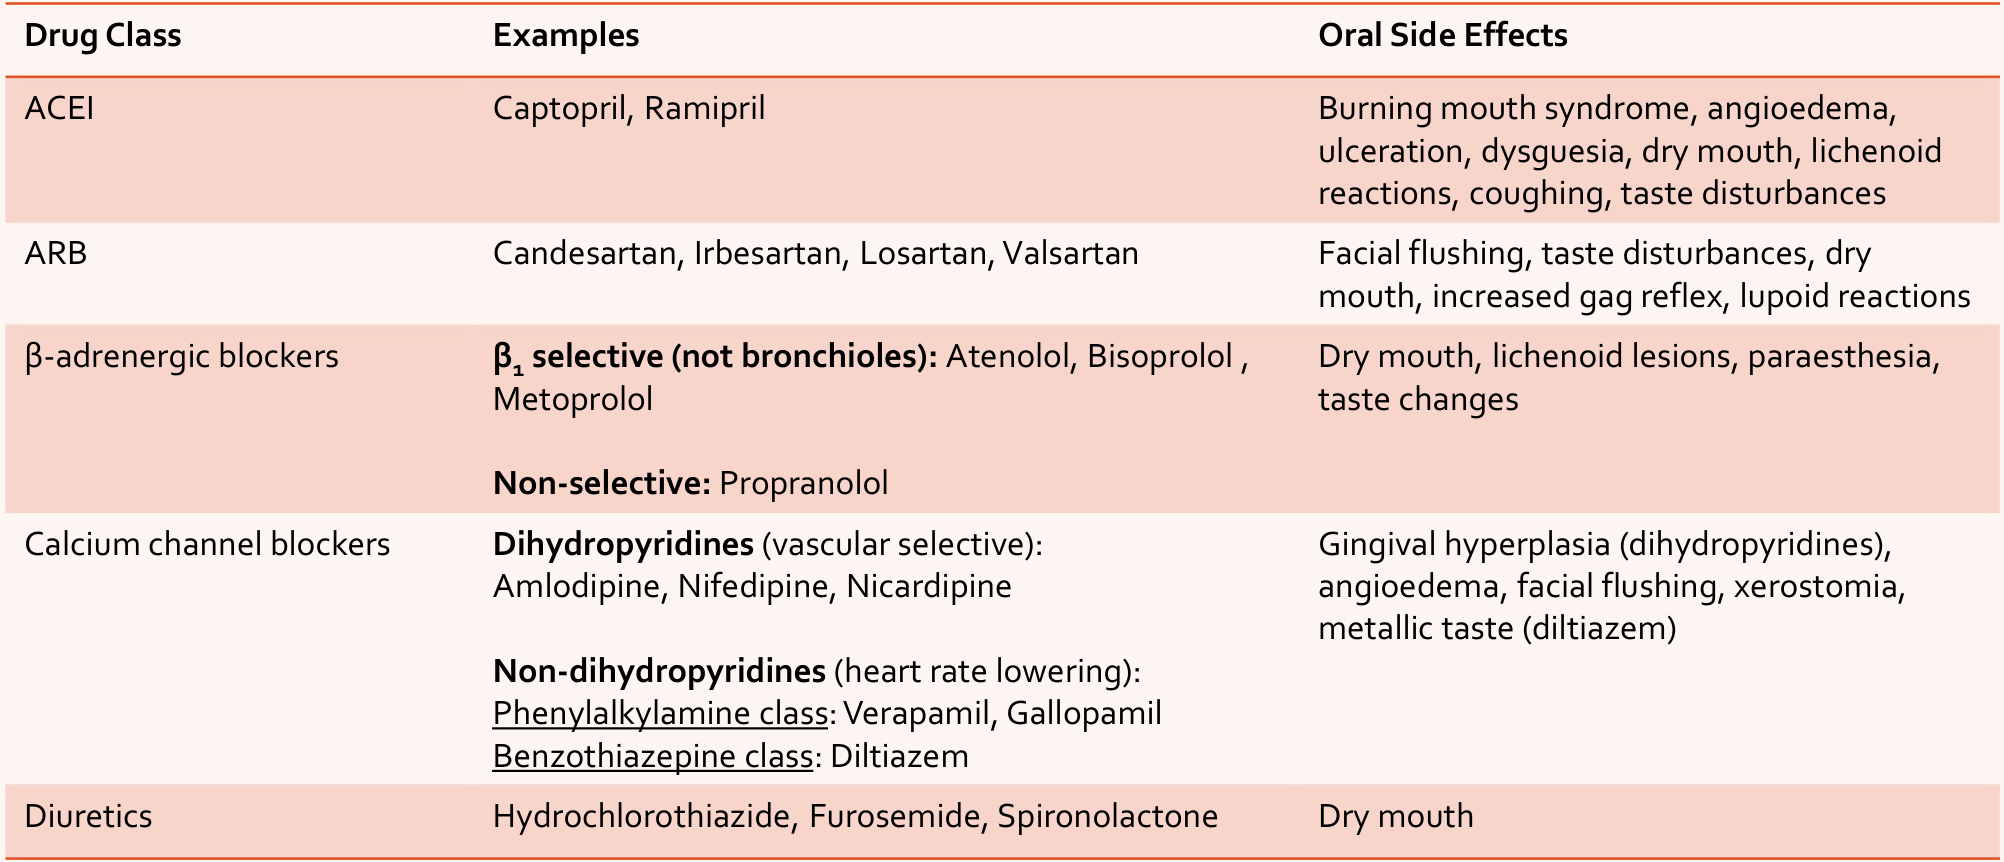
Hypertension Oral Manifestations17
- No recognised oral manifestations from disease
- Hypertensive crisis – facial palsy may occur
- Side-effects of antihypertensive drugs:
| Drug Class | Examples | Oral Side Effects |
|---|---|---|
| ACEI | Captopril, Ramipril | Burning mouth syndrome, angioedema, ulceration, dysguesia, dry mouth, lichenoid reactions, coughing, taste disturbances |
| ARB | Candesartan, Irbesartan, Losartan, Valsartan | Facial flushing, taste disturbances, dry mouth, increased gag reflex, lupoid reactions |
| β-adrenergic blockers | β₁ selective (not bronchioles): Atenolol, Bisoprolol, Metoprolol; Non-selective: Propranolol | Dry mouth, lichenoid lesions, paraesthesia, taste changes |
| Calcium channel blockers | Dihydropyridines (vascular selective): Amlodipine, Nifedipine, Nicardipine; Non-dihydropyridines (heart rate lowering): Phenylalkylamine class — Verapamil, Gallopamil; Benzothiazepine class — Diltiazem | Gingival hyperplasia (dihydropyridines), angioedema, facial flushing, xerostomia, metallic taste (diltiazem) |
| Diuretics | Hydrochlorothiazide, Furosemide, Spironolactone | Dry mouth |
Hypertension Oral Management18
Risk Assessment19
- General dental treatment possible if blood pressure is controlled
- Drug interactions and side effects
- Decrease endogenous catecholamine release: dental anxiety, “white coat syndrome”, manage pain
- Underlying disease or problems (cardiac/renal/endocrine)
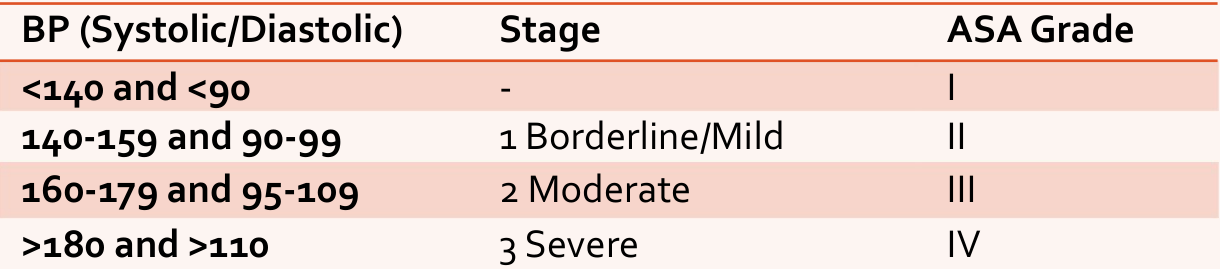
- Avoid elective dental treatment if >180/110 mmHg → refer for medical assessment
- Anaesthetic and sedation risks:
| BP (Systolic/Diastolic) | Stage | ASA Grade |
|---|---|---|
| <140 and <90 | – | I |
| 140–159 and 90–99 | 1 Borderline/Mild | II |
| 160–179 and 95–109 | 2 Moderate | III |
| >180 and >110 | 3 Severe | IV |
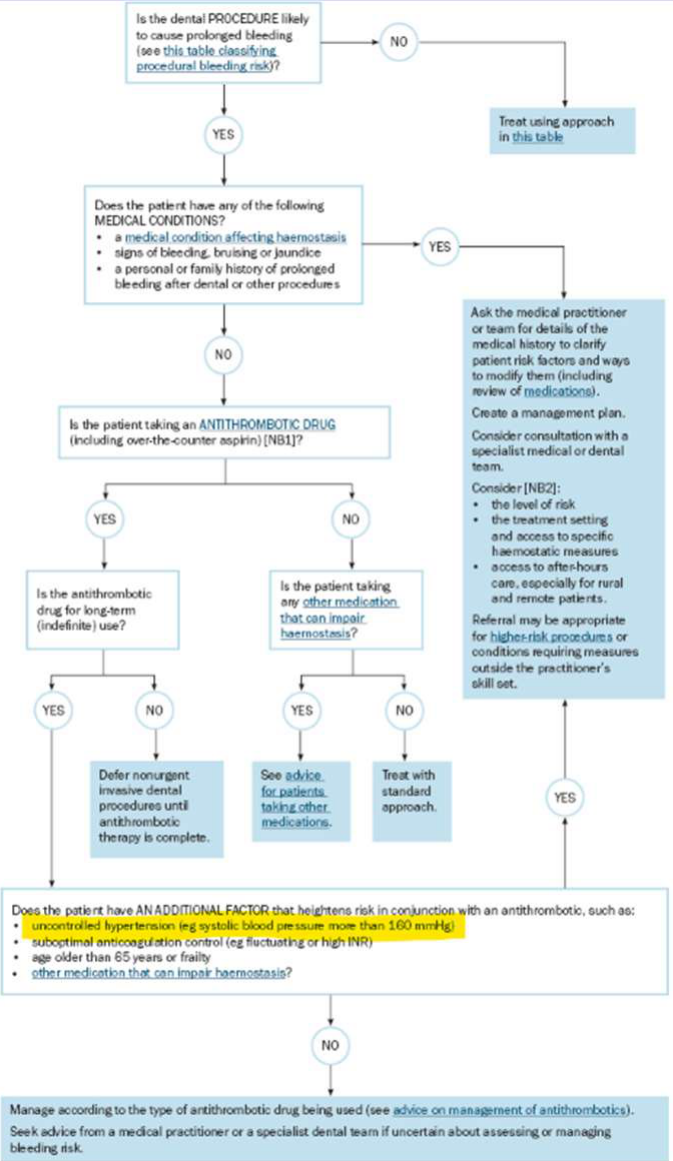
Risk factor when evaluating peri-procedural bleeding risk
(Therapeutic Guidelines v4 2026 – Figure 13.73)
Access20
- Timing/Appointments: Short, minimally stressful, ideally late morning
- Positioning: orthostatic hypotension (ACEIs, ARBs)
- Setting: hospital if severe/uncontrolled hypertension and urgent dental care needed
Education/Prevention
- Common risk factor approach: smoking, alcohol, diet
- Antihypertensives: dry mouth management
- Calcium channel blockers (e.g. amlodipine) → gingiva enlargement
- Minimise with good oral hygiene and perio debridement
- Extensive enlargement → specialist periodontal and medical management
Surgery21
- Check BP control prior to treatment
- Manage dental anxiety (exacerbates hypertension)
- Avoid NSAIDs = diuretic + either of:
- Angiotensin converting enzyme inhibitor (e.g. perindopril)
- Angiotensin II receptor blocker (e.g. candesartan)
- → risk of acute kidney injury
- Sedation may be helpful to control stress/blood pressure
- Pending nature and severity of underlying disease
Vasoconstrictors in Local Anaesthesia2223
How much adrenaline-containing LA can we use?24
- Profound anaesthesia for pain and anxiety control is important to ↓ endogenous catecholamine release
LA with adrenaline:
- Delays systemic absorption
- Increases duration of anaesthesia
- Provides local haemostasis
- Reduces the dose required
Poses a theoretical risk:
- Stimulates α and β adrenergic receptors (tachycardia, increase BP)
- Irritates cardiac pacemaker cells (arrhythmias)
Lecturer — Adrenaline Exposure
The systemic effects of vasoconstrictors depend on the dose and route of administration. Intravenous administration produces greater systemic effects, and the scientific evidence regarding a maximum safe dose remains limited.
- Evidence regarding maximum safe dose of adrenaline is lacking:
- Malamed 2004: Most frequently quoted. Recommended max 0.04 mg adrenaline per dental appointment.
- ~2 cartridges containing 1:100,000 adrenaline (0.018 mg per 1.8 ml cartridge, or 0.022 mg per 2.2 ml cartridge)
- Tolas et al 1982, Cioffi et al 1985: Evaluated healthy patients following 2% lignocaine 1:100,000 adrenaline injection
- After 1.8 ml (1 cartridge): plasma levels increased 2–3x, no significant changes in BP or HR
- After 5.4 ml (3 cartridges): plasma levels increased 5–6x, significant increase in HR and BP
- Godzieba et al 2014: Systematic review of 11 RCTs
- Use of ≤4 cartridges of lignocaine with 1:100,000 adrenaline seems relatively safe for cardiovascular compromised patients
- Serrera Figallo et al 2012: Systematic review of RCTs
- Possible to use a dose between 1.8 ml and 3.6 ml on a general basis in patients with CVD
- Malamed 2004: Most frequently quoted. Recommended max 0.04 mg adrenaline per dental appointment.
Conclusion:
- Use of >2 cartridges of vasoconstrictor-containing LA should be considered a relative rather than absolute contraindication.
- Current consensus seems to favour judicious use of local anaesthetics containing vasoconstrictors to ensure profound anaesthesia.
Recommendations:
- If supplementation with plain LA is required, use vasoconstricting LA first
- Aspirating syringe
- Intraligamentary injection contraindicated
- Some report felypressin has fewer haemodynamic effects
- ?Adrenaline-containing retraction cord astringent
Therapeutic Guidelines v4 202625
-
Local anaesthetics containing adrenaline = limited effect on BP elevation
-
Avoid in patients with uncontrolled hypertension
- Consider felypressin (Citanest® = prilocaine + felypressin)
- Also avoid: MI in previous 6 months, unstable angina, uncontrolled arrhythmias, uncontrolled hyperthyroidism
-
Felipressin is considered an alternative because it has minimal effects on the myocardium at the concentration used in dental cartridges
Ischaemic Heart Disease
- Definition: Group of syndromes resulting from myocardial ischaemia – an imbalance between cardiac blood supply (perfusion) and myocardial oxygen demand.
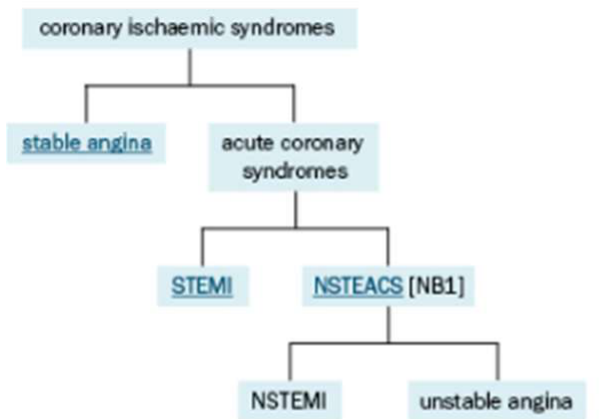
Classification / Aetiology26
Coronary ischaemic syndromes divide into stable angina and acute coronary syndromes; the latter comprise STEMI and NSTEACS (NSTEMI and unstable angina).
 |  |
 |
Ischaemic Heart Disease Definition and Epidemiology
- Stable angina: chronic symptoms
- Stable atherosclerotic plaque → fixed coronary obstruction
- ACS: new or increasing ischaemic symptoms
- Unstable atherosclerotic plaque or endothelial disruption → transient/permanent thrombotic occlusion → ischaemia and infarction
NSTEACS = non-ST elevation acute coronary syndrome; NSTEMI = non-ST elevation myocardial infarction; STEMI = ST elevation myocardial infarction
NB1: NSTEACS can progress to STEMI and acute coronary occlusion can occur without ST elevation, so ongoing monitoring is essential.
Ischaemic Heart Disease Aetiology
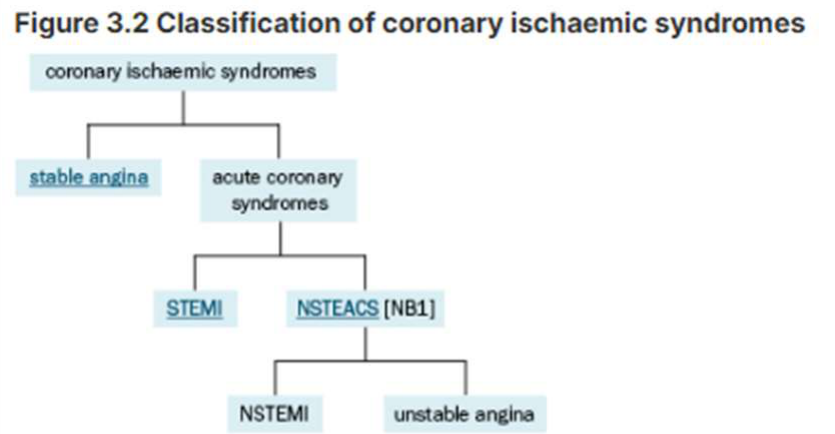
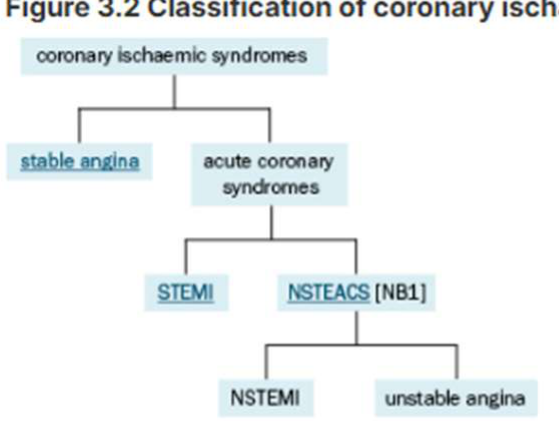
Classification of Coronary Ischaemic Syndromes27
Figure 3.2 Classification of coronary ischaemic syndromes
Coronary ischaemic syndromes divide into stable angina and acute coronary syndromes; the latter comprise STEMI and NSTEACS (NSTEMI and unstable angina).
NSTEACS = non-ST elevation acute coronary syndrome; NSTEMI = non-ST elevation myocardial infarction; STEMI = ST elevation myocardial infarction
NB1: NSTEACS can progress to STEMI and acute coronary occlusion can occur without ST elevation, so ongoing monitoring is essential.
 |  |  |
 |  |  |
 |
Acute Coronary Syndromes
- Non-ST elevation acute coronary syndrome
- Unstable angina = without elevated cardiac biomarkers
- Non-ST elevation myocardial infarction = pts with MI as determined by elevated cardiac biomarkers
- ST-elevation myocardial infarction = medical emergency
→ NSTEACS can progress to STEMI
Thygesen K, Alpert JS, Jaffe AS, Chaitman BR, Bax JJ, Morrow DA, et al. Fourth Universal Definition of Myocardial Infarction (2018). J Am Coll Cardiol 2018;72(18):2231-64
Type 1 Myocardial Infarction28
- Atherothrombotic coronary occlusion compromises myocardial blood flow
Type 2 Myocardial Infarction
- Secondary to an imbalance between myocardial oxygen supply and demand (arises from e.g. tachyarrhythmias, sustained bradyarrhythmias, anaemia, respiratory failure and hypotension)
- Coronary artery spasm
- Spontaneous coronary artery dissection
- Coronary embolism
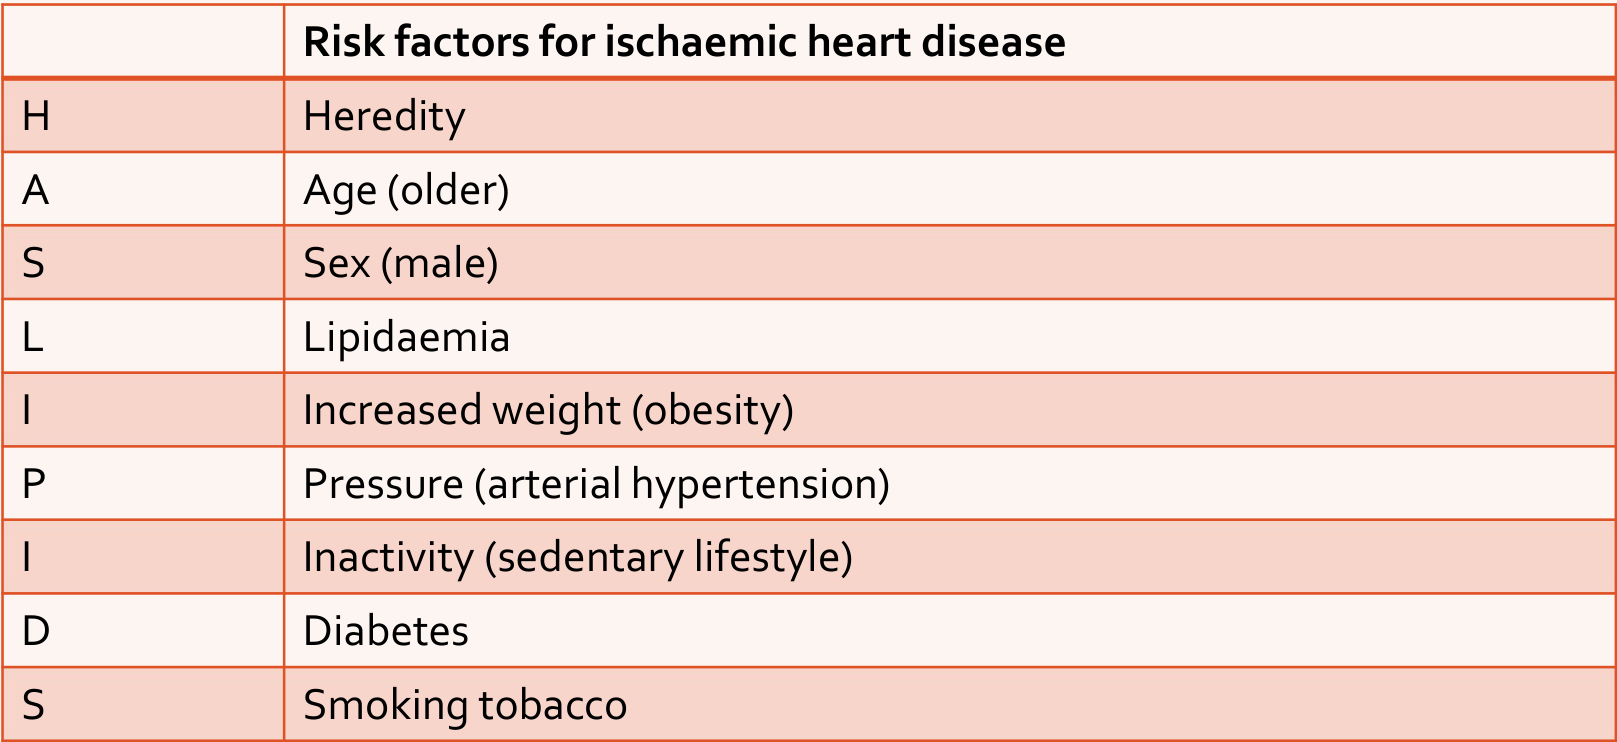
Risk Factors for Ischaemic Heart Disease29
- H – Heredity
- A – Age (older)
- S – Sex (male)
- L – Lipidaemia
- I – Increased weight (obesity)
- P – Pressure (arterial hypertension)
- I – Inactivity (sedentary lifestyle)
- D – Diabetes
- S – Smoking tobacco
Epidemiology30
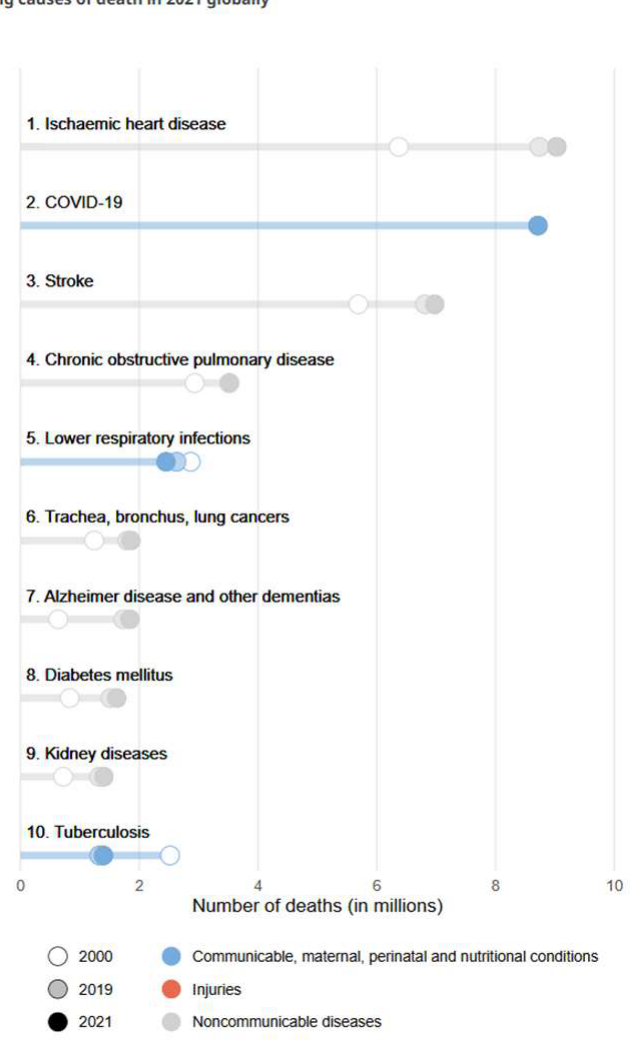
- Leading cause of death globally: 13%
- Prevalence: 3% in Australia (higher amongst males)
- Significant decrease in age-standardised IHD mortality rates
- 1960s: 7/10 MIs fatal; today: 7/10 survive an MI
- CVD-related prescriptions increased 7–8 fold in this time
Ischaemic Heart Disease General Manifestations31
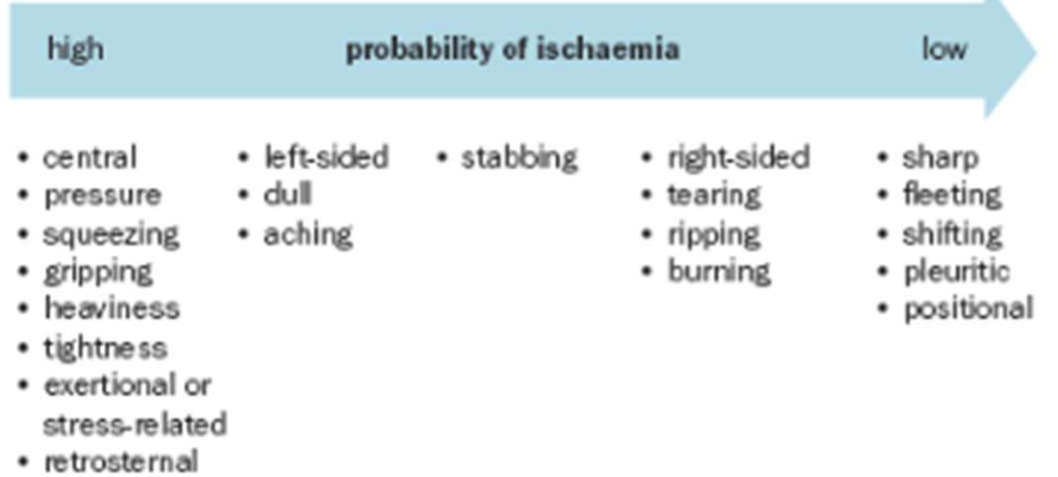
Chest pain features range from a high probability of ischaemia to low:
- High probability of ischaemia
- central
- pressure
- squeezing
- gripping
- heaviness
- tightness
- exertional or stress-related
- retrosternal
- Intermediate
- left-sided
- dull
- aching
- stabbing
- right-sided
- tearing
- ripping
- burning
- Low probability
- sharp
- fleeting
- shifting
- pleuritic
- positional
Gulati M, Levy PD, Mukherjee D, Amsterdam E, Bhatt DL, Birtcher KK, et al. 2021 AHA/ACC/ASE/CHEST/SAEM/SCCT/SCMR Guideline for the Evaluation and Diagnosis of Chest Pain: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 2021;144(22):e368-e454.
Stable Angina32
- Episodic retrosternal chest discomfort (pain, ache or tightness)
- May radiate to arms, neck, back, shoulder, jaw
- Commonly triggered by physical activity or emotional stress
- Predictable, consistent over time
- Lasts <10 min if provoking stimulus removed
- Subsides with rest or GTN
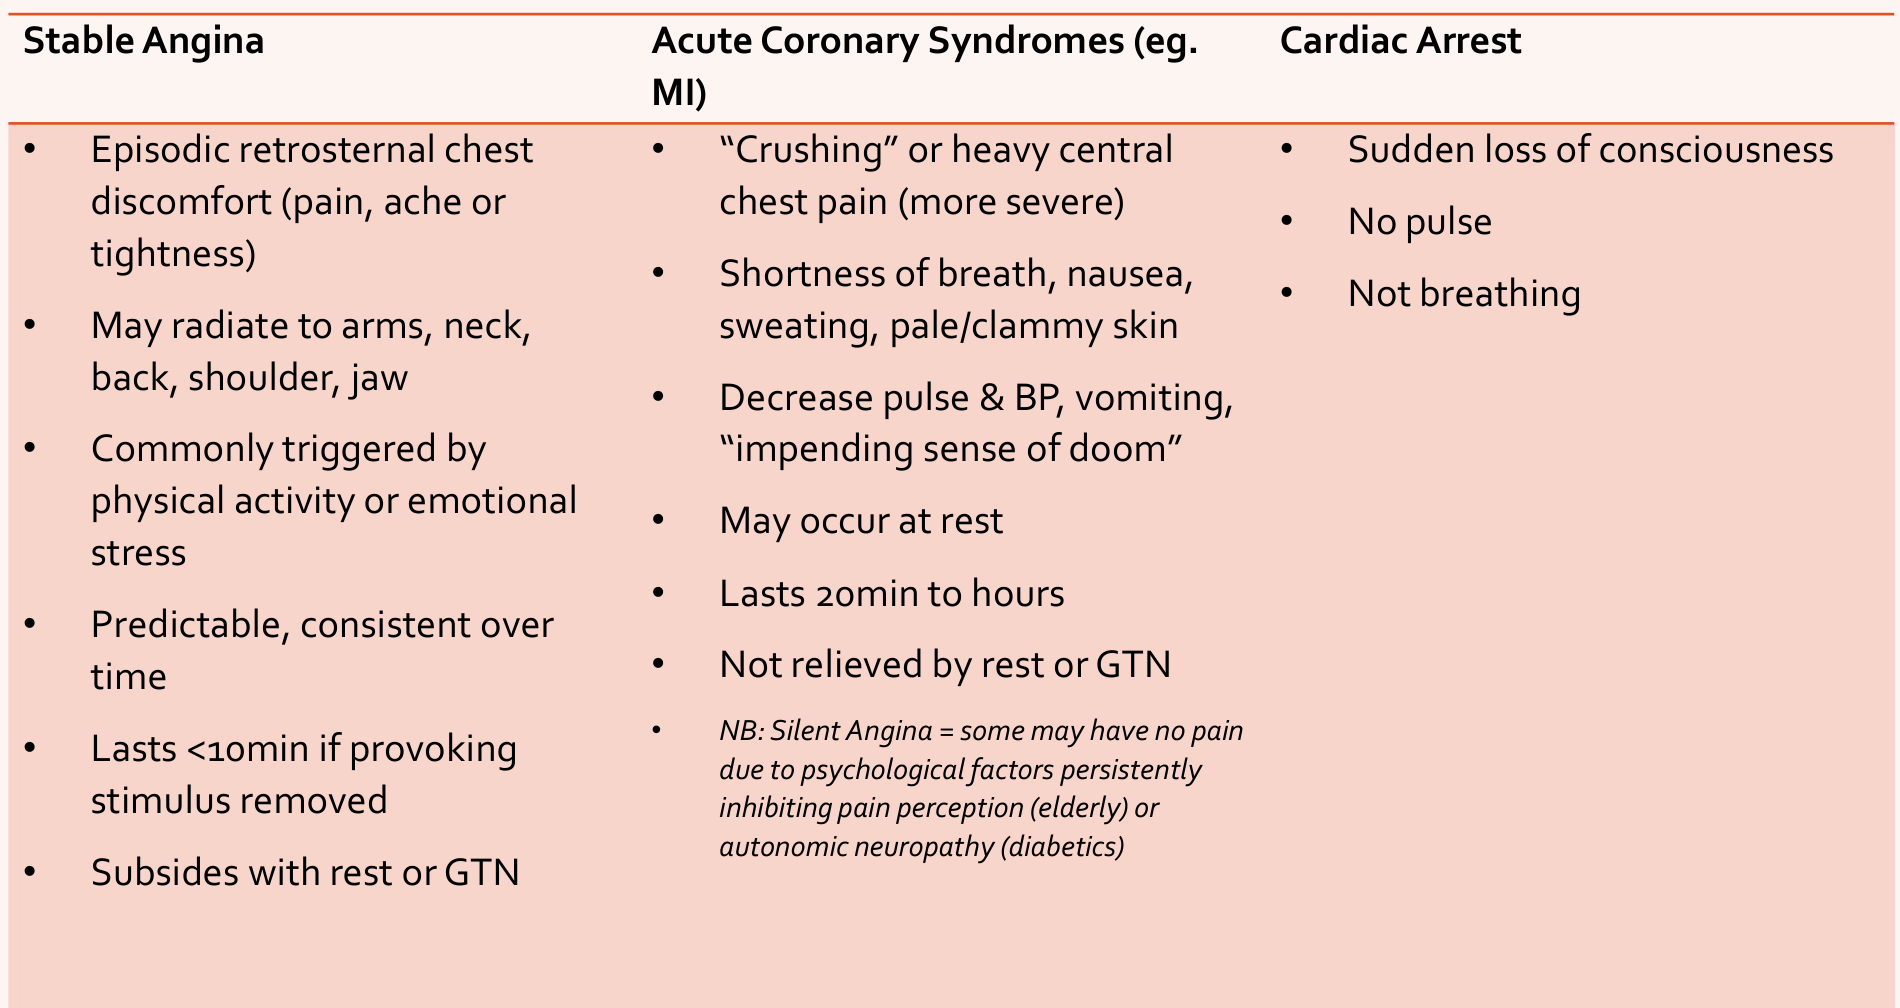
Acute Coronary Syndromes (e.g. MI)
- “Crushing” or heavy central chest pain (more severe)
- Shortness of breath, nausea, sweating, pale/clammy skin
- Decreased pulse & BP, vomiting, “impending sense of doom”
- May occur at rest
- Lasts 20 min to hours
- Not relieved by rest or GTN
NB: Silent angina = some may have no pain due to psychological factors persistently inhibiting pain perception (elderly) or autonomic neuropathy (diabetics)
Cardiac Arrest
- Sudden loss of consciousness
- No pulse
- Not breathing
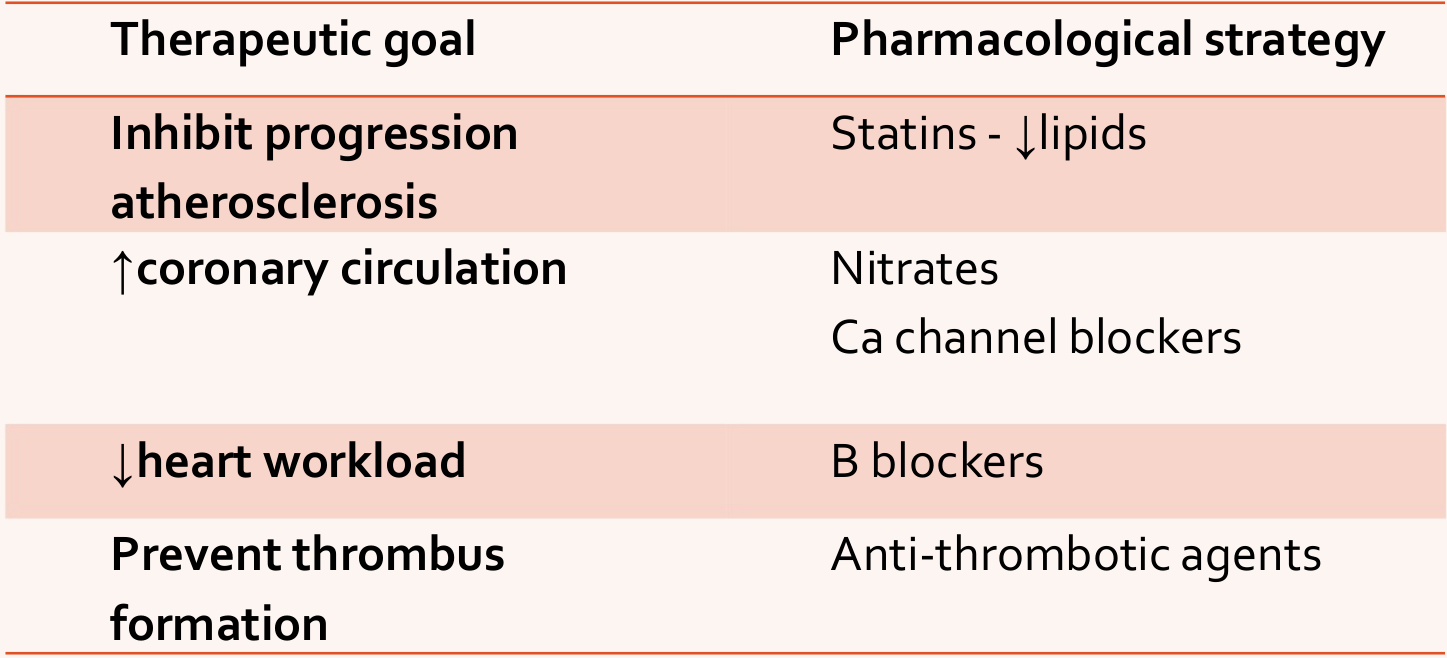
Ischaemic Heart Disease General Management33
Lifestyle34
- ↓ Smoking
- Diet
- ↓ Alcohol
- Physical activity
- Healthy weight
- Psychosocial
Pharmacological
- Beta-blockers
- Calcium-channel blockers
- Nitrates
- Nicorandil
- ACE inhibitors
- ARBs
- Antiplatelets
- Lipid-lowering drugs
- Ivabradine
Revascularisation
- Coronary artery bypass grafting (CABG)
- Percutaneous coronary intervention (PCI) = “coronary angioplasty and stent”
Lecturer — Revascularisation Details
Revascularisation improves oxygen supply by relieving or bypassing the atherosclerotic obstruction.
- Coronary artery bypass grafting may use the left internal mammary artery, saphenous vein or radial artery, attached above and below the obstruction.
- Coronary angioplasty uses a catheter and balloon to open the vessel, after which a stent remains in place to keep it open.
| Therapeutic goal | Pharmacological strategy |
|---|---|
| Inhibit progression of atherosclerosis | Statins – ↓ lipids |
| ↑ coronary circulation | Nitrates; Ca channel blockers |
| ↓ heart workload | Beta blockers |
| Prevent thrombus formation | Anti-thrombotic agents |
Ischaemic Heart Disease Oral Manifestations35
- Antihypertensive drugs: as per previous section
- Nicorandil: oral/skin/eye ulceration, facial flushing, lupoid lesions
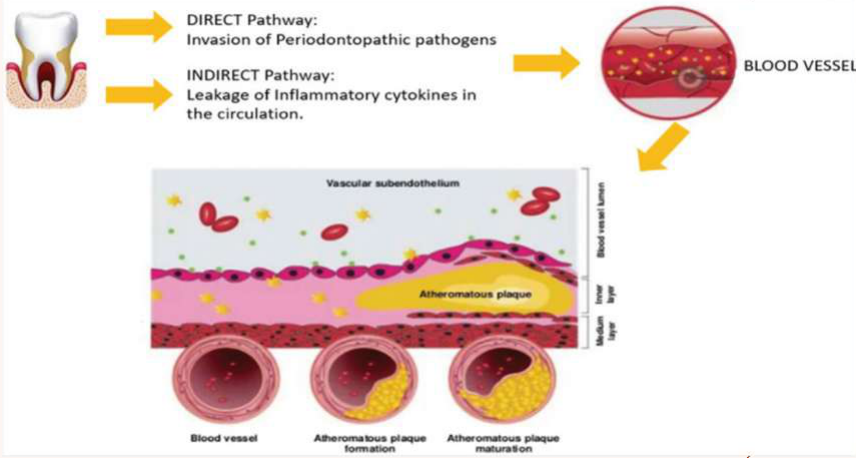
Periodontitis36
Possible association with periodontitis (growing evidence):
- Direct pathway – bacteraemia
- Indirect pathway – induces chronic systemic inflammatory state
Lecturer — Periodontitis Mechanisms
Proposed links between periodontitis and ischaemic heart disease include more than bacteraemia and chronic systemic inflammation.
- Inflammatory mediators may promote a prothrombotic state.
- Antibodies produced in response to periodontal infection may cross-react with the heart.
- The association is emerging and is not equivalent in strength to the established association between diabetes and periodontitis.
Endodontic Disease
Possible association with endodontic disease (less investigated and inconclusive evidence):
- Apical periodontitis – comparable inflammatory and microbial profile (gram –ve anaerobes) to periodontal disease
- Pulp stones – similarity to calcified stones forming in coronary and renal arteries
Referred Pain
Rarely, angina pain referred to lower jaw/teeth mistakenly thought to be of dental origin (clue: onset with exertion)
Periodontal Disease and Atherosclerotic Cardiovascular Disease: A Scientific Statement From the American Heart Association | Circulation
European Federation of Periodontology: https://www.bsperio.org.uk/assets/downloads/EFP_cardiovascular-disease-gum-disease.pdf
Ischaemic Heart Disease Dental Management
Risk Assessment37
Careful medical history at first appointment. Ask about indicators of risk:
- History of chest pain at rest
- Triggers/frequency of episodes
- Carry GTN?
- How episodes are usually managed
- Number of anti-anginal medications
- Hx of CABG/stent placement with ongoing symptoms
- Hx of heart failure
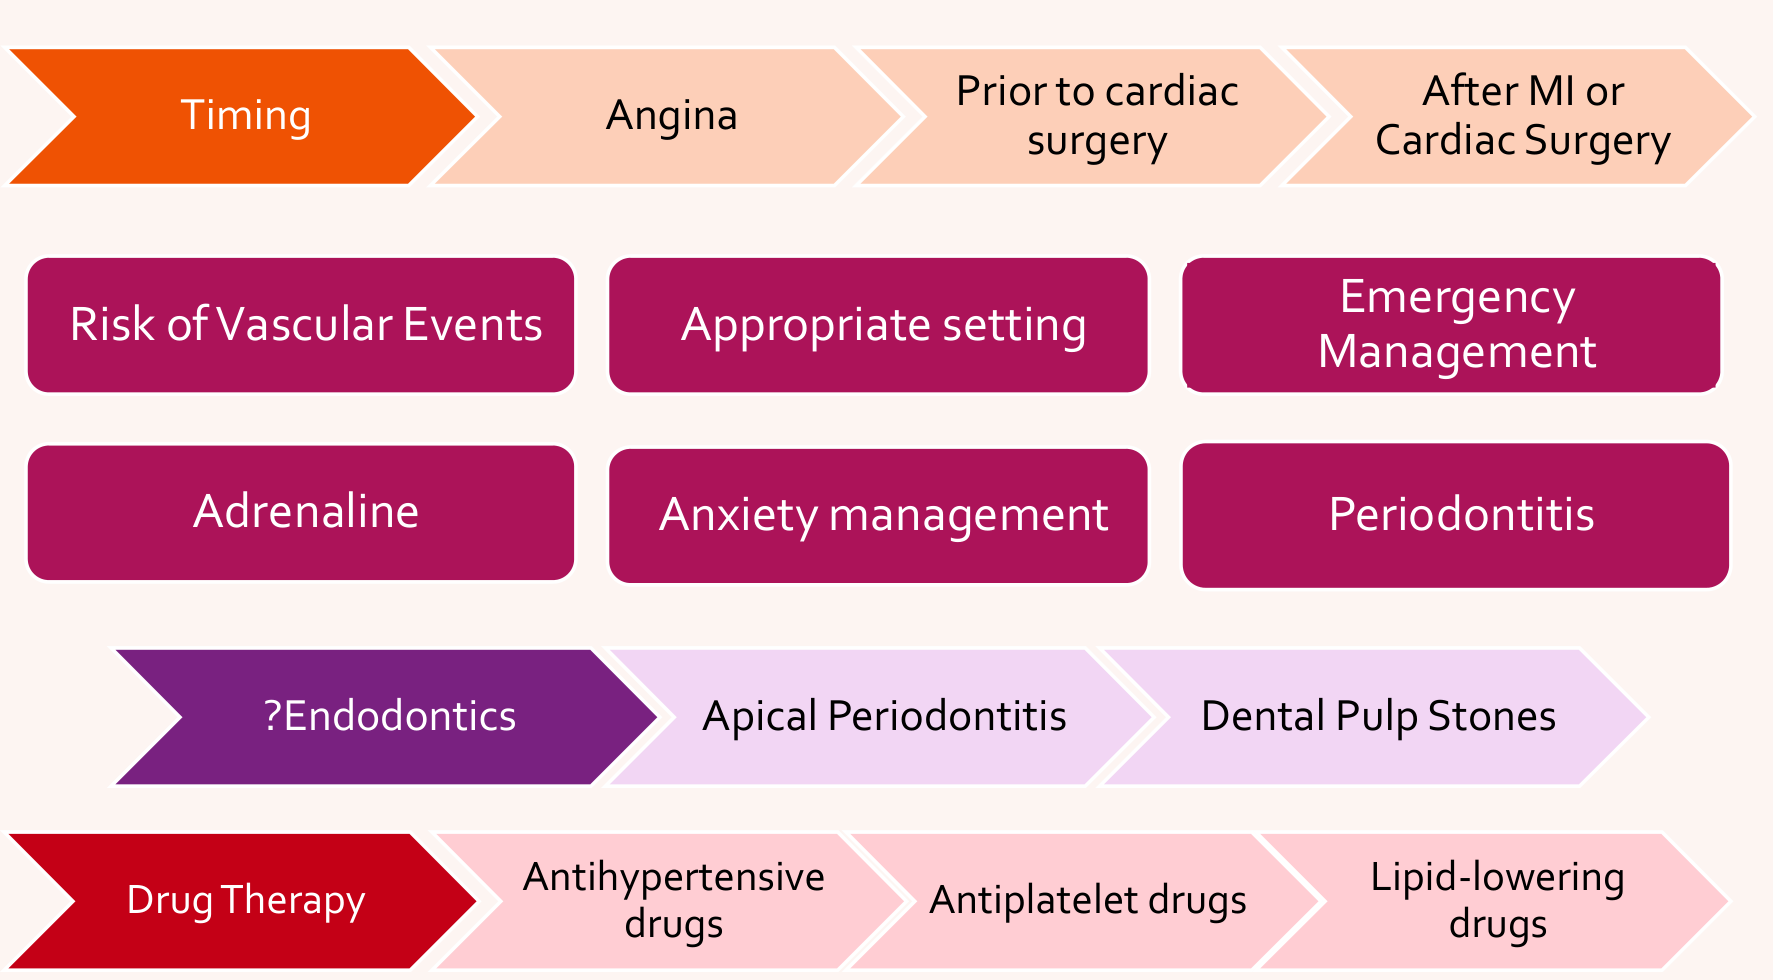
Risk Assessment – Key Considerations38
- Timing: angina → prior to cardiac surgery → after MI or cardiac surgery
- Risk of vascular events
- Appropriate setting
- Emergency management
- Adrenaline
- Anxiety management
- Periodontitis
- ?Endodontics: apical periodontitis → dental pulp stones
- Drug therapy: antihypertensive drugs → antiplatelet drugs → lipid-lowering drugs
Access39
-
Access to clinic / mobility: functional capacity (cardiopulmonary reserve)
-
Appointments: short, minimally stressful appointments; late morning appointments
-
Positioning: orthostatic hypotension (antihypertensives) → semi-supine and slowly upright
-
Location / setting: hospital setting may be required for severe cardiac disease when emergency dental treatment required
-
Patients may be connected to monitoring equipment, fluids or other devices that affect their ability to access a dental chair
Timing
- Patients with history of angina (or MI >6 months earlier) can undergo dental treatment if medically stable
- Defer elective dental care if unstable angina
- Defer elective dental procedures for 6 months after MI, stent placement or CABG
- Pain and infection within 6 months of the above:
- provide adequate emergency treatment
- avoid use of adrenaline-containing LA
- consider specialist advice re: appropriate treatment and timing of procedures
Capacity40
- Nil significant
Consent
- Nil significant
Education / Prevention
- Oral side effects of medications
- Possible association with periodontitis +/- endodontic disease
Pre-operative41
- Instruct patients with angina to bring their medication (e.g. GTN spray or tablets), and have it readily accessible
- Ensure GTN and oxygen readily available
- Monitor SpO₂, BP, HR
Peri-operative
- Use relaxation techniques and consider other measures for anxiety management
- Limit the duration of dental procedures
- Bleeding: may be on antithrombotics (see Haematology – Bleeding Disorders lecture)
- LA: ensure effective analgesia → use of adrenaline (see Hypertension)
- Sedation: anxiety relief helpful (see Hypertension)
Post-operative
- Caution with NSAIDs
Management of Chest Pain in Dental Practice42
NB1: Many people with chest pain do not have angina or a heart attack, but anyone with acute chest pain requires rapid medical evaluation for potentially life-threatening causes. The likelihood of angina or heart attack increases with the number of suggestive features.
NB2: Sublingual glyceryl trinitrate (GTN) dosing is a 400 microgram spray (or 300 to 600 microgram tablet) generally administered every 5 minutes to a maximum of 3 doses. Ask patients who use GTN to bring their GTN to their dental appointment so that it can be administered if chest pain occurs.
NB3: If symptoms (pain or other features that may indicate angina) last longer than the patient’s usual angina symptoms, urgent medical evaluation of a possible heart attack or other urgent condition is required.
Patient with Chest Pain and Features Suggestive of Heart Attack [NB1]43
- A prior diagnosis of angina or heart attack, or chest pain on exertion
- Persistent central chest sensation of: pressure, squeezing, gripping, heaviness, or tightness
- Radiation of the pain, pressure or tightness to the arms, neck, back or jaw
- Breathlessness, nausea, vomiting, sweating or fatigue (these can be present in angina or heart attack without pain, especially in older patients, females and people with diabetes)
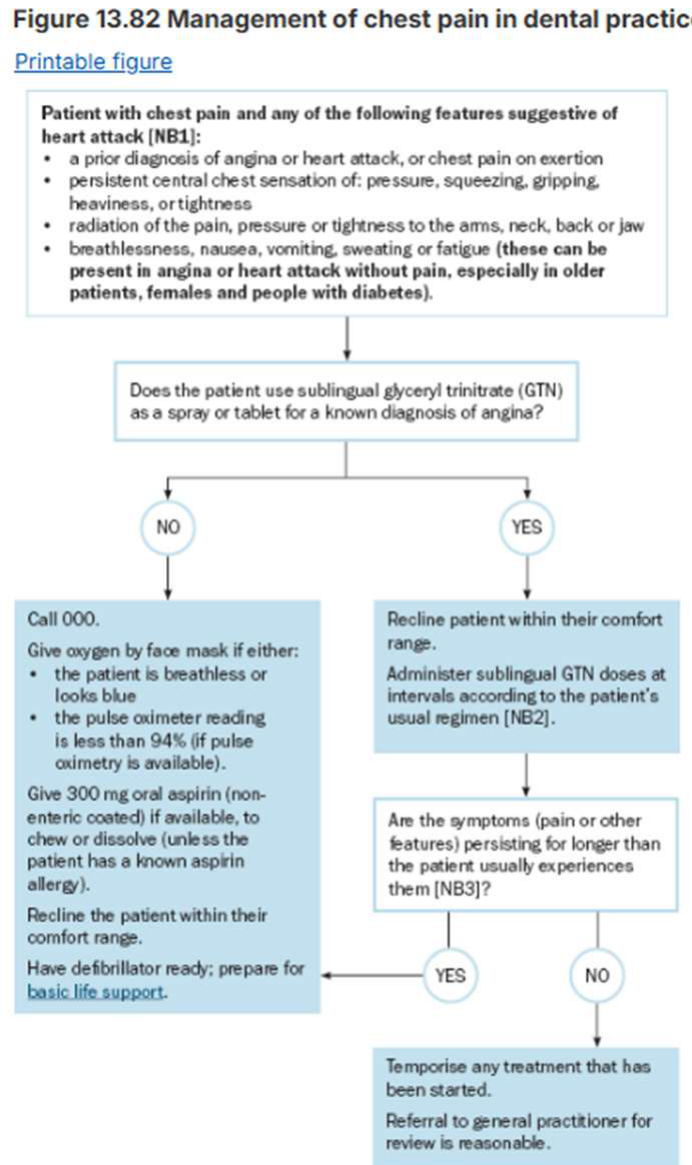
Does the Patient Use Sublingual GTN for a Known Diagnosis of Angina?
NO
- Call 000.
- Give oxygen by face mask if either:
- the patient is breathless or looks blue
- the pulse oximeter reading is less than 94% (if pulse oximetry is available)
- Give 300 mg oral aspirin (non-enteric coated) if available, to chew or dissolve (unless the patient has a known aspirin allergy)
- Recline the patient within their comfort range
- Have defibrillator ready; prepare for basic life support
YES
- Recline patient within their comfort range
- Administer sublingual GTN doses at intervals according to the patient’s usual regimen [NB2]
Are the Symptoms Persisting Longer than the Patient Usually Experiences Them [NB3]?
YES → Call 000
NO
- Temporise any treatment that has been started
- Referral to general practitioner for review is reasonable
If administering nitrates, recline the patient because blood pressure can be reduced by administration. To manage chest pain in a patient with a history of angina, use:
-
Glyceryl trinitrate spray 400 micrograms sublingually, repeat every 5 minutes if pain persists, up to a total of 3 doses if tolerated
OR
-
Glyceryl trinitrate tablet 300 to 600 micrograms sublingually, repeat every 5 minutes if pain persists, up to a total of 3 doses if tolerated
To manage chest pain if angina or heart attack is suspected, provided no contraindication (e.g. aspirin allergy) is present, use:
- Aspirin (non-enteric coated) 300 mg orally, chewed or dissolved before swallowing
Thromboembolic Complications of CVD
Aetiology44
- Arterial thrombi: platelet aggregation + fibrin + erythrocytes
- Venous thrombi: slow & turbulent blood flow, ↑ risk small emboli detaching & blocking pulmonary arteries
Arterial Thrombi45
- TIA/stroke
- Occlusion of coronary artery grafts
- MI & death in unstable angina
- Systemic embolism with prosthetic heart valves/AF
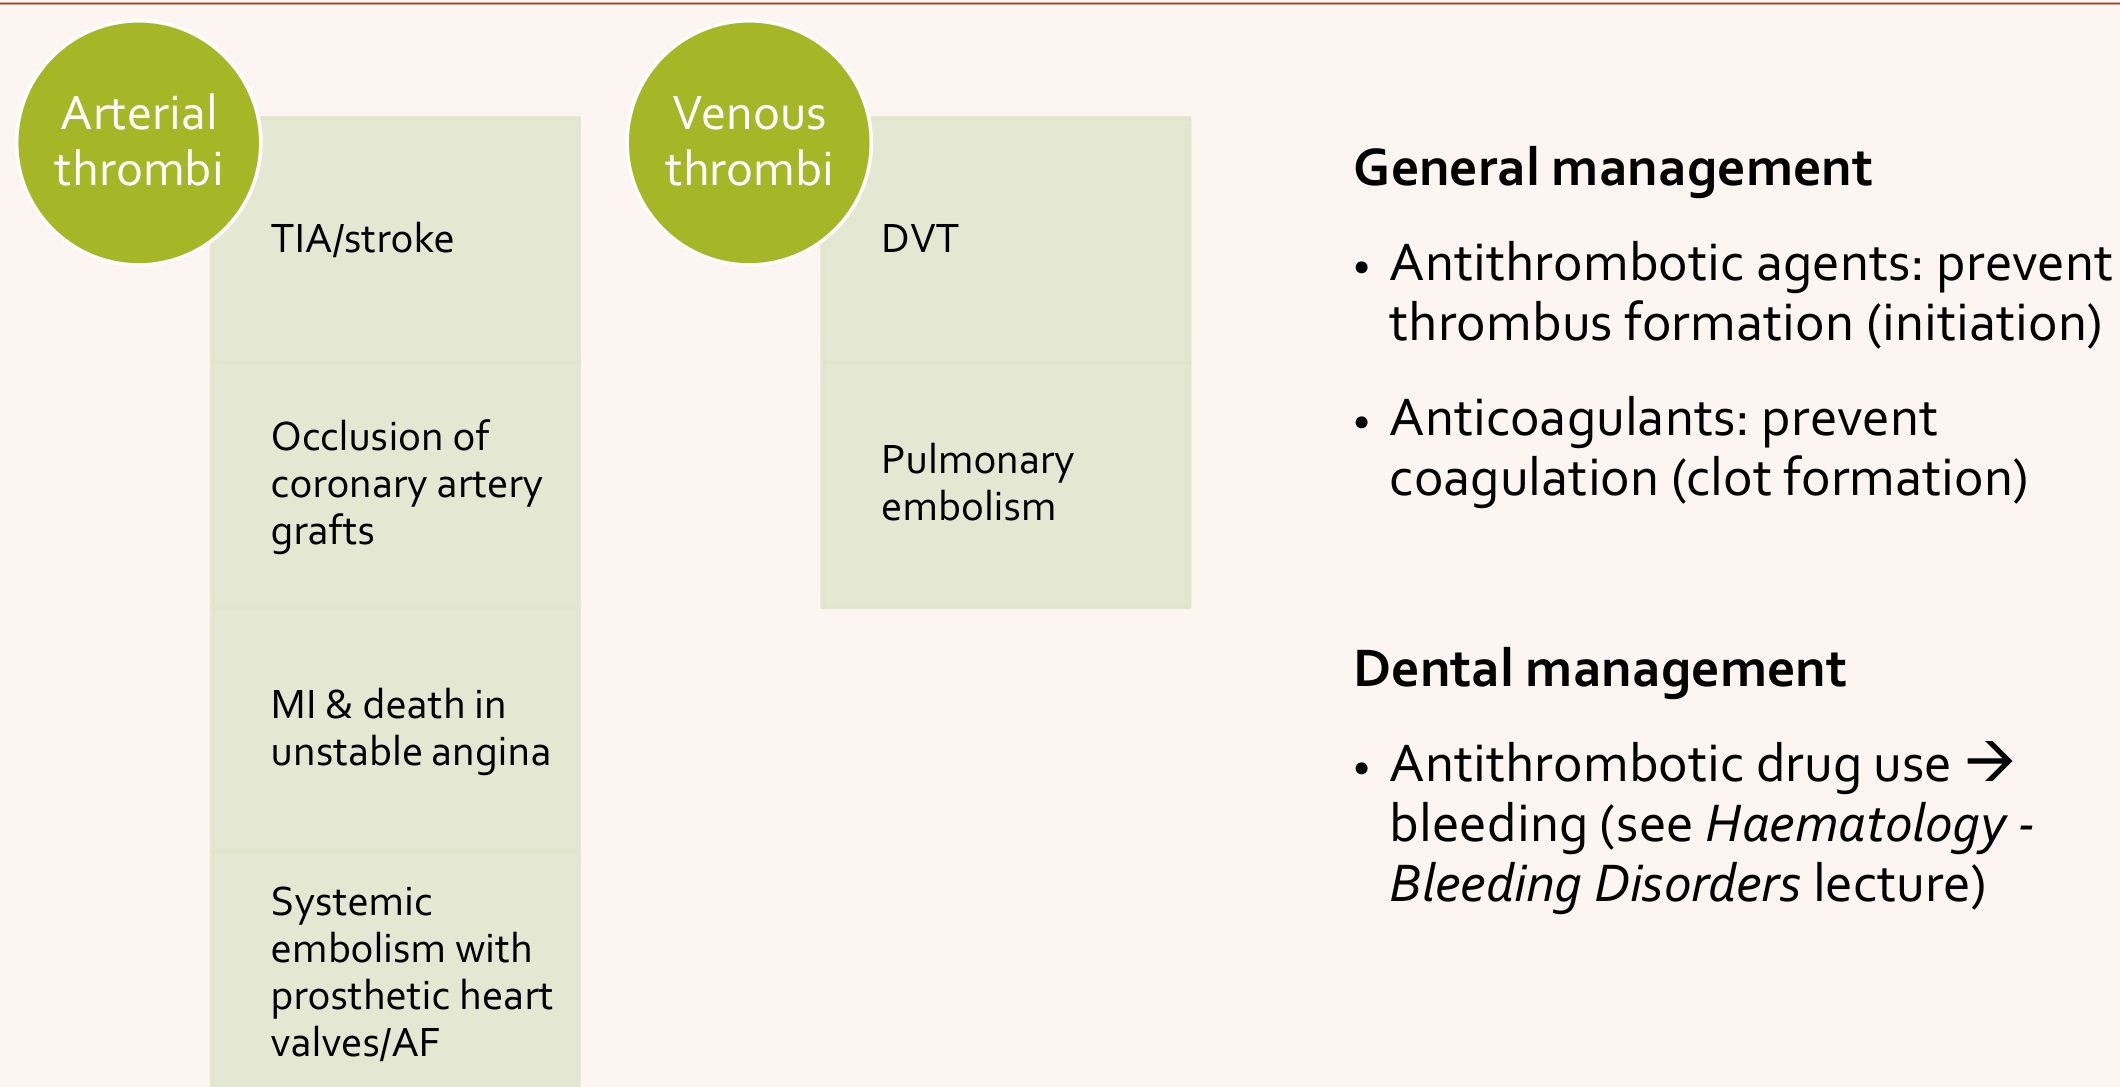
Venous Thrombi
- DVT
- Pulmonary embolism
General Management
- Antithrombotic agents: prevent thrombus formation (initiation)
- Anticoagulants: prevent coagulation (clot formation)
Dental Management
- Antithrombotic drug use → bleeding (see Haematology – Bleeding Disorders lecture)
Valvular Conditions46
- Rheumatic fever and rheumatic heart disease
- Infective endocarditis
- Aortic and mitral valve stenosis, regurgitation and prolapse
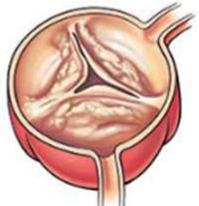
Rheumatic Fever and Rheumatic Heart Disease47
 |  |
 |
Definition48
- Rheumatic Fever: An acute, immunologically-mediated, systemic inflammatory condition characterised by fever and arthritis 2-4 weeks after pharyngitis. Caused by certain strains of Group A beta-haemolytic streptococci (e.g. following impetigo and scabies).
Epidemiology
- 1.06 Acute rheumatic fever and rheumatic heart disease - AIHW Indigenous HPF
- RHD is a disease of disadvantage that is both preventable and treatable.
- First Nations people in Australia have one of the highest recorded rates of ARF and RHD in the world (119 per 100,000), with incidence rates increasing (50% increase 2012-2021)
- First Nations people accounted for 92% of the total number of ARF cases in Australia recorded over the 5-year period 2017–2021
- Otherwise rare disease in Western world, common in Indian subcontinent, Middle East, some Caribbean islands.
Aetiology49
- Group A streptococci
- RHD: repeated episodes of RF
- Autoimmune reaction: antibodies produced to fight streptococci cross react with enzymes of the heart
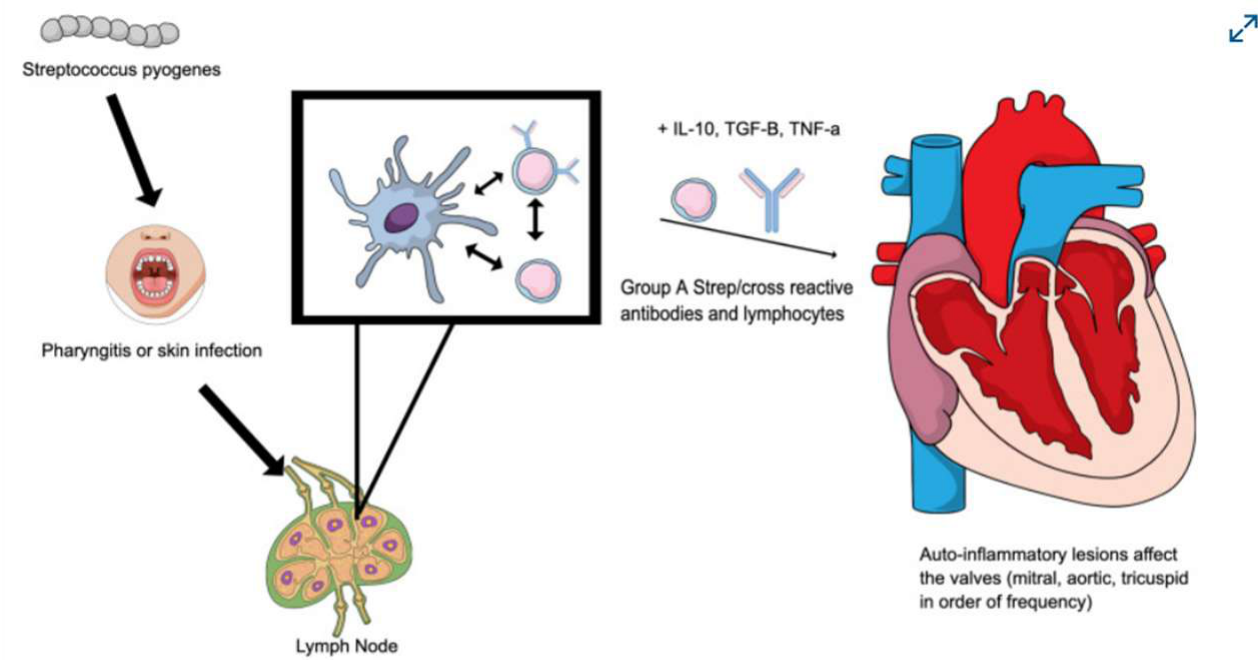
Pathogenesis
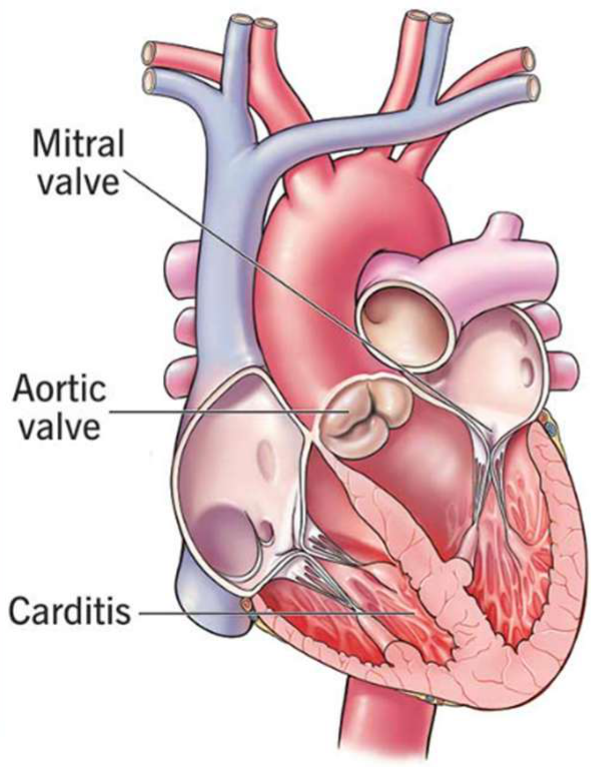
Streptococcus pyogenes → pharyngitis or skin infection → lymph node (+ IL-10, TGF-β, TNF-α) → Group A Strep/cross reactive antibodies and lymphocytes → auto-inflammatory lesions affect the valves (mitral, aortic, tricuspid in order of frequency)
Lecturer — Rheumatic Carditis
All layers of the heart may potentially be affected, producing rheumatic carditis.
- Vasculitis and inflammatory lesions may also involve the joints, skin and nervous system.
- Subendocardial inflammation occurs along valve closure lines, especially at the mitral and aortic valves.
- Minute fibrinous vegetations may form, and subsequent scarring, stiffening and distortion can cause permanent valve damage.
- Turbulent blood flow through damaged valves increases susceptibility to infective endocarditis.
Simpson MT, et al. Rheumatic Heart Disease in the Developing World. Structural Heart. 2023; 7(6): 100219
General Manifestations50
- Acute Rheumatic Fever
- Subacute/chronic Rheumatic Fever
 |  |
Acute Rheumatic Fever
- Etiology: previous GAS pharyngitis/tonsillitis without antibiotic treatment
- Peak incidence: 5–15 years of age
- Diagnosis: evidence of a previous GAS infection (e.g., throat culture, rapid antigen detection test, antistreptolysin O, antistreptococcal DNase B test); Revised Jones criteria
- Treatment: antibiotic treatment of underlying GAS infection; symptomatic treatment of arthritis and fever
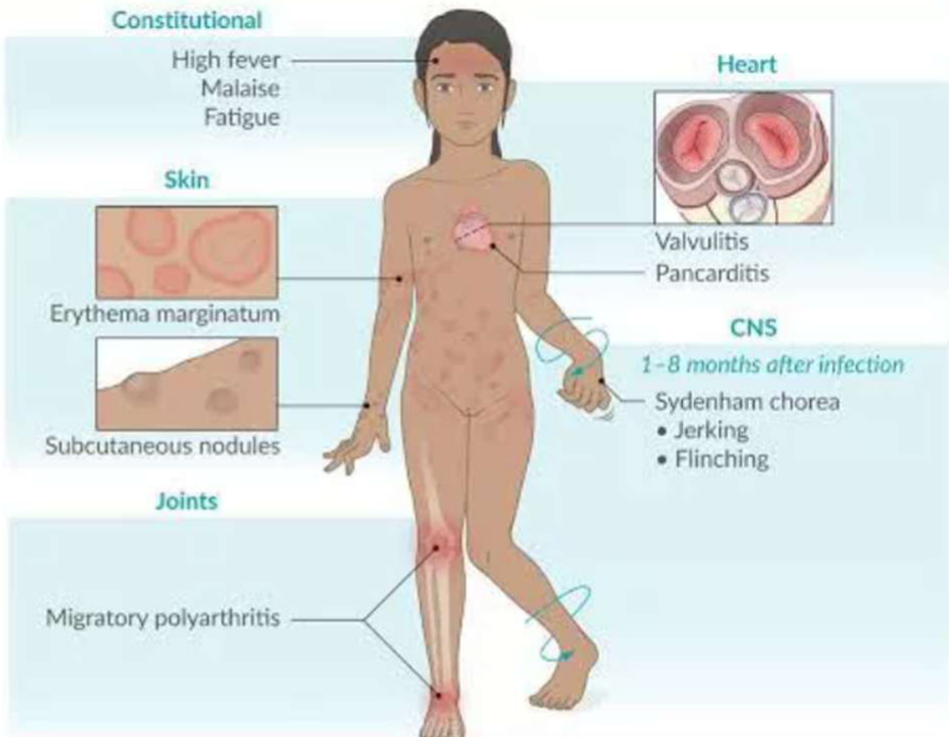
Clinical Features
- Constitutional: high fever, malaise, fatigue
- Skin: erythema marginatum, subcutaneous nodules
- Joints: migratory polyarthritis
- Heart: valvulitis, pancarditis
- CNS: 1–8 months after infection — Sydenham chorea, jerking, flinching
Untreated GAS pharyngitis/tonsillitis → acute infection → development of antibodies → molecular mimicry → Type II hypersensitivity reaction → latent period (2–4 weeks) → inflammation and cell damage → rheumatic fever onset
- Rheumatic Heart Disease
- Valvular damage → regurgitation, stenosis → IE risk
- Early heart disease: heart murmur
- Late effects: heart enlargement, cardiac failure
- Other:
- Shortness of breath
- Chest pain
- Fatigue
- Swollen legs and feet
Mitral valve, aortic valve — carditis
Diagnosis51
- Physical examination
- History collection
- Echocardiogram
- Electrocardiogram
- Blood tests
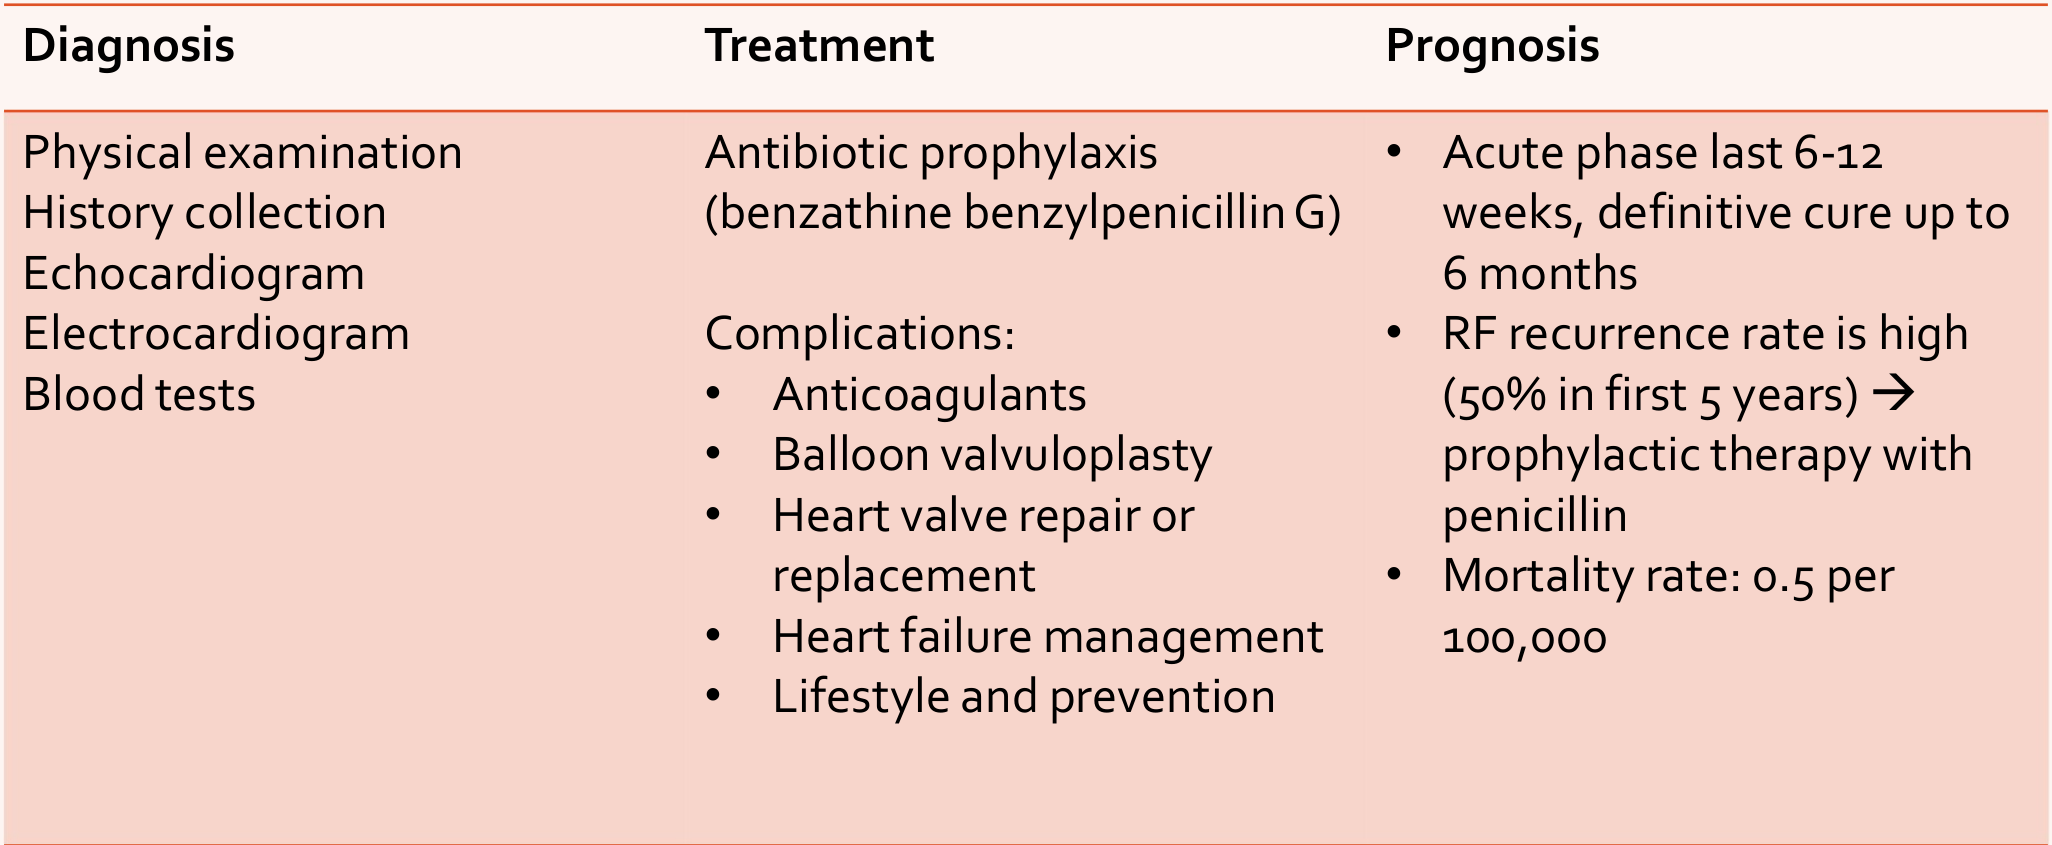
Treatment
- Antibiotic prophylaxis (benzathine benzylpenicillin G)
- Complications:
- Anticoagulants
- Balloon valvuloplasty
- Heart valve repair or replacement
- Heart failure management
- Lifestyle and prevention
Prognosis
- Acute phase lasts 6-12 weeks, definitive cure up to 6 months
- RF recurrence rate is high (50% in first 5 years) → prophylactic therapy with penicillin
- Mortality rate: 0.5 per 100,000
Infective Endocarditis
Definition52
A rare, but dangerous, infection of the endocardial surface of the heart. Predominantly affects one or more heart valves, especially where there is turbulent blood flow because of valve damage (typically left sided valves).
Epidemiology
- Relatively uncommon illness with high morbidity and mortality
- 2010: Australian incidence 4.7 cases per 100 000 person-years
- In-hospital mortality variable – increases with age (up to 15% in 80-89 yos)
Aetiology53
- Endothelial sites with turbulent blood flow
- → Platelet and fibrin deposits accumulate (non-thrombotic endocarditis)
- → sterile “vegetations” produced
- → can be readily infected if a subsequent bacteraemia occurs
Causative Organisms
- Streptococci viridans (oral) 50-60%
- Enterococci (faecal strep) 10%
- Staphylococci (skin) 20-30%
- Others 10% (Gram negative bacilli – mainly HACEK group, fungi)
Association with Dentistry54
- Dental procedures involving bleeding can initiate a bacteraemia that may lead to endocarditis (usually transient and <15min, but occasionally up to 1 hour)
- Most common types of bacteraemia in IE:
- S mutans and S sanguis (both Strep viridans) from dental plaque [40% of IE causative organisms due to complex attachment mechanisms enabling them to adhere to endocardium]
- Gram negative bacilli (HACEK group, including AA) occasionally implicated
- Chance of dental extraction causing IE in patient with valvular disease may be as low as 1 in 3000, therefore bacteraemia not synonymous with IE (or would need antibiotic cover for brushing).
Dental treatment is not the only source of IE-bacteraemia → susceptible surface + high circulating bacterial loads
Lecturer — Bacteraemia and Risk
Healthy ambulant patients do not generally develop infective endocarditis merely because bacteraemia occurs.
- The condition may occur in edentulous patients, demonstrating that dentistry is not the only source.
- Risk depends on a susceptible surface, such as damaged endocardium, together with a high bacterial load in the circulation.
Risk Groups55
- High risk of IE: previous IE, prosthetic heart valves or valves repaired with prosthetic material, unrepaired cyanotic congenital heart disease, or some repaired congenital heart defects (up to 6 months after the procedure or lifelong if residual shunt or valvular regurgitation remains), +/- cardiac transplantation with cardiac valvulopathy.
- Moderate risk: previous rheumatic fever, heart murmur, or evidence of native valve disease.
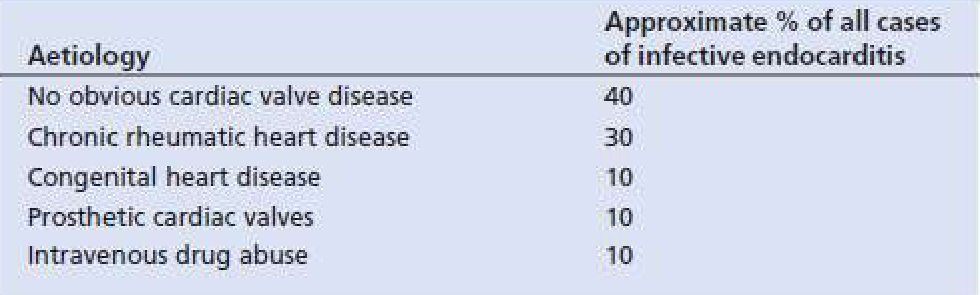
Table 5.32 Main groups affected by infective endocarditis
| Aetiology | Approximate % of all cases of infective endocarditis |
|---|---|
| No obvious cardiac valve disease | 40 |
| Chronic rheumatic heart disease | 30 |
| Congenital heart disease | 10 |
| Prosthetic cardiac valves | 10 |
| Intravenous drug abuse | 10 |
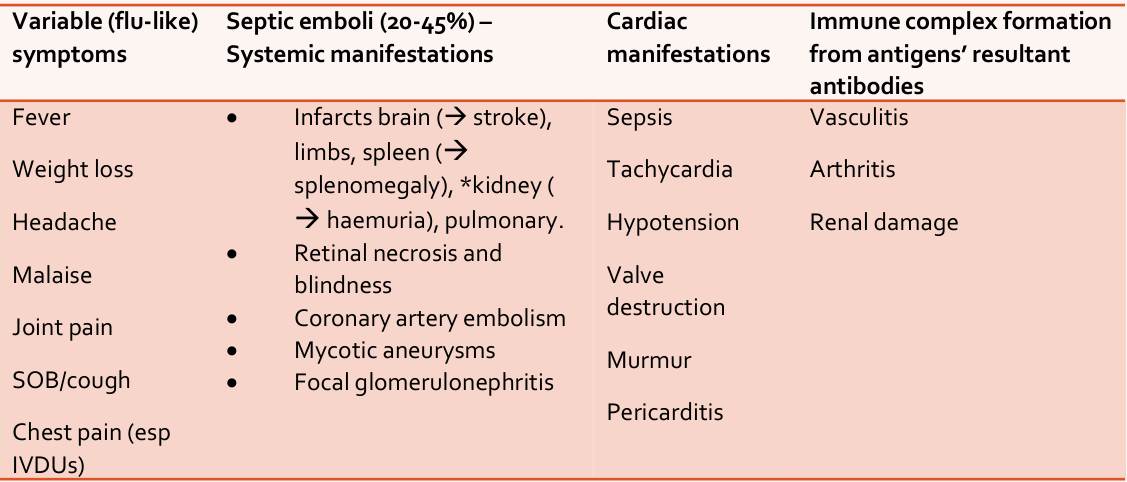
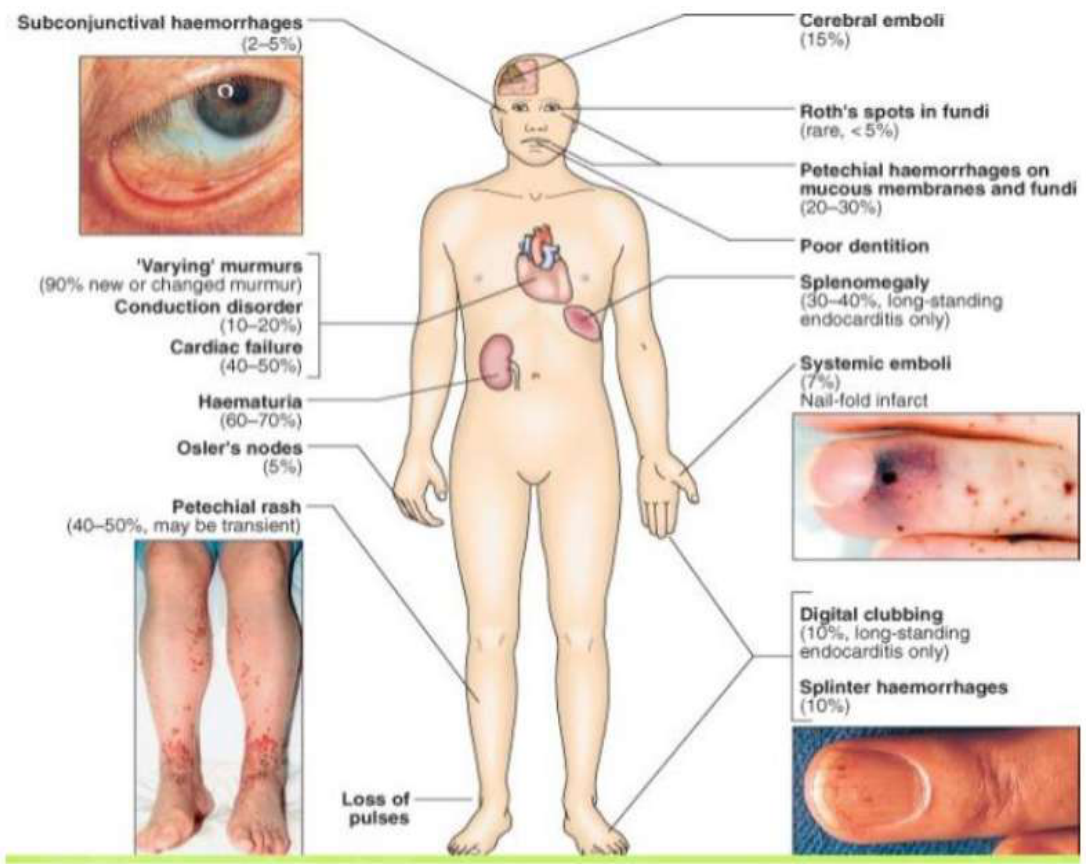
General Manifestations56
| Variable (flu-like) symptoms | Septic emboli (20-45%) – systemic manifestations | Cardiac manifestations | Immune complex formation from antigens’ resultant antibodies |
|---|---|---|---|
| Fever | Infarcts brain (→ stroke), limbs, spleen (→ splenomegaly), kidney (→ haematuria), pulmonary | Sepsis | Vasculitis |
| Weight loss | Retinal necrosis and blindness | Tachycardia | Arthritis |
| Headache | Coronary artery embolism | Hypotension | Renal damage |
| Malaise | Mycotic aneurysms | Valve destruction | |
| Joint pain | Focal glomerulonephritis | Murmur | |
| SOB/cough | Pericarditis | ||
| Chest pain (esp IVDUs) |
Common signs: 90% fever, 85% heart murmurs
 |  |
General Management57
| Treatment | Prognosis |
|---|---|
| Hospital admission for early treatment | 15-20% die during initial hospital admission; further 10-15% die over the following year |
| Antibiotic therapy | 40-45% require surgery during initial hospital admission; further 10% require surgery within 1 yr post-discharge |
| Severe cases: valve replacement | Good prognostic factors: young, penicillin-sensitive isolates, early tx |
Lecturer — Endocarditis Antibiotics
Antibiotic choice is determined by the bacteriological findings and consultation with a microbiologist.
- Penicillin with gentamicin may be used for two weeks when streptococci are the main causative organisms.
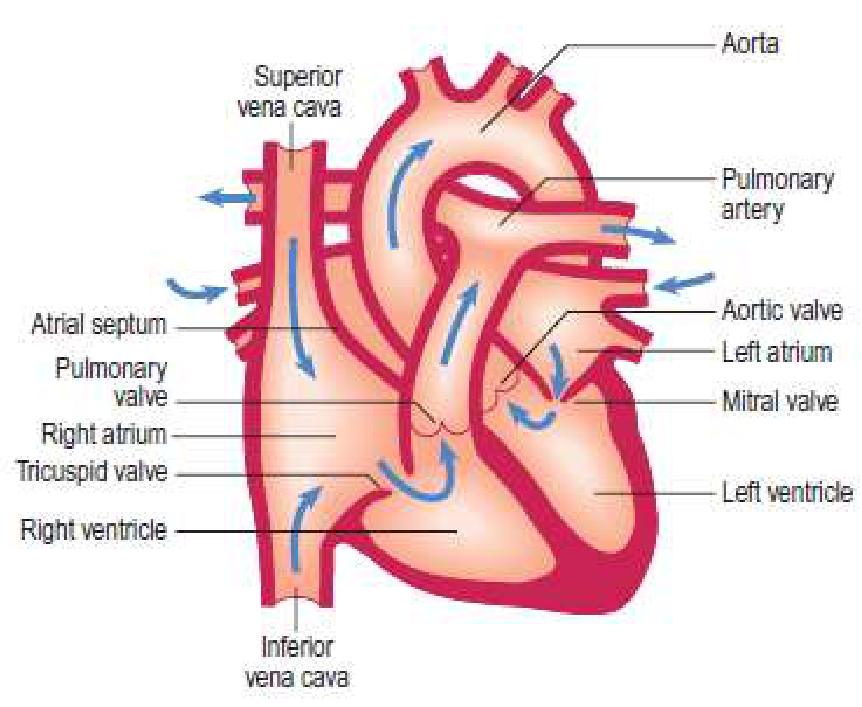
Aortic and Mitral Valve Disease58
-
Aortic stenosis: narrowing of the aortic valve; this generates an increased pressure in the left ventricle to maintain the blood volume per beat
-
Aortic regurgitation: blood propelled to the aorta during systole returns to the left ventricle during diastole due to a defective aortic valve
-
Mitral valve stenosis: narrowing of the mitral valve that generates an increasing pressure in the left atrium of the heart
-
Mitral valve regurgitation: the blood propulsed to the left ventricle during systolic contraction returns into the left atrium during diastolic dilatation due to a valve closure defect
-
Mitral valve prolapse: protrusion of the valves into the left atrium during systole. May exist in isolation, but sometimes associated with mitral regurgitation. May be associated with atrial septal defect, patent ductus arteriosus.
-
Valve disease does not automatically indicate antibiotic prophylaxis; assess the patient’s specific risk factors using the relevant guidelines.
→ DO NOT REQUIRE ANTIBIOTIC PROPHYLAXIS
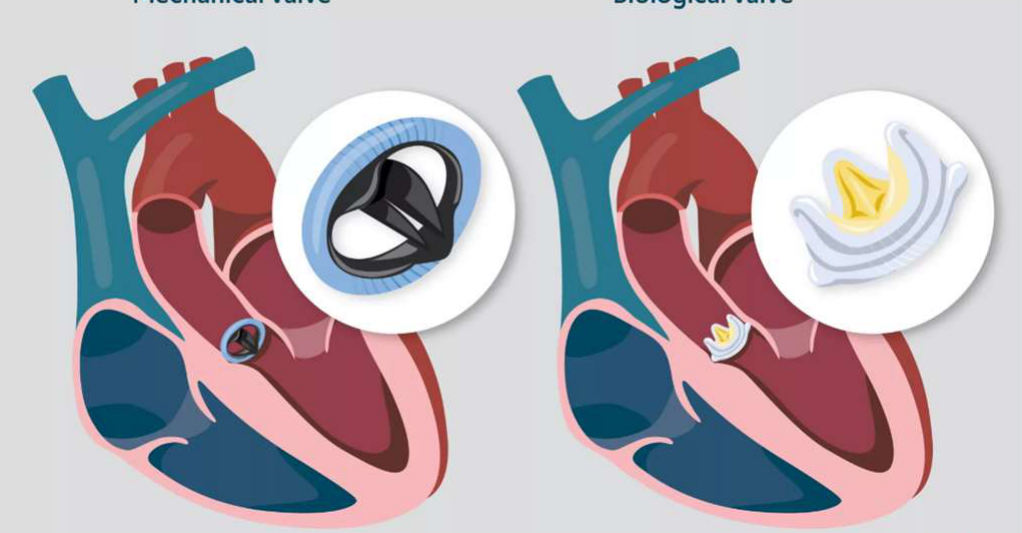
Valve Replacement59
-
Tissue valve
- Material: porcine, bovine, human
- Lifespan = 10-20 years
- Usually for older patients
- No turbulence = no anticoagulation required
- Unless required for other reason e.g. AF, DVT
- No noise
-
Mechanical valve
- Material: carbon, titanium
- Lifespan = highly durable, can last lifetime (30+ years)
- Usually for younger patients
- Turbulence = anticoagulation required
- Noisy
Lecturer — Valve Selection
Valve replacement may be considered when medication does not adequately relieve symptoms.
- Indications may include improving quality of life and the ability to exercise.
- The choice of valve balances durability, medical options and risks.
- Patients already taking warfarin for atrial fibrillation or deep vein thrombosis may be considered for a mechanical valve.
Valvular Heart Disease Dental Management
Risk Assessment60
Valvular Heart Disease Risk Assessment
- Bacteraemia to heart valves
- Oral hygiene
- Timing to perform dental treatment
- Anticoagulation
- Oral side effects of diuretics (e.g., furosemide), ACE inhibitors, and beta-blockers
- GA/sedation risks: myocarditis
- Concurrent antibiotic therapy
Valvular Heart Disease Dental Care
Access61
- Postpone elective dental care 6 months after episode of RF
- Elective dental care may need to be postponed for six months after infective endocarditis or valve surgery as well as rheumatic fever.
- RHD → IE or valve surgery = urgent management of dental infections (bacteraemia)
- May be hospital in-patient setting
- IVDUs: less reliable attendance unless in pain
Capacity/Consent
- Nil significant
Lecturer — Consent and Capacity
Consider the patient’s ability to consent and tolerate treatment.
- The dental treatment plan should account for the urgency of the cardiac condition and the extent of treatment required.
Education/Prevention
- Good oral hygiene most important factor in reducing risk in susceptible individuals
- Preventive measures to avoid caries and periodontal disease
- OHI for home maintenance, regular dental attendance, diet, etc
- Patient educated to alert dental providers of RHD/IE history, and need for antibiotic prophylaxis
Surgery62
-
Antibiotic prophylaxis (see lecture Antibiotic Prophylaxis and Dentistry)
- Liaise with Infectious Diseases physician if on concurrent antibiotics
-
Consult with physician re: anticoagulation (see lecture Bleeding Disorders and Dentistry)
-
LA: use adrenaline with caution, aspirating syringe (IV injection may precipitate arrhythmias)
-
Conscious sedation / GA: avoid when acute RF (myocarditis), hospital environment if required
-
Patients awaiting urgent valve surgery may require multiple extractions over a short period to become dentally fit.
Spread of Infection
- Infective endocarditis bacteraemia (antibiotic prophylaxis)
- Possible antibiotic resistance issues
Antibiotic Prophylaxis
Table 2.5 Indications for antibiotic prophylaxis for endocarditis63
Antibiotic prophylaxis against infective endocarditis is recommended only for people who meet both of the following criteria:
- are undergoing a procedure associated with a high risk of a bacteraemia and subsequent infective endocarditis
- have a cardiac condition associated with an increased risk of developing infective endocarditis and the highest risk of adverse outcomes from endocarditis.
Procedures for which endocarditis prophylaxis is recommended for patients with a cardiac condition listed below [NB1]
- Dental procedures – only those involving manipulation of the gingival or periapical tissue or perforation of the oral mucosa (eg dental extractions, implant placement, biopsy, removal of soft tissue or bone, subgingival debridement, replanting avulsed teeth) [NB2] [NB3] [12] [33] [44].
NB1: Endocarditis prophylaxis is not recommended for procedures other than those covered in this topic. However, surgical prophylaxis may be indicated even if endocarditis prophylaxis is not – see Surgical antibiotic prophylaxis recommendations for specific procedures.
NB2: For a list of dental procedures classified by invasiveness and their indications for endocarditis prophylaxis, see Table 13.29.
NB3: Evidence on the risk of bacteraemia and subsequent infective endocarditis following supragingival debridement is conflicting. Pending further evidence, endocarditis prophylaxis is only recommended for supragingival debridement that involves manipulation of the gingival tissue [49] [50].
Cardiac conditions for which endocarditis prophylaxis is recommended for patients undergoing a procedure listed above [NB5] [NB6] [12] [48] [56]
- prosthetic cardiac valve, including transcatheter-implanted prosthesis or homograft
- prosthetic material used for cardiac valve repair, such as annuloplasty rings and chords
- previous infective endocarditis
- ventricular assist devices [36] [56]
- congenital heart disease but only if it involves:
- unrepaired cyanotic defects, including palliative shunts and conduits
- repaired defects with residual defects at or adjacent to the site of a prosthetic patch or device (which inhibit endothelialisation) [33] [48]
- rheumatic heart disease [NB7].
NB5: Endocarditis prophylaxis is not recommended for patients with forms of valvular or structural heart disease not listed in this table, including patients with mitral valve prolapse, septal defects or cardiac implantable electronic devices.
NB6: Patients with a heart transplant who have developed cardiac valvulopathy may also be at high risk of adverse outcomes from endocarditis; consult the patient’s cardiologist for specific recommendations.
NB7: Endocarditis prophylaxis was previously only recommended for rheumatic heart disease in Aboriginal and Torres Strait Islander peoples, or considered for people with rheumatic heart disease at significant socioeconomic disadvantage. However, studies have demonstrated that rheumatic heart disease is an independent risk factor for the development of and adverse outcomes from infective endocarditis [1] [3] [20].
Lecturer — Guideline Changes
Therapeutic Guidelines have changed across versions in relation to rheumatic heart disease.
- Rheumatic heart disease was omitted in one previous version.
- Rheumatic heart disease in First Nations and lower socioeconomic populations was included in a later version.
- Version 4 included rheumatic heart disease again.
- Intravenous drug use alone is not an indication for prophylaxis; the relevant cardiac or valvular condition must also be present.
- A pacemaker or implantable defibrillator alone is not an indication for surgical antibiotic prophylaxis.
Therapeutic Guidelines / Antibiotic / Infective endocarditis / Prevention of infective endocarditis [accessed July 2026]
Electrical Dysrhythmias64
- Extrasystoles (ectopics)
- Tachycardia (including Atrial fibrillation)
- Bradycardias
Dysrhythmias Overview65
-
Definition: An alteration in the normal rhythm of the heartbeat.
-
Epidemiology: 15% of the population
-
Aetiology: disorders in heart automaticity (impulse formation) or conductivity (block or delay)
-
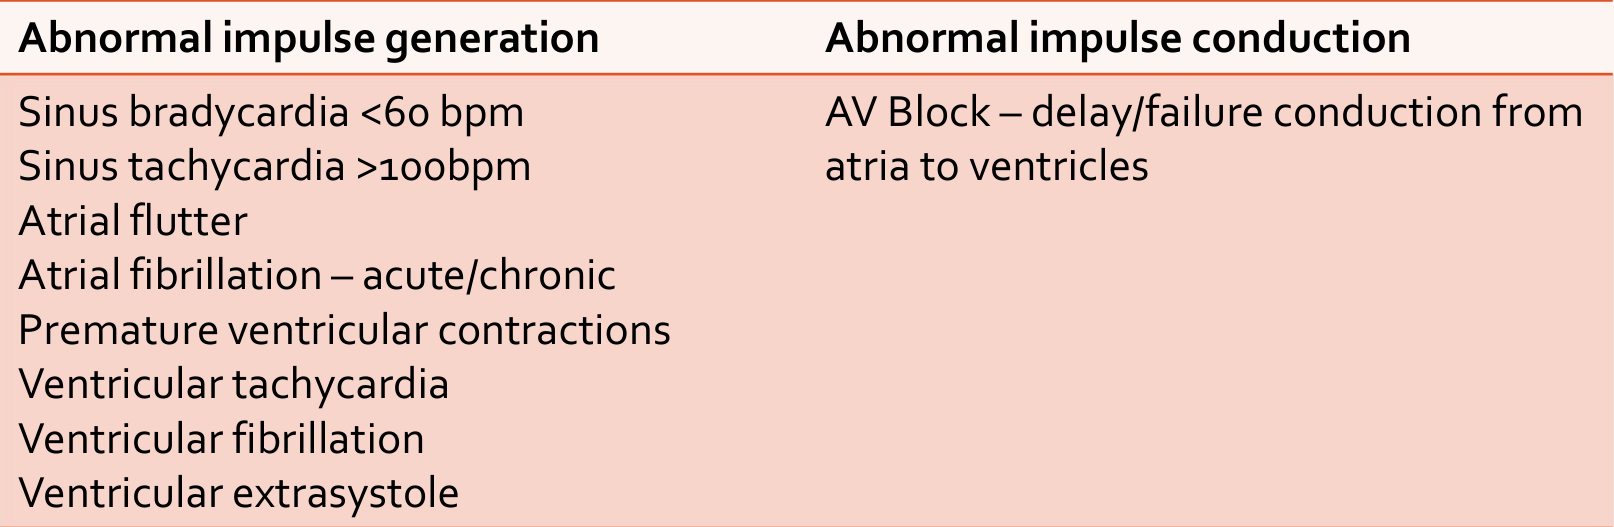
Atrial fibrillation is the most common arrhythmia and affects approximately 1% of the general population. | Abnormal impulse generation | Abnormal impulse conduction | | :--- | :--- | | Sinus bradycardia <60 bpm | AV Block – delay/failure conduction from atria to ventricles | | Sinus tachycardia >100 bpm | | | Atrial flutter | | | Atrial fibrillation – acute/chronic | | | Premature ventricular contractions | | | Ventricular tachycardia | | | Ventricular fibrillation | | | Ventricular extrasystole | |
Dysrhythmias Aetiology66
- Cardiac disease
- Drugs: caffeine, alcohol, smoking, β-2-agonists, digoxin, dopamine, tricyclics, tobacco
- Metabolic changes: catecholamines, autonomic/endocrine disease, hyperthyroidism, fever, hypoxia, surgery, persistent vegetative neurological states
- Electrolyte imbalance: e.g. secondary to CKD
- Respiratory: COPD
Lecturer — Hyperthyroidism
Hyperthyroidism may cause dysrhythmias, and treating the thyroid disease may correct the cardiac problem.
Dysrhythmias General Manifestations
Signs/Symptoms67
- Most frequent symptom: palpitations.
- Others: sickness, syncope, dyspnoea, anxiety, fatigue, chest pain, dizziness.
- May have no symptoms.
Classification
-
Rate:
- Tachycardia (fast rate >100 bpm)
- Bradycardia (slow rate <60 bpm day, <50 bpm night)
- Irregular
-
Mechanism: automaticity, re-entry, fibrillation
-
Origin: atrium, ventricle
-
Students are not expected to memorise every type, but should recognise the terms and understand that they may affect dental management.
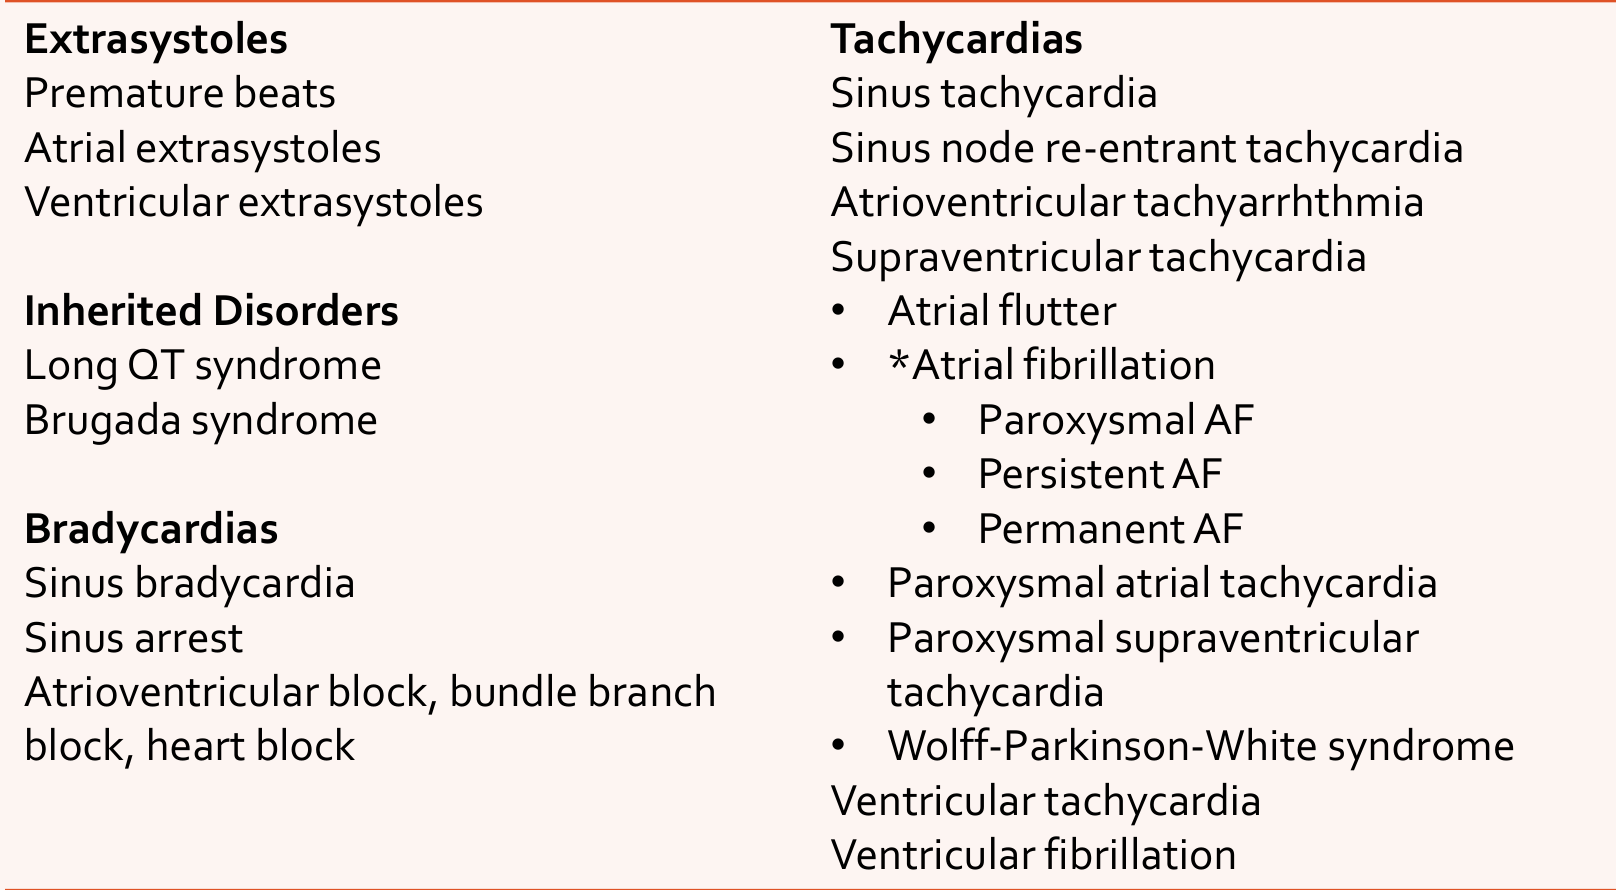
Types of Arrhythmias68
| Extrasystoles | Tachycardias |
|---|---|
| Premature beats | Sinus tachycardia |
| Atrial extrasystoles | Sinus node re-entrant tachycardia |
| Ventricular extrasystoles | Atrioventricular tachyarrhythmia |
| Supraventricular tachycardia | |
| • Atrial flutter | |
| • Atrial fibrillation | |
| • Paroxysmal AF | |
| • Persistent AF | |
| • Permanent AF | |
| • Paroxysmal atrial tachycardia | |
| • Paroxysmal supraventricular tachycardia | |
| • Wolff-Parkinson-White syndrome | |
| Ventricular tachycardia | |
| Ventricular fibrillation | |
| Inherited Disorders | |
| Long QT syndrome | |
| Brugada syndrome | |
| Bradycardias | |
| Sinus bradycardia | |
| Sinus arrest | |
| Atrioventricular block, bundle branch block, heart block |
Dysrhythmias General Management69
| Identify cause | If no underlying cause | Treatments |
|---|---|---|
| May only need treatment for this | Treatment depends on type/severity of arrhythmia. Focus: controlling RATE and RHYTHM | Medications Pharmacological cardioversion Electric cardioversion Pacemaking / Defibrillation Surgery |
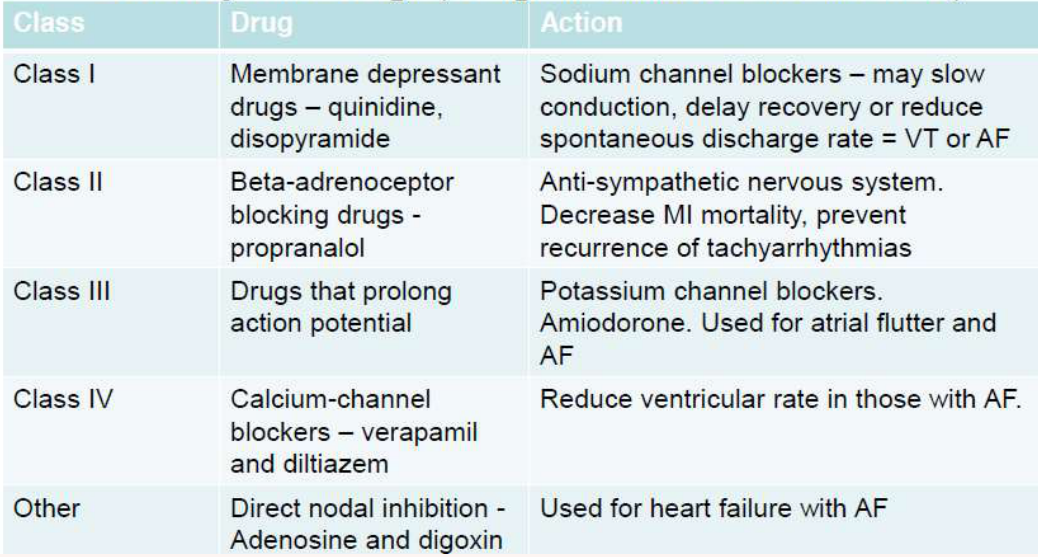
Medications70
- Control abnormal heart rhythm: anti-arrhythmic drugs (Vaughan Williams Classification)
- Treat related hypertension/CAD/heart failure: adenosine, digoxin
- Reduce stroke risk: DOACs
| Class | Drug | Action |
|---|---|---|
| Class I | Membrane depressant drugs – quinidine, disopyramide | Sodium channel blockers – may slow conduction, delay recovery or reduce spontaneous discharge rate = VT or AF |
| Class II | Beta-adrenoceptor blocking drugs – propranolol | Anti-sympathetic nervous system. Decrease MI mortality, prevent recurrence of tachyarrhythmias |
| Class III | Drugs that prolong action potential | Potassium channel blockers. Amiodarone. Used for atrial flutter and AF |
| Class IV | Calcium-channel blockers – verapamil and diltiazem | Reduce ventricular rate in those with AF |
| Other | Direct nodal inhibition – adenosine and digoxin | Used for heart failure with AF |
Cardioversion71
-
Restores regular rhythm
-
Pharmacological (chemical) cardioversion
-
Electrical cardioversion
-
Electrical cardioversion uses electrical shocks when medication is ineffective.
Cardiovascular Implantable Electronic Devices (CIEDs)
- Permanent pacemakers
- External cardiac defibrillators
- Ventricular assistive devices (VAD)
- Implantable Cardioverter Defibrillator (ICD)
Lecturer — Device Activation
Implantable cardioverter defibrillators may activate without significant warning.
- Activation may cause the patient to flinch, bite down or move suddenly.
- Some devices may cause loss of consciousness when activated, although this is less likely with newer devices.
Radiofrequency Ablation (Catheter Ablation)
Lecturer — Radiofrequency Ablation
Radiofrequency ablation uses radiofrequency energy to destroy cardiac tissue producing abnormal electrical signals. It may be used when medication is ineffective or cannot be tolerated.
Dysrhythmias Dental Manifestations
Anti-arrhythmic Drugs72
- Gingival swelling = verapamil/diltiazem (Ca-channel blockers), enalapril (ACE inhibitor)
- Lichenoid ulceration and oral ulceration related to agranulocytosis = some β-blockers
- Lupus-like reaction and mucosal ulcers due to agranulocytosis = procainamide
- Xerostomia = disopyramide
Dysrhythmias Risk Assessment73
-
Anticoagulation (see Bleeding Disorders lecture)
-
Oral side effects of drugs (see Hypertension section)
-
CIED interference
-
Assess the risk of sudden device activation and whether the patient may be injured by sudden movement.
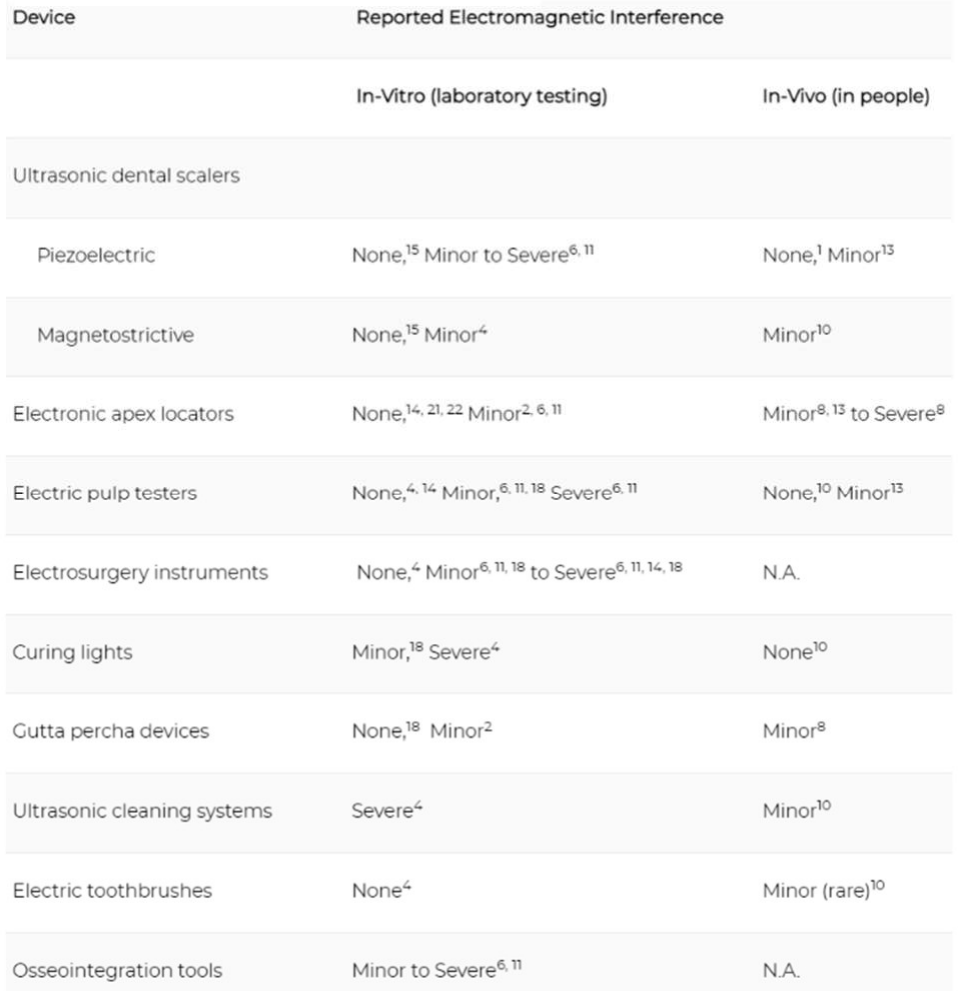
Cardiac Implantable Electronic Devices7475
- Patients with CIED can undergo most general dental treatment.
- Surgical diathermy can interfere with some CIEDs (especially monopolar).
- With modern CIEDs, interference from most other dental electronic and ultrasonic devices is usually not clinically significant.
- Consult cardiologist if in doubt.
- CIED is not an indication for surgical nor IE antibiotic prophylaxis.
- LVADs increase risk of thrombotic events ∴ increased risk of post-op bleeding.
- Patients may be on antithrombotics.
- LVAD-induced blood pressure changes.
Further info on interference (American Dental Association): https://www.ada.org/resources/ada-library/oral-health-topics/cardiac-implanted-devices-and-electronic-dental-instruments
| Device | Reported Electromagnetic Interference: In-Vitro (laboratory testing) | Reported Electromagnetic Interference: In-Vivo (in people) |
|---|---|---|
| Ultrasonic dental scalers | ||
| Piezoelectric | None,¹³ Minor to Severe⁶, ¹¹ | None,¹ Minor¹³ |
| Magnetostrictive | None,¹⁵ Minor⁴ | Minor¹⁰ |
| Electronic apex locators | None,¹⁴, ²¹, ²² Minor², ⁶, ¹¹ | Minor⁸, ¹³ to Severe⁸ |
| Electric pulp testers | None,⁶, ¹⁴ Minor,⁶, ¹¹, ¹⁸ Severe⁶, ¹¹ | None,¹⁰ Minor¹³ |
| Electrosurgery instruments | None,⁴ Minor⁶, ¹¹, ¹⁸ to Severe⁶, ¹¹, ¹⁴, ¹⁸ | N.A. |
| Curing lights | Minor,¹⁸ Severe⁴ | None¹⁰ |
| Gutta percha devices | None,¹⁸ Minor² | Minor⁸ |
| Ultrasonic cleaning systems | Severe⁴ | Minor¹⁰ |
| Electric toothbrushes | None⁴ | Minor (rare)¹⁰ |
| Osseointegration tools | Minor to Severe⁶, ¹¹ | N.A. |
“Minor” refers to non-clinically significant interference (noise, telemetry); “Severe,” to clinically significant outcomes (i.e., pacing disturbances or shock); “N.A.” (Not Applicable), no studies available.
Dysrhythmias Dental Management
Access76
- Peak endogenous epinephrine levels in early morning → ideally appointments late morning or early afternoon
- High risk patients – treated in hospital
Education/Prevention
- Oral side effects of medication
Surgery
- Liaise with cardiologist if concerned about CIED interference
- Pre-operative: anxiety management, check INR if warfarinated, defibrillator readily available
- Peri-operative:
- Positioning: supine if pacemaker
- LA: adequate provision, judicious use of vasoconstrictor, avoid intravenous injection
- Sedation: oxygen saturation monitoring, may be helpful to minimise stress
- Post-operative: haemostasis if anticoagulated
Lecturer — Anticoagulant Choice
Many patients now take a direct oral anticoagulant rather than warfarin.
Muscular Cardiomyopathies77
- Primary – genetic/inherited, acquired
- Secondary
Cardiomyopathies Definition and Aetiology
Definition: broad term for diseases of the heart muscle that result in reduced ability for the heart to pump blood to the rest of the body.
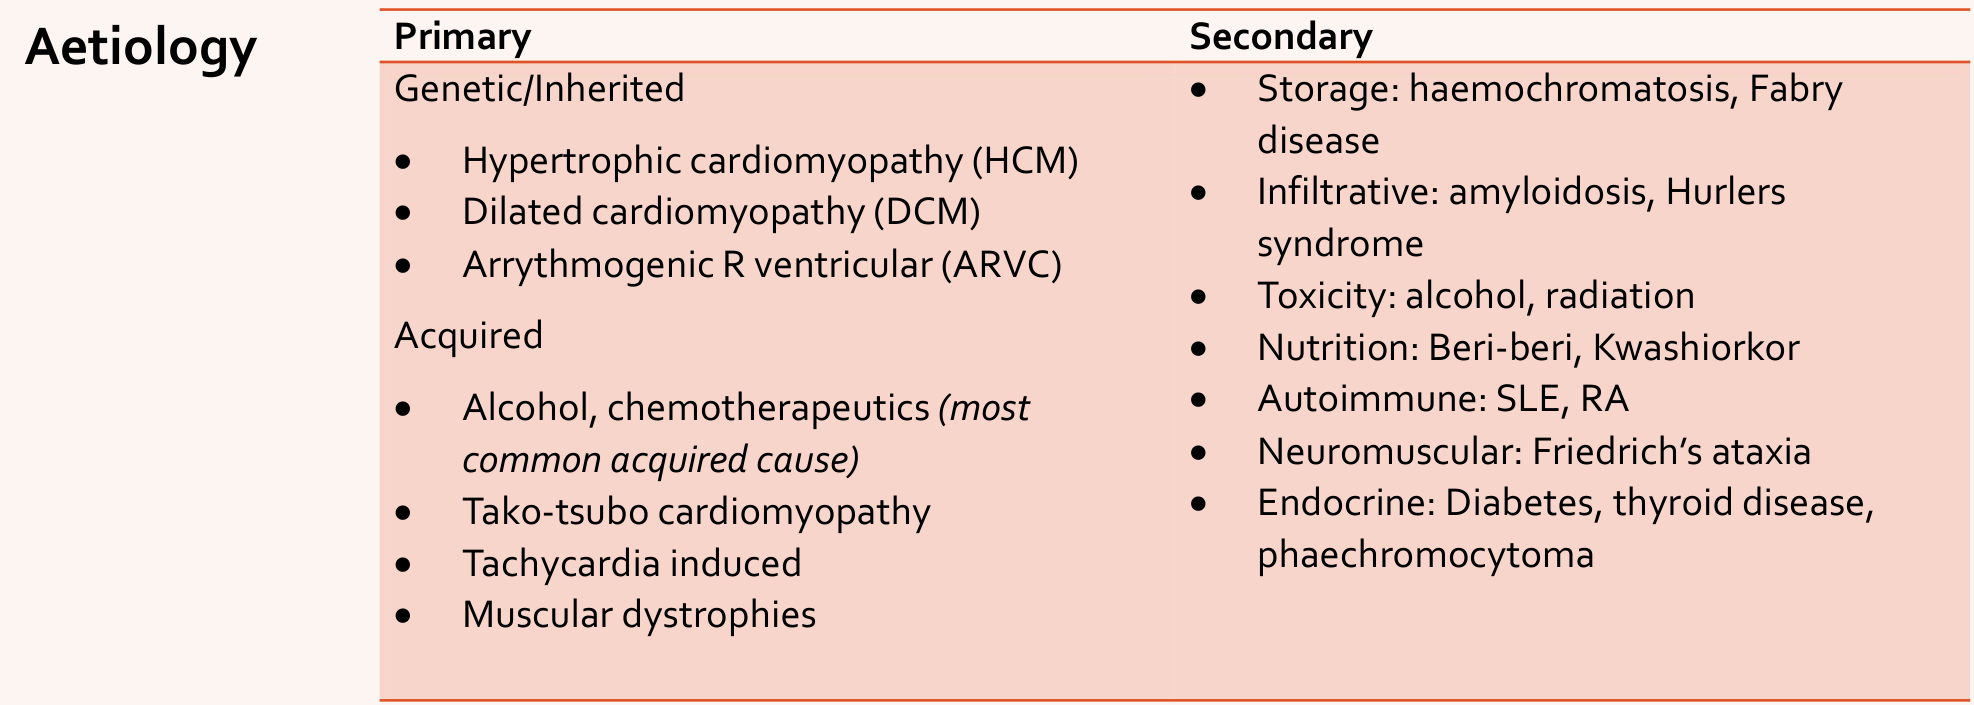
Aetiology78
Primary
- Genetic/Inherited
- Hypertrophic cardiomyopathy (HCM)
- Dilated cardiomyopathy (DCM)
- Arrythmogenic R ventricular (ARVC)
- Acquired
- Alcohol, chemotherapeutics (most common acquired cause)
- Tako-tsubo cardiomyopathy
- Tachycardia induced
- Muscular dystrophies
Secondary
- Storage: haemochromatosis, Fabry disease
- Infiltrative: amyloidosis, Hurlers syndrome
- Toxicity: alcohol, radiation
- Nutrition: Beri-beri, Kwashiorkor
- Autoimmune: SLE, RA
- Neuromuscular: Friedrich’s ataxia
- Endocrine: Diabetes, thyroid disease, phaeochromocytoma
Cardiomyopathies General Manifestations and Management79
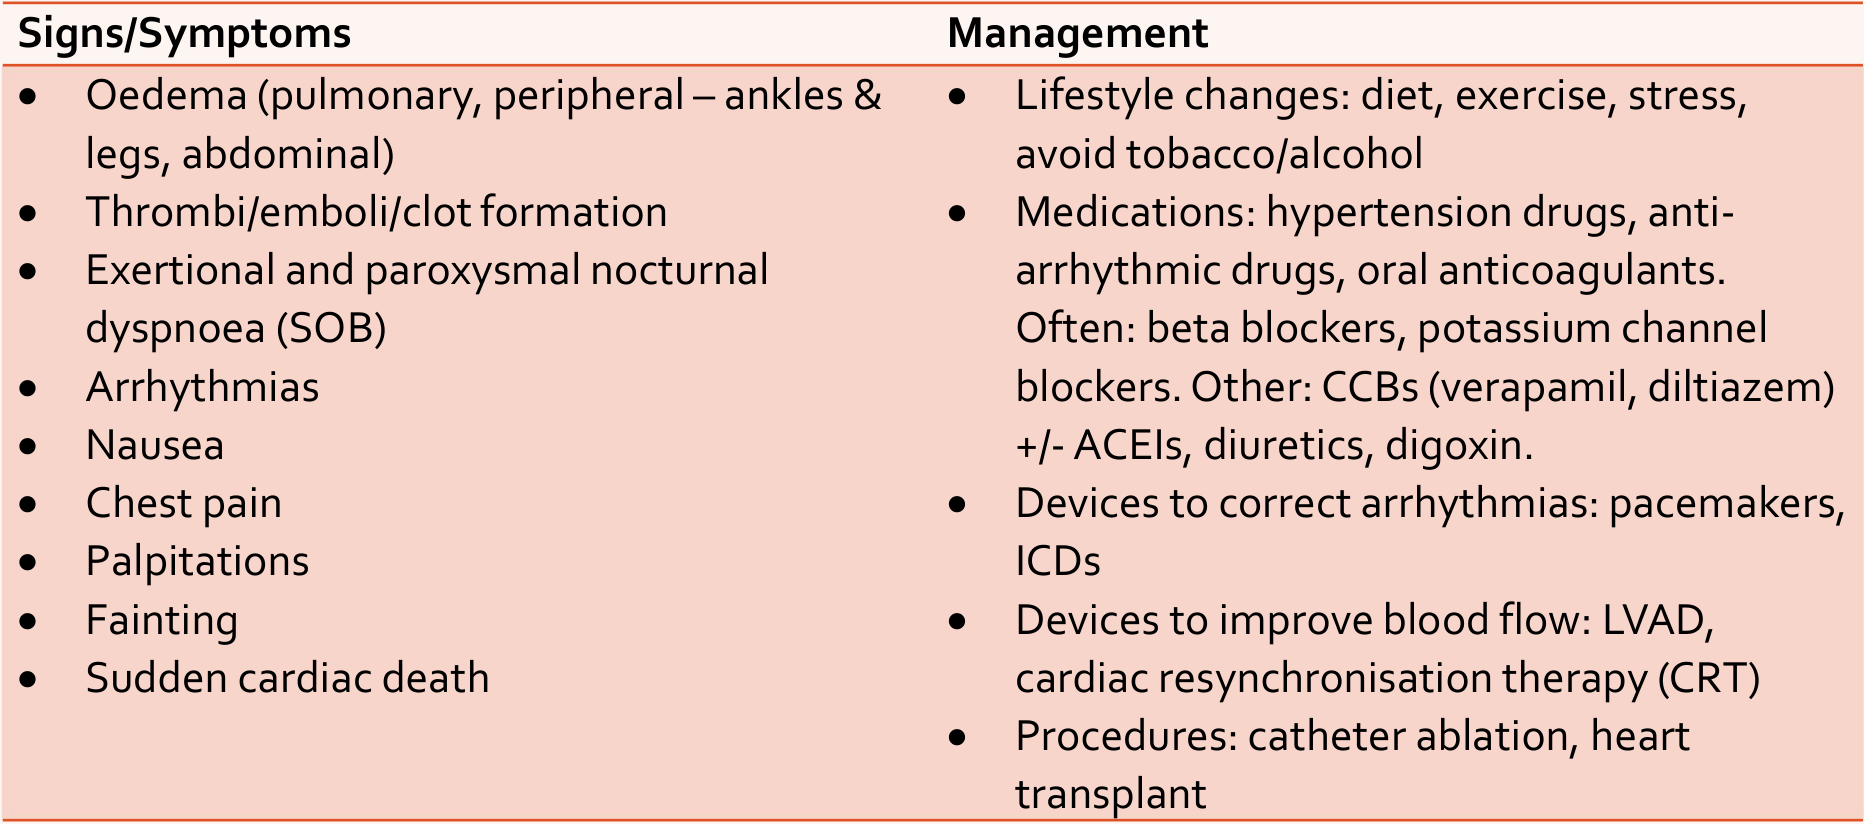
Signs/Symptoms80
-
Oedema (pulmonary, peripheral – ankles & legs, abdominal)
-
Thrombi/emboli/clot formation
-
Exertional and paroxysmal nocturnal dyspnoea (SOB)
-
Arrhythmias
-
Nausea
-
Chest pain
-
Palpitations
-
Fainting
-
Sudden cardiac death
-
Fatigue
Management
- Lifestyle changes: diet, exercise, stress, avoid tobacco/alcohol
- Medications: hypertension drugs, anti-arrhythmic drugs, oral anticoagulants. Often: beta blockers, potassium channel blockers. Other: CCBs (verapamil, diltiazem) +/- ACEIs, diuretics, digoxin.
- Devices to correct arrhythmias: pacemakers, ICDs
- Devices to improve blood flow: LVAD, cardiac resynchronisation therapy (CRT)
- Procedures: catheter ablation, heart transplant
Lecturer — Cardiomyopathy Management
Cardiomyopathy may worsen over time, but treatment can slow progression and improve quality of life.
- Management depends on the underlying cause and associated medical conditions.
- Dental management follows the general cardiovascular risk-assessment and access framework.
Congenital Heart Disease
Congenital Heart Disease Definition and Epidemiology
Definition81
- Any congenital structural defects of the heart (including valve stenosis or septal defects) or adjacent great vessels that lead to malfunction (arrhythmias or flow problems). Can occur alone or in combinations.
Epidemiology
- The most common type of heart problem in children (1% of live births); 20% also have other congenital anomalies.
- Diagnosed in at least 1 in 180 births (1–2% of the population).
Congenital Heart Disease Aetiology
- Often unidentified, multifactorial — genetic and environmental factors.
Acquired Causes82
- Maternal infections (Rubella, Cytomegalovirus)
- Maternal drug use (alcohol, anticonvulsants, lithium, thalidomide, warfarin, other drugs)
- Maternal systemic disease (SLE, diabetes); maternal irradiation (rare)
Genetic Syndromes with Cardiac Defects
-
Chromosomal: Down syndrome, Edwards syndrome, Turner syndrome
-
Hereditary: Ehlers-Danlos syndrome, Marfan syndrome, osteogenesis imperfecta, mucopolysaccharidosis, Holt-Oram syndrome, Noonan syndrome, Williams syndrome
-
Myler syndrome and other vascular or connective tissue disorders may also be associated with cardiac defects.
Congenital Heart Disease General Manifestations
Classification83
- Cyanotic (R to L shunting): shunting deoxygenated blood from the right ventricle into the left side of the heart and the systemic circulation (bypassing the lungs)
- Acyanotic (obstruction, or L to R shunting): blood contains enough oxygen but is pumped abnormally around the body, forcing the heart to work harder
| Cyanotic | Acyanotic, no shunt | Acyanotic with shunt |
|---|---|---|
| Tetralogy of Fallot | Aortic stenosis | Atrial septal defect |
| Eisenmenger syndrome | Bicuspid aortic valve | Patent ductus arteriosus |
| Pulmonary atresia | Coarctation of the aorta | Ventricular septal defect |
| Pulmonary valve stenosis | Dextrocardia | |
| Total anomalous venous drainage | Mitral valve prolapse | |
| Transposition of the great vessels | ||
| Tricuspid atresia |

Complications84
- Arrhythmias
- Infective endocarditis
- Stroke (cerebral abscess)
- Pulmonary hypertension and oedema
- Polycythaemia / bleeding tendency / thrombotic tendency
- Heart failure
Congenital Heart Disease Oral Manifestations8586
- Delayed eruption of both dentitions
- Positional anomalies
- Enamel hypoplasia
- Gross vasodilatations in the pulps
- Cleft palate
- Fissured tongue
- Greater caries and periodontal disease (associated with poor oral hygiene and lack of dental attention)
Lecturer — Oral Disease Burden
Congenital heart disease may affect growth and development, and increased dental disease may have several contributing factors.
- Multiple medical problems can compete with oral care.
- Competing appointments may reduce the priority given to oral hygiene.
- Treatment burnout may further contribute to increased caries and periodontal disease.
Heart Failure
Cardiac Failure Definition and Aetiology
Definition: When structural or functional impairment of the pumping action of the heart leads to blood output insufficient to meet the body’s demands → lack of tissue and organ perfusion.
Aetiology: Any structural or functional cardiac or non-cardiac disorder that impairs ability of heart to respond to physiological demands for CO.
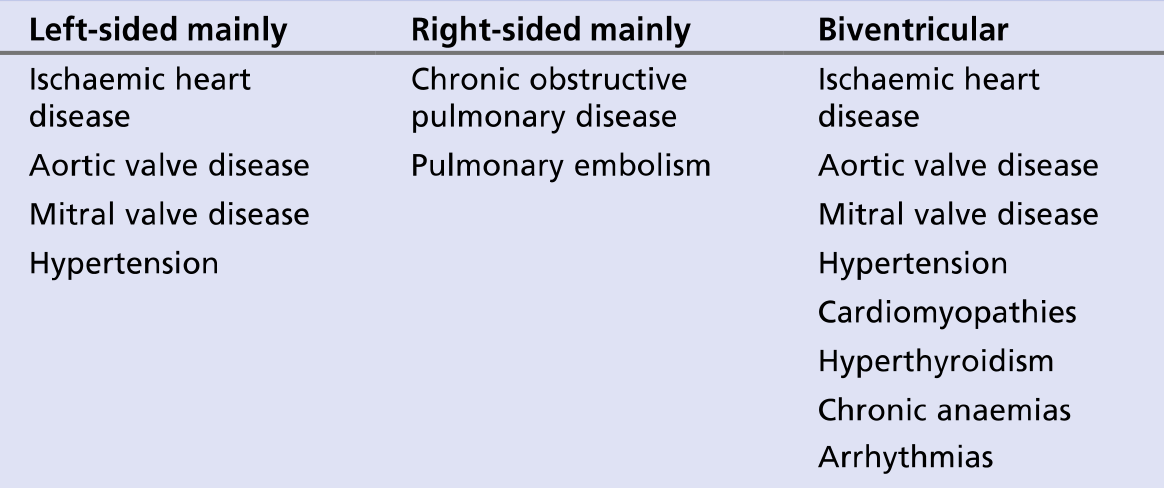
Table 5.34 Main causes of heart failure87
| Left-sided mainly | Right-sided mainly | Biventricular |
|---|---|---|
| Ischaemic heart disease | Chronic obstructive pulmonary disease | Ischaemic heart disease |
| Aortic valve disease | Pulmonary embolism | Aortic valve disease |
| Mitral valve disease | Mitral valve disease | |
| Hypertension | Hypertension | |
| Cardiomyopathies | ||
| Hyperthyroidism | ||
| Chronic anaemias | ||
| Arrhythmias |
- Heart failure may result from the progression or complication of cardiovascular conditions, including ischaemic, valvular, muscular and congenital disease.
Cardiac Failure General Manifestations
Left-sided vs Right-sided Heart Failure88
- Left-sided heart failure: Left side of heart can’t pump blood out of heart so blood backs up into the LUNGS
- Right-sided heart failure: Right side of heart can’t pump received blood to the lungs so blood backs up into the BODY
 |  |
Symptoms
-
Pulmonary congestion:
- Cough
- Crackles
- Pink-tinged sputum
- Tachypnea
-
Tachycardia
-
Fatigue
-
Cyanosis
-
Exertional dyspnea
-
Peripheral edema
-
Ascites
-
Enlarged liver & spleen
-
JVD
-
Weight gain
-
Increased peripheral venous pressure
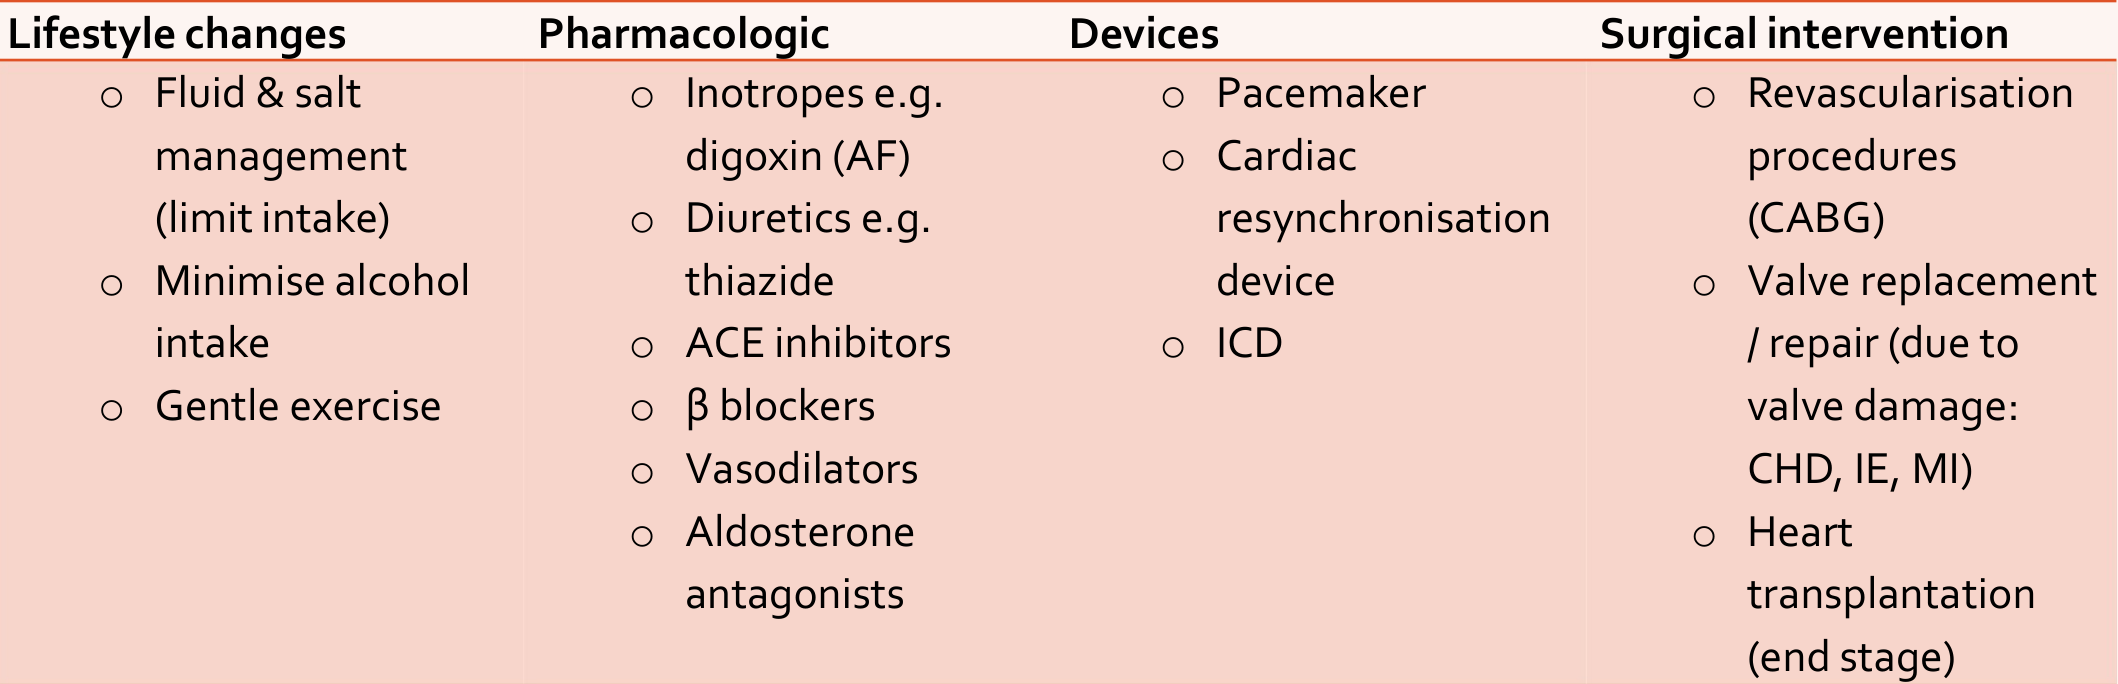
Cardiac Failure General Management89
| Lifestyle changes | Pharmacologic | Devices | Surgical intervention |
|---|---|---|---|
| Fluid & salt management (limit intake) | Inotropes e.g. digoxin (AF) | Pacemaker | Revascularisation procedures (CABG) |
| Minimise alcohol intake | Diuretics e.g. thiazide | Cardiac resynchronisation device | Valve replacement / repair (due to valve damage: CHD, IE, MI) |
| Gentle exercise | ACE inhibitors | ICD | Heart transplantation (end stage) |
| β blockers | |||
| Vasodilators | |||
| Aldosterone antagonists |
Heart Failure Dental Management9091
-
Do not undertake dental treatment unless medical practitioner advised HF is stable
-
Limit duration of dental procedures
-
Patient may be unable to lie horizontally
- Position dental chair with head higher than heart
- Comfortable position for sleeping → “how many pillows do you use when sleeping?”
-
Increased risk with sedation and GA → hospital environment with anaesthetist
-
Avoid NSAIDs if possible
- Especially if diuretic + (ACEI or A2RB) → risk of acute kidney injury
-
Diuretics + drugs with diuretic effect (e.g. dapagliflozin, empagliflozin) → dry mouth
-
May be candidate for heart transplant.
- Require dental assessment before being waitlisted
- Optimise oral health
- Use regular recalls and preventive management to optimise oral health and avoid delays if transplantation is required.
- May seek hospital dental specialist for advice for pre-transplant dental treatment plan
-
Severe heart failure patients should not be prescribed NSAIDs by a dentist.
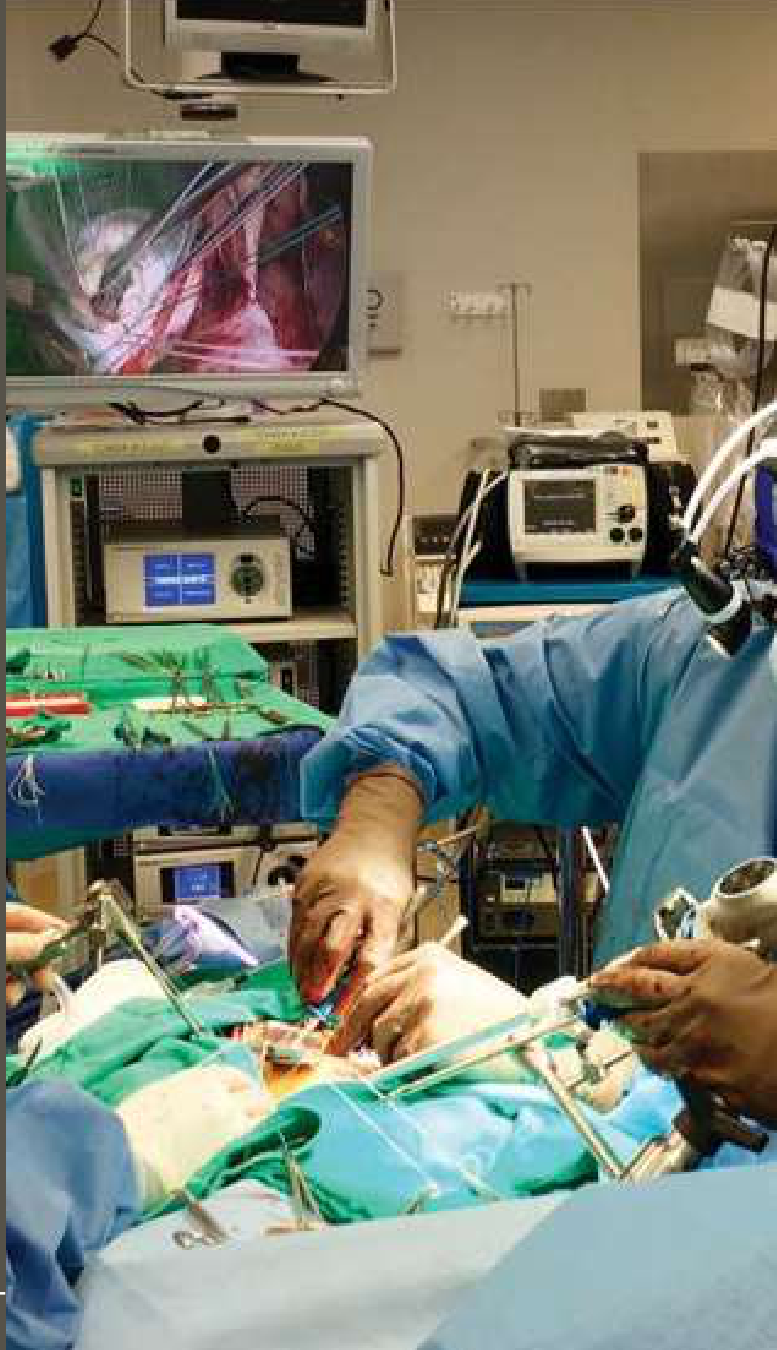
Cardiac Surgery and Perioperative Dental Management
- Coronary angioplasty and stent (bare metal or drug-eluting) = Percutaneous coronary intervention (PCI)
- Improve blood flow through occluded coronary arteries
- Coronary artery bypass grafting (CABG)
- Redirect blood flow around occluded coronary arteries
- Valve replacement or Transcatheter aortic valve implantation (TAVI)
- Replace faulty or damaged heart valves
- Congenital correction
- Repair abnormal or damaged structures
- Pacemaker or Implantable Cardioverter Defibrillator (ICD) placement
- Implant devices to control heart beat or support function / blood flow
- Cardiac Transplant
- Replace a damaged heart, severe heart failure
Lecturer — Stent Placement
A catheter-mounted balloon widens the blocked artery, and a wire mesh stent remains in place to keep it open.
- Stents may be bare metal, drug-eluting, or non-drug-eluting.
Types of Cardiac Surgery92
Cardiac Risks of Dental Treatment9394
- Risk stratification guidelines: Peri-operative risks for CVD patients undergoing non-cardiac surgical procedures
- H&N surgery 1-5%, dental surgery / superficial surgery <1%
- European Society of Cardiology (ESC) and European Society of Anaesthesiology (ESA) (Halvorsen et al., 2022)
- American College of Cardiology (ACC) and American Heart Association (AHA) (Thompson et al, 2024)
- Smith et al 2014:
- Prophylactic dental extractions prior to cardiac surgery carries a 3% risk of death and 8% risk of major adverse outcome before cardiac operation
Lecturer — Cardiac Stress
Non-cardiac surgery can precipitate a cardiac event because major surgery stresses the cardiovascular system.
- Patients with limited cardiac reserve may be unable to increase cardiac output adequately in response to stress.
- Increased adrenaline and catecholamines may cause tachycardia, coronary vasoconstriction, platelet aggregation, coagulation, and an adverse oxygen supply-demand balance.
- General anaesthetic agents may act directly on the myocardium, decrease muscular tone, produce hypotension, and cause compensatory tachycardia.
- Dental extraction is generally less extensive than head and neck surgery.
Smith MM, Barbara DW, Mauermann WJ, Viozzi CF, Dearani JA, Grim KJ. Morbidity and Mortality Associated with Dental Extraction Before Cardiac Operation. Ann Thorac Surg. 2014; 97: 838-44.
”… raises the question whether we should in fact get on with our cardiac operations and deal with the dental work at some other time, if at all, or risk killing patients with good intent!”
Lecturer — Extraction Risk
Subsequent commentaries questioned whether the risks reported for prophylactic dental extractions were as high as originally stated.
- In some cases, it may be safer to proceed with cardiac surgery first and perform elective dental treatment later.
Unsworth-White 2014 (commentary of Smith et al 2014)
Unsworth-White MJ. Invited Commentary - Morbidity and Mortality Associated with Dental Extraction Before Cardiac Operation. Ann Thorac Surg. 2014;97,844.
Risks Versus Benefits of Pre-Operative Dental Treatment
Management of perioperative acute pain and infection (pus, swelling, cellulitis) needs to be a joint decision between the dentist and the physicians caring for the patient planned for cardiothoracic surgery.
But when should we treat chronic, asymptomatic pathology?
Risks Outweigh Benefits95
- Ischaemic disease (eg. CABG, PCI, stent, angioplasty)
- Rhythmic disease (eg. ICD/pacemaker, ablation)
Benefits May Outweigh Risks
- Valvular disease (eg. replacement, repairs, TAVI)
- Infective endocarditis (often leads to valvular surgery)
- Heart transplant (heart failure)
Ischaemic Indications – Potential Benefits of Pre-Op Dental Treatment96
- Decrease endogenous catecholamine release (resulting in increased BP) if patient is in pain
- ?Reduce pre-operative infection risk or graft rejection
- Limited literature regarding dental extractions prior to CABG or heart transplant surgery
→ lack of clear evidence to support the reduced risk of post-operative infection (Meyer et al., 1999)
Lecturer — Ischaemic Timing
When cardiac surgery is being performed for an ischaemic indication alone, restoring coronary perfusion through stenting or bypass may reduce cardiac risk.
- It may therefore be safer to defer elective dental treatment until after perfusion has been restored.
- Evidence that pre-operative dental treatment reduces infection risk in this setting is limited.
Management of perioperative acute pain and infection (pus, swelling, cellulitis) needs to be a joint decision between the dentist and the physicians caring for the patient planned for cardiothoracic surgery.
But when should we treat chronic, asymptomatic pathology?
-
Ischaemic disease (eg. CABG, PCI, stent, angioplasty)
-
Rhythmic disease (eg. ICD/pacemaker, ablation)
-
Valvular disease (eg. replacement, repairs, TAVI)
-
Infective endocarditis (often leads to valvular surgery)
-
Heart transplant (heart failure)
Supporting Evidence: Pacemaker/ICD Infections97
Eberhard et al. Journal of Cardiothoracic Surgery 2013, 8:73. http://www.cardiothoracicsurgery.org/content/8/1/73
The oral cavity is not a primary source for implantable pacemaker or cardioverter defibrillator infections — Jörg Eberhard, Nico Stumpp, Fadi Ismail, Ulrike Schnaidt, Wieland Heuer, Maximilian Pichlmaier, Christian Kühn, Axel Haverich and Meike Stiesch
- Background: To test the hypothesis that the oral cavity is a potential source for implantable pacemaker and cardioverter defibrillator infections, the bacterial diversity on explanted rhythm heart management devices was investigated and compared to the oral microbiome.
- Methods: A metagenomic approach was used to analyze the bacterial diversity on the surfaces of non-infected and infected pacemakers. The DNA from surface swabs of 24 non-infected and 23 infected pacemakers was isolated and subjected to bacterial-specific DNA amplification, single strand conformation polymorphism- (SSCP) and sequencing analysis. Species-specific primer sets were used to analyze for any correlation between bacterial diversity on pacemakers and in the oral cavity.
- Results: DNA of bacterial origin was detected in 21 cases on infected pacemakers and assigned to the bacterial phylotypes Staphylococcus epidermidis, Propionibacterium acnes, Staphylococcus aureus, Staphylococcus schleiferi and Staphylococcus. In 17 cases bacterial DNA was found on pacemakers with no clinical signs of infections. On the basis of the obtained sequence data, the phylotypes Propionibacterium acnes, Staphylococcus and an uncultured bacterium were identified. Propionibacterium acnes and Staphylococcus epidermidis were the only bacteria detected in pacemaker (n = 25) and oral samples (n = 11).
- Conclusions: The frequency of the coincidental detection of bacteria on infected devices and in the oral cavity is low and the detected bacteria are highly abundant colonizers of non-oral human niches. The transmission of oral bacteria to the lead or device of implantable pacemaker or cardioverter defibrillators is unlikely relevant for the pathogenesis of pacemaker or cardioverter defibrillator infections.
Lecturer — Device Prophylaxis
The presence of a pacemaker or implantable cardioverter defibrillator alone is not an indication for dental antibiotic prophylaxis.
- A patient with an implantable cardiac device may be better treated after the cardiac condition is controlled.
Keywords: Biofilm, Infection, Pacemaker, Defibrillator, Oral cavity
Management of perioperative acute pain and infection (pus, swelling, cellulitis) needs to be a joint decision between the dentist and the physicians caring for the patient planned for cardiothoracic surgery.
But when should we treat chronic, asymptomatic pathology?
- Valvular disease (eg. replacement, repairs, TAVI)
- Infective endocarditis (often leads to valvular surgery)
- Heart transplant (heart failure)
Supporting Evidence: Dental Treatment Before Cardiac Valve Surgery98
Lockhart PB, DeLong HR, Lipman RD, Abt E, Baddour LM, Colvin M, Miller CS, Sollecito T, O’Brien K, Estrich CG, Araujo MWB, Carrasco-Labra A. Effect of dental treatment before cardiac valve surgery: Systematic review and meta-analysis. JADA 2019;150(9):739-747. https://doi.org/10.1016/j.adaj.2019.04.024
- Background: The purpose of this systematic review was to determine the potential effect of dental treatment before cardiac valve surgery (CVS) or left ventricular assist device (LVAD) implantation on morbidity and mortality.
- Types of Studies Reviewed: The authors included relevant studies from MEDLINE, Embase, and the Cochrane Central Register of Controlled Trials, including randomized controlled trials and cohort studies, published from 1998 through 2019 and involving adults who received dental treatment before CVS or LVAD implantation. The authors assessed bias by using the Newcastle-Ottawa Quality Assessment Scale and evidence certainty by using the Grading of Recommendations Assessment, Development and Evaluation approach. The authors used a meta-analysis with a random-effects model to estimate dichotomous and continuous outcomes, expressed as relative risk (RR) and weighted mean difference.
- Results: Six studies met the inclusion criteria for CVS but none for LVAD implantation. Very low certainty in the evidence suggested uncertainty as to whether health outcomes for patients undergoing dental treatment before CVS differed from those who did not. Postsurgical outcomes included all-cause mortality (RR, 1.00; 95% confidence interval [CI], 0.53 to 1.91), infective endocarditis (RR, 1.30; 95% CI, 0.51 to 3.35), postsurgical infection (RR, 1.01; 95% CI, 0.76 to 1.33), and length of stay in the hospital (weighted mean difference, 2.9; 95% CI, −2.3 to 8.1).
- Conclusions and Practical Implications: From the available evidence, it is unclear whether postoperative outcomes differ in patients receiving dental treatment before CVS compared with outcomes in those who do not. Dentists and medical care professionals should collaborate on an appropriate course of action for each patient, weighing any potentially relevant care considerations.
Lecturer — Valve Surgery Decisions
Cardiologists may be particularly concerned about infective endocarditis in patients undergoing valve surgery.
- Because infective endocarditis has substantial morbidity and mortality, dental treatment is often undertaken before valve surgery despite uncertainty in the evidence.
Key Words: Cardiac; pretreatment; medically complex; presurgical; dental clearance.
Management of perioperative acute pain and infection (pus, swelling, cellulitis) needs to be a joint decision between the dentist and the physicians caring for the patient planned for cardiothoracic surgery.
But when should we treat chronic, asymptomatic pathology?
- Valvular disease (eg. replacement, repairs, TAVI)
- Infective endocarditis (often leads to valvular surgery)
- Heart transplant (heart failure)
Supporting Evidence: Heart Transplants – Assessment of Dental Procedures99
Meyer U, Weingart D, Deng MC, Scheld HH, Joos U. Heart transplants – assessment of dental procedures. Clin Oral Invest (1999) 3:79–83. © Springer-Verlag 1999.
- Abstract: The object of this study was to evaluate the effects of dental foci on survival rates and rejection episodes in heart transplant recipients. Therefore, in a retrospective longitudinal study we studied 74 heart transplant recipients at the Department of Maxillofacial Surgery and Department of Thoracic and Cardiovascular Surgery, University of Münster. Study patients were divided into groups: those in which dental foci had been verified (n=31) and those without dental foci (n=43). Statistical analysis was performed using the chi-square test, Kaplan-Meier life table analysis, and the log-rank test. Before heart transplantation, patients were screened clinically and radiographically to determine the extent of dental foci. Postoperatively, patients were evaluated dentally and medically to identify the impact of dental foci on the incidence of systemic and oral infections, frequency and severity of rejection episodes, mortality, and complications arising during dental treatment. By comparing the mortality, infection and rejection rates in the various groups no statistically significant differences (P>0.05) were found between patients. Despite immunosuppression, extended inflammatory processes such as abscess formation or viral stomatitis were not found in the oral cavity. We therefore suggest that patients suffering from the symptoms of severe heart failure need not be subjected to rigorous preoperative dental treatment.
Key words: Heart transplant · Dental treatment · Mortality
- Introduction: The survival rate of patients after heart transplantation has improved due to recent advances in perioperative management and immunosuppression. Preoperative evaluation includes assessment of dental foci and their subsequent eradication. So far, no study has examined the need for such a radical approach. Most microorganisms associated with bacteremia in patients with heart transplantation are commensal organisms of the oral cavity. Systemic infections and rejection dramatically decrease the survival rate in patients subjected to heart transplantation. Since odontogenic inflammation may favor transplant rejection, cause bacterial endocarditis and may lead to life-threatening postoperative infections, all existing or potential sources of dental infection should be eliminated before heart transplantation. To our knowledge, specific guidelines specifying the extent of such dental procedures do not exist. The purpose of this study was to analyze the complication rates in patients in whom dental foci had been verified as compared with patients without dental foci so that the role of these foci on the postoperative outcome of heart transplantation could be determined. The influence of various dental foci on differences in survival and rejection probabilities of heart transplant recipients was investigated to reevaluate our dental treatment protocol.
Lecturer — Transplant Assessment
Evidence remains limited regarding whether dental treatment before heart transplantation reduces postoperative infection, mortality, or organ rejection.
- Patients become immunosuppressed after transplantation to prevent rejection, so infection is a concern.
- Patients may therefore benefit from dental assessment before transplantation.

Decision Making for Dental Treatment Before Cardiac Surgery
Assessing Risk100
- Dental treatment need
- Severity of cardiac disease (e.g. chest pain at rest, triggers/frequency, number of medications)
- Type and magnitude of dental procedure
- Stability and cardiopulmonary reserve (functional capacity)
→ Recommendation: integrated team decision based on individual situation of the patient (stable vs unstable condition)
Lecturer — Risk Assessment
Assessment should include the symptoms caused by dental infection and the risk of systemic complications from dental disease.
- Also consider the treatment burden, the number and type of cardiac medications, and the patient’s functional capacity and cardiopulmonary reserve.
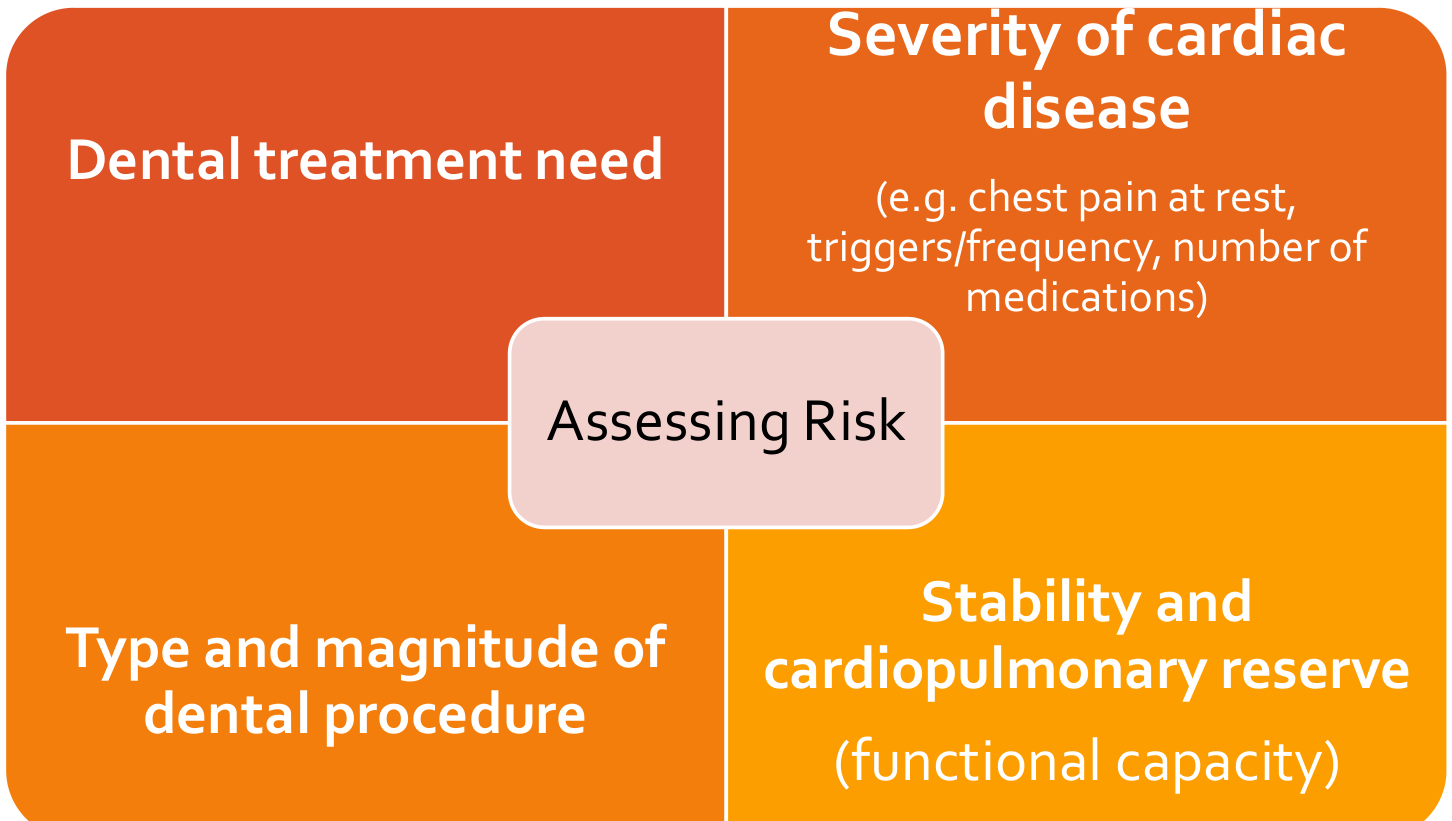
Timing of Dental Treatment After Cardiac Events
How far ahead to future proof?101
“IN THE 12 MONTHS AFTER MYOCARDIAL INFARCTION, STENT PLACEMENT, CORONARY ARTERY BYPASS SURGERY, OR VALVE PROCEDURES (INCLUDING TRANSCATHETER AORTIC VALVE IMPLANTATION [TAVI]), PATIENTS ARE AT INCREASED RISK OF A MAJOR ADVERSE CARDIAC EVENT (EG SUDDEN DEATH).
DEFER ELECTIVE DENTAL TREATMENT FOR 6 MONTHS AFTER MYOCARDIAL INFARCTION, STENT PLACEMENT, CORONARY ARTERY BYPASS SURGERY OR VALVE PROCEDURE.
IF DENTAL PAIN OR INFECTION OCCURS WITHIN 6 MONTHS FOLLOWING THE EVENT, PROVIDE ADEQUATE EMERGENCY TREATMENT BUT AVOID THE USE OF ADRENALINE-CONTAINING LOCAL ANAESTHETICS. CONSIDER SEEKING SPECIALIST ADVICE ABOUT APPROPRIATE TREATMENT AND TIMING OF PROCEDURES.”
Lecturer — Future Proofing
Pre-operative dental treatment is not necessarily intended to provide comprehensive dental rehabilitation.
- Assess how long each dental problem is likely to remain stable and focus on conditions likely to cause problems while elective dental care is deferred.
- Early caries that is unlikely to cause a problem during the relevant six-month period may not require immediate treatment, because unnecessary treatment adds physiological stress.
Oral & Dental Therapeutic Guidelines v4 2026
Lecturer — Emergency Timing
The six-month deferral reflects historic concerns about reinfarction, mortality, healing of necrotic myocardium, and development of collateral circulation.
- Emergency treatment during this period may require specialist advice, a medically monitored hospital setting, ECG or pulse oximetry monitoring, and intravenous sedation or an anaesthetist where appropriate.
- Cardiac rehabilitation and exercise-tolerance testing may help determine recovery and the timing of later dental treatment.
Thinking It Through Cardiac Surgery
Rationale102
- Does need for dental treatment outweigh the cardiac risks?
- Direct effect on cardiac outcome = Endocarditis risk
Medical, Dental and Social Considerations
- Bacteraemia risk of dental pathology
- Amount of treatment patient can tolerate in one go vs risks of performing over multiple visits
- Anticoagulation / antiplatelet drugs (prophylactic vs therapeutic)
- Antibiotic prophylaxis
- Focus on preventive oral hygiene to ↓ daily bacteraemia
- Entire or localised areas of the mouth — entire dentition
Lecturer — Treatment Burden
If many teeth require removal, the patient may not tolerate complete treatment in one appointment.
- Spreading treatment across appointments may increase the number of episodes requiring antibiotic prophylaxis and anticoagulant considerations.
- The medical, dental, and social context should be considered together.
Optimal Timeframes
- Urgency for cardiac surgery
- Future-proof for next 6 months (i.e. optimise for the short-term)
Treatment Approaches
- Aggressive (e.g. typically insufficient time to assess periapical response to RCT)
Lecturer — Aggressive Treatment
For a tooth with infection, extraction may provide a more definitive treatment than root canal treatment when there is insufficient time to assess the periapical response.
- The aim is to address dental conditions most likely to cause problems while elective treatment will be deferred.
- Preventive care and oral hygiene remain important, but treatment should be proportionate to the cardiac situation and the patient’s capacity.
Questions103
Lecturer — Clinical Framework
Study by applying a consistent framework rather than memorising every list or table.
- Use definition, aetiology and epidemiology, general manifestations and management, oral manifestations and management, risk assessment, and access, communication, consent, education, surgery, and spread.
- Clinical questions may use patient cases, so apply the framework to a scenario and consider what happens when a patient returns to general dental practice after hospital treatment.
Audio Appendix
Additional Audio Content
These lecturer notes could not be placed against a slide in the notes.
Lecturer notes that could not be placed against a slide
-
Carditis occurs in approximately 50% of acute rheumatic fever cases.
-
Diuretics such as furosemide, ACE inhibitors and beta blockers may be used in managing complications.
Footnotes
-
Original PDF page 1: L1 Cardiovascular Disease and Dentistry, p.1 ↩
-
Original PDF page 2: L1 Cardiovascular Disease and Dentistry, p.2 ↩
-
Original PDF page 3: L1 Cardiovascular Disease and Dentistry, p.3 ↩
-
Original PDF page 4: L1 Cardiovascular Disease and Dentistry, p.4 ↩
-
Original PDF page 5: L1 Cardiovascular Disease and Dentistry, p.5 ↩
-
Original PDF page 6: L1 Cardiovascular Disease and Dentistry, p.6 ↩
-
Original PDF page 7: L1 Cardiovascular Disease and Dentistry, p.7 ↩
-
Original PDF page 8: L1 Cardiovascular Disease and Dentistry, p.8 ↩
-
Original PDF page 9: L1 Cardiovascular Disease and Dentistry, p.9 ↩
-
Original PDF page 10: L1 Cardiovascular Disease and Dentistry, p.10 ↩
-
Original PDF page 11: L1 Cardiovascular Disease and Dentistry, p.11 ↩
-
Original PDF page 12: L1 Cardiovascular Disease and Dentistry, p.12 ↩
-
Original PDF page 13: L1 Cardiovascular Disease and Dentistry, p.13 ↩
-
Original PDF page 14: L1 Cardiovascular Disease and Dentistry, p.14 ↩
-
Original PDF page 15: L1 Cardiovascular Disease and Dentistry, p.15 ↩
-
Original PDF page 16: L1 Cardiovascular Disease and Dentistry, p.16 ↩
-
Original PDF page 17: L1 Cardiovascular Disease and Dentistry, p.17 ↩
-
Original PDF page 19: L1 Cardiovascular Disease and Dentistry, p.19 ↩
-
Original PDF page 18: L1 Cardiovascular Disease and Dentistry, p.18 ↩
-
Original PDF page 20: L1 Cardiovascular Disease and Dentistry, p.20 ↩
-
Original PDF page 21: L1 Cardiovascular Disease and Dentistry, p.21 ↩
-
Original PDF page 23: L1 Cardiovascular Disease and Dentistry, p.23 ↩
-
Original PDF page 24: L1 Cardiovascular Disease and Dentistry, p.24 ↩
-
Original PDF page 22: L1 Cardiovascular Disease and Dentistry, p.22 ↩
-
Original PDF page 25: L1 Cardiovascular Disease and Dentistry, p.25 ↩
-
Original PDF page 26: L1 Cardiovascular Disease and Dentistry, p.26 ↩
-
Original PDF page 27: L1 Cardiovascular Disease and Dentistry, p.27 ↩
-
Original PDF page 28: L1 Cardiovascular Disease and Dentistry, p.28 ↩
-
Original PDF page 29: L1 Cardiovascular Disease and Dentistry, p.29 ↩
-
Original PDF page 30: L1 Cardiovascular Disease and Dentistry, p.30 ↩
-
Original PDF page 31: L1 Cardiovascular Disease and Dentistry, p.31 ↩
-
Original PDF page 32: L1 Cardiovascular Disease and Dentistry, p.32 ↩
-
Original PDF page 34: L1 Cardiovascular Disease and Dentistry, p.34 ↩
-
Original PDF page 33: L1 Cardiovascular Disease and Dentistry, p.33 ↩
-
Original PDF page 36: L1 Cardiovascular Disease and Dentistry, p.36 ↩
-
Original PDF page 35: L1 Cardiovascular Disease and Dentistry, p.35 ↩
-
Original PDF page 37: L1 Cardiovascular Disease and Dentistry, p.37 ↩
-
Original PDF page 38: L1 Cardiovascular Disease and Dentistry, p.38 ↩
-
Original PDF page 39: L1 Cardiovascular Disease and Dentistry, p.39 ↩
-
Original PDF page 40: L1 Cardiovascular Disease and Dentistry, p.40 ↩
-
Original PDF page 41: L1 Cardiovascular Disease and Dentistry, p.41 ↩
-
Original PDF page 43: L1 Cardiovascular Disease and Dentistry, p.43 ↩
-
Original PDF page 42: L1 Cardiovascular Disease and Dentistry, p.42 ↩
-
Original PDF page 44: L1 Cardiovascular Disease and Dentistry, p.44 ↩
-
Original PDF page 45: L1 Cardiovascular Disease and Dentistry, p.45 ↩
-
Original PDF page 46: L1 Cardiovascular Disease and Dentistry, p.46 ↩
-
Original PDF page 50: L1 Cardiovascular Disease and Dentistry, p.50 ↩
-
Original PDF page 47: L1 Cardiovascular Disease and Dentistry, p.47 ↩
-
Original PDF page 48: L1 Cardiovascular Disease and Dentistry, p.48 ↩
-
Original PDF page 49: L1 Cardiovascular Disease and Dentistry, p.49 ↩
-
Original PDF page 51: L1 Cardiovascular Disease and Dentistry, p.51 ↩
-
Original PDF page 52: L1 Cardiovascular Disease and Dentistry, p.52 ↩
-
Original PDF page 53: L1 Cardiovascular Disease and Dentistry, p.53 ↩
-
Original PDF page 54: L1 Cardiovascular Disease and Dentistry, p.54 ↩
-
Original PDF page 55: L1 Cardiovascular Disease and Dentistry, p.55 ↩
-
Original PDF page 56: L1 Cardiovascular Disease and Dentistry, p.56 ↩
-
Original PDF page 57: L1 Cardiovascular Disease and Dentistry, p.57 ↩
-
Original PDF page 58: L1 Cardiovascular Disease and Dentistry, p.58 ↩
-
Original PDF page 59: L1 Cardiovascular Disease and Dentistry, p.59 ↩
-
Original PDF page 60: L1 Cardiovascular Disease and Dentistry, p.60 ↩
-
Original PDF page 61: L1 Cardiovascular Disease and Dentistry, p.61 ↩
-
Original PDF page 62: L1 Cardiovascular Disease and Dentistry, p.62 ↩
-
Original PDF page 63: L1 Cardiovascular Disease and Dentistry, p.63 ↩
-
Original PDF page 64: L1 Cardiovascular Disease and Dentistry, p.64 ↩
-
Original PDF page 65: L1 Cardiovascular Disease and Dentistry, p.65 ↩
-
Original PDF page 66: L1 Cardiovascular Disease and Dentistry, p.66 ↩
-
Original PDF page 67: L1 Cardiovascular Disease and Dentistry, p.67 ↩
-
Original PDF page 68: L1 Cardiovascular Disease and Dentistry, p.68 ↩
-
Original PDF page 69: L1 Cardiovascular Disease and Dentistry, p.69 ↩
-
Original PDF page 70: L1 Cardiovascular Disease and Dentistry, p.70 ↩
-
Original PDF page 71: L1 Cardiovascular Disease and Dentistry, p.71 ↩
-
Original PDF page 72: L1 Cardiovascular Disease and Dentistry, p.72 ↩
-
Original PDF page 73: L1 Cardiovascular Disease and Dentistry, p.73 ↩
-
Original PDF page 74: L1 Cardiovascular Disease and Dentistry, p.74 ↩
-
Original PDF page 75: L1 Cardiovascular Disease and Dentistry, p.75 ↩
-
Original PDF page 76: L1 Cardiovascular Disease and Dentistry, p.76 ↩
-
Original PDF page 77: L1 Cardiovascular Disease and Dentistry, p.77 ↩
-
Original PDF page 78: L1 Cardiovascular Disease and Dentistry, p.78 ↩
-
Original PDF page 80: L1 Cardiovascular Disease and Dentistry, p.80 ↩
-
Original PDF page 79: L1 Cardiovascular Disease and Dentistry, p.79 ↩
-
Original PDF page 81: L1 Cardiovascular Disease and Dentistry, p.81 ↩
-
Original PDF page 82: L1 Cardiovascular Disease and Dentistry, p.82 ↩
-
Original PDF page 83: L1 Cardiovascular Disease and Dentistry, p.83 ↩
-
Original PDF page 84: L1 Cardiovascular Disease and Dentistry, p.84 ↩
-
Original PDF page 85: L1 Cardiovascular Disease and Dentistry, p.85 ↩
-
Original PDF page 86: L1 Cardiovascular Disease and Dentistry, p.86 ↩
-
Original PDF page 87: L1 Cardiovascular Disease and Dentistry, p.87 ↩
-
Original PDF page 88: L1 Cardiovascular Disease and Dentistry, p.88 ↩
-
Original PDF page 89: L1 Cardiovascular Disease and Dentistry, p.89 ↩
-
Original PDF page 90: L1 Cardiovascular Disease and Dentistry, p.90 ↩
-
Original PDF page 91: L1 Cardiovascular Disease and Dentistry, p.91 ↩
-
Original PDF page 92: L1 Cardiovascular Disease and Dentistry, p.92 ↩
-
Original PDF page 93: L1 Cardiovascular Disease and Dentistry, p.93 ↩
-
Original PDF page 94: L1 Cardiovascular Disease and Dentistry, p.94 ↩
-
Original PDF page 95: L1 Cardiovascular Disease and Dentistry, p.95 ↩
-
Original PDF page 96: L1 Cardiovascular Disease and Dentistry, p.96 ↩
-
Original PDF page 97: L1 Cardiovascular Disease and Dentistry, p.97 ↩
-
Original PDF page 98: L1 Cardiovascular Disease and Dentistry, p.98 ↩
-
Original PDF page 99: L1 Cardiovascular Disease and Dentistry, p.99 ↩
-
Original PDF page 100: L1 Cardiovascular Disease and Dentistry, p.100 ↩
-
Original PDF page 101: L1 Cardiovascular Disease and Dentistry, p.101 ↩
-
Original PDF page 102: L1 Cardiovascular Disease and Dentistry, p.102 ↩
-
Original PDF page 103: L1 Cardiovascular Disease and Dentistry, p.103 ↩